Doctors Revision

Anatomy

The Neck
Anatomy

The Neck

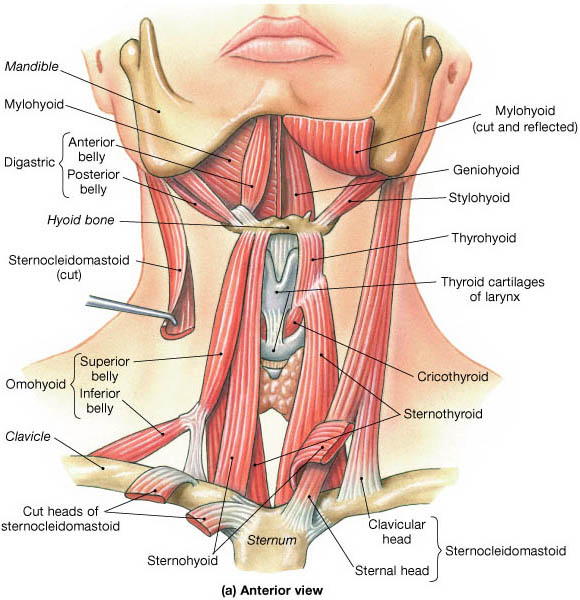
Anatomy of the Neck Module Learning Objectives By the conclusion of this exhaustive anatomical master guide, you will be deeply conversant with: The anatomical boundaries and the longitudinal compartmentalization of the neck. The detailed organization of the Anterior and Posterior Triangles, including their precise subdivisions and boundaries. The origins, insertions, innervations, and functions of the Suprahyoid and Infrahyoid (Strap) muscles. The complete Carotid Arterial System (Common, Internal, and External) along with the extensive branches of the External Carotid Artery. The major venous drainage of the neck, primarily focusing on the Internal Jugular Vein (IJV). The precise routing and innervation targets of the Cranial and Peripheral Nerves within the neck. The comprehensive anatomy, blood supply, and surgical relations of the Thyroid and Parathyroid Glands. I. Introduction and Boundaries of the Neck The neck is the vital, transitional anatomical tube providing critical continuity from the head to the trunk. It acts as a major conduit for the spinal cord, massive blood vessels supplying the brain, and the upper digestive and respiratory tracts. Defining the Anatomical Extent Anteriorly: The neck extends from the lower border of the mandible (jawbone) superiorly, down to the upper surface of the manubrium of the sternum inferiorly. Posteriorly: It extends from the superior nuchal line on the occipital bone of the skull superiorly, down to the intervertebral disc located between the C7 (Vertebra Prominens) and T1 vertebrae inferiorly. II. Longitudinal Organization: Compartments and Fascia Within this vital tube, the structures are highly organized into four distinct longitudinal compartments. These compartments are tightly bound by tough layers of deep cervical fascia, which serve not only to organize structures but to dictate the potential spread of deep neck infections. The Four Compartments The Visceral Compartment: Located anteriorly. It contains the vital tubular organs of the digestive and respiratory systems (Pharynx, Larynx, Trachea, and Esophagus), as well as several endocrine glands (Thyroid and Parathyroid glands). The Vertebral Compartment: Located posteriorly. It contains the rigid cervical vertebrae, the delicate spinal cord, exiting cervical nerves, and the postural muscles associated with the vertebral column. The Two Vascular Compartments (Left and Right): Located laterally on each side. They are encapsulated by the Carotid Sheath and contain the major blood vessels (Common/Internal Carotid Arteries and Internal Jugular Veins) as well as the Vagus nerve [CN X]. Fascial Layers of the Neck The neck is wrapped in layers of deep cervical fascia that enclose these compartments: Investing Fascia: Surrounds the entire neck like a collar, enclosing the SCM and Trapezius muscles. Pretracheal Fascia: Specifically encloses the anterior Visceral compartment (Thyroid, trachea, esophagus). Prevertebral Fascia: Encloses the posterior Vertebral compartment. Carotid Sheath: Encloses the lateral Vascular compartments. III. The Triangles of the Neck For descriptive, surgical, and diagnostic purposes, the neck is divided into two massive geometric regions separated by the diagonally placed Sternocleidomastoid (SCM) muscle: The Anterior Triangle and the Posterior Triangle. 1. The Posterior Triangle Located on the lateral aspect of the neck, behind the SCM. Anterior Boundary: The posterior border of the Sternocleidomastoid (SCM) muscle. Posterior Boundary: The anterior border of the Trapezius muscle. Inferior Boundary (Base): The middle one-third of the clavicle (collarbone). 2. The Anterior Triangle Located in the front of the neck, containing the most vital visceral and vascular structures. Lateral Boundary: The anterior border of the Sternocleidomastoid (SCM) muscle. Superior Boundary (Base): The inferior border of the mandible. Medial Boundary: The exact midline of the neck (from the chin down to the sternum). Subdivisions of the Anterior Triangle Because the anterior triangle is large and highly complex, anatomists further subdivide it into four smaller triangles using the Digastric and Omohyoid muscles as intersecting borders. The Submandibular Triangle: Outlined by the inferior border of the mandible superiorly, and the anterior and posterior bellies of the digastric muscle inferiorly. (Houses the submandibular salivary gland). The Submental Triangle: Outlined by the hyoid bone inferiorly, the anterior belly of the digastric muscle laterally, and the midline of the neck. (Located directly under the chin). The Muscular Triangle: Outlined by the hyoid bone superiorly, the superior belly of the omohyoid muscle and the anterior border of the SCM muscle laterally, and the midline of the neck. (Houses the infrahyoid strap muscles and thyroid gland). The Carotid Triangle: Outlined by the superior belly of the omohyoid muscle anteroinferiorly, the stylohyoid muscle and posterior belly of the digastric superiorly, and the anterior border of the SCM posteriorly. (Crucial surgical access point to the Carotid arterial system). IV. Musculature of the Anterior Triangle The muscles in the anterior triangle are primarily responsible for the complex movements of swallowing, speaking, and protecting the airway. They are logically grouped according to their physical location relative to the Hyoid bone (a U-shaped bone that does not articulate with any other bone). A. The Suprahyoid Muscles Located superior (above) the hyoid bone. They occupy the submental and submandibular triangles. They pass in a superior direction from the hyoid bone up to the skull or mandible. Primary Action: They raise/elevate the hyoid bone and the floor of the mouth, which is a critical action during swallowing. Muscle Innervation Action / Characteristics 1. Stylohyoid Facial nerve [CN VII] Pulls the hyoid bone posterosuperiorly (backward and upward) during swallowing. 2. Digastric Posterior belly: Facial nerve [CN VII]Anterior belly: Trigeminal nerve [CN V] Has two distinct bellies connected by an intermediate tendon which attaches to the body of the hyoid bone via a fibrous sling. 3. Mylohyoid Trigeminal nerve [CN V] Forms a muscular sling that supports and elevates the floor of the mouth and elevates the hyoid bone. 4. Geniohyoid Branch from anterior ramus of C1 (carried along the Hypoglossal nerve [CN XII]) Has two distinct functions depending on which bone is fixed:– If mandible is fixed: Elevates and pulls the hyoid forward.– If hyoid is fixed: Pulls the mandible downward and inward (opening the jaw). B. The Infrahyoid Muscles (Strap Muscles) Located inferior (below) the hyoid bone, occupying the muscular triangle. Because of their long, flat, ribbon-like appearance, they are widely referred to
Osteology (Vertebrae & Skull)
Anatomy

Osteology (Vertebrae & Skull)

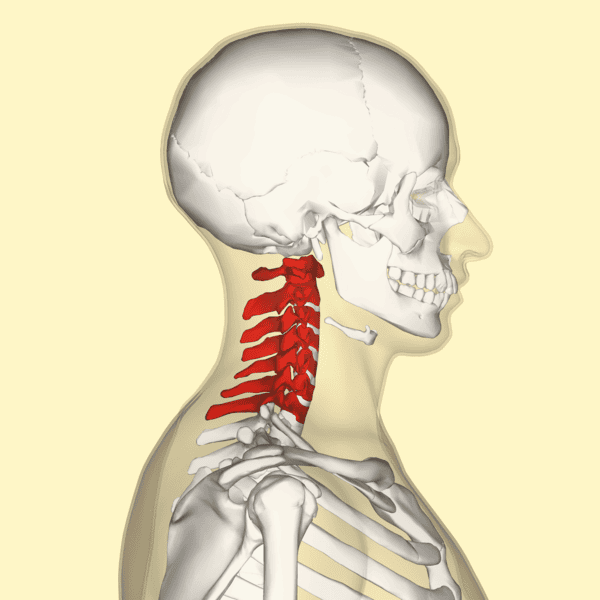
Anatomy of the Skull and Cervical Vertebrae Module Learning Objectives By the conclusion of this exhaustive anatomical master guide, you will be deeply conversant with: The structural division of the human skeleton into the Axial and Appendicular systems. The comprehensive anatomy of the 22 bones of the Skull (Cranial and Facial bones), their specific landmarks, and critical physiological functions. The functional articulation of individual skull bones, including sutures, foramina, and processes. The structural organization of the Vertebral Column, with a specific, deep focus on the cervical region. The precise morphological differences between Typical and Atypical Cervical Vertebrae (Atlas, Axis, and Vertebra Prominens). Relevant clinical correlations, including fractures, joint dislocations, and developmental anomalies associated with these osseous structures. I. Introduction to the Skeletal System The human skeleton is a dynamic, living framework providing support, protection, hematopoiesis (blood cell production), and mineral storage. It consists of 206 bones in the adult body and is divided into two primary functional divisions: 1. The Axial Skeleton Forms the central longitudinal axis of the body. It consists of 80 bones designed primarily for the protection of vital organs (brain, spinal cord, heart, and lungs) and support. Components: The Skull, the Hyoid bone, the Auditory Ossicles, the Vertebral Column, and the Thoracic Cage (Ribs and Sternum). 2. The Appendicular Skeleton Consists of the appendages (limbs) and the girdles that attach them to the axial skeleton. It consists of 126 bones designed primarily for movement and environmental interaction. Components: Pectoral (shoulder) girdles, Upper limbs, Pelvic (hip) girdle, and Lower limbs. II. The Skull: Cranial and Facial Bones The skull is the most complex bony structure in the body. It consists of 22 distinct bones (28 if you include the 6 auditory ossicles deep within the ear). The skull’s primary functions are to enclose and protect the fragile brain, house the special sense organs (sight, hearing, smell, taste), and provide attachment sites for the muscles of mastication (chewing) and facial expression. The skull is sub-divided into two main anatomical and developmental categories: Cranial Bones (Neurocranium): 8 bones that form the protective cranial vault (braincase). Facial Bones (Viscerocranium): 14 bones that form the anterior aspect of the face, the orbital cavities, and the nasal and oral cavities.

Associated Structures
Anatomy

Associated Structures

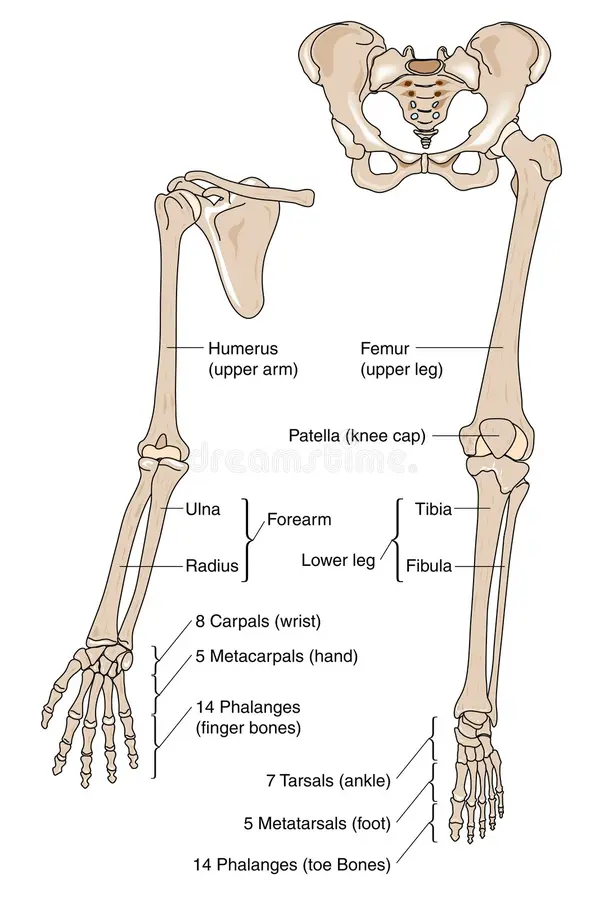
Foundational Principles of Associated Structures & Regional Anatomy An exhaustive, deeply expanded master guide based on the foundational principles of macroscopic gross anatomy. Expanded with advanced clinical correlations, surgical significance, and anatomical variations. Module Learning Objectives By the conclusion of this comprehensive guide, you will be deeply conversant with: The structural and functional definitions of associated anatomical structures and fascial compartmentalization. The highly detailed topography and contents of key transition zones: the Axilla, Cubital Fossa, Carpal Tunnel, Femoral Triangle, Gluteal Region, Popliteal Fossa, and Tarsal Tunnel. The precise spatial relationships within neurovascular bundles and their vulnerability to mechanical trauma. Advanced clinical integration including specific fracture-associated nerve injuries and the pathophysiology of chronic entrapment neuropathies. CHAPTER 1: FOUNDATIONAL PRINCIPLES OF ASSOCIATED STRUCTURES 1.1 Structural and Functional Definition In macroscopic gross anatomy, a primary structure (such as a specific bone like the humerus, or a discrete muscle pack like the biceps brachii) does not exist, nor does it function, in isolation. The term associated structures defines the immediate, localized network of accessory features that provide structural stability, metabolic maintenance, waste elimination, and neural control to that primary feature. When analyzing any musculoskeletal region, a clinician or anatomist’s focus must extend far beyond simple origins and insertions to encompass these deeply interdependent relationships: Primary Anatomical Structure Ecosystem Investing Deep Fascia: Compartmentalization & Boundary Management. Acts as a biological “stocking” keeping tissues under pressure. Arterial Supply & Collateral Anastomoses: Nutrient and oxygen inflow. Collaterals provide critical alternative pathways during arterial occlusion. Venae Comitantes & Superficial Drainage: Metabolic outflow and thermoregulation. Motor / Sensory Innervation: Functional activation (efferent) and proprioceptive/pain feedback (afferent). Synovial Bursae & Tendon Sheaths: Kinematic friction reduction, ensuring smooth gliding of structures over bony prominences. 1.2 The Fascial Framework and Compartmentalization Deep fascia serves as the foundational structural scaffolding of the limbs. It forms a dense, unyielding, inelastic sleeve of connective tissue (predominantly collagen) around deep structures. Investing Fascia: Extends from the outer fascial sleeve deep into the core of the limb, attaching directly to periosteal bony landmarks (the outer lining of the bones). Intermuscular Septa: These are thick, fibrous walls that divide limbs into discrete, walled-off anatomical compartments (e.g., separating the anterior flexors from the posterior extensors in the arm). Functional Isolation: Compartmentalization perfectly groups muscles with similar actions, shared embryonic origins, and identical neurovascular supplies. Example: All muscles in the anterior compartment of the arm are flexors and are uniformly innervated by the musculocutaneous nerve. Clinical Relevance: Acute Compartment Syndrome Because the fascial boundaries are exceptionally rigid and unyielding, they severely limit the expansion of fluid. In clinical emergencies (like a crush injury, severe burn, or massive bone fracture), bleeding or inflammatory edema causes tissue swelling. Because the fascia cannot stretch, internal compartment pressure skyrockets. This pressure rapidly collapses the low-pressure venous drainage, followed by the capillary beds, and finally arterial inflow. This compresses the associated neurovascular bundles, leading to agonizing pain out of proportion to the injury, pulselessness, pallor, paresthesia, and rapid ischemic tissue necrosis (muscle death). The only definitive treatment is an emergency surgical fasciotomy (slicing the fascia open to relieve the pressure). 1.3 Architecture of Neurovascular Bundles Blood vessels and nerves rarely travel independently through limb tissues; they are intimately organized into highly protected, integrated neurovascular bundles. The Protective Sleeve: Wrapped inside a shared connective tissue sheath, an artery, its corresponding deep veins (venae comitantes), and a regional peripheral nerve course together through specialized fascial planes. This sheath protects them from stretching and shearing forces. Venae Comitantes Dynamics (The Arteriovenous Pump): Deep veins typically flank their corresponding artery in pairs. The structural expansion of the pulsing high-pressure artery mechanically compresses these flanking, valved veins. This physical “milking” action forces venous blood upward against gravity toward the heart. They also serve a thermoregulatory function via countercurrent heat exchange (warm arterial blood warms the returning cold venous blood). Bony Trajectories: These bundles frequently run along specialized grooves or depressions across bony surfaces (e.g., the radial groove of the humerus). While this protects them from external trauma, it leaves them exceptionally vulnerable to tearing or compression during bone displacements, dislocations, or fractures. CHAPTER 2: HIGH-YIELD ASSOCIATED STRUCTURES OF THE UPPER LIMB 2.1 The Axilla: The Primary Transition Zone The axilla (armpit) is a complex, pyramid-shaped gateway facilitating the crucial transit of major neurovascular structures from the root of the neck down into the free upper extremity. It represents the major distribution hub of the upper limb. Boundary Structures of the Axillary Pyramid Apex (Cervicoaxillary Canal): The narrow superior opening bounded anteriorly by the clavicle, medially by the outer border of the first rib, and posteriorly by the superior border of the scapula. This is the entry point from the neck. Base: Formed by the tough axillary fascia and the overlying hairy skin of the armpit. Anterior Wall: Formed prominently by the pectoralis major and pectoralis minor muscles, thoroughly supported by the clavipectoral fascia. Posterior Wall: Formed by the subscapularis (superiorly), teres major, and the broad latissimus dorsi muscles (inferiorly). Medial Wall: Formed by the upper thoracic wall (ribs 1–4 and intercostal muscles) covered by the serratus anterior muscle. Lateral Wall: A very narrow wall formed by the intertubercular sulcus (bicipital groove) of the humerus. Associated Internal Contents The contents are densely packed in axillary fat, which protects the structures from extreme arm movements. The Axillary Artery: Continuously wrapped inside the axillary sheath, it is anatomically divided into three distinct descriptive segments based on its relationship to the overlying pectoralis minor muscle (Part 1 is medial, Part 2 is posterior, Part 3 is lateral to the muscle). The Brachial Plexus Cords: The neurovascular network. The lateral, medial, and posterior cords are named directly and specifically for their precise spatial relationship to the second part of the axillary artery. Axillary Lymph Node Groups: Crucial for breast cancer staging and upper limb lymphatic drainage. They are divided into five clusters: Pectoral (anterior), Subscapular (posterior), Humeral (lateral), Central, and Apical clusters, tracking regional lymphatic clearance up toward the venous system. 2.2 The Arm

lungs and pleura
Anatomy

lungs and pleura

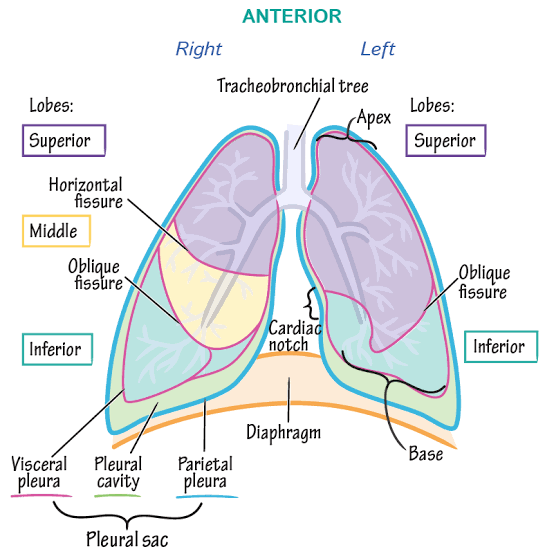
Gross Anatomy of the Lungs and Pleura Module Learning Objectives By the conclusion of this exhaustive master guide, you will be deeply conversant with: The detailed anatomy of the Pleura and Pleural Cavities, including their recesses and embryological formation. The comprehensive gross anatomy of the Right and Left Lungs (lobes, fissures, surfaces, and borders). The vital neurovascular relations at the Root and Hilum of the lung, and adjacent mediastinal structures. The intricate branching of the Tracheobronchial Tree and the surgical significance of Bronchopulmonary Segments. The precise Surface Anatomy of the lungs and pleura (The “Rule of 6-8-10 / 8-10-12”). High-yield clinical correlates including Thoracentesis, Bronchoscopy, Pleural Effusion, and TE Fistulas. I. The Pleura and Pleural Cavities The thoracic cavity contains two separate pleural cavities, one on either side of the centrally located Mediastinum. Each lung is independently enclosed within its own pleural cavity, ensuring that if one lung collapses (pneumothorax), the other remains functional. 1. The Two Layers of the Pleura Each pleural cavity is completely lined by a continuous, serous mesothelial membrane called the Pleura. During embryological development, the growing lung bud punches into the coelomic cavity (like a fist pushing into a deflated balloon), creating two distinct layers: Parietal Pleura: The outer layer that intimately lines the inner surface of the thoracic wall, the superior surface of the diaphragm, and the lateral surface of the mediastinum. Visceral Pleura: The inner layer that directly and inextricably adheres to the outer surface of the lung, dipping deep into the fissures between the lobes. The Reflection: The parietal pleura reflects (folds back upon itself) at the root of the lung to become continuous with the visceral pleura. 2. The Pleural Cavity (Pleural Space) Under normal, healthy conditions, the pleural cavity is a potential space. The visceral and parietal pleura are in direct contact, separated only by a microscopic, capillary-thin layer of serous pleural fluid. Function of Fluid: It acts as a lubricant to allow the lungs to slide frictionlessly against the chest wall during breathing. Crucially, the surface tension of this fluid firmly holds the lung against the chest wall, preventing lung collapse. 3. Pleural Recesses The lungs do not completely fill the pleural cavities, especially during quiet expiration. This leaves empty, potential spaces where two layers of parietal pleura touch each other. These are called recesses, and they only fill with lung tissue during deep, forced inspiration. Costodiaphragmatic Recess: The largest and clinically most important recess. It lies inferiorly in the trough between the costal (rib) wall and the dome of the diaphragm. Fluid (like blood or pus) preferentially pools here due to gravity when a patient is standing or sitting upright. Costomediastinal Recess: Located anteriorly, where the costal pleura folds back to become the mediastinal pleura, notably behind the sternum (associated with the cardiac notch of the left lung). Clinical Correlate: Pleural Effusion Pathology: A pleural effusion is the abnormal accumulation of excess fluid (serous fluid, blood, or pus) in the pleural cavity. Because the fluid takes up space, it physically compresses the underlying lung tissue. Clinical Signs: Diminished or Absent Breath Sounds: The fluid blocks the acoustic transmission of air moving in the lungs. Collapsed Lung: The affected lung (e.g., right lung) collapses away from the chest wall. Tracheal Deviation: A massive effusion generates immense pressure, physically displacing the mediastinum and pushing the trachea toward the opposite, healthy side (e.g., trachea displaced to the left). II. Gross Anatomy of the Lungs The lungs are paired, spongy, highly elastic organs responsible for respiration. Each lung is shaped like a half-cone. 1. Defining Features The Apex: The blunt superior end. It projects above rib I and into the root of the neck (roughly 1 inch / 2.5 cm above the medial third of the clavicle). It is protected by the suprapleural membrane (Sibson’s fascia), a thickening of the endothoracic fascia. The Base: The broad, concave inferior surface that rests directly upon the convex dome of the diaphragm. 2. Surfaces and Borders Costal Surface: The large, smooth, convex surface lying immediately adjacent to the ribs and intercostal spaces. Mediastinal Surface: The medial surface facing the heart. It contains the comma-shaped Hilum (the doorway where structures enter and leave the lung). Inferior Border: Sharp and distinct; separates the base from the costal surface. Anterior Border: Sharp; separates the costal surface from the medial surface anteriorly. Posterior Border: Unlike the other borders, this is completely smooth and rounded, resting in the deep concavity beside the vertebral column. 3. Right vs. Left Lung: Key Anatomical Differences The two lungs are not perfectly symmetrical. The heart, occupying the left side of the chest, severely alters the structure of the left lung. Feature Right Lung Left Lung Size & Weight Larger, heavier, and shorter (because the liver pushes the right hemidiaphragm up). Smaller and narrower (due to the presence of the heart). Lobes Three (3): Superior, Middle, and Inferior lobes. Two (2): Superior and Inferior lobes. Fissures Two (2): 1. Oblique Fissure.2. Horizontal Fissure (separates superior from middle lobe). One (1): 1. Oblique Fissure only. Unique Features Relatively uniform anterior border. Contains the Cardiac Notch (a deep indentation on the anterior border) and the Lingula (a tongue-like projection below the notch, homologous to the right middle lobe). III. The Root, Hilum, and Mediastinal Relations The lung does not float freely; it remains firmly anchored to the mediastinum by its Root. 1. The Root and the Hilum The Root: A short, tubular collection of structures (airway, blood vessels, lymphatics, nerves) connecting the lung to the mediastinum. The Hilum: The actual geographical depression (the “doorway”) on the mediastinal surface of the lung through which the root structures pass. The Pulmonary Ligament: A thin, blade-like fold of pleura that projects inferiorly from the root. It provides dead space, allowing the pulmonary veins to distend comfortably when cardiac output increases during exercise. Crucial Neurovascular Relations The Nerves Around the Root This is highly tested anatomical topography: The Phrenic Nerve (which innervates the diaphragm) passes immediately ANTERIOR to the root

Mediastinum
Anatomy

Mediastinum

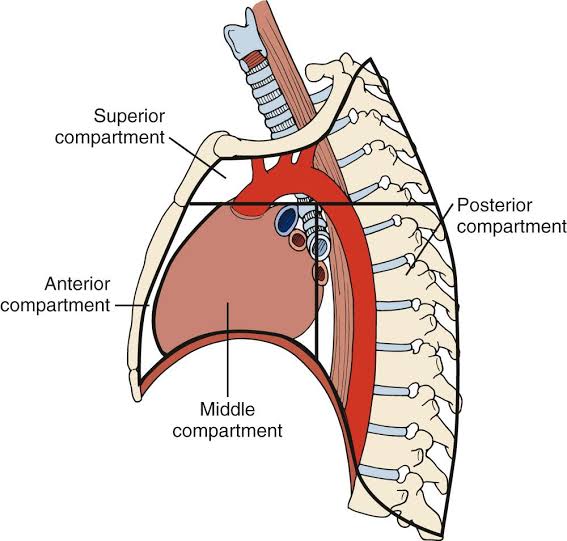
The Mediastinum: Anatomy, Contents, and Clinical Topography Module Learning Objectives By the conclusion of this exhaustive anatomical master guide, you will be deeply conversant with: The comprehensive 3D boundaries and subdivisions of the Mediastinum. The exact contents (vascular, nervous, lymphatic, and visceral) of the Superior, Anterior, Middle, and Posterior Mediastinum. The cross-sectional topography at the T4 level (Sternal Angle / Angle of Louis) and its immense clinical significance. The fascial planes of the neck and how they dictate the spread of Mediastinitis. The pathophysiology of Mediastinal Syndrome, Mediastinal Shift, and Mediastinal Widening. I. Introduction and General Boundaries The Mediastinum (from Latin mediastinus, meaning “midway”) is the thick, flexible, and highly dynamic central partition of the thoracic cavity. It is a broad, central compartment that completely separates the two lateral pleural cavities (which house the lungs). It acts as the major conduit for structures passing between the neck, the thorax, and the abdomen. Because it contains vital hollow organs, massive pressurized blood vessels, and loose connective tissue, it is highly mobile, accommodating the volumetric changes of the lungs during respiration and the beating of the heart. General Boundaries of the Entire Mediastinum: Anteriorly: The sternum and costal cartilages. Posteriorly: The bodies of the 12 thoracic vertebrae (T1 to T12). Laterally (Sides): The mediastinal parietal pleura (which reflects over the medial surfaces of the lungs). Superiorly: The superior thoracic aperture (thoracic inlet), continuous with the fascial planes of the neck. Inferiorly: The diaphragm. II. Divisions of the Mediastinum: The Sternal Angle For anatomical and surgical clarity, the mediastinum is divided into distinct compartments by a highly significant imaginary plane called the Transverse Thoracic Plane. This imaginary horizontal line passes from the Sternal Angle (Angle of Louis) anteriorly to the intervertebral disc between T4 and T5 posteriorly. The Magic of the Sternal Angle (T4/T5 Plane) This plane is arguably the most tested and clinically relevant landmark in thoracic anatomy. It dictates the division of the mediastinum into: Superior Mediastinum: Everything ABOVE the plane. Inferior Mediastinum: Everything BELOW the plane. The Inferior Mediastinum is further massively subdivided by the pericardial sac (the heart) into: Anterior Mediastinum: In front of the pericardium. Middle Mediastinum: The pericardium and its contents. Posterior Mediastinum: Behind the pericardium. III. The Superior Mediastinum This compartment lies deep to the manubrium of the sternum and contains the massive “great vessels” that exit and enter the heart, as well as critical nerves descending from the brain. Boundaries: Anterior: Manubrium sterni (posterior surface). Posterior: The bodies of the first four thoracic vertebrae (T1 to T4). Sides (Lateral): Mediastinal pleura of the right and left lungs. Superior: The plane of the thoracic inlet (root of the neck). Inferior: The imaginary transverse thoracic plane (joining the sternal angle to the lower border of T4). Contents of the Superior Mediastinum: The contents are densely packed and are classically arranged in layers from anterior to posterior (Muscles/Glands → Veins → Arteries → Airways → GI Tract). 1. Muscles & Glands Muscles: The origins of the infrahyoid “strap” muscles: Sternohyoid and Sternothyroid. The inferior attachments of the Longus colli muscles. Thymus: The lower portion of the thymus gland (highly prominent in childhood and puberty, slowly replaced by fat in adults). 2. The Great Veins Superior Vena Cava (SVC): The upper half of the SVC resides here before entering the pericardium. Brachiocephalic Veins: Both the Right and Left Brachiocephalic veins (the left is much longer and crosses anterior to the major arteries). Left Superior Intercostal Vein: Drains the 2nd, 3rd, and 4th intercostal spaces. 3. The Great Arteries Arch of the Aorta: Curves backward over the left main bronchus. Brachiocephalic Artery (Trunk): The first branch of the aortic arch. Left Common Carotid Artery: The second branch. Left Subclavian Artery: The third branch. 4. Viscera (Tubes) Trachea: Lies anterior to the esophagus, bifurcating at the very bottom of this compartment. Esophagus: The most posterior hollow tube, lying flat against the vertebral bodies. 5. Nerves, Lymph & Ducts Nerves: Both Vagus Nerves (CN X), both Phrenic Nerves (C3-C5), Cardiac Nerves. Left Recurrent Laryngeal Nerve: A critical branch of the left vagus that hooks completely under the arch of the aorta, ascending back up in the groove between the trachea and esophagus. Thoracic Duct: The massive lymphatic vessel lying on the left side of the esophagus. Lymph Nodes: Brachiocephalic and Tracheobronchial nodes. IV. The Inferior Mediastinum: Anterior, Middle, and Posterior The Inferior Mediastinum extends from the transverse thoracic plane down to the diaphragm. The presence of the heart and its tough fibrous sac (the pericardium) acts as a physical barrier, dividing this vast space into three highly distinct zones. A. The Anterior Mediastinum (The Narrowest Compartment) This is a remarkably shallow space squeezed between the sternum and the heart. Boundaries: Anterior: Body of the sternum. Posterior: Pericardium (enclosing the heart). Sides: Mediastinal pleura. Superior: Imaginary plane (Sternal angle). Inferior: Diaphragm. Contents: Thymus: (The lower pole extending down in children/infants). Sternopericardial Ligaments: Tough fibrous bands that physically anchor the pericardium to the posterior aspect of the sternum, keeping the heart in place. Internal Thoracic Artery & Branches: (Also known as the Internal Mammary Artery, heavily used in coronary bypass surgeries). Lymphatics & Lymph nodes: Prepericardial lymph nodes. B. The Middle Mediastinum This is the central, most vital compartment of the entire thoracic cavity. It is dominated entirely by the heart and the very beginnings of the great vessels. Boundaries: It is defined simply as the pericardial sac and everything contained within it, extending slightly upward to encompass the roots of the great vessels. Contents: Heart enclosed in the Pericardium. Arteries: Ascending Aorta (the very first segment before the arch), Pulmonary trunk with its Left & Right branches. Veins: Lower half of the Superior Vena Cava (SVC), the Termination (arch) of the Azygos vein as it dumps into the SVC, and the Pulmonary veins entering the left atrium. Nerves: Phrenic nerves (which uniquely run directly over the lateral surface of the pericardium) and the Deep Cardiac Plexus. Airways: The Bifurcation of the Trachea

Routes of Administration
Anatomy, Pathology

Routes of Administration

Routes of Drug Administration Routes of Administration Fundamental Definitions and Concepts What is a Drug? In the strictest scientific sense, a drug is defined as any chemical agent or substance which affects, alters, or modifies any biological process within a living organism. It is important to realize that the body does not distinguish between a “therapeutic medication,” an “environmental toxin,” or a “recreational substance”—to the body’s cells, they are all simply foreign chemicals (xenobiotics) that bind to biological targets and induce a change. What is Pharmacology? Pharmacology is the comprehensive scientific study of exactly how these drugs affect biological systems. It investigates the entire lifecycle of a drug interaction: from how the drug is manufactured and sourced, to how it travels through the bloodstream, how it binds to microscopic cellular receptors, and ultimately, how the body destroys and removes it. The Five Major Branches of Pharmacology To fully understand drug action, pharmacology is systematically divided into distinct domains: 1 Pharmacokinetics “What the body does to the drug.” This encompasses the four pillars of drug biodisposition: Absorption (getting in), Distribution (moving around), Metabolism/Biotransformation (being broken down by enzymes), and Excretion (leaving the body). 2 Pharmacodynamics “What the drug does to the body.” This looks at the microscopic level: drug receptors (the protein locks that drugs fit into), the physiological effects of the drug, cellular responses, and potential toxicity or adverse effects. 3 Pharmacotherapeutics The clinical study of the strictly medical use of drugs to prevent, diagnose, or treat diseases. 4 Pharmacognosy The highly specialized study of identifying, extracting, and isolating crude materials from natural sources to be used as drugs. 5 Toxicology The study of the poisonous, adverse, and toxic effects of chemicals on living systems. Sources of Drugs and Forms of Medication Sources of Drugs (Pharmacognosy) Historically, all drugs came from nature. Today, we source drugs from five primary categories: Plants: The oldest source of medicine. Examples include Morphine (from the opium poppy), Digoxin (from the foxglove plant for heart failure), and Quinine (from the cinchona tree bark for malaria). Animals: Historically, many hormones were extracted from slaughtered livestock. Examples include Insulin (previously extracted from pig and cow pancreases) and Heparin (a blood thinner extracted from pig intestines). Minerals: Earthly elements used directly for health. Examples include Iron (for anemia), Lithium (for bipolar disorder), and Magnesium (as an antacid or laxative). Synthetic: Today, the vast majority of drugs are entirely synthesized in chemistry laboratories. This allows for massive scaling, precise purity, and the structural modification of natural drugs to reduce side effects. Microbes: Many life-saving drugs are produced by harnessing bacteria and fungi. The most famous example is Penicillin (produced by the Penicillium fungus). Forms of Medication Medications are practically never pure, raw chemicals. They are carefully formulated into specific “preparations” or “dosage forms.” The form of the medication strictly dictates its route of administration. The composition of the medicine is intricately designed by pharmaceutical scientists to enhance its absorption, dictate its metabolism rate, and ensure patient compliance. Common forms include: Tablet: A solid dosage form made by highly compressing powdered drug and inactive binders into a hard pill. Capsule: A drug enclosed within a gelatin shell. They dissolve quickly in the stomach, releasing the powder or liquid inside. Elixir: A clear, sweetened, hydro-alcoholic liquid intended for oral use, perfect for drugs that do not dissolve easily in pure water. Enteric-coated: A specially designed tablet with an acid-resistant shell. It passes through the highly acidic stomach unharmed and only dissolves when it reaches the alkaline environment of the small intestine. This protects sensitive drugs from destruction and protects the stomach from irritating drugs. Suppository: A solid, bullet-shaped mass that is inserted into a body cavity (rectum or vagina) which is explicitly designed to melt at exact human body temperature (37°C) to release the drug. Suspension: A liquid preparation containing undissolved solid drug particles. Because the drug settles at the bottom, these must be shaken vigorously before administration. Transdermal patch: An adhesive patch placed on the skin that delivers a specific, slow, and continuous dose of medication through the skin and directly into the bloodstream. Routes of Drug Administration A route of administration is the specific anatomical path by which a drug, fluid, poison, or other substance is brought into contact with the body. Routes of administration are broadly classified into three main channels based on whether they act locally or systematically, and whether they involve the digestive tract: Enteral: Through the gastrointestinal tract (Oral, Sublingual, Buccal, Rectal). Parenteral: Bypassing the gastrointestinal tract, usually via injection (IV, IM, SC, etc.). Topical: Applied to a specific surface for a localized effect (Skin, eyes, ears, lungs). Enteral Routes of Administration The term Enteral comes from the Greek word enteron, meaning intestine. It refers to anything involving the alimentary tract, from the mouth down to the rectum. A. Oral Route or Per Os (P.O.) The oral route involves swallowing a drug. It is the most common, oldest, and generally most universally accepted route of administration. It utilizes the body’s natural machinery used for digesting food, absorbing nutrients, and eliminating wastes. Advantages of the Oral Route: It is safe: Because absorption is relatively slow, there is a window of opportunity to induce vomiting or pump the stomach in case of an accidental overdose. It is convenient: Patients can take it themselves anywhere. It is cheap: Tablets and capsules do not require sterile manufacturing conditions like injectable fluids do. No skilled personnel required: The patient does not need a nurse or doctor to administer the dose. Disadvantages of the Oral Route: Unpalatable drugs: Bitter or foul-tasting drugs can cause severe irritation to the intestinal tract, resulting in nausea, vomiting, and diarrhea. Destruction by enzymes and acid: Some drugs are completely annihilated by stomach acid (HCl) or digestive enzymes before they can be absorbed. For example, Insulin is a protein; if swallowed, the stomach digests it just like a piece of meat, destroying its therapeutic value. Not suitable for emergencies: It takes time for a pill

Introduction to Basic Pharmacology
Anatomy, Pathology

Introduction to Basic Pharmacology

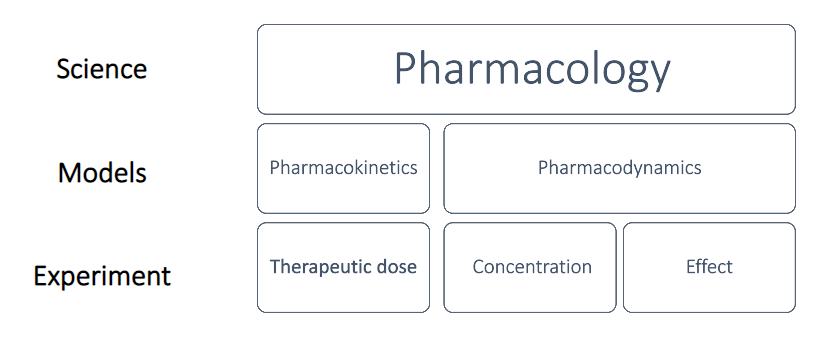
Pharmacology Intro: Basic & Practicals Introduction to Basic Pharmacology and Pharmacology Practicals (Instrumentation) Learning Outcomes of the Lecture By the end of this comprehensive guide, students should be fully equipped to: Define pharmacology and clearly outline its major branches and sub-disciplines. Distinguish definitively between the concepts of pharmacodynamics and pharmacokinetics. Explain the critical importance of pharmacology practicals and laboratory experiments in medical and scientific training. Identify and understand the major instruments and equipment used in modern and historical pharmacology laboratories. Describe the specific functions of organ bath systems, transducers, and recording devices in depth. Recognize and apply ethical considerations (such as the 3Rs) in experimental pharmacology. Introduction to Pharmacology Pharmacology is broadly defined as the rigorous scientific study of drugs and their interactions with living systems. Derived from the Greek words pharmakon (drug or poison) and logos (study), it is a vast field that examines every aspect of how drugs produce their physiological effects, how the human (or animal) body processes these foreign substances, and how these chemicals can be utilized therapeutically to treat disease, or experimentally to understand biological processes. Definition: A Drug A drug, in the context of pharmacology, can be defined as any chemical substance (natural, synthetic, or endogenous) that modifies physiological or biochemical functions when administered to a living organism. This includes everything from life-saving antibiotics to everyday pain relievers, as well as substances of abuse and environmental toxins. The Multidisciplinary Nature of Pharmacology Pharmacology does not exist in isolation. It acts as a bridge between the physical sciences and the biological sciences. It integrates core knowledge from several crucial disciplines, including: Physiology: Understanding normal body functions is essential before one can understand how a drug alters those functions. Biochemistry: Provides the foundation for understanding the chemical basis of drug action at the enzymatic and metabolic levels. Molecular Biology: Helps in understanding how drugs interact with genetic material, intracellular signaling, and protein synthesis. Medicinal Chemistry: Focuses on the structural design, synthesis, and optimization of pharmaceutical drugs. Toxicology: The study of the adverse or poisonous effects of chemicals, closely tied to drug safety. Clinical Medicine: The ultimate application of pharmacological knowledge to diagnose, prevent, and treat illnesses in human patients. Major Branches of Pharmacology To fully grasp pharmacology, the field is traditionally divided into several distinct, yet deeply interconnected, branches. 1. Pharmacodynamics Pharmacodynamics essentially studies what the drug does to the body. It delves into the specific biochemical and physiological effects of drugs and their mechanisms of action. Key aspects of pharmacodynamics include: Mechanism of Drug Action: Exactly how a drug produces its effect at the cellular level. Drug–Receptor Interactions: How drugs bind to specific protein targets (receptors) to initiate or block a biological response. Cellular Targets: Drugs typically exert their effects by interacting with four main regulatory proteins: Ion Channels: Drugs can act as openers (increasing ion influx) or blockers (preventing ion passage). Enzymes: Drugs often act as inhibitors, preventing the enzyme from converting a substrate into a product (e.g., aspirin inhibiting COX enzymes). Transporters: Drugs can act as transport inhibitors, preventing the movement of molecules across cell membranes. Receptors: Drugs can be Agonists (activating the receptor for signal transduction) or Antagonists (blocking the receptor and preventing activation). Dose–Response Relationships: The mathematical and graphical relationship between the amount of drug given (dose) and the magnitude of the effect produced. As the log of the drug concentration increases, the effect typically increases until a maximum plateau is reached. Therapeutic and Toxic Effects: Determining the primary intended effects versus unintended side effects. Example of Pharmacodynamics How β-blockers reduce heart rate: A beta-blocker (like Atenolol) acts as an antagonist. It specifically targets and blocks β1-adrenergic receptors located in the heart muscle. By blocking these receptors, it prevents adrenaline from binding, which structurally and functionally reduces the heart rate and blood pressure (this is what the drug does to the body). 2. Pharmacokinetics Pharmacokinetics studies what the body does to the drug. It traces the journey of a drug molecule from the moment it enters the body until it is completely removed. It involves four major, continuous processes, universally remembered by the acronym ADME: A – Absorption The movement of a drug from its site of administration (e.g., gut, muscle, skin) into the systemic blood circulation. Factors like route of administration, lipid solubility, and pH heavily influence this. D – Distribution The reversible transfer of a drug from one location to another within the body, typically from the bloodstream into tissues, organs, and intracellular spaces. It is affected by blood flow, tissue binding, and membrane permeability (e.g., the blood-brain barrier). M – Metabolism (Biotransformation) The chemical modification or breakdown of drugs, primarily occurring in the liver. The body attempts to make the drug more water-soluble so it can be easily excreted. E – Excretion The irreversible elimination of the drug and its metabolites from the body. The kidneys (via urine) are the primary route, but drugs can also be excreted through bile, feces, sweat, saliva, tears, and lungs (exhaled air). Example of Pharmacokinetics First-pass metabolism of drugs like propranolol: When propranolol is taken orally, it is absorbed by the digestive tract and carried directly to the liver via the hepatic portal vein. The liver highly metabolizes (destroys) a large portion of the drug before it ever reaches the systemic circulation. This “first-pass effect” drastically reduces the bioavailability of the drug, which is an example of what the body does to the drug. 3. Therapeutics (Clinical Pharmacology/Pharmacotherapeutics) This branch focuses strictly on the clinical use of drugs to prevent, diagnose, or treat diseases. It is the practical application of pharmacology in a healthcare setting, emphasizing evidence-based medicine, rational prescribing, and patient care. Antihypertensive therapy: Using drugs to lower high blood pressure and prevent cardiovascular events. Antidiabetic therapy: Managing blood sugar levels using insulin or oral hypoglycemic agents. Antimicrobial therapy: Utilizing antibiotics, antivirals, or antifungals to eradicate infections while minimizing harm to the host. 4. Toxicology Toxicology is the study of the harmful, adverse, or toxic effects of drugs, chemicals, and

intracellular accumulation
Anatomy, Pathology

Intracellular Accumulation & Acute Inflammation

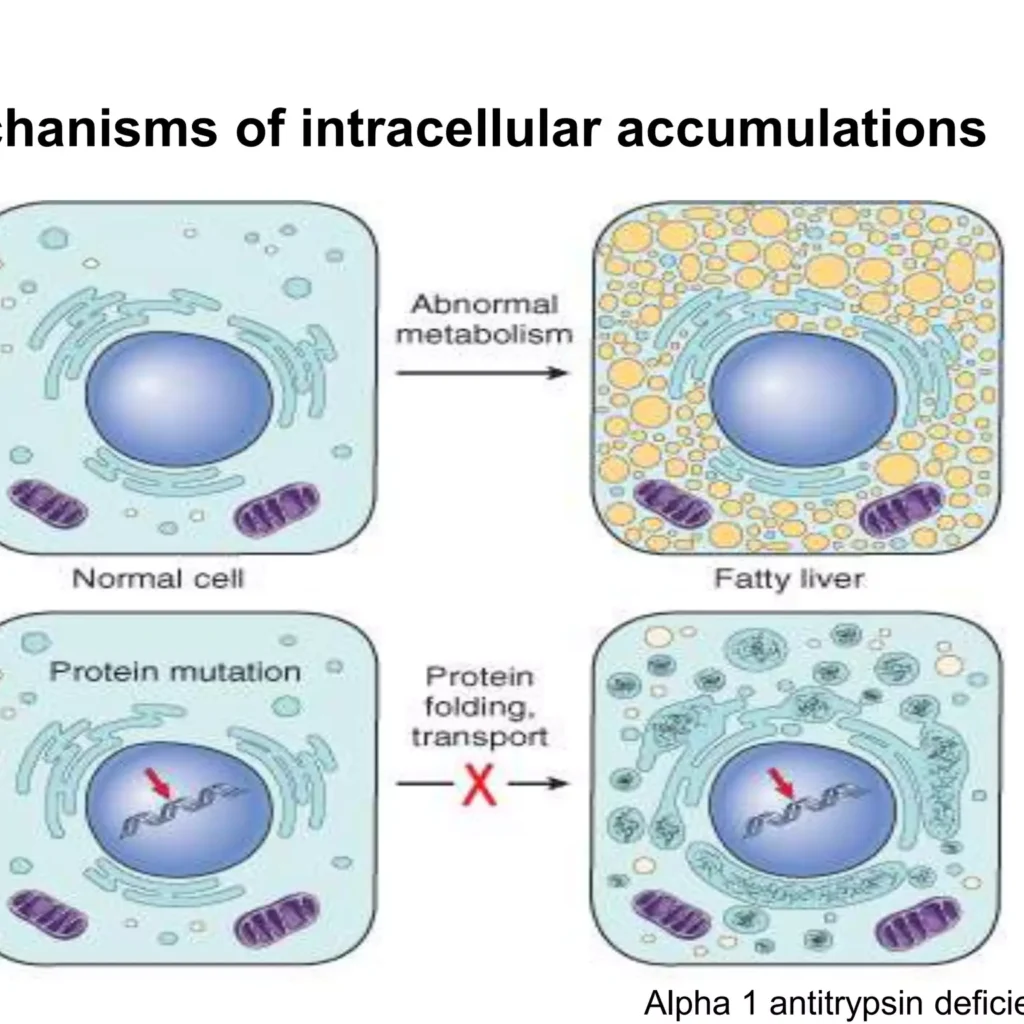
Intracellular Accumulation & Acute Inflammation Intracellular Accumulation & Acute Inflammation Intracellular Accumulations Intracellular accumulations are the buildup of substances—such as lipids, proteins, glycogen, or pigments—within cells due to metabolic derangements, genetic defects, or environmental factors. These accumulations occur in the cytoplasm or nucleus, ranging from harmless to severely toxic, causing reversible or irreversible cell injury. Key mechanisms include increased production, defective metabolism/transport, or lack of enzymes to break down substances. General Principles Cells often act as reservoirs for metabolic products or exogenous substances. These accumulations represent a sign of metabolic derangement. Subcellular Localization Cytoplasm: Most common (e.g., Fatty change, Glycogen). Organelles: Specifically within Lysosomes (e.g., Pompe disease) or the Endoplasmic Reticulum (e.g., Protein folding defects). Nucleus: Rare, but seen in certain viral infections or lead poisoning. The Four Pathological Mechanisms Abnormal Metabolism: A normal endogenous substance (like water, lipids, or proteins) is produced at a normal or increased rate, but the metabolic rate is inadequate for its removal (e.g., Steatosis). Defect in Protein Folding/Transport: Genetic mutations or acquired defects cause proteins to misfold. These “garbage” proteins build up because they cannot be exported or degraded (e.g., α1-antitrypsin deficiency). Enzymatic Deficiency: An inherited lack of a vital enzyme (usually lysosomal) means a specific substrate cannot be broken down, leading to massive buildup—known as Storage Diseases. Inability to Degrade Exogenous Material: The cell encounters a substance (like carbon or silica) for which it has no natural enzymes to digest. Examples of Abnormal Accumulations 1. Fatty Change (Steatosis) The abnormal accumulation of triglycerides within parenchymal (functional) cells. Organ Involvement: Primarily the Liver (yellow, greasy, enlarged). It is also significant in the Heart (where it can cause “Tiger effect” banding) and the Kidneys. Etiology (The “Why”): Toxins: Most notably Alcohol, which is a mitochondrial toxin that impairs fat oxidation. Protein Malnutrition: Lack of “apoproteins” needed to carry fat out of the liver. Anoxia: Lack of oxygen prevents the oxidation (burning) of fatty acids. Diabetes Mellitus & Obesity: Causes an oversupply of free fatty acids to the liver. 2. Cholesterol and Cholesteryl Esters Pathology: Unlike triglycerides, cholesterol is usually stored in macrophages or smooth muscle cells. Atherosclerosis: The most critical clinical result. Phagocytic cells in the large arteries become overloaded with lipid, forming “Foam Cells.” These accumulate in the intimal layer of arteries, leading to yellow fatty streaks and eventually plaques. 3. Proteins Morphology: Appear as rounded, eosinophilic (bright pink) droplets, vacuoles, or aggregates. Clinical Examples: Nephrotic Syndrome: Excess protein leaks into the kidney tubules; the cells reabsorb it, creating pink protein droplets. Russell Bodies: Found in plasma cells (overproduction of immunoglobulins). Misfolded Proteins: Build up in the brain (Amyloid plaques in Alzheimer’s). 4. Glycogen Association: Highly associated with Glucose metabolism disorders. Diabetes Mellitus: Glycogen is found in the epithelial cells of the distal segments of the renal tubules and the liver. Glycogen Storage Diseases (GSD): Genetic defects where glycogen cannot be converted back to glucose, leading to massive cell death and organ failure. 5. Pigments: The “Colored” Pathologies Exogenous (Environmental): Carbon (Anthracosis): The most ubiquitous pigment. Inhaled carbon is phagocytosed by alveolar macrophages. These macrophages travel through the lymphatics to the tracheobronchial lymph nodes. In coal miners, this leads to “Black Lung” disease (Coal Workers’ Pneumoconiosis). Endogenous (Produced by the body): Lipofuscin: A “wear-and-tear” pigment. It is a sign of free radical injury and lipid peroxidation. It does not harm the cell but is a tell-tale marker of aging. Melanin: An insoluble brown-black pigment produced by melanocytes in the epidermis to protect against UV radiation. Hemosiderin: A hemoglobin-derived, golden-yellow to brown, granular pigment. It represents local or systemic Iron excess. Staining Tip: On a standard H&E slide, it looks like brown granules. To prove it is iron, pathologists use the Prussian Blue Histochemical Stain (the iron turns bright blue). Pathologic Calcification Pathologic calcification is the abnormal deposition of calcium salts (phosphates, carbonates) in soft tissues, commonly due to injury or metabolic dysfunction. Calcification is a permanent marker of past or present tissue injury. It occurs in two main forms: dystrophic (normal serum calcium, damaged tissue) and metastatic (high serum calcium, normal tissue). I. Dystrophic Calcification (Local Injury) Occurs in dead or dying tissues (necrosis) despite normal serum calcium levels, often seen in atherosclerosis, damaged heart valves, or tuberculous lymph nodes. Requirement: Occurs in non-viable (dead) or dying tissues. Calcium Levels: Serum calcium levels are Normal; there is no systemic mineral imbalance. Pathogenesis: Necrotic cells have damaged membranes; calcium binds to the phospholipids in these membranes, initiating the “crystallization” of calcium phosphate. Clinical Examples: Atherosclerosis: The core of an old plaque is often “bone-hard” due to calcification. Tuberculosis (TB): Areas of Caseous Necrosis often calcify, making them visible on X-rays (Ghon complex). Aging/Damaged Heart Valves: Leads to stenosis (narrowing of the valve). II. Metastatic Calcification (Systemic Imbalance) Occurs in normal tissues due to hypercalcemia (high calcium levels in the blood), often caused by renal failure, hyperparathyroidism, or Vitamin D intoxication. Requirement: Occurs in normal, healthy tissues. Calcium Levels: Always associated with Hypercalcemia (Elevated blood calcium). The Four Major Causes of Hypercalcemia Hyperparathyroidism: Either a primary tumor of the parathyroid gland or “ectopic” secretion of PTH-related protein by cancers (like lung or breast cancer). Rapid Bone Destruction: Multiple Myeloma: A cancer of plasma cells that “eats” bone. Paget’s Disease: Disorganized bone remodeling. Immobilization: Long-term bedrest leads to bone resorption. Vitamin D Disorders: Intoxication (overdose) or Sarcoidosis (where lung macrophages inappropriately activate Vitamin D). Renal Failure: Leads to phosphate retention, which triggers a secondary rise in PTH, pulling calcium out of the bones and into the tissues. Morphology and Distribution Gross (Macroscopic): Calcium deposits are white, chalky granules. When a pathologist cuts through the tissue, it feels “gritty” (like cutting through sand or eggshells). Microscopic (Histology): Stains Basophilic (deep blue/purple) with H&E. Can be found inside cells (mitochondria) or outside cells in the matrix. Psammoma Bodies: In some tumors (like thyroid cancer), the calcification forms beautiful, laminated, sand-like concentric circles. Preferred “Metastatic” Targets: High-calcium levels prefer tissues that have an alkaline (basic) internal environment, which promotes

pathology pathophysiology intro
Anatomy, Pathology

Pathology Intro: Concepts & Applications

Pathology Intro: Concepts & Applications Pathology Intro: Concepts & Applications What is Pathology? Pathology is the scientific study of disease. It acts as the bridge between basic sciences (like anatomy, physiology, biochemistry, microbiology) and clinical medicine. Etymology: Derived from Greek words: Pathos = Suffering Logos = Study Pathology seeks to understand the causes (etiology), mechanisms (pathogenesis), structural alterations (morphological changes), and functional consequences (clinical manifestations) of disease. Definition Pathology is a branch of natural science that studies the etiology (cause), mechanisms (pathogenesis), and effects (morphological changes and clinical manifestations) produced by diseases in all living organisms, including humans, animals, and plants. Ancient Foundations (The Roots) Imhotep (Egypt, c. 2600 BC): Recognized as the oldest known physician/doctor in history. He transitioned medicine from purely magic to early observation. The Papyrus (Egypt, c. 1600 BC): Specifically the Edwin Smith Papyrus, it is considered the oldest study of anatomy and surgical trauma, detailing clinical observations and treatments. The Evolution of Pathological Thought 1. The Era of Religious & Supernatural Beliefs Before a rational approach was developed, disease was attributed to: Divine Punishment: A “Curse from God” or the result of sin. Magic/Supernatural: Belief in the “evil eye” or malevolent spirits. Scriptural References: Examples found in the Bible (Job 2:7—affliction with boils; Exodus 9:8-12—the plague of boils). Cultural Deities: Different regions had specific gods of disease, such as Walumbe in the Buganda kingdom (associated with death and disease). 2. The Antiquity to AD 1500: The Rational Approach This period saw the shift from mysticism to observation. Hippocrates (Greece, 460–377 BC): Known as the “Father of Medicine.” Dissociation: Permanently dissociated medicine from religious mysticism. Clinical Observation: Established the study of patient symptoms as the primary method for diagnosis. Cornelius Celsus (Rome, 53 BC–7 AD): Described the 4 Cardinal Signs of Inflammation: Rubor (redness), Calor (heat), Tumor (swelling), and Dolor (pain). Claudius Galen (130–200 AD): Postulated the Humoral Theory (Galenic Theory). He argued that illness resulted from an imbalance of four body fluids: Blood, Lymph, Black Bile (associated with the spleen), and Biliary Secretion/Yellow Bile (from the liver). 3. The Era of Gross Pathology (AD 1500 to 1800) During this time, physicians began correlating symptoms with what they saw during autopsies. Giovanni B. Morgagni (Italy, 1682–1771): The “Father of Anatomical Pathology.” Introduced Clinical Pathologic Correlation (CPC)—the practice of linking a patient’s symptoms during life to the organ changes found after death. John Hunter (Scotland, 1728–1793): Introduced the Pathology Museum as a vital tool for medical education and the systematic study of diseased specimens. R.T.H. Laennec (France, 1781–1826): Described lung diseases, including various tuberculous lesions and bronchiectasis. Described cirrhosis of the liver (still frequently called Laennec’s Cirrhosis). Invented the stethoscope, allowing for better clinical-pathological correlation during life. 4. The Era of Technology & Cellular Pathology (AD 1800 to 1950s) The invention of the microscope shifted the focus from organs to cells. Rudolf Virchow (Germany, 1821–1905): Known as the “Father of Cellular Pathology.” Proposed the Cellular Theory: Disease does not arise in organs or tissues generally, but primarily in individual cells (Omnis cellula e cellula). Established Histopathology as a formal diagnostic branch of medicine. George N. Papanicolaou (USA, 1883–1962): Known as the “Father of Exfoliative Cytology.” Developed the Pap Smear in the 1930s for the early detection of cervical cancer, proving that microscopic examination of individual cells could prevent disease. 5. Modern Pathology (1950s to the 21st Century) The focus shifted again—from the cell to the molecule and DNA. Watson and Crick (1953): Described the double-helix structure of DNA, opening the door to molecular pathology. Nowell and Hungerford (1960): Discovered the Philadelphia chromosome in Chronic Myeloid Leukemia (CML), identifying the specific translocation t(9;22). Gall and Pardue (1969): Developed In Situ Hybridization, allowing researchers to locate specific nucleic acid sequences within tissues. Kary Mullis (1983): Introduced the Polymerase Chain Reaction (PCR), a revolutionary technique that allows for the amplification of DNA, now used for diagnosing infections, genetic mutations, and cancers. Modern Diagnostic Modalities: Telepathology Telepathology is the practice of diagnostic pathology by a remote pathologist utilizing images of tissue specimens transmitted over a telecommunication network. This allows for rapid consultation and diagnosis across different geographical locations. 1. Components of Telepathology Conventional Light Microscope: The primary tool used to view the specimen. Image Capture Method: Usually a high-resolution digital camera mounted on the microscope. Telecommunications Link: A secure network (internet or satellite) to transmit data between the sending and receiving sites. Workstation: A computer at the receiving end equipped with a high-quality, medical-grade monitor for accurate interpretation. 2. Types of Telepathology Static (Store-and-Forward): Images are captured and sent as individual files. The remote pathologist views them later (passive telepathology). Dynamic (Robotic/Virtual Microscopy): This involves Virtual Pathology Slides (VPS). The remote pathologist can interact with the microscope in real-time, moving the slide or changing magnification remotely (robotic interactive telepathology). Fields and Branches of Pathology Pathology is not limited to humans; it is a universal study of disease across living systems. 1. Major Study Fields Human Pathology: Study of diseases in humans. Veterinary Pathology: Study of diseases in animals. Plant Pathology: Study of diseases in plants. Teratology: The scientific study of visible conditions/congenital malformations caused by the interruption or alteration of normal development (e.g., birth defects). Nosology: The branch of medicine that deals with the classification and description of known diseases. 2. Functional Branches Etiology: The study of the causes of disease (why it happens). Pathogenesis: The study of the mechanisms and steps of disease development (how it happens). Physiopathology (Pathophysiology): The study of the disordered physiological processes associated with disease or injury. Semiology: The study of the symptoms (subjective, felt by the patient) and signs (objective, observed by the doctor) of disease. Clinic: The practical management and treatment of the disease. Anatomic Pathology The study of morphological and structural changes in cells, tissues, and organs that underlie disease. General Pathology: Studies basic reactions of cells and tissues to abnormal stimuli that occur in all diseases (e.g., inflammation, neoplasia, cell death). Systemic Pathology: Studies diseases as they pertain to specific organs

Scroll to Top