
On this page
Definitions of Terms: Joint & Articulation
A Comprehensive Clinical Reference Guide covering joint anatomy, structural and functional classifications, detailed synovial structures, and pathological correlations .
1. Definition of a Joint
A joint (Latin: articulus) is the precise site where two or more bones meet or articulate. Joints are the fundamental units that provide mobility and stability to the human skeleton, making all body movements possible. The human skeleton contains 206 bones that serve as structural scaffolding; their interaction at joints facilitates locomotion while ensuring the protection of internal organs through the immobility of specific adjacent bones (e.g., cranial sutures protecting the brain).
Joint dysfunction is among the most common reasons for patient visits in primary care. An accurate clinical assessment requires a deep understanding of both the structural components (what the joint is made of) and the functional capabilities (how the joint moves).
2. Definition of Articulation
Articulation refers specifically to the coming together of two bone surfaces at a joint. While often used interchangeably with "joint," the term articulation emphasizes the functional relationship and the point of contact between bone surfaces rather than just the structural assembly.
- Quality of Articulation: Determines the range and type of movement possible.
- Fit vs. Mobility: A "poor" articulation fit, such as the glenohumeral (shoulder) joint, allows for maximum mobility but sacrifices stability. Conversely, an "excellent" fit, such as the hip joint, provides high stability at the cost of reduced mobility.
3. Key Terminology for Clinical Officers
The following terms are essential for diagnostic and therapeutic practice regarding musculoskeletal health:
Scroll the table sideways on a smaller screen.
| Term | Definition | Clinical Relevance |
|---|---|---|
| Articular cartilage | Hyaline cartilage covering bone ends at synovial joints; provides a smooth, slippery surface. | Prevents friction and absorbs shock; damaged in osteoarthritis; avascular. |
| Joint capsule | Fibrous sleeve enclosing the joint; consists of outer fibrous and inner synovial layers. | Inflamed in capsulitis; provides structural integrity; continuous with periosteum. |
| Synovial membrane | Inner layer of capsule secreting synovial fluid; highly vascularized serous tissue. | Site of inflammation in Rheumatoid Arthritis; produces hyaluronan and lubricin. |
| Synovial fluid | Viscous, non-Newtonian fluid filling the joint cavity; yolk-like consistency. | Provides lubrication and nutrients; altered in septic arthritis. |
| Ligament | Dense regular connective tissue connecting bone to bone. | Frequently torn in sports injuries (sprains); can be extrinsic or intrinsic. |
| Articular disc / Meniscus | Fibrocartilage pad between articulating surfaces (C-shaped or oval). | Torn meniscus is a common knee injury; smooths bone movement. |
| Bursa | Fluid-filled sac lined by synovial membrane. | Reduces friction at pressure points; inflamed in bursitis. |
| Tendon | Dense connective tissue attaching muscle to bone. | Acts as a "dynamic ligament"; prone to tendonitis and rupture. |
| Articular cavity | Fluid-filled space within synovial joints. | Site of joint effusion and hematoma; target for arthrocentesis. |
4. Joint Classification
Joints are classified via two complementary systems: Structural (the binding tissue) and Functional (the range of motion).
4.1 Structural Classification
Scroll the table sideways on a smaller screen.
| Type | Binding Tissue | Examples | Mobility |
|---|---|---|---|
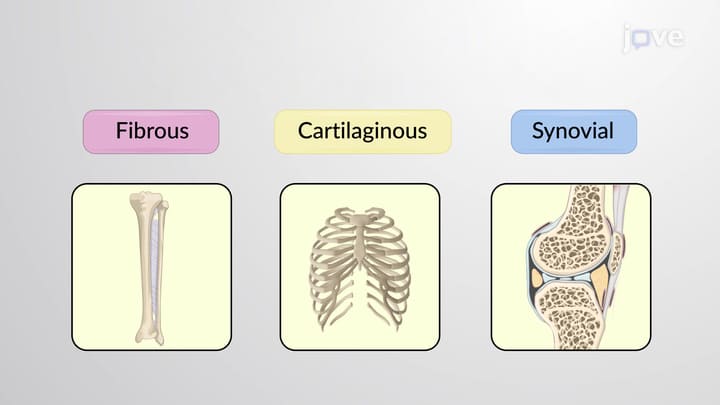
| Fibrous | Dense fibrous connective tissue; no joint cavity. | Cranial sutures, syndesmosis, teeth (gomphosis). | Immovable (Synarthrosis) |
| Cartilaginous | Hyaline cartilage (Primary) or Fibrocartilage (Secondary). | Epiphyseal plates, pubic symphysis, IV discs. | Slightly movable (Amphiarthrosis) |
| Synovial | Not directly joined; enclosed by an articular capsule. | Shoulder, hip, knee, elbow, wrist, ankle. | Freely movable (Diarthrosis) |
4.2 Functional Classification
- Synarthrosis: No movement permitted. Mostly corresponds to fibrous joints (e.g., skull sutures).
- Amphiarthrosis: Slight or partial movement. Mostly corresponds to cartilaginous joints (e.g., intervertebral discs).
- Diarthrosis: Free movement in one or more planes. All synovial joints are diarthroses.
Functional Classification by Axes of Movement (Diarthroses):
Scroll the table sideways on a smaller screen.
| Classification | Axes | Movement Types | Examples |
|---|---|---|---|
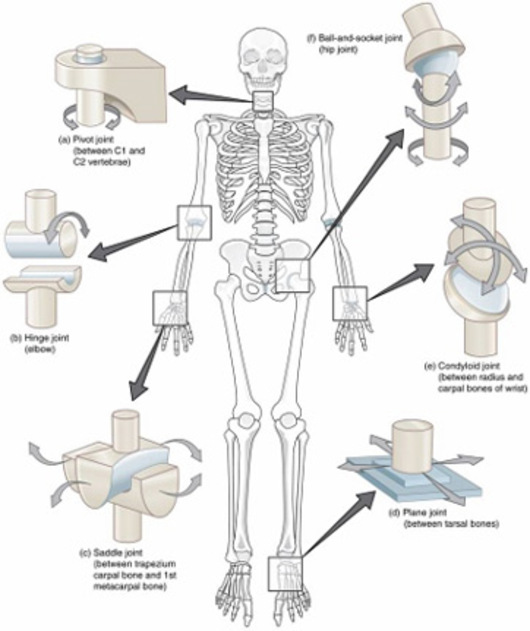
| Uniaxial | One axis | Flexion/Extension only | Hinge (knee); Pivot (atlantoaxial) |
| Biaxial | Two axes | Flexion/Extension + Abduction/Adduction | Condyloid (wrist); Saddle (thumb) |
| Polyaxial | Three axes | All movements including rotation | Ball-and-socket (hip, shoulder) |
4.3 Subtypes of Synovial Joints
Synovial joints are the most movable and are divided into six distinct structural subtypes:
Scroll the table sideways on a smaller screen.
| Type | Description | Movement | Example |
|---|---|---|---|
| Plane (Gliding) | Flat or slightly curved articulating surfaces. | Sliding/gliding | Intercarpal joints, vertebral facet joints. |
| Hinge | Convex surface fits into a concave surface. | Uniaxial: flexion/extension. | Elbow, knee, ankle. |
| Pivot | Rounded bone rotates within a ring of ligament/bone. | Uniaxial: rotation only. | Atlantoaxial joint (C1-C2). |
| Condyloid | Oval-shaped condyle fits into an elliptical cavity. | Biaxial: flexion/extension, abd/add. | Radiocarpal (wrist) joint. |
| Saddle | Both surfaces are concave and convex (saddle-shaped). | Biaxial: all movements except rotation. | 1st carpometacarpal (thumb) joint. |
| Ball-and-Socket | Spherical head fits into a cup-like socket. | Polyaxial: all movements in all planes. | Shoulder, Hip. |
5. SYNOVIAL JOINT STRUCTURE IN DETAIL
5.1 Articular Capsule
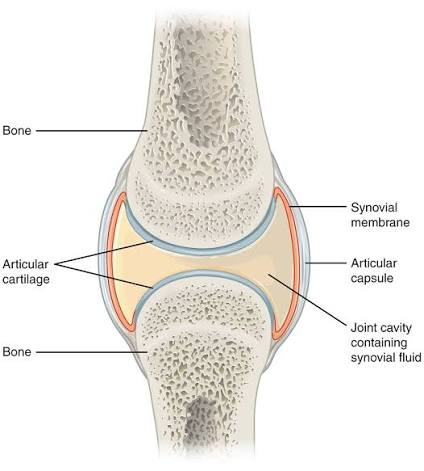
The capsule is continuous with the periosteum and consists of two layers:
- Fibrous Layer (Outer): Dense white fibrous tissue (capsular ligament). It holds the joint together and is highly innervated but lacks blood vessels.
- Synovial Layer (Inner): Also known as the synovium. A highly vascularized layer that secretes and absorbs synovial fluid.
— Type A synoviocytes: Macrophagic cells that remove debris.
— Type B synoviocytes: Fibroblastic cells that manufacture hyaluronan and lubricin.
5.2 Articular Cartilage
Hyaline cartilage serves to minimize friction and absorb shock. It is organized into four zones:
- Superficial zone: Collagen fibers are parallel to the surface.
- Transitional zone: Randomly oriented fibers.
- Deep zone: Fibers are perpendicular to the surface.
- Tidemark: The calcified interface separating cartilage from subchondral bone.

5.3 Synovial Fluid
A non-Newtonian ultrafiltrate of plasma. Viscosity is maintained by hyaluronan molecules. Its three primary functions are:
- Lubrication: Reduces friction during movement.
- Nutrient Distribution: Vital for avascular articular cartilage.
- Shock Absorption: Cushions impact during loading.
5.5 Innervation and Vasculature
Hilton's Law: States that the nerves supplying a joint also supply the muscles moving that joint and the skin covering their distal attachments. Articular nerves transmit proprioceptive (position) and nociceptive (pain) data.
Vasculature: Arterial supply comes from articular arteries forming frequent anastomoses (communications) to ensure blood flow regardless of joint position.
6. CLINICAL CORRELATIONS
6.1 Osteoarthritis (OA)
Pathophysiology: Degenerative wear-and-tear leading to cartilage erosion and exposure of subchondral bone. The bone responds by thickening (sclerosis) and forming osteophytes (spurs).
Clinical Features: Morning stiffness < 30 minutes, crepitus, and pain that worsens with activity.
6.2 Rheumatoid Arthritis (RA)
Pathophysiology: Autoimmune attack on the synovial membrane, causing pannus formation (invasive hyperplastic synovium) that destroys bone and cartilage.
Clinical Features: Symmetrical involvement, prolonged morning stiffness > 1 hour, systemic fatigue/fever.
6.3 Gout
Pathophysiology: Monosodium urate crystals deposit in the joint, activating the NLRP3 inflammasome. Classically affects the 1st MTP joint (podagra).
6.6 Meniscal Tears
Medial meniscus is more commonly injured than the lateral due to its firm attachment to the medial collateral ligament (MCL). Clinical indicators include joint line pain, locking, and a positive McMurray’s test.
Clinical Summary Table
Scroll the table sideways on a smaller screen.
| Condition | Primary Structure Affected | Key Clinical Feature | Management |
|---|---|---|---|
| Osteoarthritis | Articular cartilage | Morning stiffness <30 min | NSAIDs, weight loss, PT |
| Rheumatoid Arthritis | Synovial membrane | Morning stiffness >1 hr; Symmetrical | DMARDs, biologics |
| Gout | Synovial fluid / Cartilage | Acute podagra (1st MTP) | Colchicine, Allopurinol |
| Sprain | Ligament | Instability after trauma | RICE protocol |
| Bursitis | Bursa | Localized swelling; pain with motion | Aspiration, steroid injection |
Lesson map
Use this map to move through the lesson in order:
Further reading
For deeper study, compare this lesson with current guidance and standard references from recognised medical and public-health organisations.