
On this page
Overview
Bone and joint disorders are among the commonest reasons patients seek care — the aching knee, the swollen hand, the child who will not walk, the diabetic foot that will not heal. The diseases look alike at first complaint (pain, stiffness, swelling), yet their mechanisms split cleanly into degeneration, autoimmunity, infection, crystal deposition and metabolic failure. This note maps the anatomy of the healthy joint, then works through osteoarthritis and rheumatoid arthritis, the arthritic mimics, osteomyelitis, and the metabolic and genetic bone disorders — ending with the pattern-recognition skills that separate them at the bedside.
Learning objectives
- Name the structures of a healthy synovial joint and their roles.
- Compare osteoarthritis and rheumatoid arthritis for cause, symmetry, stiffness pattern and radiology.
- Outline the routes, diagnosis and treatment of osteomyelitis.
- Recognise gout, osteoporosis, rickets and Paget's disease at the bedside.
- Differentiate common bone disorders by history, examination and simple investigations.
The healthy joint
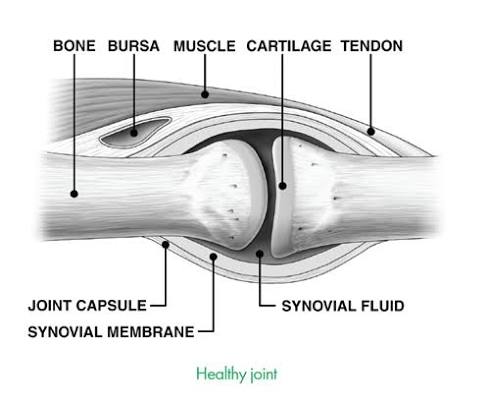
A synovial joint brings together: articular (hyaline) cartilage — the low-friction, avascular cushion covering bone ends; the synovial membrane — secreting lubricating synovial fluid; the fibrous capsule and ligaments stabilising the joint; and nearby bursae and tendons. Each disease below picks its own target: OA destroys the cartilage, RA attacks the synovium, gout inflames the fluid and lining, and bursitis chooses the bursa. Knowing the anatomy is already a diagnostic sieve.
Arthritis: the overview
Arthritis simply means joint inflammation, and over 100 specific types exist. The two that dominate adult practice are osteoarthritis (degenerative) and rheumatoid arthritis (autoimmune); together they teach the two-pathway model every other arthritis relates to.
Osteoarthritis
Osteoarthritis is the commonest joint disease in the world — fundamentally degenerative, driven by mechanical wear exceeding the cartilage's repair capacity.
- Pattern. Usually asymmetrical, slow over years; targets hands (DIP and thumb base), hips, knees and spine — the weight-bearing and over-used joints.
- Symptoms. Morning stiffness under an hour, activity-related pain relieved by rest, crepitus, and slowly restricted movement.
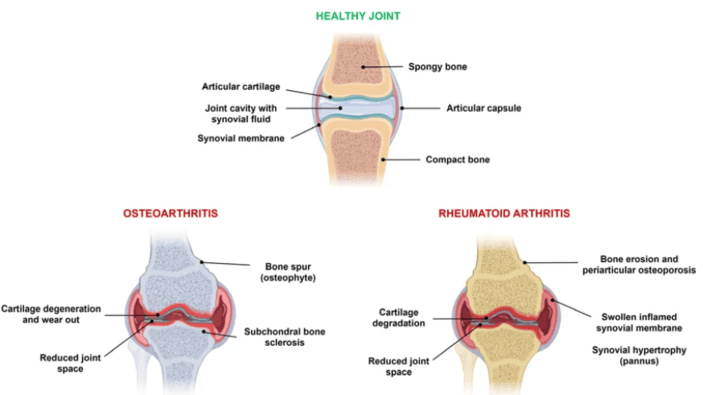
- Pathology. Cartilage thins and fissures until bone meets bone; the joint margin answers with osteophytes (bone spurs). The joint-space narrowing and osteophytes of the radiograph are this pathology in silhouette.
Rheumatoid arthritis
Rheumatoid arthritis is a chronic autoimmune, systemic disease — the immune system targets the synovial membrane.
- Pattern. Symmetrical small-joint involvement — MCPs and PIPs of both hands, wrists — typically starting at age 25–50.
- Symptoms. Morning stiffness over an hour, warmth and swelling, plus systemic features: fatigue, low-grade fever, weight loss.
- Pathology. Chronic synovitis thickens into an invasive pannus, which eats cartilage and produces marginal bony erosions on X-ray. Rheumatoid factor and anti-CCP support the diagnosis; DMARDs (methotrexate first line) and biologics modify the disease, not just the pain.
OA versus RA: the comparison
Scroll the table sideways on a smaller screen.
| Feature | Osteoarthritis | Rheumatoid arthritis |
|---|---|---|
| Cause | Mechanical wear and tear | Autoimmune |
| Age | Usually later life | Any age (peak 25–50) |
| Symmetry | Often asymmetric | Symmetrical |
| Morning stiffness | < 1 hour | > 1 hour |
| Target | Articular cartilage | Synovial membrane (pannus) |
| Bone changes | Osteophytes (spurs) | Marginal erosions |
| Systemic features | None | Fatigue, fever, weight loss |
Other arthritic conditions
Scroll the table sideways on a smaller screen.
| Condition | Mechanism | Bedside clue |
|---|---|---|
| Gout | Uric acid crystal deposition | Sudden, exquisitely painful red big toe (podagra), often at night; high urate |
| SLE | Autoimmune, multi-organ | Arthralgia with rash, photosensitivity, renal involvement |
| Juvenile idiopathic arthritis | Autoimmune, childhood | The child who will not walk; can affect bone growth |
| Fibromyalgia | Widespread pain syndrome | Widespread pain and fatigue — without joint inflammation |
| Bursitis | Bursa inflammation | Localised tenderness (e.g. prepatellar, trochanteric), little joint disease |
Osteomyelitis: infection of bone
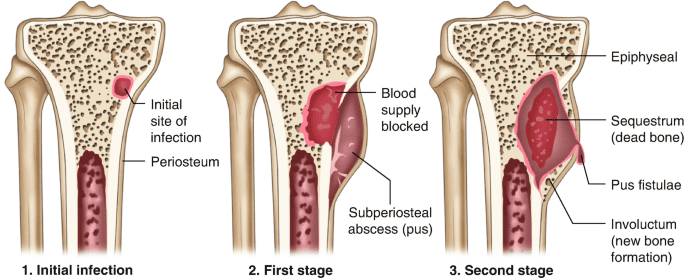
Osteomyelitis is a severe bone infection that can permanently damage or kill bone without prompt treatment. Staphylococcus aureus is the leading pathogen in most settings.
The three routes in:
- Haematogenous spread. Organisms seed bone via the bloodstream from a distant focus (pneumonia, UTI, skin infection) — the classic route in children, where the metaphyseal blood supply favours seeding.
- Direct inoculation. Puncture wounds, open fractures and orthopaedic surgery introduce organisms straight into bone.
- Contiguous spread. Infection reaches bone from adjacent soft tissue — the diabetic foot ulcer is the everyday example.
Diagnosing and treating osteomyelitis
- Diagnosis. Raised ESR and CRP, positive blood cultures when systemic, MRI (most sensitive early imaging; X-ray changes lag 2–3 weeks), and bone biopsy/culture to name the organism before antibiotics where the patient allows.
- Treatment. Aggressive intravenous antibiotics for weeks (staphylococcal cover first), narrowed by culture; surgical debridement to remove the sequestrum (dead bone) and drain abscesses; prolonged oral follow-on therapy. Hyperbaric oxygen is an adjunct in chronic, non-healing cases.
- Complications of delay. Osteonecrosis (dead bone), septicaemia, and in children impaired growth when the epiphyseal plate is involved — a child limping with fever always deserves this diagnosis considered.
Other bone disorders
Scroll the table sideways on a smaller screen.
| Disorder | Mechanism | Presentation / notes |
|---|---|---|
| Osteoporosis | Reduced bone mass and microarchitecture | Fragility fractures (hip, wrist, vertebrae); highest risk in postmenopausal women; treat with calcium, vitamin D, bisphosphonates |
| Paget's disease | Disordered, excessive bone remodelling | Enlarged, deformed, weak bones — skull and pelvis common; raised alkaline phosphatase |
| Osteogenesis imperfecta | Defective type I collagen | "Brittle bone disease" — recurrent fractures from minimal trauma, blue sclerae |
| Rickets / osteomalacia | Vitamin D deficiency → poor mineralisation | Rickets in children (bowed legs, rachitic rosary, wide wrists); osteomalacia in adults (bone pain, fractures) |
| Bone tumours | Primary (osteosarcoma, Ewing) or metastatic | Metastases (breast, prostate, lung) far outnumber primaries; night pain and a mass demand X-ray and referral |
Worked example: three patients, three joints
Scenario. Three patients arrive at the clinic with joint complaints. Sort them by mechanism before you order a single test.
- Patient 1 — 65-year-old, both knees aching for years, worse after walking, stiffness under an hour, crepitus. Chronic, mechanical, big weight-bearing joints, short stiffness: osteoarthritis. X-ray for confirmation; management is activity, weight, analgesia and, when crippling, joint replacement.
- Patient 2 — 38-year-old, both hands and wrists swollen and stiff for three months, stiffness all morning, exhausted and feverish. Symmetrical small joints, prolonged stiffness, systemic features: rheumatoid arthritis until proven otherwise. Check RF and anti-CCP, refer early — DMARDs work best before the erosions form.
- Patient 3 — 12-year-old, fever, refuses to bear weight, CRP markedly raised. Fever plus a non-weight-bearing limb is septic arthritis or acute haematogenous osteomyelitis until proven otherwise — aspirate the joint and start antibiotics after cultures; this is a time-critical diagnosis where delay costs the joint or the growth plate.
The viva point: three patients, one symptom — and the history (symmetry, stiffness duration, fever, age) did all the diagnostic work before any investigation. That is how joint disease is actually practised.
Key points
- Every arthritis attacks a named joint structure — cartilage (OA), synovium (RA), fluid and lining (gout), bursa (bursitis).
- OA: degenerative, asymmetric, stiffness < 1 hour, osteophytes. RA: autoimmune, symmetrical, stiffness > 1 hour, pannus and marginal erosions, DMARDs early.
- Osteomyelitis: staphylococcal, haematogenous in children, contiguous in diabetic feet; treat with weeks of antibiotics plus debridement of the sequestrum.
- A limping febrile child is a septic joint or osteomyelitis until proven otherwise — aspirate and treat urgently.
- Rickets (vitamin D), osteoporosis (bone mass), osteogenesis imperfecta (collagen) and Paget's (remodelling) each define one mechanism of bone failure.
References and further reading
- Klippel JH, et al. Primer on the Rheumatic Diseases — arthritis classification and management. (Library reference.)
- Mandell GL, Bennett JE, Dolin R. Mandell, Douglas and Bennett's Principles and Practice of Infectious Diseases — osteomyelitis. (Library reference.)
- Ralston SH, et al. Davidson's Principles and Practice of Medicine — bone and joint disorders chapters. (Library reference.)
- Ministry of Health, Uganda. Uganda Clinical Guidelines — musculoskeletal infection, fractures and referral. (Library reference.)
For education only. Apply current Uganda Clinical Guidelines, local protocols and specialist advice in clinical practice.