Description of the Skeletal System
A comprehensive anatomical guide covering the skeletal framework, including the axial and appendicular divisions, bone markings, and regional clinical considerations.
1. OVERVIEW AND GENERAL CHARACTERISTICS
The skeletal system is the body's structural framework, comprising 206 bones in the adult human (270 at birth, with many fusing during development). It provides support, protection, movement, mineral storage, and hematopoiesis.
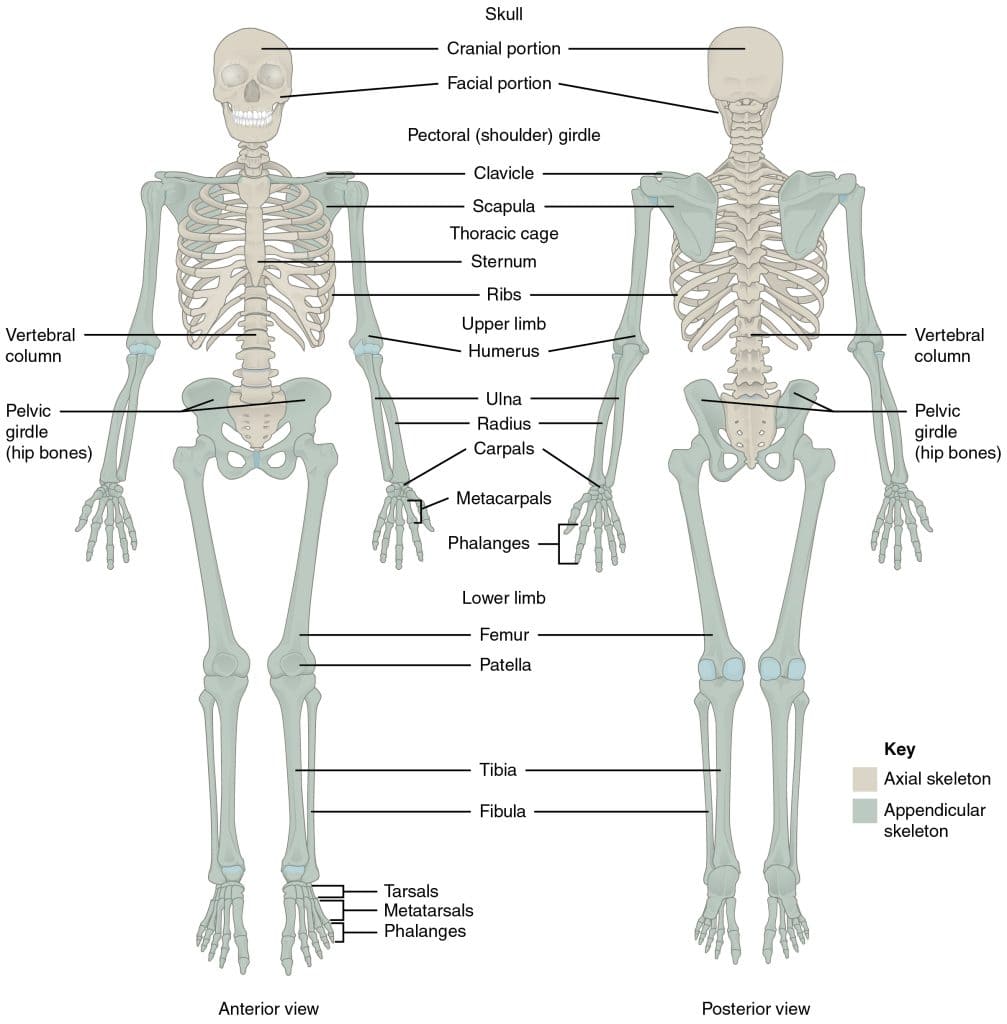
The adult skeleton weighs approximately 10–15 kg in a 70 kg adult and represents about 12–15% of total body weight. Bone is a dynamic, living tissue with a rich blood supply (5–10% of cardiac output) and extensive innervation. The skeleton is divided into two major divisions: the axial skeleton (80 bones) and the appendicular skeleton (126 bones).
| Feature | Axial Skeleton (80 bones) | Appendicular Skeleton (126 bones) |
|---|---|---|
| Primary Function | Protection of CNS and vital organs; support of head/trunk | Locomotion; manipulation of environment; suspension of limbs |
| Major Components | Skull, vertebral column, thoracic cage, hyoid, ossicles | Pectoral girdle, upper limbs, pelvic girdle, lower limbs |
| Clinical Focus | Spinal cord injuries, skull fractures, thoracic trauma | Fractures, dislocations, arthritis, sports injuries, developmental issues |
2. THE AXIAL SKELETON — Overview
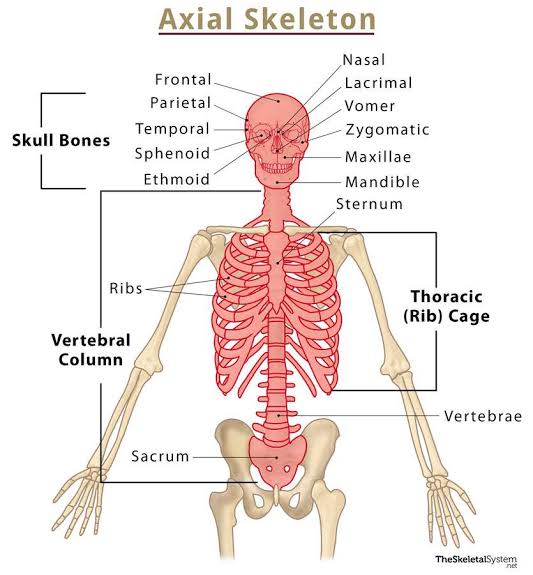
The axial skeleton forms the central axis of the body. It includes the skull (22 bones), vertebral column (26 bones in adults), thoracic cage (sternum + 12 pairs of ribs + 12 thoracic vertebrae), the hyoid bone, and the 6 auditory ossicles. It protects the brain, spinal cord, heart, and lungs while providing attachment points for the muscles of the head, neck, and trunk.
2.1 The Skull (Cranium) — Cranial & Facial Bones
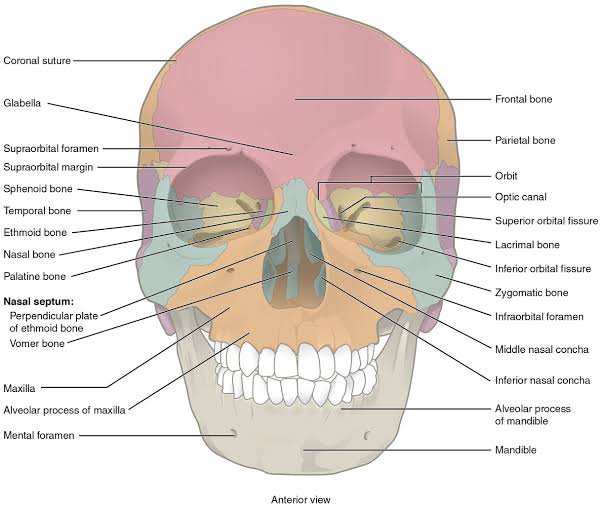
The skull consists of 22 bones (8 cranial + 14 facial) plus 6 auditory ossicles and the hyoid bone. It protects the brain, supports facial structures, and provides attachment for muscles of mastication and facial expression.
CRANIAL BONES (8 bones):
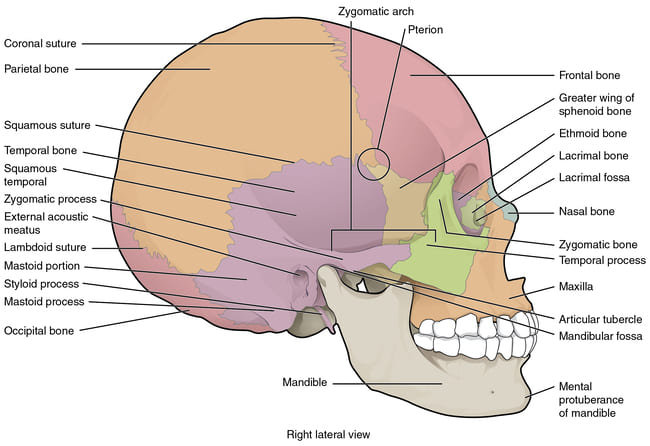
- Frontal Bone (1): Forms the forehead and superior part of the orbits. Contains frontal sinuses. Clinical: Frontal bone fractures can involve the anterior cranial fossa and frontal sinus, risking CSF leak and infection.
- Parietal Bones (2): Form the superior and lateral walls of the cranium. Articulate at sagittal suture, coronal suture with frontal, lambdoid suture with occipital. Clinical: Depressed skull fractures often involve the parietal bones due to their broad, thin structure.
- Temporal Bones (2): Complex bones on the lateral skull base containing external auditory meatus, mastoid process, styloid process, zygomatic process, and mandibular fossa. Houses middle and inner ear structures. Clinical: Mastoiditis can complicate otitis media. Temporal bone fractures can injure facial nerve (CN VII) and internal carotid artery.
- Occipital Bone (1): Forms the posterior skull base and posterior cranial fossa. Contains foramen magnum (spinal cord passage) and occipital condyles (articulate with atlas/C1). Clinical: Basilar skull fractures can cause Battle's sign (mastoid ecchymosis) and CSF otorrhoea/rhinorrhea.
- Sphenoid Bone (1): The 'keystone' of the cranium — articulates with all other cranial bones. Butterfly-shaped with greater and lesser wings, body (sphenoid sinuses), pterygoid processes. Contains sella turcica (pituitary gland) and foramina (rotundum, ovale, spinosum). Clinical: Sphenoid wing meningiomas can compress the optic nerve.
- Ethmoid Bone (1): Complex bone between the orbits, forming part of medial orbital wall, nasal cavity roof, and nasal septum. Contains cribriform plate (olfactory nerve passage) and ethmoid air cells. Clinical: Fractures can cause anosmia and CSF rhinorrhea. Ethmoid sinusitis can lead to orbital cellulitis.
FACIAL BONES (14 bones):
- Maxillae (2): Upper jaw bones; contain maxillary sinuses (largest paranasal sinuses) and alveolar processes (hold upper teeth). Form anterior hard palate and floor of orbits. Clinical: Le Fort I, II, III fractures are common in facial trauma. Maxillary sinusitis is the most common sinus infection.
- Mandible (1): The only movable skull bone. U-shaped with body, ramus, condylar process (articulates with temporal bone at TMJ), coronoid process, and alveolar process. Clinical: Most commonly fractured facial bone. Condylar fractures can cause malocclusion.
- Zygomatic Bones (2): Cheekbones; articulate with frontal, temporal, maxillary, and sphenoid bones. Form lateral orbital wall and part of zygomatic arch. Clinical: Zygomatic fractures ('tripod' or 'malar' fractures) cause flattening of the cheek and infraorbital nerve anesthesia.
- Nasal Bones (2): Small rectangular bones forming the bridge of the nose. Clinical: Most commonly fractured bone in the face due to prominence and thinness.
- Lacrimal Bones (2): Smallest facial bones; form part of medial orbital wall and contain lacrimal fossa (houses lacrimal sac). Clinical: Involved in nasolacrimal duct obstruction causing epiphora (excessive tearing).
- Palatine Bones (2): L-shaped bones forming posterior hard palate and part of lateral nasal wall and orbital floor. Clinical: Cleft palate involves failure of fusion of palatine processes.
- Inferior Nasal Conchae (2): Scroll-like bones projecting into nasal cavity, increasing surface area for warming and humidifying air. Clinical: Can become enlarged in chronic rhinitis and may require surgical reduction (turbinectomy).
- Vomer (1): Thin, plow-shaped bone forming inferior part of nasal septum. Clinical: Deviated nasal septum (often involving vomer and perpendicular plate of ethmoid) can cause nasal obstruction and sinusitis.
2.2 The Vertebral Column
The vertebral column consists of 33 vertebrae in the newborn: 7 cervical, 12 thoracic, 5 lumbar, 5 sacral (fuse to form sacrum), and 4 coccygeal (fuse to form coccyx). In adults, this becomes 26 bones due to fusion. The spine protects the spinal cord, supports the head and trunk, and allows movement while maintaining an S-shaped curvature.
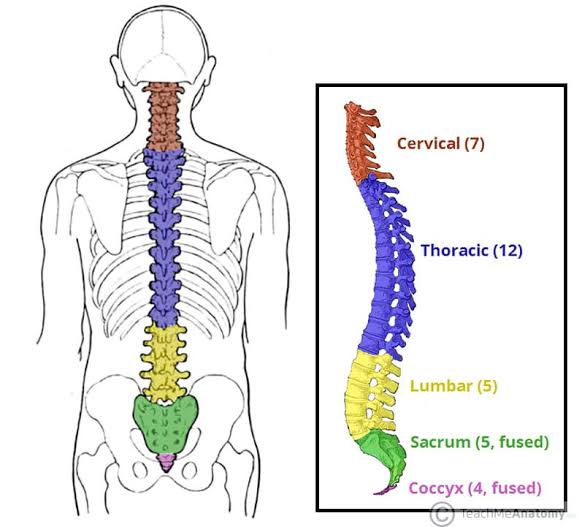
Vertebral Column — Regional Characteristics
| Region | Count | Distinguishing Features | Clinical Relevance |
|---|---|---|---|
| Cervical (C1–C7) | 7 | Small bodies; transverse foramina (vertebral artery passage); bifid spinous processes (C2–C6). C1 (atlas) articulates with occipital condyles. C2 (axis) has the dens (pivot for rotation). C7 (vertebra prominens) is a palpable landmark. | C-spine fractures (C1/C2 most lethal); injury to vertebral artery. |
| Thoracic (T1–T12) | 12 | Medium-sized bodies with costal facets for rib articulation. Long, downward-pointing spinous processes. Narrow vertebral foramina. | Thoracic outlet syndrome; Scheuermann's disease (kyphosis). |
| Lumbar (L1–L5) | 5 | Large, kidney-shaped bodies; short, thick spinous processes. No costal facets. Triangular vertebral foramina. L5 has a massive transverse process articulating with sacrum. | Lumbar disc herniation (L4-L5, L5-S1 common); spinal stenosis. |
| Sacrum | 5 fused | Triangular, curved bone; articulates with ilia at sacroiliac joints. Contains the sacral canal and sacral hiatus. Sacral promontory is the anterior superior margin. | Sacral fractures; caudal epidural access point via hiatus; landmark for pelvic inlet measurement. |
| Coccyx | 3–5 fused | Small, triangular vestigial bone; articulates with sacrum. Attachment for pelvic floor muscles (coccygeus, levator ani) and ligaments. | Coccydynia (tailbone pain); difficulty in vaginal delivery if fractured/rigid. |
The spinal cord ends at the conus medullaris (L1–L2 in adults). Below this, the vertebral canal contains the cauda equina (bundle of nerve roots). Lumbar puncture must be performed below L2 (typically L3-L4 or L4-L5 interspace) to avoid direct spinal cord injury. The subarachnoid space extends to S2.
2.3 The Thoracic Cage
The thoracic cage consists of the sternum, 12 pairs of ribs, and the 12 thoracic vertebrae. It protects the heart, lungs, and great vessels, provides attachment for respiratory muscles, and plays a critical role in the mechanics of breathing.
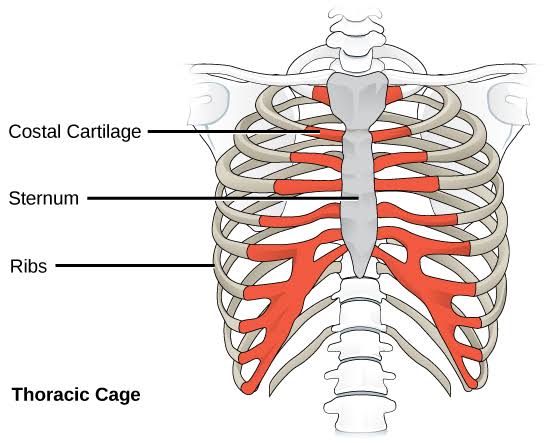
The Sternum: A flat bone consisting of three parts: the manubrium (superior, articulates with clavicles and first rib), the body/gladiolus (middle, articulates with ribs 2–7), and the xiphoid process (inferior, ossifies by age 40). The manubriosternal joint (Angle of Louis) marks the level of the second costal cartilage, tracheal bifurcation, and aortic arch.
| Type | Count | Characteristics | Clinical Relevance |
|---|---|---|---|
| True Ribs (Vertebrosternal) | 1st–7th pairs | Directly attach to sternum via individual costal cartilage. | Rib fractures most common in ribs 4–9; 1st rib fracture indicates severe trauma. |
| False Ribs (Vertebrochondral) | 8th–10th pairs | Indirectly attach to sternum via costal cartilage of the rib above. | Costal margin tenderness in cholecystitis (Murphy's sign). |
| Floating Ribs | 11th–12th pairs | No anterior attachment; short with a pointed end. | Prone to traumatic fracture; can injure kidneys. |
2.4 Auditory Ossicles and Hyoid Bone
The malleus (hammer), incus (anvil), and stapes (stirrup) are the smallest bones in the body. They transmit sound vibrations from the tympanic membrane to the oval window of the inner ear, amplifying sound pressure ~20-fold.
Clinical: Otosclerosis (abnormal bone growth around the stapes) causes conductive hearing loss. Ossicular chain disruption occurs in temporal bone trauma.
The only bone in the body that does not articulate with any other bone. U-shaped, located in the anterior neck at the C3 level. Serves as attachment for tongue muscles, suprahyoid muscles (digastric, stylohyoid, mylohyoid, geniohyoid), and infrahyoid muscles (sternohyoid, omohyoid, sternothyroid, thyrohyoid).
Clinical: Hyoid bone fractures indicate strangulation/hanging. Landmark for cricothyrotomy.
3. THE APPENDICULAR SKELETON — Full Overview
The appendicular skeleton includes the pectoral girdle (clavicle, scapula), upper limbs (humerus, radius, ulna, hand bones), pelvic girdle (hip bones), and lower limbs (femur, tibia, fibula, foot bones). It enables locomotion and manipulation of the environment.
3.1 The Pectoral (Shoulder) Girdle & 3.2 The Upper Limb
The pectoral girdle connects the upper limbs to the axial skeleton. It consists of the clavicle and scapula on each side. Unlike the pelvic girdle, it is not directly attached to the vertebral column, allowing great mobility.
- Clavicle (Collarbone): S-shaped bone articulating medially with the manubrium (sternoclavicular joint) and laterally with the acromion of the scapula (acromioclavicular joint). The only long bone that lies horizontally. Clinical: Most commonly fractured bone in children (midshaft, from falls on outstretched hand). Fractures can injure the subclavian vessels and brachial plexus.
- Scapula (Shoulder Blade): Large, flat, triangular bone on the posterior thorax (ribs 2–7). Features include the spine, acromion, coracoid process, glenoid cavity (articulates with humerus), supraspinous and infraspinous fossae, and subscapular fossa. Clinical: Scapular fractures indicate high-energy trauma. Winging of the scapula indicates long thoracic nerve (C5-C7) injury → serratus anterior paralysis.
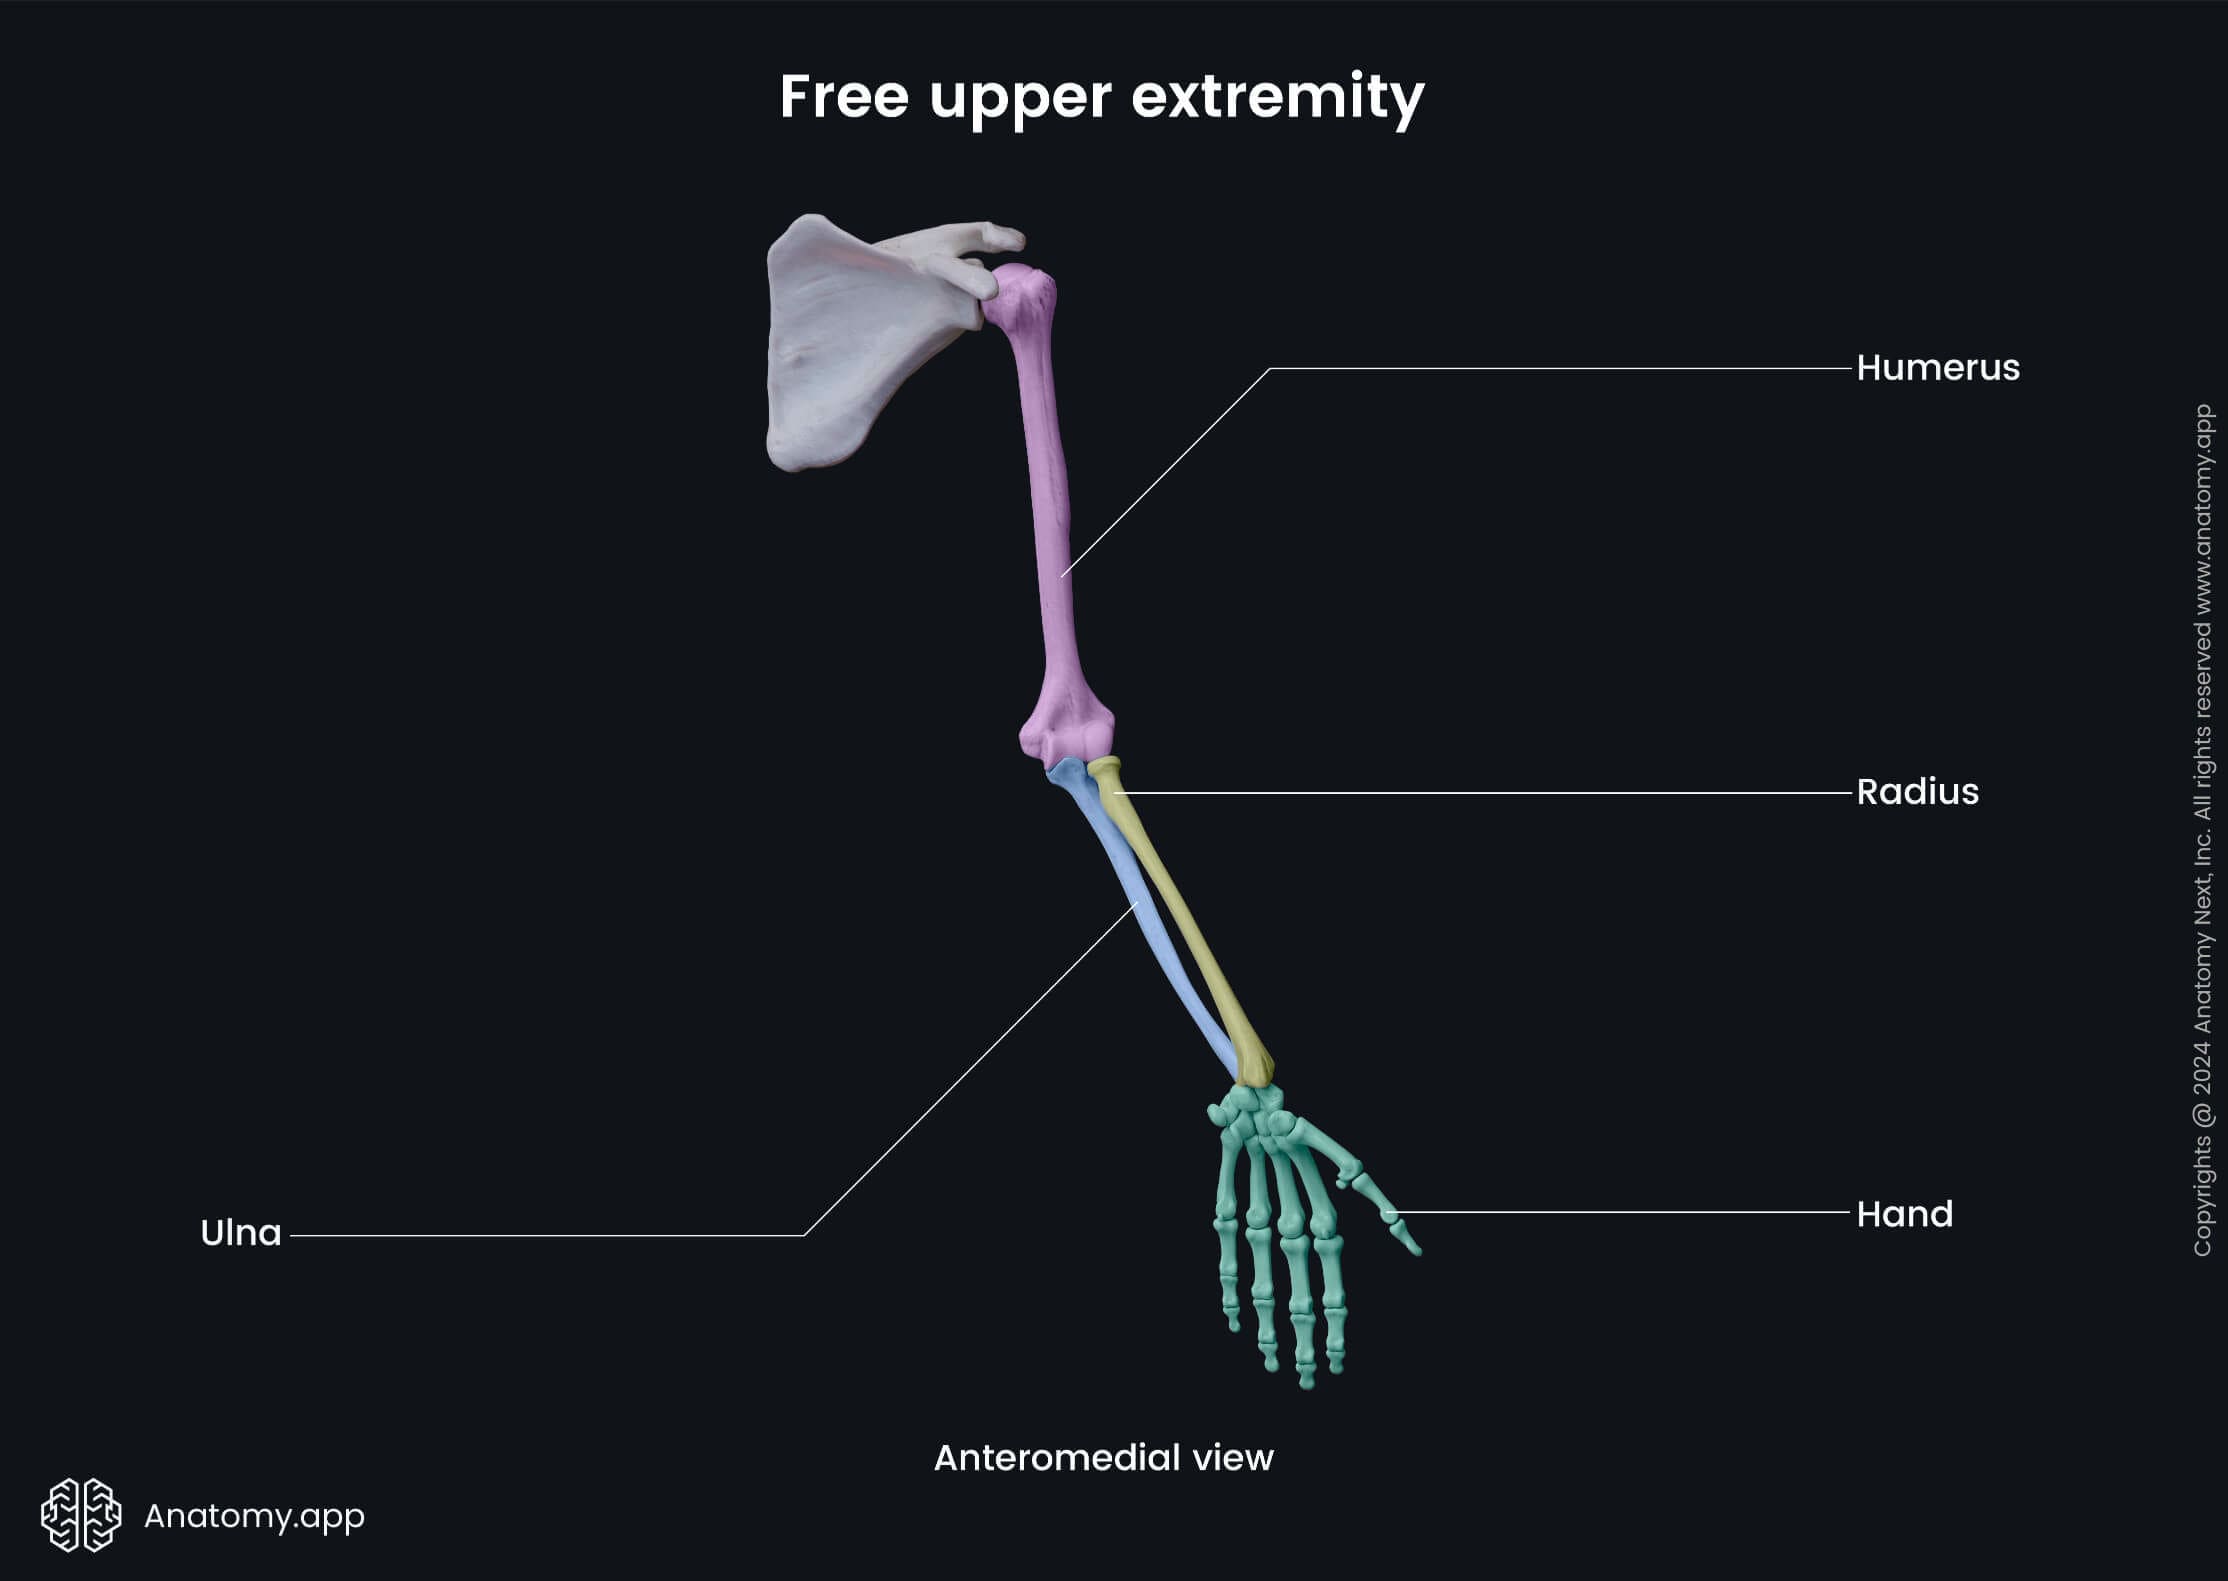
3.2 The Upper Limb — Detailed Anatomy
Arm (Brachium) — Humerus: Longest bone of the upper limb. Proximal end: head (articulates with glenoid), greater tubercle (supraspinatus, infraspinatus, teres minor insertions), lesser tubercle (subscapularis insertion), intertubercular (bicipital) groove (long head of biceps tendon). Shaft: deltoid tuberosity, radial (spiral) groove (radial nerve + profunda brachii artery). Distal end: medial and lateral epicondyles, trochlea (articulates with ulna), capitulum (articulates with radius), coronoid and olecranon fossae. Clinical: Supracondylar fractures (common in children) can injure the brachial artery and median nerve → Volkmann's ischemic contracture. Radial nerve injury in the spiral groove causes "wrist drop."
Forearm (Antebrachium):
- Radius: Lateral forearm bone. Proximal head articulates with capitulum of humerus and radial notch of ulna (pivot joint). Distal end is broad, articulates with scaphoid and lunate (wrist), and has the styloid process. The radius crosses over the ulna during pronation. Clinical: Distal radius fractures (Colles' fracture — 'dinner fork' deformity) are the most common fracture in adults >50 years.
- Ulna: Medial forearm bone. Proximal end: olecranon (triceps insertion), coronoid process, trochlear notch (articulates with humeral trochlea), radial notch. Distal end: head and styloid process. The ulna does not articulate with carpal bones. Clinical: Olecranon fractures disrupt triceps function. Ulnar nerve injury at the cubital tunnel causes "claw hand" (ulnar claw).
Hand:
- Carpal Bones (8): Proximal row: scaphoid, lunate, triquetrum, pisiform. Distal row: trapezium, trapezoid, capitate, hamate. Clinical: Scaphoid fractures (most common carpal fracture) have high non-union and avascular necrosis risk due to retrograde blood supply. Hamate hook fractures occur in golfers/baseball players. Carpal tunnel syndrome involves median nerve compression under the flexor retinaculum.
- Metacarpals (5): Numbered I–V from thumb to little finger. Clinical: Boxer's fracture (5th metacarpal neck fracture) from punching. Bennett's fracture (base of 1st metacarpal intra-articular) requires surgical fixation.
- Phalanges (14 per hand): Proximal, middle, and distal phalanges for digits 2–5; thumb has only proximal and distal. Clinical: Tuft fractures (distal phalanx) are common crush injuries. Mallet finger (extensor tendon avulsion from distal phalanx) causes flexion deformity.
3.3 The Pelvic Girdle
The pelvic girdle consists of the two hip (coxal) bones, each formed by the fusion of three bones (ilium, ischium, pubis) at the acetabulum. It articulates posteriorly with the sacrum (sacroiliac joints) and anteriorly with each other at the pubic symphysis. The pelvis transmits body weight from the vertebral column to the lower limbs and protects pelvic organs.
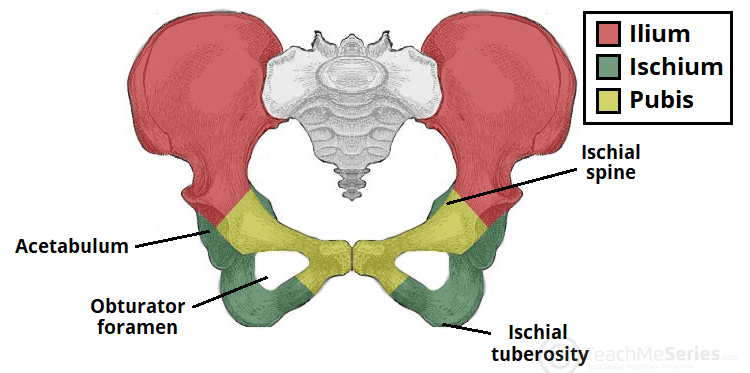
- Ilium: The broad, flared superior portion. Features: iliac crest (attachment for abdominal wall muscles), anterior superior iliac spine (ASIS — inguinal ligament attachment, landmark for lumbar puncture), anterior inferior iliac spine (rectus femoris origin), posterior superior iliac spine (PSIS — dimple of Venus, landmark for sacroiliac joint), greater sciatic notch. The iliac fossa is the origin of iliacus muscle. Clinical: Iliac crest is the standard site for bone marrow biopsy. Avulsion fractures of ASIS occur in adolescent athletes (sartorius origin).
- Ischium: The posterior-inferior 'sit bone.' Features: ischial tuberosity (hamstring origin), ischial spine (sacrospinous ligament attachment, boundary of greater/lesser sciatic foramina), lesser sciatic notch. Clinical: Ischial bursitis ('weaver's bottom') causes pain when sitting. The ischial spine is an important landmark in obstetrics (assessment of pelvic outlet).
- Pubis: The anterior portion. Features: body, superior and inferior rami, pubic tubercle (inguinal ligament medial attachment), pubic crest. The obturator foramen is formed by the pubis and ischium (closed by obturator membrane except for the obturator canal). Clinical: Pubic rami fractures are common in elderly falls (osteoporotic). Osteitis pubis is an inflammatory condition of the pubic symphysis in athletes.
3.4 The Lower Limb
Thigh (Femur): The longest and strongest bone in the body. Proximal end: head (articulates with acetabulum, supplied by medial circumflex femoral artery — critical for blood supply), neck (common fracture site in elderly), greater trochanter (gluteus medius/minimus insertion), lesser trochanter (iliopsoas insertion), intertrochanteric line and crest. Shaft: linea aspera (attachment for adductors and vastus muscles). Distal end: medial and lateral condyles (articulate with tibia), medial and lateral epicondyles, intercondylar fossa (cruciate ligament attachments), patellar surface.
Clinical: Femoral neck fractures (intracapsular) have high avascular necrosis risk due to tenuous retinacular blood supply. Intertrochanteric fractures (extracapsular) have better blood supply and healing. Femoral shaft fractures in adults require intramedullary nailing.
Leg (Crus):
- Tibia: The larger, medial weight-bearing bone of the leg. Proximal end: medial and lateral condyles (articulate with femoral condyles), tibial tuberosity (patellar ligament insertion), intercondylar eminence. Shaft: anterior border (subcutaneous — 'shin'), interosseous membrane (attachment for fibula). Distal end: medial malleolus (forms medial ankle), fibular notch. Clinical: Tibial shaft fractures are common open fractures. Proximal tibial fractures can injure the popliteal artery. Stress fractures occur in runners ('shin splints' → medial tibial stress syndrome).
- Fibula: The slender, lateral non-weight-bearing bone. Proximal head articulates with tibia (proximal tibiofibular joint). Shaft: attachment for muscles of lateral compartment (peroneus longus and brevis). Distal end: lateral malleolus (forms lateral ankle, extends further distally than medial malleolus — stabilizes ankle). Clinical: Fibular fractures often accompany ankle fractures (Weber classification). Isolated fibular shaft fractures (Maisonneuve fracture) indicate high ankle injury with syndesmotic disruption.
Foot:
- Tarsal Bones (7): Talus (articulates with tibia/fibula superiorly, calcaneus inferiorly, navicular anteriorly — no muscle attachments, entirely covered by cartilage), calcaneus (heel bone, largest tarsal, Achilles tendon insertion), navicular, cuboid, and three cuneiforms (medial, intermediate, lateral). Clinical: Calcaneal fractures result from high-energy falls ('lover's fracture'). Talus fractures have high avascular necrosis risk (Hawkins classification). Navicular stress fractures in athletes.
- Metatarsals (5): Numbered I–V from medial to lateral. The 1st metatarsal is the thickest and shortest; the 2nd is the longest and most rigidly fixed. Clinical: Jones fracture (base of 5th metatarsal — prone to non-union). Stress fractures of 2nd/3rd metatarsals ('march fracture') in military recruits. Metatarsalgia (pain under metatarsal heads).
- Phalanges (14 per foot): Similar arrangement to hand. Hallux (great toe) has only proximal and distal phalanges. Clinical: Hallux valgus (bunion) — lateral deviation of hallux with medial eminence. Hammer toe and claw toe deformities. Turf toe (sprain of 1st MTP joint plantar capsule).
Pelvic fractures are associated with significant morbidity and mortality due to potential massive hemorrhage (pelvic venous plexus can hold 4+ liters of blood). The Young-Burgess and Tile classification systems guide management. Hemodynamic instability with pelvic fracture requires emergent pelvic binding and angiography/embolization.
4. BONE MARKINGS (Surface Features)
Bone markings reflect the functional demands placed on bones — sites of muscle/ligament attachment, joint articulation, and passage of neurovascular structures. Recognizing these markings is essential for interpreting radiographs and understanding clinical anatomy.
| Category | Term | Description | Examples |
|---|---|---|---|
| Projections | Process | Any bony prominence | Spinous process of vertebra, mastoid process |
| Projections | Tubercle | Small, rounded projection | Greater and lesser tubercles of humerus, pubic tubercle |
| Projections | Tuberosity | Large, rough projection (often for tendon attachment) | Ischial tuberosity, tibial tuberosity, radial tuberosity |
| Projections | Crest | Ridge of bone | Iliac crest, intertrochanteric crest |
| Projections | Spine | Sharp, slender projection | Ischial spine, anterior nasal spine |
| Projections | Epicondyle | Projection above a condyle | Medial and lateral epicondyles of humerus/femur |
| Projections | Condyle | Rounded articular projection | Medial and lateral condyles of femur and tibia |
| Projections | Head | Rounded articular end of bone | Head of femur, head of humerus, head of radius |
| Depressions | Fossa | Shallow depression | Olecranon fossa, coronoid fossa, infraspinous fossa |
| Depressions | Fovea | Small pit or depression | Fovea capitis of femoral head (ligamentum teres site) |
| Depressions | Groove (Sulcus) | Furrow or channel | Intertubercular (bicipital) groove of humerus |
| Openings | Foramen | Hole through which vessels/nerves pass | Foramen magnum, obturator foramen, infraorbital foramen |
| Openings | Canal | Longer, tube-like passageway | Auditory canal, carotid canal, vertebral canal |
| Openings | Fissure | Narrow, slit-like opening | Superior and inferior orbital fissures, petrotympanic fissure |
| Articulating Surfaces | Facet | Small, flat articular surface | Costal facets of thoracic vertebrae, articular facets of vertebrae |
Clinical Notes — Thoracic & Rib Fractures
Rib fractures are the most common thoracic injury. The 1st and 2nd ribs are protected by the clavicle and scapula; the 10th-12th ribs are short and more mobile. Ribs 4–9 are most commonly fractured.
A flail chest occurs when ≥3 adjacent ribs are fractured in ≥2 places, creating a free-floating segment that moves paradoxically with respiration. This requires immediate intervention as it compromises ventilation and can lead to respiratory failure.
The spinal cord ends at the conus medullaris (L1–L2 in adults). Below this, the vertebral canal contains the cauda equina (bundle of nerve roots). Lumbar puncture must be performed below L2 (typically L3-L4 or L4-L5 interspace) to avoid direct spinal cord injury. The subarachnoid space extends to S2.
Key landmarks for lumbar puncture:
- Tuffier's line: Connects the highest points of both iliac crests → intersects at L4 spinous process.
- The needle is inserted between L3-L4, L4-L5, or L5-S1 interspaces.
