Doctors Revision

Author name: doctorsrevision@gmail.com

Composition and functions of blood
Anatomy

Composition and functions of blood

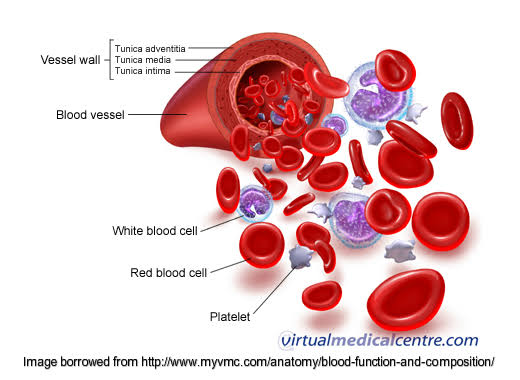
Composition and Functions of Blood Complete study notes covering the definition, general characteristics, detailed composition of plasma and formed elements, hematopoiesis, and clinical correlations. 1. Composition and Functions of Blood 1.1 Definition and General Characteristics Blood is a specialized connective tissue consisting of cells suspended in a liquid extracellular matrix called plasma. It circulates through the heart, arteries, capillaries, and veins, maintaining homeostasis throughout the body. Key Parameters: Total blood volume: ~7-8% of body weight (5-6 L in a 70 kg adult male). pH: 7.35-7.45 (slightly alkaline). Temperature: ~38°C (slightly higher than core body temperature). Viscosity: 3-5 times greater than water. Color: Bright red (oxygenated) to dark red (deoxygenated). Specific gravity: 1.055-1.065. 1.2 Composition of Blood Blood consists of two principal components: Component Percentage Constituents Plasma 55% Water (92%), proteins (7%), solutes (1%) Formed elements 45% Erythrocytes (99%), leukocytes, platelets Buffy coat <1% Leukocytes and platelets (after centrifugation) 1.2.1 Plasma Plasma is the straw-colored liquid portion of blood. Water (92%): Serves as solvent for transport. Plasma Proteins (7%): Albumin: Liver origin; maintains colloid osmotic pressure; transports fatty acids, bilirubin, and drugs. Globulins: Alpha/beta transport lipids, iron, copper; gamma = immunoglobulins. Fibrinogen: Liver origin; essential for blood clotting (converted to fibrin). Other Solutes (1%): Electrolytes (Na+, K+, Ca2+, Mg2+, Cl-, HCO3-, HPO4^2-) Nutrients (glucose, amino acids, fatty acids, vitamins) Waste products (urea, uric acid, creatinine, bilirubin) Respiratory gases (O2, CO2) and hormones 1.2.2 Erythrocytes (Red Blood Cells) Structure: Biconcave disc shape; 7-8 um in diameter. Anucleate (no nucleus) and lack organelles in mature form. Cell membrane contains spectrin and actin for flexibility through capillaries. Cytoplasm filled with hemoglobin (~280 million molecules per cell). Hemoglobin: Molecular weight: 64,458 Da. Four polypeptide chains (2 alpha, 2 beta in adults = HbA) + four heme groups. Each heme contains Fe2+ binding one O2 molecule. Normal types: HbA (95-98%), HbA2 (2-3%), HbF (<1% in adults). Function: Transport of O2 from lungs to tissues and CO2 from tissues to lungs. Normal Values: Parameter Adult Male Adult Female RBC count 4.5-5.5 x 10^12/L 4.0-5.0 x 10^12/L Hemoglobin 13.5-17.5 g/dL 12.0-16.0 g/dL Hematocrit 40-54% 37-47% MCV 80-100 fL 80-100 fL MCH 27-33 pg 27-33 pg MCHC 32-36 g/dL 32-36 g/dL Lifespan: 120 days. Senescent RBCs removed by macrophages in spleen, liver, and bone marrow. 1.2.3 Leukocytes (White Blood Cells) Leukocytes are nucleated cells critical for immune defense. Type % Key Features Functions Neutrophils 50-70% Multilobed nucleus (2-5); Fine lilac granules Phagocytosis of bacteria; first responders to acute inflammation Eosinophils 1-4% Bilobed nucleus; red-orange granules Defense against parasites; modulate allergic responses Basophils 0.5-1% S-lobed nucleus; deep blue granules Release histamine and heparin; mediate allergic reactions Lymphocytes 20-40% Large round nucleus; scant cytoplasm B cells = antibodies; T cells = cellular immunity; NK cells = tumors Monocytes 2-8% Kidney-shaped nucleus; gray cytoplasm Differentiate into macrophages; phagocytosis; antigen presentation Normal total WBC count: 4,000-11,000 cells/uL (4.0-11.0 x 10^9/L). 1.2.4 Platelets (Thrombocytes) Small cell fragments (2-4 um) derived from megakaryocytes in bone marrow. Anucleate but contain mitochondria, lysosomes, and granules. Normal count: 150,000-400,000/uL (150-400 x 10^9/L). Lifespan: 8-10 days. Functions: Formation of platelet plugs during hemostasis. Clot retraction through actin and myosin filaments. Release of growth factors (PDGF) promoting tissue repair. 1.3 Hematopoiesis Hematopoiesis is the process of blood cell formation. In adults, it occurs primarily in red bone marrow (sternum, ribs, vertebrae, pelvis, proximal femurs, and humeri). Stages: Pluripotent hematopoietic stem cells — self-renewal and differentiation. Multipotent progenitor cells — myeloid and lymphoid lineages. Committed progenitor cells — specific cell lines. Precursor cells (blasts) — immature forms with specific morphology. Mature cells — released into circulation. Key Regulatory Factors: Erythropoietin (EPO): Kidney production; stimulates erythropoiesis. Colony-stimulating factors (CSFs): Stimulate granulocyte/monocyte production. Thrombopoietin (TPO): Stimulates megakaryocyte and platelet production. Interleukins: Regulate lymphocyte development and immune responses. 1.4 Functions of Blood Function Mechanism Clinical Relevance Transport Carries O2, CO2, nutrients, hormones, waste products, heat Hypoxia in anemia; uremia in renal failure Regulation Buffers pH (bicarbonate); regulates temperature; maintains osmotic pressure Acid-base disorders; edema in hypoalbuminemia Protection Immune function (WBCs, antibodies); hemostasis (platelets, clotting factors) Immunodeficiency; bleeding disorders 1.5 Clinical Correlation: Complete Blood Count (CBC) The CBC is the most commonly ordered hematological investigation. It provides: RBC count, hemoglobin, hematocrit. RBC indices (MCV, MCH, MCHC, RDW). WBC count with differential. Platelet count. Peripheral blood smear morphology. Clinical Pearl A peripheral blood smear examination remains essential for confirming automated CBC findings and identifying morphological abnormalities such as sickle cells, schistocytes, or blast cells. Summary — Composition and Functions of Blood Key Points to Remember Blood volume: 5-6 L in adults. Plasma vs Formed elements: 55% vs 45%. RBC Lifespan: 120 days. Platelet Lifespan: 8-10 days. Hematopoiesis: Occurs in red bone marrow, regulated by EPO, TPO, and cytokines. Primary functions: Transport, Regulation, and Protection.
Types of blood groups
Anatomy

Types of blood groups

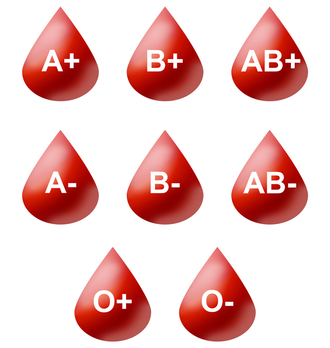
Types of Blood Groups Complete study notes covering the genetics, biochemistry, compatibility, and clinical significance of the ABO and Rh systems, as well as minor blood group systems and cross-matching procedures. 2.1 Introduction Blood groups are determined by antigenic substances (glycoproteins and glycolipids) present on the surface of erythrocytes. The two most clinically significant systems are the ABO and Rh systems. Historical Note ABO system: Discovered by Karl Landsteiner in 1900 (Nobel Prize, 1930). Rh system: Identified by Landsteiner and Wiener in 1939. 2.2 ABO Blood Group System The ABO system is governed by three alleles (I^A, I^B, and i) located on chromosome 9. 2.2.1 Genetics and Biochemistry Genotype Phenotype RBC Antigens Plasma Antibodies I^A I^A or I^A i A A antigen Anti-B I^B I^B or I^B i B B antigen Anti-A I^A I^B AB A and B antigens None ii O None (H only) Anti-A and Anti-B Biochemical Basis: The H antigen (precursor) is present on all RBCs. I^A allele codes for an enzyme adding N-acetylgalactosamine = A antigen. I^B allele codes for an enzyme adding galactose = B antigen. i allele is non-functional; no modification of H antigen occurs. Antibody Characteristics: Anti-A and Anti-B are naturally occurring (develop by 3-6 months of age). They are IgM antibodies, capable of fixing complement. Cause rapid intravascular hemolysis. Primary cause of acute hemolytic transfusion reactions. Bombay Phenotype (hh) Rare individuals lack H antigen due to FUT1 gene mutations. They type as O but possess anti-H, anti-A, and anti-B antibodies, making blood transfusion extremely difficult as they can only receive blood from other Bombay phenotype donors. 2.2.2 ABO Compatibility for Transfusion Recipient Can Receive From Can Donate To A A, O A, AB B B, O B, AB AB A, B, AB, O (univ. rec) AB only O O only A, B, AB, O (univ. donor) **Universal donor:** O negative (no A, B, or D antigens). **Universal recipient:** AB positive (no anti-A, anti-B, or anti-D antibodies). 2.3 Rh Blood Group System The Rh system is the second most important blood group system clinically, particularly in obstetrics. 2.3.1 Genetics and Antigens Determined by RHD and RHCE genes on chromosome 1. The D antigen is the most immunogenic Rh antigen. Rh-positive: D antigen present on RBCs. Rh-negative: D antigen absent. Prevalence: Rh-positive: ~85% Caucasians, 92% African Americans, 99% East Asians. Rh-negative: ~15% Caucasians, 8% African Americans,

Mechanism of blood clotting
Anatomy

Mechanism of blood clotting

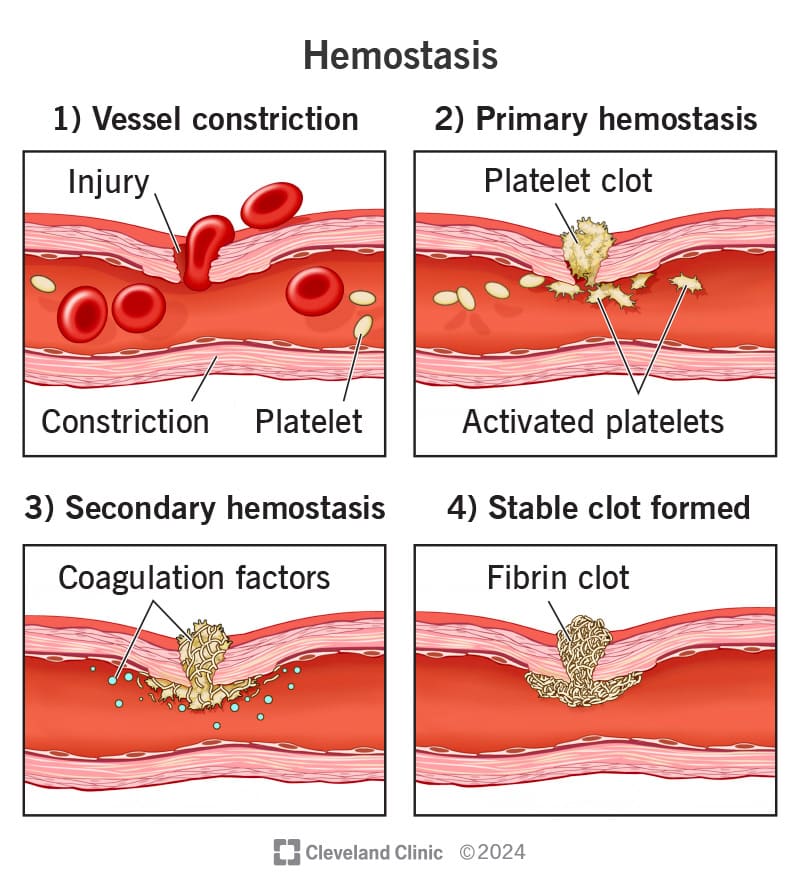
Mechanism of Blood Clotting Complete study notes covering the physiological phases of hemostasis, the biochemical coagulation cascade, modern cell-based models, fibrinolysis, and clinical laboratory diagnostics. 3.1 Definition and Overview Hemostasis is the physiological process that stops bleeding from a damaged blood vessel. It is a rapid, localized, and carefully regulated process that involves three overlapping phases: Vascular spasm (vasoconstriction) Platelet plug formation (primary hemostasis) Coagulation cascade (secondary hemostasis) Clot stabilization and fibrinolysis 3.2 Vascular Spasm This is the immediate reflex constriction of a damaged vessel to reduce blood loss. It is most effective in smaller vessels and is mediated by: Local myogenic spasm: Direct damage to vascular smooth muscle triggers contraction. Endothelin release: Released from damaged endothelial cells. Neural reflexes: Triggered by pain receptors. 3.3 Platelet Plug Formation (Primary Hemostasis) This process converts a temporary leak into a mechanical plug through three distinct steps: Step 1: Adhesion Vessel injury exposes subendothelial collagen. von Willebrand factor (vWF) binds to the exposed collagen. Platelet glycoprotein Ib (GPIb) receptors bind to vWF, causing platelets to adhere to the damaged wall. Step 2: Activation Adhesion triggers a platelet shape change (pseudopod formation). Release of granule contents: — Dense granules: Release ADP, serotonin, and Ca2+. — Alpha granules: Release fibrinogen, factor V, vWF, and PDGF. Synthesis and release of thromboxane A2 (TXA2), a potent vasoconstrictor and platelet activator. Platelet membrane expresses glycoprotein IIb/IIIa (GPIIb/IIIa) receptors. Step 3: Aggregation GPIIb/IIIa receptors bind fibrinogen, linking platelets together. This forms a loose platelet plug (white thrombus), which is later reinforced by fibrin. Clinical Correlation Antiplatelet Therapy Aspirin irreversibly inhibits COX-1, blocking the synthesis of Thromboxane A2 (TXA2). This effectively reduces platelet aggregation and forms the basis for secondary prevention of myocardial infarction and stroke. 3.4 Coagulation Cascade (Secondary Hemostasis) Secondary hemostasis involves a series of enzymatic reactions involving plasma proteins called clotting factors. Most factors are synthesized in the liver. Factors II, VII, IX, and X are Vitamin K-dependent. 3.4.1 Clotting Factors Factor Name Source Function I Fibrinogen Liver Converted to fibrin (clot structure) II Prothrombin Liver Converted to Thrombin (central enzyme) III Tissue Factor Tissue Initiates the Extrinsic Pathway IV Calcium (Ca2+) Diet Cofactor for multiple reactions V Proaccelerin Liver Cofactor for Factor X activation VII Proconvertin Liver Initiates extrinsic pathway VIII Antihemophilic A Liver Cofactor for Factor IX (Deficient in Hemophilia A) IX Antihemophilic B Liver Activates Factor X (Deficient in Hemophilia B) X Stuart-Prower Liver Forms Prothrombinase complex XI PTA Liver Activates Factor IX XII Hageman Factor Liver Initiates Intrinsic Pathway XIII Fibrin-stabilizing Liver Cross-links fibrin monomers *Note: Factor VI was originally assigned to activated factor V but is no longer used in modern nomenclature. 3.4.2 The Three Pathways A. Extrinsic Pathway (Tissue Factor Pathway) Trigger: Tissue injury exposing Tissue Factor (Factor III) to blood. Sequence: Factor III + Factor VII activates Factor X. Speed: Fast-acting; generates thrombin within seconds. Lab Test: Prothrombin Time (PT). B. Intrinsic Pathway (Contact Activation Pathway) Trigger: Blood exposure to negatively charged subendothelial surfaces. Sequence: Factor XII → XI → IX (with VIII as cofactor) → activates Factor X. Speed: Slower; requires several minutes. Lab Test: Activated Partial Thromboplastin Time (aPTT). C. Common Pathway Both pathways converge at Factor X activation. Factor Xa + Va (Prothrombinase complex) + Ca2+ + phospholipids converts Prothrombin (II) to Thrombin (IIa). Thrombin converts Fibrinogen (I) to Fibrin monomers. Fibrin monomers polymerize into a mesh. Factor XIIIa cross-links the fibrin to create a stable, permanent clot. 3.4.3 Cell-Based Model (Modern Understanding) Modern hematology emphasizes that coagulation occurs in three phases on cell surfaces: Initiation: Tissue factor-bearing cells activate small amounts of X and thrombin. Amplification: Thrombin activates platelets and cofactors (V, VIII, XI). Propagation: Large-scale thrombin generation (thrombin burst) on platelet surfaces produces a massive fibrin clot. 3.5 Clot Retraction and Repair Platelets contain actin and myosin filaments (contractile proteins). Clot contraction pulls wound edges together. This squeezes serum out of the clot (Serum = Plasma without clotting factors). Platelet-Derived Growth Factor (PDGF) stimulates fibroblast migration and tissue repair. 3.6 Fibrinolysis (Clot Removal) Fibrinolysis prevents excessive clot propagation and removes the clot once healing has occurred. Mechanism: Plasminogen (inactive) is incorporated into the clot during formation. Tissue plasminogen activator (t-PA) from endothelial cells converts plasminogen to Plasmin. Plasmin digests fibrin into fibrin degradation products (FDPs). D-dimer is a specific FDP from cross-linked fibrin. Diagnostic Value D-dimer Elevated D-dimer levels indicate active fibrinolysis and are used to screen for thrombotic conditions like DVT or Pulmonary Embolism (PE). However, it is non-specific and can also be elevated in infection, pregnancy, or malignancy. 3.7 Natural Anticoagulant Mechanisms Mechanism Action Deficiency State Antithrombin III Inhibits thrombin and factors Xa, IXa Thrombophilia Protein C Inactivates factors Va and VIIIa Thrombophilia; Warfarin skin necrosis Protein S Cofactor for Protein C Thrombophilia TFPI Inhibits Tissue Factor-VIIa complex — Fibrin Clot Adsorbs 85-90% of thrombin to prevent spread — 3.8 Clinical Laboratory Tests of Coagulation Test Measures Normal Range Prolonged In… PT Extrinsic + Common (VII, X, V, II, I) 11–13 sec Warfarin use, Vit K deficiency, Liver disease aPTT Intrinsic + Common (XII, XI, IX, VIII, X, V, II, I) 25–35 sec Heparin use, Hemophilia, vWD INR Standardized PT ratio 0.9–1.1 Warfarin monitoring TT Fibrinogen → Fibrin conversion 15–19 sec Hypofibrinogenemia, DIC D-dimer Fibrin degradation products <0.5 ug/mL DVT, PE, DIC, Post-surgery Key Comparison Hemophilia A vs. B Hemophilia A: Deficiency of Factor VIII. Hemophilia B: Deficiency of Factor IX. Both present with bleeding into joints (hemarthrosis), muscle hematomas, and a prolonged aPTT with a normal PT.

Muscle disorders (Myositis, Strain, Paralysis)
Anatomy

Muscle disorders (Myositis, Strain, Paralysis)

Muscle Disorders: Myositis, Strain, and Paralysis A comprehensive clinical resource for the Muscular System (Sub-topic 2.3), detailing the pathophysiology, classification, diagnosis, and management of inflammatory, mechanical, and neurological muscle conditions. 1. INTRODUCTION Muscle disorders represent a significant category of clinical conditions encountered in general medical practice. These disorders may result from inflammation, mechanical injury, or neurological dysfunction. This chapter examines three specific entities: myositis (inflammation of muscle), muscle strain (mechanical injury to fibers), and paralysis (loss of function due to neurological impairment). 2. MYOSITIS Myositis is defined as the inflammation of skeletal muscle. It may be acute or chronic, localized or generalized, occurring as an isolated condition or as part of a systemic disease. Involvement may include muscle fibers, connective tissue, or intramuscular blood vessels. 2.1 Classification and Types Infectious Myositis: Caused by bacterial, viral, fungal, or parasitic organisms. Bacterial myositis (pyomyositis): Common in tropical regions and immunocompromised states; Staphylococcus aureus is the most common pathogen. Viral myositis: Caused by influenza, coxsackievirus, EBV, or HIV. Parasitic myositis: Includes trichinellosis (Trichinella spiralis) and toxoplasmosis. Idiopathic Inflammatory Myopathies (IIM): Autoimmune disorders including: Dermatomyositis: Features proximal muscle weakness and characteristic skin rashes (heliotrope rash on eyelids, Gottron papules over knuckles). Associated with malignancy and interstitial lung disease. Polymyositis: Progressive, symmetric proximal weakness without skin involvement. Inclusion body myositis: Most common in older adults; causes asymmetric weakness of finger flexors and quadriceps. Often refractory to treatment. Drug-induced Myositis: Triggered by statins (cholesterol-lowering), colchicine, chloroquine, and zidovudine. Ranges from myalgia to severe rhabdomyolysis. 2.2 Pathophysiology The mechanism varies by etiology. In infectious forms, organisms invade tissue directly, triggering an acute response with neutrophils and macrophages releasing proteolytic enzymes. In autoimmune forms, autoreactive T cells target muscle antigens leading to fiber necrosis. In dermatomyositis, a complement-mediated microangiopathy causes ischemic damage to the fibers. 2.3 Clinical Features The hallmark is proximal muscle weakness (shoulders and hips). Patients report difficulty climbing stairs, rising from chairs, or lifting objects overhead. Muscle pain (myalgia): Severe in infectious; mild/absent in idiopathic. Muscle tenderness: Palpation reveals tenderness and potential swelling. Systemic: Fatigue, fever (infectious), and dysphagia (pharyngeal involvement). Dermatological: Heliotrope rash and shawl sign (dermatomyositis). 2.4 Diagnosis and Management Blood tests: Creatine Kinase (CK) is the most sensitive marker for damage. Autoantibodies (anti-Jo-1, anti-Mi-2) support IIM diagnosis. Imaging: MRI (T2-weighted/STIR) is the modality of choice for identifying inflammation. Muscle Biopsy: The gold standard; shows inflammatory infiltration and fiber necrosis. Management Principle Autoimmune Myositis: First-line treatment is high-dose corticosteroids (prednisone 1 mg/kg/day). Steroid-sparing agents (methotrexate, azathioprine) are added for resistant cases. Drug-induced: Immediate discontinuation of the offending agent. Severe cases require aggressive hydration to prevent acute kidney injury. 3. MUSCLE STRAIN A muscle strain (pulled muscle) is an injury to a muscle or its tendons caused by overstretching or excessive force. Strains involve muscles/tendons, whereas sprains involve ligaments. 3.1 Etiology and Vulnerability Occurs during sudden acceleration or deceleration. Common mechanisms include direct trauma, muscle fatigue, and inadequate warm-up. The hamstrings (biceps femoris) are most vulnerable as they cross two joints (hip and knee). 3.2 Classification by Severity Grade Severity Pathology Healing Time Grade I Mild Few fibers torn; minimal swelling; no strength loss. 1–2 weeks Grade II Moderate Moderate fibers torn; intact muscle; noticeable weakness/bruising. 3–6 weeks Grade III Severe Complete rupture of muscle or tendon; palpable defect; complete loss of function. 3–6 months 3.4 Management: The PRICE Protocol In the acute phase (first 48 hours): P — Protection: Use splints or crutches. R — Rest: Avoid activities that cause pain (relative rest). I — Ice: Apply cold packs for 15–20 mins every 2–3 hours. C — Compression: Elastic bandages to minimize swelling. E — Elevation: Raise limb above heart level to reduce edema. Surgical Note Surgical management is reserved for Grade III strains with complete rupture, particularly involving the Achilles tendon or pectoralis major in athletes. 4. PARALYSIS Paralysis is the complete or partial loss of muscle function resulting from damage anywhere along the motor pathway, from the motor cortex to the neuromuscular junction (NMJ). 4.1 Classification By Distribution: — Monoplegia: One limb. — Hemiplegia: One side of the body. — Paraplegia: Both lower limbs. — Quadriplegia: All four limbs. By Muscle Tone: — Flaccid: Loss of tone (hypotonia), absent reflexes, muscle atrophy. Caused by LMN lesions. — Spastic: Increased tone (hypertonia), hyperreflexia, clonus, Babinski sign. Caused by UMN lesions. 4.2 Causes and Clinical Features Upper Motor Neuron (UMN) Lesions: Originate in the cortex. Causes: Stroke, MS, Cerebral Palsy. Features: Spasticity, weakness in extensors (upper) and flexors (lower). Lower Motor Neuron (LMN) Lesions: Originate in the anterior horn. Causes: Polio, GBS, Nerve trauma. Features: Fasciculations and severe neurogenic atrophy. Clinical Differentiation Facial Paralysis In Bell’s palsy (LMN), the entire half of the face is affected (cannot wrinkle forehead). In a Stroke (UMN), the forehead is spared because the frontalis muscle receives bilateral cortical innervation. 4.6 Summary Comparison Table: UMN vs. LMN Feature Upper Motor Neuron (UMN) Lower Motor Neuron (LMN) Muscle Tone Increased (Spasticity) Decreased (Flaccidity) Reflexes Hyperreflexia Hyporeflexia or absent Babinski Sign Present (Upgoing toe) Absent Atrophy Mild (Disuse) Severe (Neurogenic) Fasciculations Absent Present Surgical Emergency Cauda Equina Syndrome Compression of nerve roots below L1–L2. Red flags: saddle anesthesia, bladder/bowel dysfunction. Decompression within 48 hours is required to improve outcomes. 5. KEY POINTS SUMMARY Myositis: CK is the most sensitive lab marker; MRI is the choice for imaging. Muscle Strain: Grade III is a complete rupture requiring potential surgery; hamstrings are most frequently injured. Paralysis: UMN lesions result in spasticity; LMN lesions result in flaccidity and fasciculations. Bell’s Palsy: An LMN facial nerve lesion affecting the entire ipsilateral half of the face.

Physiology of muscle contraction
Anatomy

Physiology of muscle contraction

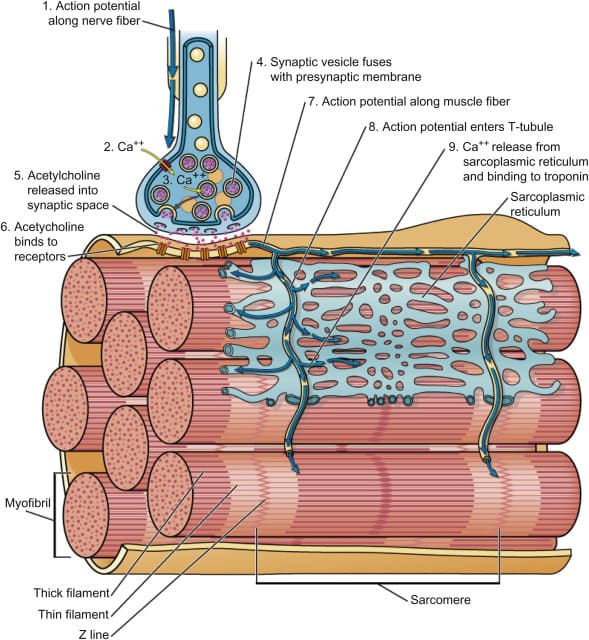
Physiology of Muscle Contraction Complete detailed notes on the mechanisms and regulation of skeletal muscle contraction, covering the neuromuscular junction, sarcomere architecture, sliding filament theory, and clinical correlations. 1. Introduction Muscle contraction is a complex physiological process that converts chemical energy into mechanical force. Understanding these mechanisms is essential for diagnosing neuromuscular disorders and managing patients with muscle-related conditions. This study covers the structural and functional integration of the nervous and muscular systems. 2. The Neuromuscular Junction (NMJ) The Neuromuscular Junction (NMJ) is a specialized synapse between a motor neuron and a skeletal muscle fiber. It is the critical site where neural signals initiate muscular action. 2.1 Structure of the NMJ Presynaptic Terminal: The axon terminal of the motor neuron containing numerous synaptic vesicles filled with acetylcholine (ACh). It features voltage-gated calcium channels in its membrane. Synaptic Cleft: A narrow extracellular space (~50 nm wide). It contains the enzyme acetylcholinesterase (AChE), which terminates the signal by hydrolyzing ACh. Postsynaptic Membrane (Motor End Plate): The specialized region of the sarcolemma containing nicotinic acetylcholine receptors (nAChR). These are concentrated in junctional folds that maximize surface area. Each nAChR consists of five subunits (two alpha, one beta, one gamma/delta, one epsilon). 2.2 Events at the NMJ (Step-by-Step) Step 1 — Arrival of action potential: The impulse reaches the presynaptic terminal, opening voltage-gated calcium (Ca2+) channels. Step 2 — Calcium influx and vesicle fusion: Ca2+ triggers the exocytosis of ACh into the synaptic cleft. Step 3 — ACh binding: ACh diffuses across the cleft and binds to the alpha subunits of nAChR on the motor end plate. Step 4 — Depolarization: Receptors open, allowing sodium (Na+) influx and potassium (K+) efflux. This produces an End-Plate Potential (EPP). Step 5 — Muscle fiber action potential: The EPP is typically suprathreshold, triggering a general action potential that spreads across the sarcolemma. Step 6 — ACh hydrolysis: AChE breaks down ACh into acetate and choline, preventing continuous stimulation. Key Points ACh is the primary neurotransmitter of the NMJ. The EPP is always suprathreshold under normal physiological conditions. AChE is vital for the precise control of muscle relaxation. 3. Sarcomere Structure The sarcomere is the basic functional unit of skeletal muscle contraction, defined as the region between two adjacent Z-discs. 3.1 Thin Filaments (Actin) Composed primarily of Actin. G-actin (globular) polymerizes into F-actin (filamentous). In the resting state, myosin-binding sites are blocked by tropomyosin. The Troponin complex regulates this: Troponin T: Binds to tropomyosin. Troponin I: Inhibits the actin-myosin interaction. Troponin C: Binds calcium ions. 3.2 Thick Filaments (Myosin) Composed of Myosin II. Each molecule consists of two heavy chains (forming the tail and heads) and four light chains. Each head contains an ATP-binding site and an actin-binding site. 3.3 Bands and Zones A band: The dark band representing the full length of thick filaments. I band: The light band containing only thin filaments; bisected by the Z-disc. H zone: The center of the A band containing only thick filaments (no overlap). M line: Protein line in the center of the H zone that anchors thick filaments. Z-disc: Anchors thin filaments; defines the sarcomere boundary. 4. The Sliding Filament Theory Proposed by Huxley and Hanson (1954), this theory states that muscle shortening occurs because thin filaments slide past thick filaments without the individual filaments changing length. 4.1 The Cross-Bridge Cycle Step 1 — Cross-bridge formation: Calcium binds to Troponin C, moving tropomyosin and exposing binding sites. The myosin head (bound to ADP + Pi) attaches to actin. Step 2 — Power stroke: Release of Pi triggers the head to pivot, pulling the thin filament ~10 nm toward the M line. ADP is released. Step 3 — Cross-bridge detachment: A new ATP binds to the myosin head, causing it to release from actin. Step 4 — Reactivation: Myosin hydrolyzes ATP into ADP + Pi, “re-cocking” the head into its high-energy state. Rigor Mortis ATP is required for detachment. In the absence of ATP (after death), cross-bridges remains permanently bound, resulting in the muscle stiffness known as rigor mortis. 5. Excitation-Contraction Coupling This is the process by which an electrical action potential triggers the mechanical release of calcium for contraction. 5.1 Steps of Coupling Action potential propagation: The signal travels down the T-tubules to reach the interior of the fiber. DHP Receptor activation: Voltage-gated Dihydropyridine (DHP) receptors in the T-tubule sense the change in voltage. Ryanodine Receptor (RyR) opening: DHP receptors are mechanically coupled to RyR channels on the Sarcoplasmic Reticulum (SR). Opening RyR allows Ca2+ to flood the cytosol. Calcium-Troponin binding: Ca2+ binds to Troponin C, initiating the cross-bridge cycle. SERCA Reuptake: Relaxation occurs when Ca2+ is actively pumped back into the SR by the Sarcoplasmic/Endoplasmic Reticulum Calcium ATPase (SERCA). 6. Energy Sources for Muscle Contraction Muscles require a continuous supply of ATP, but only store a few seconds’ worth. Rapid regeneration occurs via three systems: Energy System Substrate ATP Yield Duration Oxygen? Phosphocreatine Phosphocreatine 1 ATP per PCr 10–15 seconds No Anaerobic Glycolysis Glucose/Glycogen 2 ATP per glucose 1–2 minutes No Aerobic Respiration Glucose, Fatty Acids 30–32 ATP per glucose Hours Yes 7. Types of Muscle Contraction Isotonic Contraction: Muscle changes length while tension remains constant. Concentric: Muscle shortens (e.g., upward phase of a bicep curl). Eccentric: Muscle lengthens while generating tension (e.g., controlled lowering of a weight). Isometric Contraction: Muscle generates tension without changing length (e.g., holding a heavy object stationary). Isokinetic Contraction: Muscle contracts at a constant velocity against variable resistance (requires specialized equipment). 8. Clinical Relevance Pathology Myasthenia Gravis An autoimmune disorder where antibodies block or destroy nicotinic ACh receptors at the NMJ. Results in progressive muscle weakness that worsens with activity. Diagnosed via the edrophonium test. Pathology Malignant Hyperthermia A genetic disorder of Ryanodine Receptors (RyR) triggered by volatile anesthetics. Causes massive, uncontrolled calcium release from the SR, leading to sustained contraction, hyperthermia, and fatal hyperkalemia. Treated with dantrolene (RyR antagonist). Pathology Botulism Produced by Clostridium botulinum. The toxin cleaves SNARE proteins, preventing the release of ACh from presynaptic terminals. Results in flaccid

Foundational Concepts
Anatomy

Foundational Concepts

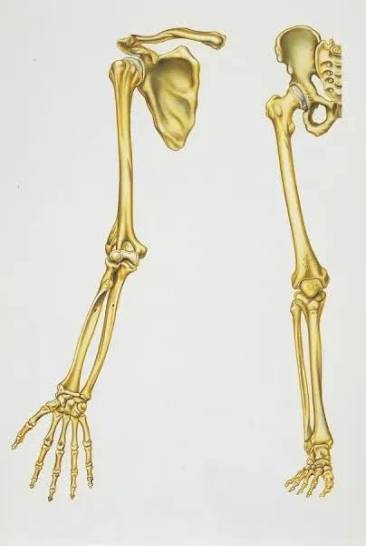
Foundational Concepts of Limb Anatomy Complete medical notes covering Bones, Joints, Muscles, Vessels, Nerves, and Surface Anatomy of the Upper and Lower Limbs. 1. INTRODUCTION TO LIMB ANATOMY The limbs are paired appendages that enable locomotion, manipulation of objects, and interaction with the environment. Each limb consists of a girdle (pectoral or pelvic), a proximal segment, an intermediate segment, and a distal segment containing multiple digits. The upper limb is specialized for prehension and fine motor control, while the lower limb is adapted for weight-bearing and locomotion. 1.1 Comparative Organization of Upper and Lower Limbs The upper and lower limbs share a common fundamental pattern of organization. This similarity reflects their common evolutionary origin. Feature Upper Limb Lower Limb Girdle Pectoral (shoulder) girdle: clavicle, scapula Pelvic girdle: hip bone (ilium, ischium, pubis) Proximal bone Humerus Femur Intermediate bones Radius and ulna Tibia and fibula Proximal carpal/tarsal bones Scaphoid, lunate, triquetrum, pisiform, trapezium, trapezoid, capitate, hamate Talus, calcaneus, navicular, cuboid, cuneiforms (3) Distal metacarpals/metatarsals 5 metacarpals 5 metatarsals Digits 5 digits (thumb has 2 phalanges; fingers have 3) 5 digits (hallux has 2 phalanges; toes have 3) Primary function Prehension, manipulation, fine motor control Weight-bearing, locomotion, stability Mobility vs stability High mobility, low stability High stability, lower mobility 2. BONES OF THE LIMBS 2.1 Upper Limb Bones Clavicle: An S-shaped long bone. It articulates medially with the manubrium (sternoclavicular joint) and laterally with the acromion (acromioclavicular joint). It is the only bony attachment of the upper limb to the axial skeleton. Fractures commonly occur at the junction of the middle and lateral thirds. Scapula: A flat, triangular bone on the posterior thoracic wall. It has three borders (superior, medial, lateral), three angles (superior, inferior, lateral), and two surfaces (costal and posterior). The glenoid cavity articulates with the head of the humerus. The spine of the scapula divides the posterior surface into supraspinous and infraspinous fossae. The acromion and coracoid process are important muscle attachment and articulation sites. Humerus: The longest bone of the upper limb. The head articulates with the glenoid cavity. The anatomical neck separates the head from the tubercles; the surgical neck is the constricted region below the tubercles and is a common fracture site. The greater tubercle receives insertions of supraspinatus, infraspinatus, and teres minor. The lesser tubercle receives the subscapularis. The deltoid tuberosity is the insertion of the deltoid. The medial and lateral epicondyles are palpable landmarks. The olecranon fossa posteriorly and coronoid fossa anteriorly receive the ulna during elbow movement. The trochlea articulates with the ulna; the capitulum articulates with the radius. Radius: The lateral bone of the forearm. Its head articulates with the capitulum of the humerus and the radial notch of the ulna. The radial tuberosity is the insertion of biceps brachii. The styloid process is palpable on the lateral aspect of the wrist. Ulna: The medial bone of the forearm. Its olecranon forms the point of the elbow. The trochlear notch articulates with the trochlea of the humerus. The coronoid process and radial notch are additional articular surfaces. Carpal Bones: Arranged in two rows. Proximal row (lateral to medial): scaphoid, lunate, triquetrum, pisiform. Distal row (lateral to medial): trapezium, trapezoid, capitate, hamate. The scaphoid is the most frequently fractured; the lunate is commonly dislocated. Mnemonic Some Lovers Try Positions That They Cannot Handle: Scaphoid, Lunate, Triquetrum, Pisiform, Trapezium, Trapezoid, Capitate, Hamate. 2.2 Lower Limb Bones Hip bone (os coxae): Formed by the fusion of three bones: ilium, ischium, and pubis. The acetabulum is the deep socket for the head of the femur. The obturator foramen is the large opening formed by the pubis and ischium. The iliac crest is palpable from ASIS to PSIS. The ischial tuberosity is the weight-bearing point in sitting. Femur: The longest and strongest bone in the body. The head articulates with the acetabulum. The fovea capitis is the pit for the ligament of the head of the femur. The neck connects the head to the shaft and is a common fracture site in elderly patients. The greater and lesser trochanters are muscle attachment sites. The linea aspera is the rough ridge on the posterior shaft. The medial and lateral condyles articulate with the tibia; the patellar surface articulates with the patella. Patella: The largest sesamoid bone, embedded in the quadriceps tendon. It protects the knee joint and improves the mechanical advantage of the quadriceps. Tibia: Large, medial weight-bearing bone. The tibial tuberosity is the insertion of the patellar ligament. The anterior border (shin) is subcutaneous. The medial malleolus forms the medial prominence of the ankle. Fibula: Slender, lateral bone. The lateral malleolus forms the lateral prominence of the ankle and extends more distally than the medial malleolus. Tarsal bones: include the talus, calcaneus (heel bone, largest), navicular, cuboid, and three cuneiforms. 3. JOINTS OF THE LIMBS Most limb joints are synovial, characterized by a joint cavity, articular cartilage, synovial membrane, and joint capsule. 3.1 Shoulder Joint (Glenohumeral) A ball-and-socket synovial joint; the most mobile joint in the body. Stability is provided by the rotator cuff muscles (SITS): supraspinatus, infraspinatus, teres minor, and subscapularis. Also supported by the glenoid labrum and coracohumeral ligament. 3.2 Elbow Joint A hinge (ginglymus) joint involving three bones and three articulations: humeroulnar, humeroradial, and proximal radioulnar. The annular ligament encircles the radial head. 3.4 Hip Joint A ball-and-socket joint. The iliofemoral ligament (Y ligament of Bigelow) is the strongest in the body and prevents hyperextension. The pubofemoral ligament limits abduction, and the ischiofemoral ligament limits internal rotation. 3.5 Knee Joint The largest and most complex joint. It consists of three articulations: lateral tibiofemoral, medial tibiofemoral, and patellofemoral. Stabilized by: MCL and LCL: Medial and lateral collateral ligaments. ACL and PCL: Anterior and posterior cruciate ligaments. Menisci: Medial and lateral fibrocartilaginous discs. 3.6 Ankle Joint (Talocrural) A hinge joint between the distal tibia, fibula, and talus. The deltoid ligament (medial) is very strong. Lateral ligaments (anterior talofibular, posterior talofibular, calcaneofibular) are weaker and more commonly sprained. 4. MUSCLE COMPARTMENTS OF THE LIMBS Organized into

Congenital Malformations
Anatomy

Congenital Malformations

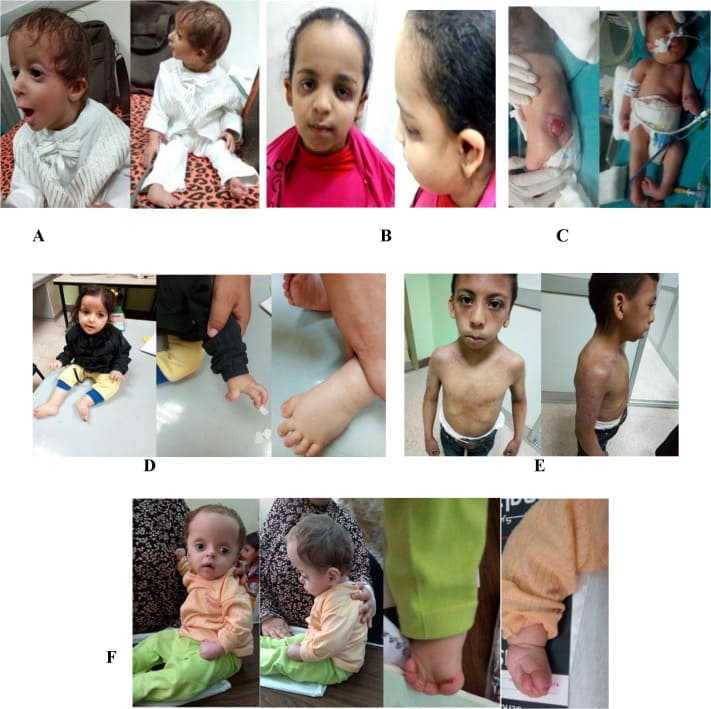
Congenital Malformations A Comprehensive Medical Reference covering Congenital Malformations, Causes, Critical Periods, and Clinical Management. 1. INTRODUCTION A congenital malformation is defined as a structural abnormality present at birth that results from a disturbance in normal embryonic or fetal development. These abnormalities may affect any organ system and range from minor cosmetic defects to severe, life-threatening conditions. Congenital malformations are a leading cause of infant mortality and childhood morbidity worldwide, including in Uganda. The study of congenital malformations (teratology) is essential for clinical medicine practitioners. Understanding the timing, mechanisms, and causes of developmental disruptions enables prevention, early detection, and appropriate management. Many congenital malformations are preventable through prenatal care, nutritional supplementation, and avoidance of teratogenic exposures. 2. EPIDEMIOLOGY Globally, congenital anomalies affect approximately 3-6% of all live births. The World Health Organization estimates that approximately 240,000 newborns die worldwide within 28 days of birth each year due to congenital anomalies. In low- and middle-income countries, including Uganda, the burden is compounded by limited access to prenatal screening, surgical services, and specialized neonatal care. The most common congenital malformations include congenital heart defects, neural tube defects, cleft lip and palate, clubfoot, and Down syndrome. The prevalence varies by geographic region, genetic background, maternal nutrition, and environmental exposures. Ugandan Context In Uganda, neural tube defects and cleft lip/palate are among the most frequently encountered major congenital anomalies in clinical practice. 3. CAUSES OF CONGENITAL MALFORMATIONS The causes of congenital malformations are traditionally categorized into genetic, environmental, and multifactorial etiologies. However, in many cases, the exact cause remains unknown. 3.1 Genetic Causes Chromosomal abnormalities: Involve alterations in chromosome number or structure. Aneuploidy (abnormal chromosome number) includes trisomies such as Down syndrome (trisomy 21), Edwards syndrome (trisomy 18), and Patau syndrome (trisomy 13). Monosomy X (Turner syndrome) and Klinefelter syndrome (XXY) are sex chromosome aneuploidies. Structural abnormalities include deletions, duplications, inversions, and translocations. Single gene mutations: Follow Mendelian inheritance patterns. Autosomal dominant disorders include achondroplasia and Marfan syndrome. Autosomal recessive disorders include cystic fibrosis and sickle cell disease. X-linked disorders include hemophilia and Duchenne muscular dystrophy. Polygenic inheritance: Involves multiple genes contributing to a phenotype. Many common malformations, including cleft lip with or without cleft palate and congenital heart defects, demonstrate polygenic inheritance with environmental interaction. 3.2 Environmental Causes (Teratogens) Teratogens are environmental agents that cause structural or functional abnormalities in the developing embryo or fetus. The effect of a teratogen depends on the timing of exposure, dose, duration, and genetic susceptibility of the embryo. 3.2.1 Infectious Teratogens Rubella virus: Infection during the first trimester causes congenital rubella syndrome, characterized by cataracts, congenital heart defects (patent ductus arteriosus, pulmonary stenosis), sensorineural deafness, and microcephaly. Vaccination has dramatically reduced incidence in countries with immunization programs. Cytomegalovirus (CMV): The most common congenital viral infection. It causes microcephaly, intracranial calcifications, chorioretinitis, sensorineural hearing loss, and hepatosplenomegaly. Toxoplasma gondii: Infection causes chorioretinitis, intracranial calcifications, hydrocephalus, and seizures. Transmission occurs through ingestion of undercooked meat or contact with cat feces. Zika virus: Infection during pregnancy causes microcephaly and other severe brain abnormalities. The virus is transmitted by Aedes mosquitoes, which are endemic in parts of Uganda. Syphilis (Treponema pallidum): Causes congenital syphilis with manifestations including hepatosplenomegaly, rash, anemia, jaundice, and bone abnormalities. Late manifestations include Hutchinson teeth, saddle nose, and interstitial keratitis. 3.2.2 Chemical and Drug Teratogens Alcohol: A potent teratogen. Fetal alcohol spectrum disorders (FASD) include fetal alcohol syndrome (FAS) characterized by growth retardation, facial dysmorphism (short palpebral fissures, smooth philtrum, thin upper lip), and central nervous system abnormalities. No safe level of alcohol consumption during pregnancy has been established. Antiepileptic drugs: Such as valproic acid and carbamazepine increase the risk of neural tube defects, craniofacial anomalies, and cardiac defects. Folic acid supplementation reduces the risk in women taking antiepileptic medications. Thalidomide: A sedative used in the 1950s-60s, caused severe limb reduction defects (phocomelia). It remains a powerful example of drug teratogenicity and has been repurposed for treatment of leprosy and multiple myeloma with strict pregnancy prevention programs. Retinoids: (isotretinoin, etretinate) cause craniofacial, cardiac, thymic, and central nervous system defects. Isotretinoin is absolutely contraindicated in pregnancy. Warfarin: Causes fetal warfarin syndrome (nasal hypoplasia, stippled epiphyses, central nervous system abnormalities) when used in the first trimester. 3.2.3 Physical Teratogens Ionizing radiation: Exposure during pregnancy, particularly in the first trimester, increases the risk of microcephaly, growth retardation, and intellectual disability. The risk is dose-dependent, with diagnostic radiation typically below the teratogenic threshold. Hyperthermia: Maternal fever >38.9°C or hot tub use in the first trimester is associated with neural tube defects, microcephaly, and facial clefts. 3.2.4 Maternal Disease States Maternal diabetes mellitus: (Both pregestational and gestational) increases the risk of congenital heart defects, neural tube defects, caudal regression syndrome, and macrosomia. Strict glycemic control before conception and during early pregnancy significantly reduces risk. Maternal phenylketonuria (PKU): Causes microcephaly, growth retardation, congenital heart defects, and intellectual disability when maternal phenylalanine levels are elevated during pregnancy. Maternal hypothyroidism: Is associated with impaired neurodevelopment and may increase the risk of congenital anomalies. 4. CRITICAL PERIODS OF DEVELOPMENT The concept of critical periods is fundamental to understanding teratogenesis. A critical period is the specific time during development when an organ system is most susceptible to teratogenic insult. Exposure to a teratogen during an organ’s critical period is most likely to produce a malformation of that organ. The embryonic period (weeks 3-8 post-fertilization) is the most vulnerable period for teratogenic effects because all major organ systems begin development during this time. Pre-implantation period (weeks 1-2): Is characterized by the ‘all-or-none’ principle: teratogenic exposure typically causes either embryonic death or no effect, as the cells are still pluripotent. Fetal period (week 9 to birth): Is less susceptible to major structural malformations but remains vulnerable to functional abnormalities and growth disturbances. 4.1 Critical Periods by Organ System Organ System Critical Period Common Teratogenic Effects Central nervous system Weeks 3-5 (neurulation) Neural tube defects, microcephaly Heart Weeks 4-9 Septal defects, tetralogy of Fallot Upper limbs Weeks 4-7 Limb reduction defects, polydactyly Lower limbs Weeks 4-8 Clubfoot, limb reduction

Glands
Anatomy

Glands

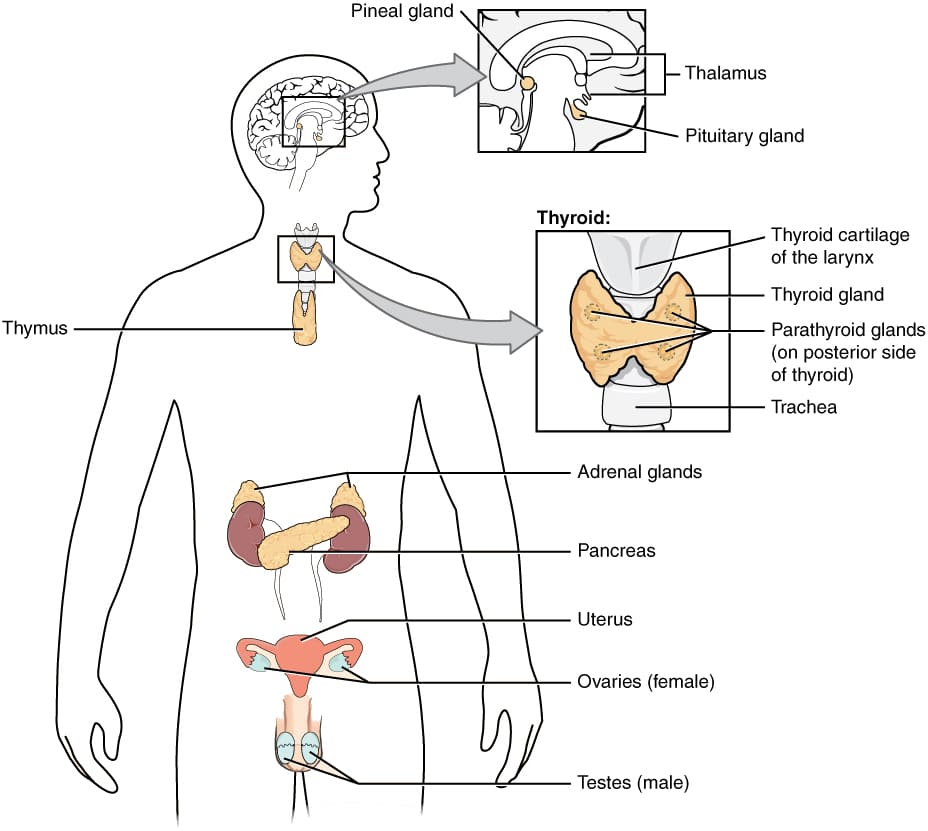
Histology of Glands Microscopic anatomy of exocrine, endocrine, and mixed glands. A detailed study of functional organization, modes of secretion, and cellular architecture essential for medical clinical practice. 1. Introduction to Glands A gland is an organized group of cells specialized to synthesize and secrete substances for use elsewhere in the body or for elimination. Glands are derived from epithelial tissue. During embryonic development, epithelial cells proliferate and invaginate into the underlying connective tissue, differentiating into secretory units and, in some cases, duct systems. The secretory products of glands include enzymes, hormones, mucus, sweat, and sebum, all of which are essential for maintaining homeostasis, digestion, and protection. 2. Classification of Glands Glands are primarily classified based on the presence or absence of a duct system and their mode of secretion. 2.1 Classification by Presence of Ducts Exocrine glands: Possess ducts that transport secretions directly onto an epithelial surface. Examples include salivary glands and sweat glands. Endocrine glands: Ductless glands that release hormones directly into the bloodstream or interstitial fluid. They are characterized by rich capillary networks. Mixed glands: Contain both exocrine and endocrine components. The pancreas is the quintessential example. 2.2 Comparison of Exocrine and Endocrine Glands Feature Exocrine Glands Endocrine Glands Ducts Present Absent Secretion route Onto epithelial surfaces/into ducts Directly into blood or lymph Secretory products Enzymes, mucus, sweat, oil, wax Hormones Distance of action Local (near site of secretion) Distant (target organs via blood) Blood supply Moderate Extremely rich capillary network Cell arrangement Acini, tubules, or alveoli Cords, clusters, or follicles 3. Exocrine Glands Exocrine glands constitute the majority of glands in the body. They consist of a secretory portion (where the product is made) and a duct system (which delivers and may modify the product). 3.1 Structural Classification 3.1.1 Based on Duct System Simple glands: Possess an unbranched duct. — Simple tubular: Intestinal glands. — Simple coiled tubular: Merocrine sweat glands. — Simple branched tubular: Gastric glands. — Simple branched alveolar: Sebaceous glands. Compound glands: Possess a branched duct system. — Compound tubular: Mucous glands of the mouth. — Compound alveolar (acinar): Mammary glands. — Compound tubuloalveolar: Salivary glands and pancreas. 3.2 Functional Classification (Modes of Secretion) Glands are classified by the mechanism used to release their products: Merocrine (Eccrine) Secretion: The product is released via exocytosis. The cell remains completely intact. This is the most common mode (e.g., Salivary glands, Pancreas). Apocrine Secretion: The apical portion of the cytoplasm is pinched off and released with the product. The cell repairs itself afterward (e.g., Apocrine sweat glands). Holocrine Secretion: The entire cell disintegrates to become the secretion. Cells are replaced by mitotic division of the basal layer (e.g., Sebaceous glands). Mode Mechanism Cell Fate Examples Merocrine Exocytosis of vesicles Cell remains intact Salivary, pancreatic acini Apocrine Apical cytoplasm pinched off Cell repairs/continues Mammary gland, axillary sweat Holocrine Entire cell disintegrates Cell dies and is shed Sebaceous glands 3.4 Histological Types of Secretory Cells Serous Cells: Produce watery, protein-rich secretions (enzymes). Pyramidal shape with round basal nuclei. Cytoplasm is basophilic (RER) at the base and eosinophilic (zymogen granules) at the apex. Mucous Cells: Produce viscous mucinogen. Columnar shape with flattened nuclei pressed against the basal membrane. Cytoplasm appears pale/vacuolated in H&E. Mixed (Seromucous) Cells: Contain both types. Often show serous demilunes (crescent caps of serous cells over mucous acini). Example: Submandibular gland. 4. Endocrine Glands Ductless glands characterized by a lack of a surface connection and a very high density of fenestrated capillaries. Secretions (hormones) diffuse into the blood for systemic distribution. 4.1 Major Endocrine Histology Thyroid Gland: Unique follicular arrangement. Spherical follicles filled with colloid (thyroglobulin). Follicular cells produce T3/T4; Parafollicular (C cells) produce Calcitonin. Adrenal Gland: — Cortex (3 Zones): Glomerulosa (Aldosterone), Fasciculata (Cortisol), Reticularis (Androgens). — Medulla: Contains Chromaffin cells secreting Epinephrine and Norepinephrine. Pituitary (Hypophysis): Anterior (Adenohypophysis) with 5 cell types; Posterior (Neurohypophysis) containing axons and pituicytes. Pancreatic Islets (Langerhans): Scattered clusters. Beta cells (Insulin), Alpha cells (Glucagon), Delta cells (Somatostatin). 5. Mixed Glands (Quintessential Example: Pancreas) The pancreas is approximately 99% exocrine (serous acini producing digestive enzymes) and 1% endocrine (islets of Langerhans). 6. Clinical Relevance Exocrine Disorder Cystic Fibrosis (CF) An autosomal recessive disorder caused by mutations in the CFTR gene. It results in defective chloride transport, leading to thick, viscous secretions that obstruct ducts in the pancreas, sweat glands, and lungs, causing pancreatic insufficiency and malabsorption. Endocrine/Nutritional Note Iodine Deficiency & Goitre Enlargement of the thyroid (Goitre) is frequently due to Iodine deficiency, which remains a significant public health concern in several regions of Uganda. Without iodine, follicular cells cannot synthesize T3/T4, leading to compensatory hypertrophy. Other Pathologies Sialadenitis: Inflammation of salivary glands (often parotid) due to mumps or sialoliths (stones). Addison Disease: Primary adrenal insufficiency due to destruction of the cortex (low cortisol/aldosterone). Pituitary Adenomas: Benign tumors that can cause hormone hypersecretion or bitemporal hemianopia by compressing the optic chiasm. 7. Summary Table: Major Glands of the Body Gland Type Mode/Mechanism Clinical Significance Parotid Exocrine Merocrine Mumps, Sjögren syndrome Thyroid Endocrine Follicular/Blood Goitre, Hypothyroidism Adrenal Cortex Endocrine Cord/Blood Addison, Cushing syndrome Adrenal Medulla Endocrine Cluster/Blood Pheochromocytoma Sebaceous Exocrine Holocrine Acne, cysts Mammary Exocrine Apocrine/Merocrine Mastitis, cancer 8. Key Points Summary Glands are organized epithelial cells classified as exocrine (ducts) or endocrine (ductless). The three release modes are merocrine (most common), apocrine (apical loss), and holocrine (cell death). The pancreas is a vital mixed gland; its endocrine dysfunction leads to Diabetes Mellitus. Adrenal cortex zones are ordered: Glomerulosa, Fasciculata, Reticularis (Salt, Sugar, Sex).

Groups of muscles, origin, insertion, and nerve supply
Anatomy

Groups of muscles, origin, insertion, and nerve supply

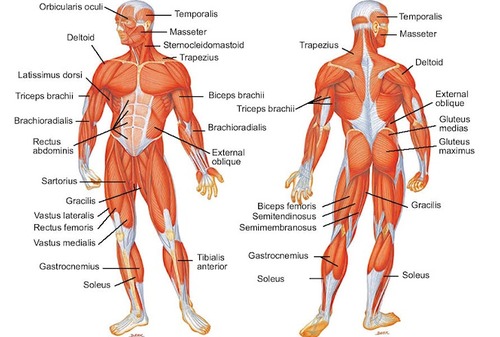
Groups of Muscles Comprehensive anatomical study of the major muscle groups of the human body, detailing their origin, insertion, nerve supply, and action. This guide is organized by anatomical region to facilitate clinical reasoning and surgical planning. 1. Introduction The human body contains over 600 skeletal muscles. These are organized into functional groups based on their anatomical location and the movements they produce. Muscles are named according to specific criteria: Size: e.g., gluteus maximus. Shape: e.g., deltoid. Location: e.g., tibialis anterior. Number of origins: e.g., biceps (two heads), triceps (three heads). Direction of fibers: e.g., rectus abdominis (straight). Action: e.g., flexor digitorum. 2. Muscles of the Head and Neck 2.1 Muscles of Facial Expression These muscles are unique because they insert into the skin rather than onto bone. They are all innervated by the Facial nerve (Cranial Nerve VII). Muscle Origin Insertion Action Frontalis Epicranial aponeurosis Skin of eyebrows and forehead Raises eyebrows, wrinkles forehead Orbicularis oculi Medial orbital margin, lacrimal sac Skin around orbit Closes eyelids Orbicularis oris Maxilla, mandible, surrounding muscles Lips Closes and protrudes lips Buccinator Maxilla, mandible, pterygomandibular raphe Orbicularis oris Compresses cheek (blowing, sucking) Platysma Fascia of deltoid and pectoralis major Mandible, skin of lower face Depresses mandible, tenses neck skin Clinical Correlation Bell’s Palsy Facial nerve palsy results in the paralysis of the muscles of facial expression on the affected side. Patients typically present with an inability to close the eye, a drooping corner of the mouth, and an inability to wrinkle the forehead. 2.2 Muscles of Mastication These muscles move the mandible and are all innervated by the Mandibular division of the Trigeminal nerve (CN V3). Muscle Origin Insertion Action Masseter Zygomatic arch Lateral surface of mandibular ramus and angle Elevates mandible (closes jaw) Temporalis Temporal fossa Coronoid process of mandible Elevates and retracts mandible Medial pterygoid Medial surface of lateral pterygoid plate Medial surface of mandibular ramus and angle Elevates and protrudes mandible Lateral pterygoid Lateral surface of lateral pterygoid plate, greater wing of sphenoid Neck of mandibular condyle, articular disc of TMJ Protrudes and depresses mandible (opens mouth) 3. Muscles of the Trunk 3.1 Anterior Abdominal Wall Muscles This group consists of three flat muscles and one vertical strap-like muscle. They function to protect viscera and increase intra-abdominal pressure. All are innervated by the Thoracoabdominal nerves (T7-T12); the internal oblique and transversus also receive supply from L1. Muscle Origin Insertion Action Rectus abdominis Pubic symphysis, pubic crest Xiphoid process, costal cartilages 5-7 Flexes trunk, compresses abdomen External oblique External surfaces of ribs 5-12 Iliac crest, pubic tubercle, linea alba Compresses abdomen, flexes and rotates trunk Internal oblique Iliac crest, inguinal ligament, thoracolumbar fascia Ribs 10-12, linea alba, pubis Compresses abdomen, flexes and rotates trunk Transversus abdominis Iliac crest, inguinal ligament, ribs 7-12 Linea alba, pubic crest Compresses abdomen (“corset” muscle) 3.2 Intercostal Muscles Essential for respiration, located in the intercostal spaces and innervated by the Intercostal nerves. External intercostal: Elevates ribs (Inspiration). Internal intercostal: Depresses ribs (Expiration). Innermost intercostal: Assists in expiration. 4. Muscles of the Upper Limb 4.1 Shoulder (Glenohumeral Joint) Muscles These muscles provide stability to the most mobile joint in the body. Muscle Origin Insertion Nerve Supply Action Deltoid Clavicle, acromion, spine of scapula Deltoid tuberosity of humerus Axillary n. (C5-C6) Abducts, flexes, and extends arm Supraspinatus Supraspinous fossa Greater tubercle of humerus Suprascapular n. (C5-C6) Initiates abduction (first 15°) Infraspinatus Infraspinous fossa Greater tubercle of humerus Suprascapular n. (C5-C6) Laterally rotates arm Teres minor Lateral border of scapula Greater tubercle of humerus Axillary n. (C5-C6) Laterally rotates arm Subscapularis Subscapular fossa Lesser tubercle of humerus Subscapular nn. (C5-C7) Medially rotates arm 4.2 Anterior Arm Muscles These muscles act primarily as flexors and are all supplied by the Musculocutaneous nerve. Biceps brachii: Flexes elbow, supinates forearm, weakly flexes shoulder. Brachialis: The primary flexor of the elbow. Coracobrachialis: Flexes and adducts the arm. 5. Muscles of the Lower Limb 5.1 Anterior Thigh Muscles (Quadriceps Femoris) Four muscles sharing a common insertion on the tibial tuberosity via the patellar ligament. All are supplied by the Femoral nerve (L2-L4). Rectus femoris: Extends knee and flexes hip. Vastus lateralis: Extends knee. Vastus medialis: Extends knee, stabilizes patella. Vastus intermedius: Extends knee. 5.2 Posterior Thigh Muscles (Hamstrings) Responsible for hip extension and knee flexion, innervated by the Sciatic nerve. Muscle Origin Insertion Action Biceps femoris Ischial tuberosity (long), Linea aspera (short) Head of fibula, lateral tibial condyle Extends hip, flexes knee, laterally rotates leg Semitendinosus Ischial tuberosity Proximal medial tibia (Pes anserinus) Extends hip, flexes knee, medially rotates leg Semimembranosus Ischial tuberosity Posterior medial condyle of tibia Extends hip, flexes knee, medially rotates leg 6. Clinical Relevance Rotator Cuff Tears The SITS muscles (Supraspinatus, Infraspinatus, Teres minor, Subscapularis) are common sites of injury. Supraspinatus tears are the most frequent, often occurring due to impingement under the acromion. Peripheral Nerve Palsies Radial Nerve Injury: Results in wrist drop due to paralysis of extensors. Femoral Nerve Palsy: Results in an inability to extend the knee and a loss of the patellar reflex. Sciatic Nerve Injury: Can result in foot drop if the common fibular division is affected. Facial Nerve Palsy vs. UMN Lesion Injury to CN VII paralyzes all facial muscles on the affected side (Bell’s Palsy). This must be distinguished from a stroke (Upper Motor Neuron lesion), which spares the forehead because the forehead receives bilateral cortical innervation. Summary Key Points Facial expression muscles are unique for inserting into skin (CN VII). Mastication muscles move the mandible (CN V3). The Rotator cuff provides essential stability to the glenohumeral joint. The Quadriceps extend the knee; Hamstrings flex the knee and extend the hip. Understanding nerve supply is required to predict motor deficits after trauma.

Functions and Types of muscles (Skeletal, Smooth, Cardiac)
Anatomy

Functions and Types of muscles (Skeletal, Smooth, Cardiac)

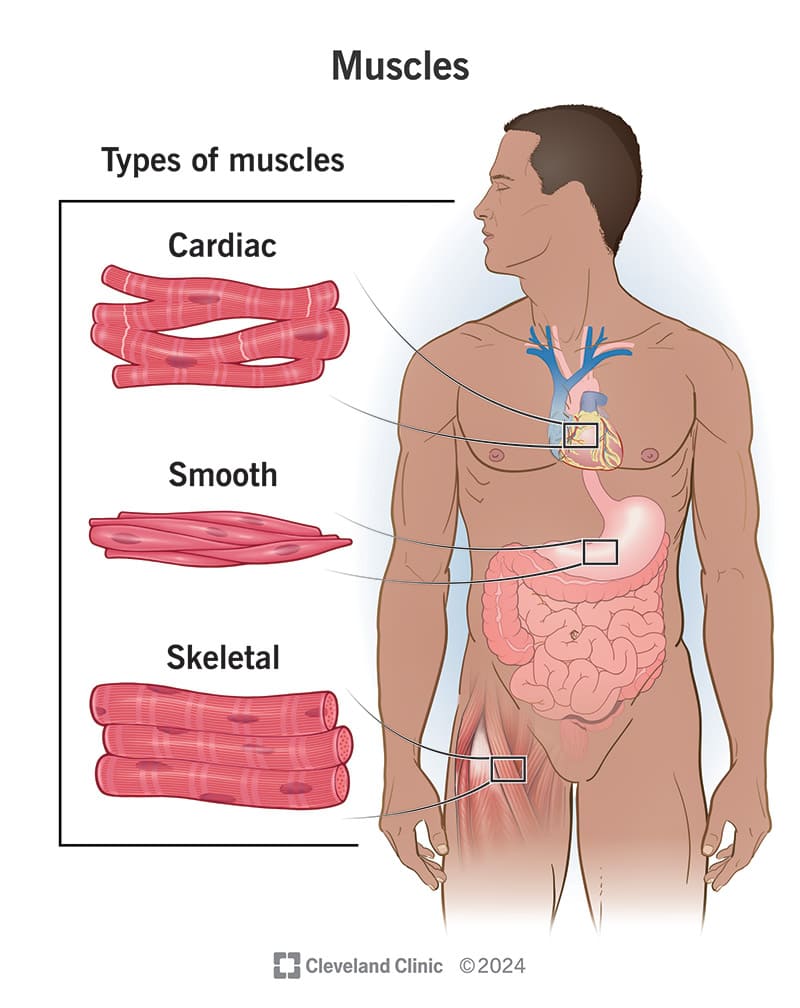
Functions and Types of Muscles A comprehensive anatomical and physiological study of skeletal, smooth, and cardiac muscle tissue, detailing their structural characteristics, functional roles, and clinical significance in medical practice. 1. Introduction Muscle tissue is a specialized tissue designed for contraction and is responsible for nearly all movement in the human body. Beyond locomotion, it performs vital roles in stability, heat generation, and the internal transport of substances. There are three distinct histological types: Skeletal, Smooth, and Cardiac. 2. Functions of Muscle Tissue Movement: Skeletal muscles produce voluntary movement by pulling on bones at joints (locomotion, facial expression). Smooth muscle handles involuntary movements like peristalsis and vascular constriction. Cardiac muscle provides rhythmic contractions to pump blood. Maintenance of Posture: Continuous contraction of skeletal muscles (specifically in the back, neck, and legs) maintains body position against gravity. These muscles are rich in Type I (slow-twitch) fibers. Joint Stabilization: Muscles provide dynamic stability by compressing joints during contraction. The rotator cuff muscles are a prime example of stabilizers for the glenohumeral joint. Heat Production: Muscle contraction is an exothermic process. Skeletal muscle accounts for approximately 85% of heat production during physical activity. Shivering is a mechanism of rapid, involuntary contraction to prevent hypothermia. Protection and Support: Abdominal muscles protect viscera, and pelvic floor muscles support pelvic organs. Key Point Muscle tissue is not just for movement; it is a metabolic engine that generates heat and a structural component that stabilizes the skeletal framework and protects internal organs. 3. Skeletal Muscle Skeletal muscle constitutes approximately 40% of total body weight. It is characterized as striated voluntary muscle. 3.1 Structure and Connective Tissue Skeletal muscle fibers are long, cylindrical, multinucleated cells with nuclei located peripherally. They range from 10 to 100 micrometers in diameter. Striations: Alternating light and dark bands caused by the arrangement of actin (thin) and myosin (thick) filaments within sarcomeres. Epimysium: Surrounds the entire muscle. Perimysium: Surrounds bundles of fibers called fascicles. Endomysium: Surrounds individual muscle fibers. 3.2 Fiber Types Feature Type I (Slow-twitch) Type II (Fast-twitch) Metabolism Oxidative (Aerobic) Glycolytic (Anaerobic) Fatigue Resistance High Low Color Red (High myoglobin) White/Pale (Low myoglobin) Specialization Endurance, posture Explosive, short-duration power 4. Smooth Muscle Smooth muscle is found in the walls of hollow organs and blood vessels. It is non-striated and involuntary. 4.1 Structure and Control Cells are spindle-shaped (fusiform) with a single central nucleus. They lack sarcomeres; instead, actin and myosin are anchored to dense bodies scattered throughout the cytoplasm and cell membrane. 4.2 Types of Smooth Muscle Single-unit (Visceral): Cells are connected by gap junctions and contract as a coordinated unit. Found in the stomach, intestines, and uterus. Multi-unit: Cells are not electrically connected and contract independently. Found in the iris of the eye, ciliary body, and arrector pili muscles. 5. Cardiac Muscle Forms the myocardium. It combines features of both skeletal (striated) and smooth (involuntary) muscle. 5.1 Intercalated Discs Cardiac muscle cells (cardiomyocytes) are branched and connected by intercalated discs, which contain: Desmosomes: Mechanical attachments. Gap Junctions: Allow rapid electrical coupling for synchronized contraction of the myocardium. 5.2 Unique Properties Automaticity: The ability to generate spontaneous action potentials (SA and AV nodes). Rhythmicity: Regular, repeating patterns of contraction. Refractory Period: A long refractory period prevents tetanic contraction, ensuring the heart has time to fill between beats. 6. Comparison of Muscle Types Feature Skeletal Muscle Cardiac Muscle Smooth Muscle Striations Present Present Absent Nuclei Multiple, peripheral Single/Double, central Single, central Control Voluntary (Somatic) Involuntary (Autonomic) Involuntary (Autonomic) Regeneration Limited (Satellite cells) None (Scar tissue forms) Capable 7. Clinical Relevance Pathology Muscular Dystrophies Inherited disorders like Duchenne muscular dystrophy (dystrophin gene mutation) lead to progressive skeletal muscle degeneration and severe weakness beginning in childhood. Pathology Hypertension Increased smooth muscle tone (vasoconstriction) in arteriole walls increases peripheral resistance. Medications like calcium channel blockers work by reducing this contraction. Pathology Myocardial Infarction (MI) Ischemic death of cardiomyocytes results in irreversible damage. Because cardiac muscle cannot regenerate, the area is replaced by non-contractile fibrous scar tissue, potentially leading to heart failure. Pathology Asthma Smooth muscle hyperreactivity in the bronchi leads to bronchospasm. Beta-2 agonists (bronchodilators) are used to relax this smooth muscle and open the airways. Clinical Key Point Skeletal muscle has some regenerative capacity via satellite cells, but cardiac muscle lacks this ability, making heart injuries permanent. Smooth muscle is the only type capable of significant hyperplasia and regeneration.

Scroll to Top