Doctors Revision

Author name: doctorsrevision@gmail.com

Organs of the lower respiratory system
Anatomy

Organs of the lower respiratory system

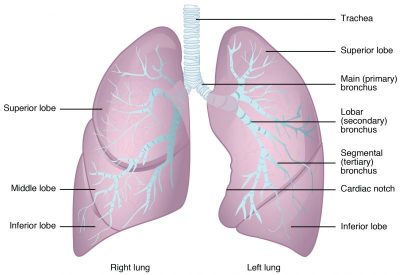
Organs of the Lower Respiratory System Comprehensive anatomical study covering the structural organization, internal architecture, neurovascular supply, and clinical correlations of the trachea, bronchial tree, and lungs. 1. Introduction The lower respiratory tract comprises the trachea, bronchi, bronchioles, and lungs. These structures function primarily to conduct air to the alveoli, where gas exchange occurs. The lower respiratory tract is lined by respiratory epithelium and supported by cartilaginous, muscular, and elastic tissues that maintain airway patency while providing the necessary flexibility for respiration and body movement. 2. The Trachea The trachea (windpipe) is a fibrocartilaginous tube measuring approximately 10–11 cm in length and 2 cm in diameter. it extends from the inferior border of the cricoid cartilage (C6) to the carina at the level of the sternal angle (T4–T5). 2.1 Structure Cartilaginous Support: Composed of 16–20 C-shaped hyaline cartilage rings that prevent airway collapse during inspiration. Trachealis Muscle: The posterior wall is membranous and contains the trachealis muscle (smooth muscle). This arrangement allows the esophagus to expand during swallowing. Histology: Lined by ciliated pseudostratified columnar epithelium with goblet cells. Submucosal glands secrete mucus that traps inhaled particles. Mucociliary Escalator: Ciliary action moves trapped particles upward toward the pharynx for swallowing or expectoration. 2.2 Anatomical Relations Relation Structures Anterior Isthmus of thyroid gland, inferior thyroid veins, sternohyoid and sternothyroid muscles, manubrium sterni. Posterior Esophagus and recurrent laryngeal nerves. Lateral Lobes of the thyroid gland, carotid sheaths. 2.3 Blood Supply and Innervation Arterial Supply: Inferior thyroid arteries. Venous Drainage: Brachiocephalic veins via inferior thyroid veins. Lymphatic Drainage: Pretracheal and paratracheal nodes. Innervation: — Parasympathetic: Vagus nerve (causes bronchoconstriction and increased mucus secretion). — Sympathetic: Sympathetic trunks (causes bronchodilation and reduced secretion). 3. The Bronchial Tree The bronchial tree is the branching system of airways that distributes air from the trachea to the alveoli. 3.1 Main (Primary) Bronchi The trachea bifurcates at the carina into right and left main bronchi. Both are supported by C-shaped cartilage rings and lined by respiratory epithelium. Right main bronchus: Wider, shorter (~2.5 cm), and more vertical than the left. Foreign bodies more commonly enter the right bronchus due to this verticality. Left main bronchus: Longer (~5 cm), narrower, and more horizontal. It passes beneath the aortic arch and anterior to the esophagus. 3.2 Lobar (Secondary) Bronchi Right lung: Three lobar bronchi (superior, middle, lower) corresponding to the three lobes. Left lung: Two lobar bronchi (upper and lower) corresponding to the two lobes. 3.3 Segmental (Tertiary) Bronchi Each lobar bronchus divides into segmental bronchi. There are typically 10 on the right and 8–10 on the left. Each segmental bronchus supplies a bronchopulmonary segment. Key Concept A bronchopulmonary segment is a functionally independent unit with its own artery, vein, and lymphatic drainage. These segments are important surgically because resection of a segment does not compromise adjacent segments. 3.4 Bronchioles Conducting bronchioles: Diameter <1 mm; they lack cartilage and glands. Lined by ciliated cuboidal epithelium. Terminal bronchioles: The most distal part of the conducting zone; each supplies a pulmonary acinus. Respiratory bronchioles: The first part of the respiratory zone; they have scattered alveoli budding directly from their walls. 4. The Lungs The lungs are the paired, cone-shaped organs of respiration located in the thoracic cavity on either side of the mediastinum. 4.1 Gross Anatomy Right lung: Larger and heavier; has three lobes (superior, middle, inferior) separated by horizontal and oblique fissures. Left lung: Smaller due to the cardiac notch; has two lobes (superior and inferior) separated by the oblique fissure. It contains the lingula (homologous to the right middle lobe). Apex: Projects into the root of the neck, 2–4 cm above the clavicle. Base: Concave, resting on the diaphragm. Hilum: Medial surface depression where bronchi, pulmonary vessels, bronchial vessels, lymphatics, and nerves enter and exit. Surfaces: Costal surface (convex, related to ribs) and Mediastinal surface (related to mediastinal structures). 4.2 Bronchopulmonary Segments Lobe Right Lung Segments Left Lung Segments Upper Lobe Apical, Posterior, Anterior Apical-posterior, Anterior, Superior lingular, Inferior lingular Middle Lobe Lateral, Medial — Lower Lobe Superior, Medial basal, Anterior basal, Lateral basal, Posterior basal Superior, Anteromedial basal, Lateral basal, Posterior basal 4.3 Pleura Parietal pleura: Lines the thoracic wall (costal pleura), diaphragm (diaphragmatic pleura), and mediastinum (mediastinal pleura). The cervical pleura (cupula) extends into the neck. Visceral pleura: Covers the lung surface, including the fissures. Pleural cavity: Potential space between parietal and visceral pleurae; contains a thin film of serous fluid (pleural fluid) that reduces friction during breathing. Pleural recesses: Potential spaces not occupied by lungs during quiet breathing, including the costodiaphragmatic recess (largest) and costomediastinal recess. 5. The Respiratory Zone The respiratory zone is where gas exchange occurs. It includes respiratory bronchioles, alveolar ducts, alveolar sacs, and alveoli. 5.1 Alveoli Approximately 300–500 million alveoli exist in adult lungs, providing a total surface area of 70–100 m². Each alveolus is a thin-walled sac (0.2–0.5 µm thick) lined by two types of pneumocytes: Type I pneumocytes: Squamous epithelial cells covering 95% of alveolar surface; the primary site of gas exchange. Type II pneumocytes: Cuboidal cells that produce surfactant (dipalmitoylphosphatidylcholine), which reduces surface tension and prevents alveolar collapse. Alveolar macrophages (dust cells): Phagocytose inhaled particles and pathogens. 5.2 Blood-Air Barrier The barrier between alveolar air and capillary blood consists of: Type I pneumocyte, fused basement membrane, and capillary endothelial cell. The total thickness is 0.2–0.5 µm, allowing for rapid gas diffusion. 5.3 Alveolar-Capillary Network Each alveolus is surrounded by a dense capillary network. Pulmonary arteries carry deoxygenated blood to the alveolar capillaries; pulmonary veins return oxygenated blood to the left atrium. Bronchial arteries (systemic): Supply oxygenated blood to the lung tissue and drain partially into pulmonary veins. 6. Clinical Correlations Clinical Scenarios Tracheal Stenosis: Narrowing of the tracheal lumen due to trauma, prolonged intubation, or granulomatous disease. Presents with stridor, dyspnea, and cough. Atelectasis: Collapse of lung tissue due to airway obstruction, compression, or surfactant deficiency. Types: Obstructive (resorption), Compressive (pleural effusion), Adhesive (ARDS). Pneumothorax: Air in the pleural cavity causing lung collapse. Can be spontaneous (rupture of bleb), traumatic
Organs of the upper respiratory tract
Anatomy

Organs of the upper respiratory tract

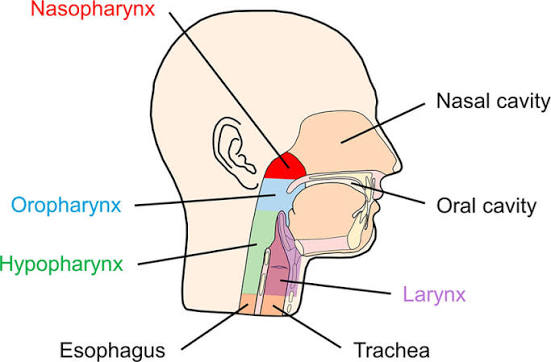
Organs of the Upper Respiratory Tract Complete, exhaustive anatomical study covering the structural organization, mucous membranes, regional compartments, and clinical pathologies of the upper airway. Prepared for Diploma-Level Clinical Medicine Curriculum. code Code 1. Introduction The upper respiratory tract consists of the nose, nasal cavity, paranasal sinuses, pharynx, and larynx. These structures serve as the entry portal for air, conditioning it through warming, humidification, and filtration before it reaches the lower respiratory tract. The upper airway also houses the organs of olfaction (smell) and phonation (voice production). 2. The Nose and Nasal Cavity 2.1 External Nose The external nose is a visible part of the respiratory system that projects from the face. It is composed of: Bone: Nasal bones, frontal processes of the maxillae, and the nasal part of the frontal bone. Cartilage: Septal, lateral, alar, and major/minor cartilages. Nares: The anterior openings (nostrils), bounded laterally by the alae. The bridge is supported by bone, while the tip and alae are cartilaginous and mobile. 2.2 Nasal Cavity The nasal cavity extends from the nostrils anteriorly to the choanae posteriorly, where it communicates with the nasopharynx. It is divided into right and left halves by the nasal septum, which is composed of the perpendicular plate of the ethmoid, the vomer, and the septal cartilage. Boundaries: Floor: Palatine process of the maxilla and horizontal plate of the palatine bone (hard palate). Roof: Nasal bones, cribriform plate of the ethmoid, and the body of the sphenoid. Lateral wall: Composed of several bones and characterized by the presence of conchae. 2.3 Nasal Conchae (Turbinates) The lateral wall contains three bony projections: superior, middle, and inferior conchae. These structures increase the surface area for warming and humidifying inspired air. Beneath each concha is a passage called a meatus: Superior meatus: Receives drainage from the posterior ethmoidal air cells. Middle meatus: Receives drainage from the frontal sinus, maxillary sinus, and anterior/middle ethmoidal air cells. Inferior meatus: Receives drainage from the nasolacrimal duct. 2.4 Nasal Mucosa Respiratory region: Lined with ciliated pseudostratified columnar epithelium with goblet cells. It covers most of the cavity. Mucus traps particles, and cilia move the mucus toward the pharynx (the mucociliary escalator). Olfactory region: Located in the roof and superior concha. It contains olfactory receptor neurons with cilia that bind odorant molecules. Axons pass through the cribriform plate to the olfactory bulb. A rich vascular plexus (cavernous tissue) warms inspired air. 2.5 Paranasal Sinuses These are air-filled cavities within cranial bones that communicate with the nasal cavity: Frontal sinuses: Within the frontal bone; drain into the middle meatus via the frontonasal duct. Maxillary sinuses: The largest; located within the body of the maxilla. Their floor is near the alveolar process of the maxilla, making them vulnerable to dental infection. Ethmoidal sinuses: Multiple small air cells within the ethmoid bone. Sphenoidal sinuses: Within the body of the sphenoid; drain into the sphenoethmoidal recess. Functions: Lighten the skull bones, resonate the voice, and produce mucus. Inflammation is known as sinusitis. 3. The Pharynx The pharynx is a muscular tube (12–14 cm) extending from the base of the skull to the esophagus. It serves as a common passage for air and food. 3.1 Nasopharynx Posterior to the nasal cavity and above the soft palate. Lined by respiratory epithelium. Contains the pharyngeal tonsil (adenoids) on the posterior wall. The auditory (Eustachian) tube opens into the lateral wall, equalizing middle ear pressure. During swallowing, the soft palate elevates to seal the nasopharynx, preventing nasal regurgitation. 3.2 Oropharynx Posterior to the oral cavity, between the soft palate and the epiglottis. Contains the palatine tonsils in the tonsillar fossae. Contains the lingual tonsil at the base of the tongue. Waldeyer ring: A ring of lymphoid tissue (pharyngeal, palatine, and lingual tonsils) surrounding the oropharyngeal inlet for immune defense. 3.3 Laryngopharynx (Hypopharynx) Extends from the tip of the epiglottis to the inferior border of the cricoid cartilage (C6), where it becomes the esophagus. The piriform fossae are recesses on either side of the laryngeal inlet; foreign bodies may lodge here. During swallowing, the larynx elevates and the epiglottis tilts downward to cover the laryngeal inlet, directing food into the esophagus. 4. The Larynx The larynx (voice box) is a cartilaginous structure located at the C3–C6 vertebral levels. It connects the pharynx to the trachea and serves three functions: airway patency, phonation, and protection of the lower airway. 4.1 Laryngeal Cartilages Thyroid cartilage: The largest; forms the laryngeal prominence (Adam’s apple). Composed of two laminae joined anteriorly. Cricoid cartilage: Signet-ring shaped; the only complete cartilaginous ring of the airway. Epiglottis: Leaf-shaped elastic cartilage attached to the thyroid cartilage. During swallowing, it folds down to cover the laryngeal inlet. Arytenoid cartilages: Paired pyramidal cartilages on the cricoid; articulate with the cricoid and move the vocal cords. Corniculate and cuneiform cartilages: Small paired cartilages within the aryepiglottic folds. 4.2 Laryngeal Cavity Vestibule: Space above the vestibular (false) vocal folds. Vestibular folds (false cords): Superior mucosal folds containing vestibular ligaments; no role in phonation. Vocal folds (true cords): Inferior mucosal folds containing vocal ligaments and the vocalis muscle. The space between them is the rima glottidis. Glottis: Comprises the vocal folds and the rima glottidis; the narrowest part of the larynx in adults. Subglottis: Region below the vocal folds extending to the inferior border of the cricoid. 4.3 Intrinsic Muscles Muscle Action on Vocal Cords Cricothyroid Tenses (lengthens) Posterior cricoarytenoid Opens glottis (the only abductor) Lateral cricoarytenoid Closes glottis (adductor) Thyroarytenoid Relaxes (shortens); fine-tunes pitch Arytenoid (transverse/oblique) Closes glottis 4.4 Nerve Supply Superior laryngeal nerve (CN X): Internal branch provides sensory innervation above the cords; external branch supplies the cricothyroid muscle. Recurrent laryngeal nerve (CN X): Motor to all intrinsic muscles except cricothyroid; sensory below the vocal cords. Clinical Note Damage to the recurrent laryngeal nerve causes hoarseness (unilateral) or life-threatening stridor (bilateral) due to vocal cord paralysis. 5. Clinical Correlations Epistaxis (Nosebleed) Most commonly occurs from the Kiesselbach plexus (Little area) on the anterior nasal septum. Causes include trauma, dry air, or

Disorders of Lymphatic system (Lymphadenitis, Hodgkin’s disease)
Anatomy

Disorders of Lymphatic system (Lymphadenitis, Hodgkin’s disease)

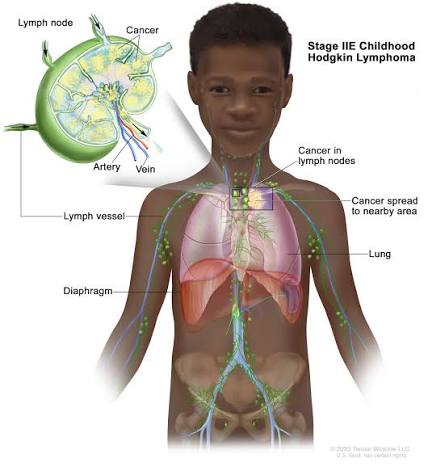
Disorders of the Lymphatic System Complete clinical notes covering the classification, pathophysiology, and management of lymphadenitis and Hodgkin Lymphoma. 1. Lymphadenitis Lymphadenitis is the inflammation of the lymph nodes, usually secondary to infection, immune activation, or malignancy in the drainage territory. It represents a localized immune response and is one of the most common clinical presentations in primary care and general medicine. 1.1 Definition and Classification Acute lymphadenitis: Rapid onset; tender, warm, enlarged nodes; typically bacterial. Chronic lymphadenitis: Persistent enlargement (>4 weeks); often granulomatous or neoplastic. Suppurative lymphadenitis: Progression to abscess formation with central necrosis and pus. Generalized lymphadenitis: Involvement of multiple non-contiguous node groups; suggests systemic disease. Localized lymphadenitis: Confined to a single regional group; indicates local infection or malignancy. 1.2 Causes and Risk Factors Category Common Causes Key Features Bacterial Staphylococcus aureus, Streptococcus pyogenes, Bartonella henselae (cat-scratch), Mycobacterium tuberculosis Acute, tender, erythematous; TB: matted, caseating, cold abscess Viral EBV (infectious mononucleosis), CMV, HIV, cytomegalovirus Bilateral, symmetrical, non-suppurative; often with pharyngitis or rash Fungal Histoplasma, Coccidioides, Sporothrix Endemic regions; chronic or granulomatous presentation Parasitic Toxoplasma gondii, filariasis, leishmaniasis Travel history; eosinophilia may be present Autoimmune SLE, rheumatoid arthritis, sarcoidosis Generalized; associated with other systemic features Malignant Metastatic carcinoma, lymphoma, leukemia Hard, fixed, non-tender; progressive enlargement; systemic B symptoms 1.3 Pathophysiology Infection or antigenic stimulus in the drainage area triggers immune cell recruitment to the regional node. Hyperplasia of germinal centers (B-cell proliferation) and paracortical expansion (T-cell response). Increased blood flow and vascular permeability cause redness, warmth, and swelling. Pressure on the capsule and surrounding tissues produces pain. In bacterial infections, neutrophil infiltration may lead to suppuration and abscess formation. In granulomatous infections (TB, fungi), epithelioid macrophages and giant cells form caseating granulomas. 1.4 Clinical Features Local signs: Enlarged, tender lymph node(s); overlying skin may be erythematous and warm. Systemic signs: Fever, malaise, anorexia; severity correlates with the underlying infection. Condition Distinguishing Features Reactive hyperplasia Recent infection; tender, mobile, bilateral; resolves within weeks Lymphoma Painless, progressive, rubbery; may have B symptoms TB Chronic, matted, cold abscess; exposure history; positive IGRA/TST Metastatic carcinoma Hard, fixed, non-tender; known primary malignancy Kikuchi-Fujimoto disease Young women; cervical nodes; self-limiting; histology diagnostic Castleman disease Localized or multicentric; hypervascular on imaging; biopsy diagnostic 1.7 Management Supportive care: Rest, hydration, analgesia (paracetamol or NSAIDs), warm compresses. Antibiotics: Empirical therapy targeting likely pathogens. — Community-acquired: amoxicillin-clavulanate or cephalexin for 7–10 days. — MRSA risk: clindamycin or trimethoprim-sulfamethoxazole. — Cat-scratch disease: azithromycin if severe; usually self-limiting. — TB lymphadenitis: standard anti-TB regimen (RIPE: rifampicin, isoniazid, pyrazinamide, ethambutol for 2 months, then rifampicin + isoniazid for 4 months). Surgical drainage: Incision and drainage for fluctuant abscesses; needle aspiration may suffice for small collections. Treatment of underlying cause: Antivirals where indicated, antiretroviral therapy for HIV, immunosuppressants for autoimmune disease. Follow-up: Reassess at 2–4 weeks; persistent or enlarging nodes require further investigation. Complications Abscess formation and spontaneous drainage. Bacteremia and sepsis. Chronic sinus tract formation (especially TB). Post-inflammatory fibrosis and persistent node enlargement. Misdiagnosis of underlying malignancy. 2. Hodgkin’s Disease (Hodgkin Lymphoma) Hodgkin lymphoma (HL) is a malignant neoplasm of the lymphatic system characterized by the presence of Reed-Sternberg cells in a background of inflammatory cells. It accounts for approximately 10% of all lymphomas and has a bimodal age distribution with peaks in young adulthood and after age 55. 2.1 Epidemiology and 2.2 Etiology Incidence: 2–3 per 100,000 annually in developed countries. Slight male predominance (M:F ratio 1.3:1). Infectious: Epstein-Barr virus (EBV) implicated in 40–50% of cases; HIV increases risk 10-fold. Genetic: Familial clustering suggests genetic susceptibility; HLA associations identified. Immunodeficiency: Congenital immunodeficiency, post-transplant immunosuppression. Environmental: No strong environmental carcinogen identified; smoking may be a minor risk factor. 2.3 Pathophysiology Originates from germinal center B cells that have undergone failed apoptosis. The neoplastic cell is the Reed-Sternberg (RS) cell or its variant, the Hodgkin cell. RS cells are large, binucleated or multinucleated cells with prominent eosinophilic nucleoli (‘owl-eye’ appearance). RS cells constitute <1% of the tumor mass; the majority is a reactive inflammatory infiltrate. RS cells express CD30 and CD15; they are usually negative for CD20 and CD45 (LCA). Cytokine production (IL-5, IL-10, TGF-beta) by RS cells contributes to the inflammatory background and systemic symptoms. 2.4 Classification (WHO 2016) Subtype Frequency Characteristics Nodular sclerosis (NSHL) 70% of cases Most common in young adults; collagen bands dividing nodules; lacunar RS cell variant; good prognosis. Mixed cellularity (MCHL) 20–25% Older adults and HIV-positive patients; numerous RS cells; EBV association common. Lymphocyte-rich (LRHL) 5% Few RS cells; abundant small lymphocytes; excellent prognosis. Lymphocyte-depleted (LDHL) <5% Rare; elderly or HIV-positive; numerous RS cells, few lymphocytes; aggressive. Nodular lymphocyte-predominant (NLPHL) Distinct entity Popcorn cells (LP cells); CD20+, CD30-; indolent; male predominance. 2.6 Staging (Ann Arbor System) Stage Description I Single lymph node region or single extralymphatic site (IE). II Two or more lymph node regions on the same side of the diaphragm. III Lymph node regions on both sides of the diaphragm; may include spleen (IIIS) or localized extralymphatic site (IIIE). IV Diffuse or disseminated involvement of one or more extralymphatic organs with or without lymph node involvement. Modifiers A: No systemic symptoms. B: Presence of B symptoms (fever, night sweats, weight loss). E: Involvement of a single extranodal site contiguous with a known nodal site. X: Bulky disease (mediastinal mass >1/3 thoracic diameter or nodal mass >10 cm). S: Spleen involvement. 2.7 Investigations Laboratory: Full blood count (anemia, leukocytosis, eosinophilia, or thrombocytosis); ESR and LDH (elevated levels correlate with disease burden); Liver and renal function tests; Serum albumin (low albumin is a poor prognostic factor); HIV and hepatitis B/C serology. Imaging: CT neck/chest/abdomen/pelvis (defines nodal and organ involvement); PET-CT (Gold standard for initial staging and response assessment). Biopsy: Excisional lymph node biopsy is mandatory; fine needle aspiration is insufficient for diagnosis. Immunohistochemistry: CD30+, CD15+, PAX5+ (weak), CD20 variable, CD45 negative. Bone Marrow Biopsy: Required in selected cases (stage IV, cytopenias, or if PET-CT is unavailable). 2.8 Differential Diagnosis Condition Distinguishing Features Non-Hodgkin lymphoma More common; diverse histology; CD30-/CD15-; no RS cells. Infectious mononucleosis Acute onset;

Formation and functions of lymph
Anatomy

Formation and functions of lymph

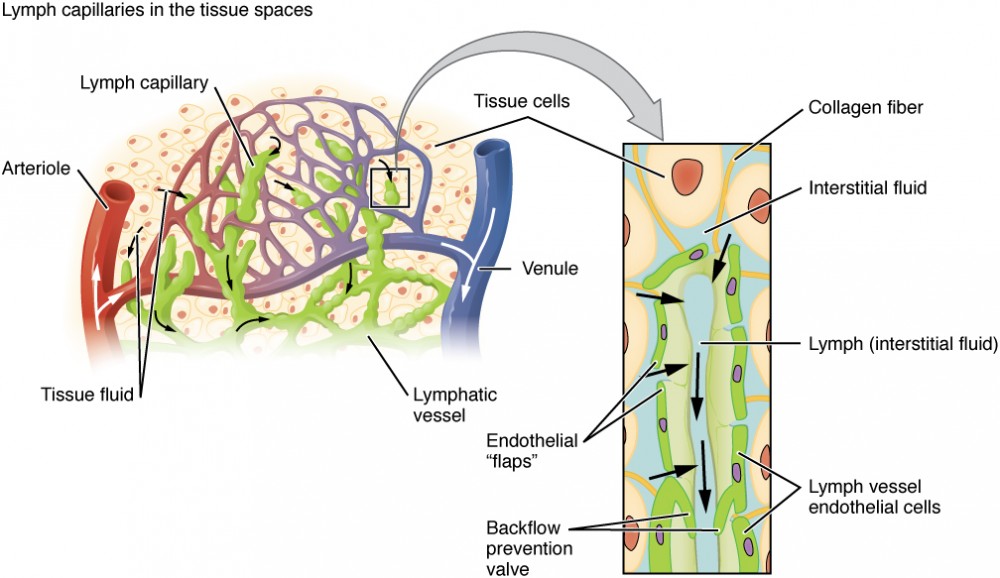
Formation and Functions of Lymph Comprehensive medical notes covering the physiological mechanisms of lymph formation, its chemical composition, circulation dynamics, and clinical relevance. 1. Lymph Formation Lymph is derived from interstitial fluid that has entered lymphatic capillaries. Its formation is a continuous process driven by the dynamics of fluid exchange at blood capillaries and the unique permeability of the lymphatic endothelium. 1.1 Origin: Interstitial Fluid Blood capillaries filter plasma into tissue spaces at the arteriolar end due to hydrostatic pressure exceeding oncotic pressure (Starling forces). Approximately 20 litres of fluid are filtered daily from blood capillaries into tissues. About 17–18 litres are reabsorbed at the venular end where oncotic pressure exceeds hydrostatic pressure. The remaining 2–3 litres constitute the net filtrate that becomes lymph. 1.2 Entry into Lymphatic Capillaries Lymphatic capillaries are blind-ended tubes with highly permeable walls. Their structure is specialized for the uptake of large molecules and fluid: Endothelial cells overlap like shingles; anchoring filaments tether them to surrounding connective tissue. When interstitial pressure rises (due to fluid accumulation or tissue movement), the endothelial junctions open, allowing fluid and particles to enter. Once inside the capillary, the fluid is termed lymph. Particles too large for blood capillaries, such as bacteria, cellular debris, and chylomicrons, can easily enter lymphatic capillaries. 1.3 Factors Promoting Lymph Formation Increased capillary permeability: Caused by inflammation or histamine release. Elevated venous pressure: Seen in heart failure or venous obstruction. Decreased plasma oncotic pressure: Resulting from hypoproteinemia (nephrotic syndrome, liver disease). Increased tissue metabolic activity and vasodilation. 2. Composition of Lymph Lymph closely resembles blood plasma in composition but with lower protein concentration and the addition of cellular elements from tissues. Component Characteristics Clinical Relevance Water and Electrolytes Similar to plasma Reflects plasma status Proteins Lower concentration than plasma (2–3 g/dL); includes albumin, globulins, fibrinogen Protein-losing enteropathies cause hypoproteinemia Lipids Chylomicrons in intestinal lymph (chyle); free fatty acids Milky appearance of chyle after meals; chylothorax if leaked Cells Lymphocytes (predominant), macrophages Reflects immune activity; metastatic cells may be present Cellular Debris Dead cells, bacteria, foreign particles Filtered and phagocytosed in lymph nodes Variations in Lymph Composition: Prenodal lymph: High cellular content, antigens, and debris; low antibody concentration. Postnodal lymph: Lower cellular content; higher antibody concentration due to plasma cell activity in nodes. Intestinal lymph (chyle): Milky appearance due to high lipid content; drains into the cisterna chyli. Liver lymph: High protein content (up to 6 g/dL) due to sinusoidal permeability. 3. Lymph Circulation Lymph flows through a one-way system from peripheral tissues toward the venous angles. Unlike blood, lymph has no central pump and relies on secondary mechanisms for propulsion. 3.1 Pathway of Lymph Flow Tissue spaces → lymphatic capillaries → collecting vessels → lymph nodes → lymphatic trunks → lymphatic ducts → subclavian veins. Lymph passes through multiple lymph nodes, progressively becoming cleaner and more antibody-rich. The entire volume of lymph (2–3 L/day) is returned to the bloodstream within 24 hours. 3.2 Mechanisms of Lymph Propulsion Skeletal muscle pump: Contraction of surrounding muscles compresses lymphatic vessels, propelling lymph forward. Respiratory pump: Changes in intrathoracic pressure during breathing create a suction effect, particularly in the thoracic duct. Intrinsic vessel contractions: Rhythmic contractions of smooth muscle in collecting vessel walls (lymphangion contractions). Valves: Bicuspid valves within collecting vessels prevent backflow, ensuring unidirectional transport. Arterial pulsations: Pulsations of adjacent arteries assist lymph movement in deep vessels. 3.3 Lymphatic Valves Formed by folds of the tunica intima. They are more numerous than venous valves, present every few millimetres. They are critical for preventing retrograde flow, especially in dependent limbs. Valve incompetence contributes to lymphedema and chronic lymphatic insufficiency. 4. Functions of the Lymphatic System The lymphatic system performs four principal functions that are essential for homeostasis and host defense. 4.1 Fluid Homeostasis Returns excess interstitial fluid to the bloodstream, preventing tissue edema. It maintains blood volume by conserving the 2–3 litres of daily capillary filtrate. Failure results in lymphedema, characterized by protein-rich tissue swelling. 4.2 Immune Surveillance and Response Lymph nodes filter lymph and trap foreign antigens, initiating adaptive immune responses. Dendritic cells and macrophages in nodes present antigens to T and B lymphocytes. Memory lymphocytes provide long-term immunity. 4.3 Fat Absorption Specialized lymphatic capillaries in intestinal villi, called lacteals, absorb dietary triglycerides. Lipids are packaged into chylomicrons within enterocytes and extruded into lacteals. Chyle (lipid-rich lymph) drains via intestinal lymphatic trunks to the cisterna chyli and thoracic duct, bypassing the hepatic portal system. Clinical Relevance Damage to intestinal lymphatics causes protein-losing enteropathy and steatorrhea. 4.4 Transport of Cells and Molecules Transports lymphocytes between tissues and lymphoid organs. It carries hormones, enzymes, and metabolic products from tissues to blood and facilitates the dissemination of malignant cells (lymphatic metastasis). 5. Clinical Relevance Lymphedema: Accumulation of protein-rich interstitial fluid due to impaired lymphatic drainage. Primary: Milroy disease (congenital aplasia), lymphedema praecox (puberty onset), lymphedema tarda (adult onset). Secondary: Post-mastectomy axillary node dissection, filariasis (Wuchereria bancrofti), radiation, trauma, recurrent infections. Features: Pitting or non-pitting edema, skin thickening, fibrosis, increased infection risk (cellulitis). Chylothorax and Chylous Ascites: Leakage of chyle into the pleural cavity or peritoneum due to thoracic duct injury (trauma, surgery, malignancy). It presents as milky pleural fluid with elevated triglycerides (>110 mg/dL). Management includes dietary modification (medium-chain triglycerides) or surgical ligation. Protein-Losing Enteropathy: Loss of plasma proteins into the intestinal lumen due to lymphatic obstruction or mucosal disease. Causes include intestinal lymphangiectasia and Crohn disease. Features include hypoalbuminemia, edema, lymphocytopenia, and steatorrhea. 6. Key Points Summary Lymph formation: Formed from excess interstitial fluid (2–3 L/day) entering blind-ended capillaries. Regional Composition: Intestinal lymph (chyle) is lipid-rich; liver lymph is protein-rich. Unidirectional flow: Driven by skeletal muscle/respiratory pumps and intrinsic contractions, assisted by valves. Four principal functions: Fluid homeostasis, immune surveillance, fat absorption, and transport of cells/molecules. Clinical disorders: Include lymphedema, chylothorax, and protein-losing enteropathy.

Structure of Lymphatic system
Anatomy

Structure of Lymphatic system

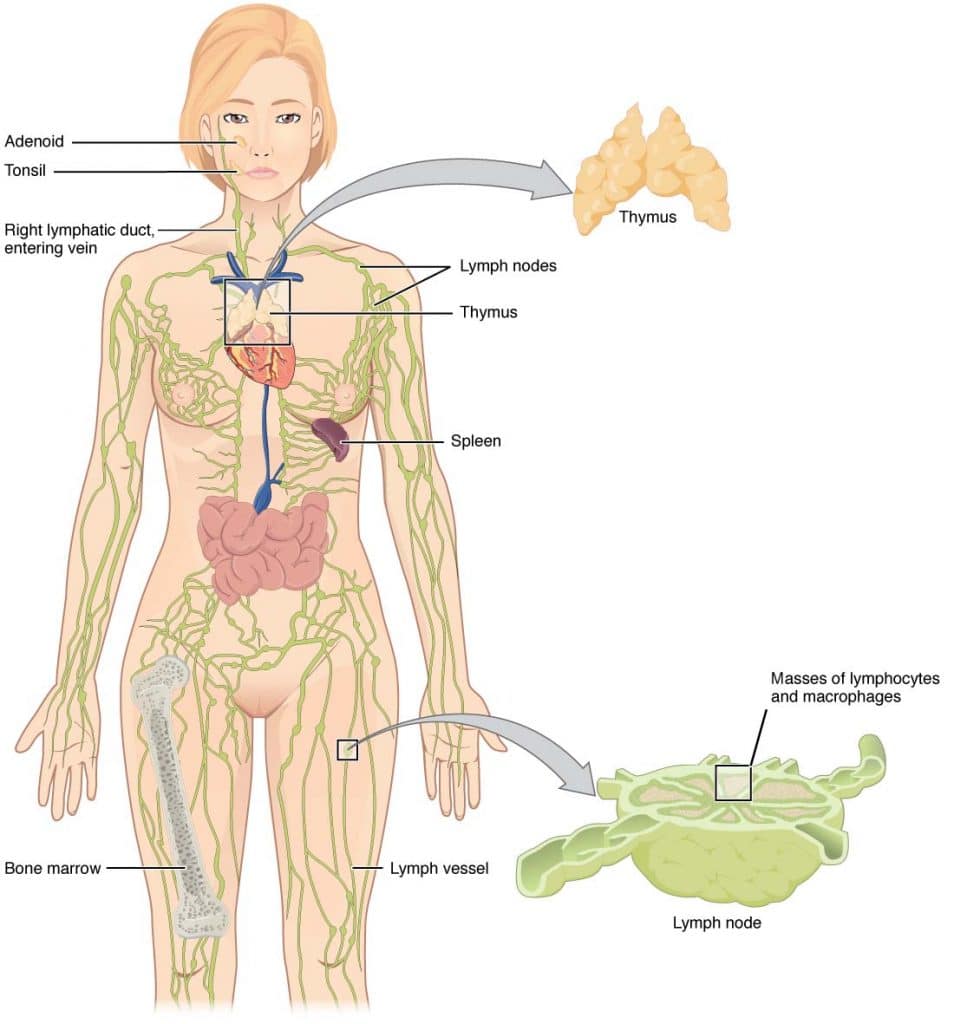
Structure of the Lymphatic System A comprehensive note covering the lymphatic tissues, vessels, and organs. 1. Introduction and Overview The lymphatic system is a network of tissues, vessels, and organs that works in close partnership with the cardiovascular system. It performs essential roles in fluid homeostasis, immune surveillance, and lipid absorption. Unlike the closed circulatory system, the lymphatic system is an open, one-way transport network that returns excess interstitial fluid to the bloodstream. Definition: The lymphatic system comprises lymphatic vessels, lymphoid tissue, lymph nodes, and lymphoid organs that collect and transport lymph—a clear fluid derived from interstitial fluid—back to the venous circulation. Key Components: Lymphatic vessels: Including capillaries, collecting vessels, trunks, and ducts. Lymph nodes: Distributed along vessel pathways for filtration. Lymphoid organs: Classified as primary (bone marrow, thymus) or secondary (spleen, tonsils, MALT). Lymph: The actual fluid transported within the system. Clinical Relevance Understanding lymphatic anatomy is fundamental for interpreting lymphadenopathy, planning cancer staging, assessing lymphedema, and performing safe surgical dissections. 2. Lymphatic Vessels Lymphatic vessels form a hierarchical network that begins as blind-ended capillaries in tissue spaces and progressively converges into larger ducts that drain into the venous system. 2.1 Lymphatic Capillaries Structure: Blind-ended, thin-walled vessels composed of a single layer of overlapping endothelial cells. Mechanism: Endothelial cells are anchored to surrounding connective tissue by fine filaments; increased interstitial pressure opens the junctions to allow fluid entry. Distribution: Present in most tissues except avascular structures (cartilage, epidermis, cornea) and the central nervous system. Specialized Capillaries: Found in the small intestine, these are called lacteals and are responsible for absorbing dietary lipids. 2.2 Collecting Vessels Formed by the union of lymphatic capillaries. Valves: Contain valves (formed by intimal folds) that ensure unidirectional flow toward the heart. Walls: Thin walls with three layers: endothelium, smooth muscle media, and fibrous adventitia. Location: Superficial vessels drain skin and subcutaneous tissue; deep vessels accompany arteries and veins. 2.3 Lymphatic Trunks Formed by the convergence of collecting vessels. There are five principal trunks: Jugular: Drains head and neck. Subclavian: Drains upper limbs. Bronchomediastinal: Drains the thorax. Intestinal: Drains abdominal viscera. Lumbar: Drains lower limbs and pelvis. 2.4 Lymphatic Ducts Thoracic duct: The largest lymphatic vessel (~38–45 cm long). It originates from the cisterna chyli (at L1-L2), ascends through the posterior mediastinum, and drains into the junction of the left subclavian and internal jugular veins. It collects lymph from the entire body except the right upper quadrant. Right lymphatic duct: A short vessel (1–2 cm) that drains into the right venous angle. It collects lymph from the right side of the head and neck, right upper limb, and right thorax. 3. Lymph Nodes Lymph nodes are small, bean-shaped organs (2–10 mm) distributed along lymphatic vessels. They function as filtration stations and sites of immune cell activation. 3.1 Gross Structure Each node is enclosed by a fibrous capsule. Afferent vessels: Penetrate the convex surface. Efferent vessels: Exit at the hilum. An internal framework of trabeculae extends from the capsule, supporting parenchymal tissue. 3.2 Microscopic Architecture Cortex: Outer zone containing lymphoid follicles (B-cell zones). Primary follicles are dense; secondary follicles develop germinal centers after antigen exposure. Paracortex: Deep cortical region rich in T lymphocytes. Contains high endothelial venules (HEVs) that allow lymphocyte entry from blood. Medulla: Innermost zone with medullary cords (plasma cells, B cells, macrophages) and medullary sinuses. Sinuses: Subcapsular, trabecular, and medullary sinuses allow slow lymph flow, facilitating phagocytosis and antigen presentation. 3.3 Regional Lymph Node Groups Region Major Groups Drainage Area Head and Neck Cervical, submandibular, preauricular, parotid Scalp, face, oral cavity, pharynx Upper Limb Axillary, epitrochlear, infraclavicular Breast, upper limb, chest wall Thorax Hilar, mediastinal, paratracheal Lungs, heart, mediastinum Abdomen Mesenteric, para-aortic, celiac GI tract, liver, spleen, kidneys Lower Limb Inguinal, popliteal Lower limb, perineum, external genitalia 4. Lymphoid Organs Lymphoid organs are classified as primary (sites of lymphocyte development) or secondary (sites of immune response activation). 4.1 Primary Lymphoid Organs Bone Marrow: Site of hematopoiesis and B-lymphocyte maturation. Progenitor cells differentiate into mature B cells expressing surface immunoglobulins. Also the source of T-cell progenitors that migrate to the thymus. Thymus: Bilobed organ located in the anterior superior mediastinum. Largest in childhood; undergoes involution after puberty, replaced by adipose tissue. Cortex: Densely packed with immature T lymphocytes (thymocytes). Medulla: Less cellular; contains Hassall corpuscles and mature T cells. Site of T-cell maturation and positive/negative selection (self-tolerance). 4.2 Secondary Lymphoid Organs Spleen: The largest lymphoid organ, located in the left upper quadrant beneath the diaphragm. Functions: Filtration of blood, removal of senescent erythrocytes, immune response to blood-borne pathogens. White pulp: Lymphoid tissue surrounding central arteries; contains periarteriolar lymphoid sheaths (T cells) and lymphoid follicles (B cells). Red pulp: Vascular sinusoids and splenic cords (cords of Billroth); site of blood filtration. Marginal zone: Interface between white and red pulp; rich in macrophages. Tonsils: Aggregates of lymphoid tissue in the oropharynx: palatine, pharyngeal (adenoids), and lingual. Form Waldeyer ring, a first-line defense against inhaled/ingested pathogens. Lack a capsule and have deep crypts lined by epithelium. Mucosa-Associated Lymphoid Tissue (MALT): Diffuse lymphoid tissue in mucosal surfaces (respiratory, GI, GU tracts). Peyer patches: Aggregated lymphoid follicles in the ileum; specialized for sampling intestinal antigens via M cells. Appendix: Contains abundant lymphoid tissue for gut immune surveillance. 5. Clinical Correlations Sentinel Lymph Node Biopsy The sentinel node is the first lymph node to receive drainage from a tumor site. Identification guides cancer staging and surgical planning (e.g., in melanoma or breast cancer). Lymphedema Accumulation of lymph in interstitial spaces due to impaired drainage. Primary: Congenital lymphatic hypoplasia. Secondary: Post-surgical, post-radiation, or caused by filariasis. Splenomegaly Enlargement of the spleen due to infections (malaria, mononucleosis), hematologic disorders, or portal hypertension. May cause hypersplenism with cytopenias. 6. Key Points Summary The lymphatic system is an open, one-way network returning interstitial fluid to venous circulation. Lymphatic capillaries are blind-ended; collecting vessels contain valves. The thoracic duct drains most of the body; the right lymphatic duct drains the right upper quadrant. Lymph nodes filter lymph and activate immune responses via B-cell follicles

Disorders of blood circulation (Heart failure, Arteriosclerosis)
Anatomy

Disorders of blood circulation (Heart failure, Arteriosclerosis)

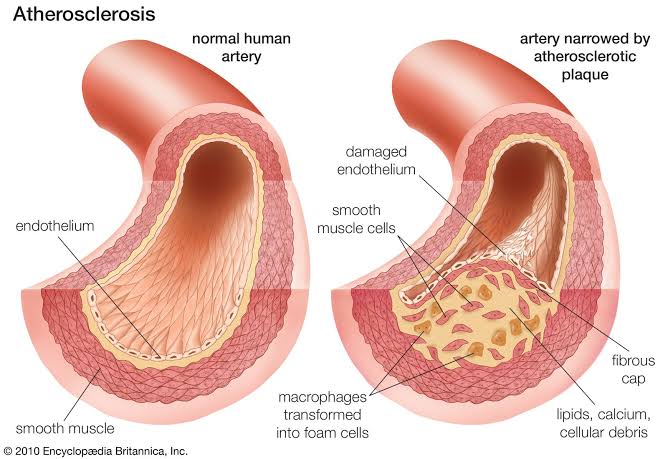
Disorders of Blood Circulation Complete study notes on Heart Failure and Arteriosclerosis, covering definitions, classifications, pathophysiology, clinical manifestations, investigations, and the “Four Pillars” of modern management. 1. HEART FAILURE (HF) 1.1 Definition Heart Failure (HF) is a clinical syndrome characterized by structural or functional abnormalities of the heart that result in impaired ventricular filling or ejection of blood. It is not a single disease but a constellation of signs and symptoms arising from inadequate cardiac output to meet the metabolic demands of the body, or from elevated cardiac filling pressures at rest or with exertion. 1.2 Classification A. By Ejection Fraction (2022 AHA/ACC/HFSA Guidelines) Type LVEF Pathophysiological Description HFrEF (Reduced) ≤ 40% Systolic dysfunction; impaired contractility. HFmrEF (Mildly Reduced) 41–49% Heart Failure with mildly reduced Ejection Fraction; intermediate group. HFpEF (Preserved) ≥ 50% Diastolic dysfunction; impaired relaxation and filling. HFimpEF (Improved) > 40% Previously HFrEF with subsequent LVEF > 40% on repeated measurement. B. By AHA/ACC/HFSA Stages (Progressive Framework) Stage A: At risk for HF but without symptoms, structural heart disease, or cardiac biomarkers. Stage B: Structural heart disease but no prior or current signs/symptoms of HF (e.g., prior MI, LV hypertrophy, valvular disease). Stage C: Structural heart disease with prior or current symptoms of HF. Stage D: Marked HF symptoms that interfere with daily life; recurrent hospitalizations despite optimized medical therapy (GDMT). C. By NYHA Functional Classification (Symptom Severity) Class I: No limitation of physical activity. Ordinary activity does not cause symptoms. Class II: Slight limitation. Comfortable at rest. Ordinary activity causes fatigue, palpitation, dyspnea, or chest pain. Class III: Marked limitation. Comfortable at rest. Less than ordinary activity causes symptoms. Class IV: Unable to perform any physical activity without symptoms. Symptoms present at rest. 1.3 Etiology and Risk Factors Category Specific Causes Ischemic heart disease Myocardial infarction, chronic angina, hibernating myocardium. Hypertension Chronic pressure overload leading to LV hypertrophy and remodeling. Valvular disease Aortic stenosis/regurgitation, mitral stenosis/regurgitation. Cardiomyopathies Dilated (alcohol, viral, genetic), hypertrophic, restrictive. Arrhythmias Atrial fibrillation (tachycardia-induced cardiomyopathy). Toxins/Drugs Alcohol, cocaine, anthracyclines (doxorubicin), trastuzumab. Metabolic Diabetes, thyroid disease, obesity, Thiamine deficiency (Beriberi). High-output states Anemia, hyperthyroidism, arteriovenous fistula. 4.1.4 Pathophysiology A. Left-Sided Heart Failure Forward failure (low output): Reduced cardiac output → tissue hypoperfusion → fatigue, weakness, oliguria, altered mental status. Backward failure (pulmonary congestion): LV fails to pump effectively → increased left ventricular end-diastolic pressure (LVEDP) → increased left atrial pressure → pulmonary venous congestion → Pulmonary Edema. B. Right-Sided Heart Failure Commonly caused by Left-sided HF, pulmonary hypertension, or chronic lung disease (Cor Pulmonale). Right ventricle fails to pump effectively → increased right ventricular and right atrial pressure → Systemic Venous Congestion. Clinical consequences: Jugular venous distension (JVD), hepatomegaly, peripheral edema (ankles, sacrum), and ascites. C. Neurohormonal Activation Sympathetic Nervous System: Increased norepinephrine → increased heart rate and contractility. Chronic activation causes myocardial toxicity and arrhythmias. RAAS System: Decreased renal perfusion → Renin release → Angiotensin II (vasoconstriction) + Aldosterone (sodium/water retention) → Volume Overload. Natriuretic Peptides (BNP, NT-proBNP): Released from stretched myocardium to promote vasodilation and diuresis (compensatory). Key Concept Cardiac Remodeling Concentric Hypertrophy: Increased wall thickness due to pressure overload (HTN, Aortic Stenosis). Eccentric Hypertrophy: Chamber dilation due to volume overload (MI, Mitral Regurgitation). 4.1.5 Clinical Features Symptom/Sign Left-Sided HF Right-Sided HF Dyspnea Exertional, Orthopnea, PND Less prominent Cough Dry or productive (pink frothy) Not typical Edema Pulmonary edema (crackles) Peripheral pitting edema JVP Normal or elevated Elevated (key sign) Heart Sounds S3 gallop Loud P2 (pulmonic) Clinical Alert Acute Pulmonary Edema (Severe Left HF) Presents with severe dyspnea at rest, anxiety, diaphoresis, and pink frothy sputum. This is a medical emergency requiring immediate intervention (Oxygen, Diuretics, Vasodilators). 4.1.6 Investigations Chest X-ray: Cardiomegaly (ratio > 50%), pulmonary congestion, Kerley B lines, and pleural effusions. ECG: Evidence of arrhythmias (Atrial Fibrillation), LV hypertrophy, Q waves (prior MI), or LBBB. Echocardiography: Gold standard for assessing LVEF, chamber size, and valvular function. BNP / NT-proBNP: Elevated levels (> 400 pg/mL BNP) support HF; levels < 100 pg/mL make HF unlikely. Troponins: Elevated in acute decompensation or myocardial stretch/necrosis. 4.1.7 Management of Heart Failure A. Guideline-Directed Medical Therapy (GDMT) — “The Four Pillars” For HFrEF, the standard of care includes the simultaneous or rapid sequence initiation of: ARNI (Sacubitril/Valsartan): Or ACEI/ARB; inhibits RAAS and neprilysin. Beta-blockers: (Carvedilol, Bisoprolol, Metoprolol succinate) to block sympathetic overactivation. MRA: (Spironolactone, Eplerenone) to block aldosterone. SGLT2 Inhibitors: (Dapagliflozin, Empagliflozin) to improve cardiovascular outcomes. B. Acute Management Oxygen therapy if hypoxemic. IV loop diuretics (Furosemide) to reduce fluid volume. Vasodilators (Nitrates) if hypertensive. Inotropes (Dobutamine) if in cardiogenic shock. 4.2 ARTERIOSCLEROSIS 4.2.1 Definition Arteriosclerosis is an umbrella term for the thickening, hardening, and loss of elasticity of arterial walls. Atherosclerosis is a specific type involving atheromatous plaque formation in the tunica intima. 4.2.2 Types of Arteriosclerosis Type Affected Vessels Key Feature Atherosclerosis Large and medium arteries Lipid-rich plaques in tunica intima; inflammatory. Monckeberg medial sclerosis Medium-sized muscular arteries Calcium deposits in tunica media; no luminal narrowing. Arteriolosclerosis Small arteries and arterioles Hyaline or hyperplastic thickening; associated with HTN/Diabetes. 4.2.3 Atherosclerosis Pathophysiology Response-to-Injury Hypothesis: Endothelial injury: Caused by smoking, hypertension, or diabetes. Lipid accumulation: LDL enters the intima and becomes oxidized (Ox-LDL). Inflammatory response: Macrophages engulf Ox-LDL to become Foam Cells. Smooth muscle proliferation: Migration from media to intima; production of collagen. Plaque progression: Fibrous cap forms over a lipid core. Plaque Morphology Feature Stable Plaque Unstable (Vulnerable) Plaque Fibrous cap Thick, well-developed Thin or absent Lipid core Small Large (> 40% of volume) Risk Gradual narrowing (Angina) Rupture → Thrombosis (MI/Stroke) Summary & Key Clinical Pearls The Four Pillars of HFrEF therapy (ARNI, beta-blocker, MRA, SGLT2i) are all mortality-reducing. BNP/NT-proBNP are essential biomarkers for excluding heart failure. Atherosclerosis is a systemic disease; management of one territory (e.g., coronary) requires modification of all vascular beds. Statins are indicated for all patients with established atherosclerotic disease regardless of baseline LDL. Ankle-brachial index (ABI) < 0.9 indicates Peripheral Artery Disease (PAD).

Types of circulation (Pulmonary, Systemic, Fetal)
Anatomy

Types of circulation (Pulmonary, Systemic, Fetal)

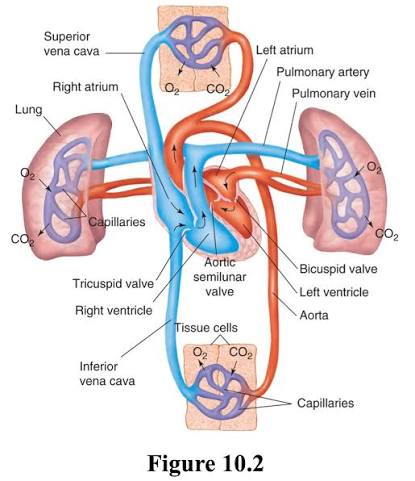
Types of Circulation Complete study notes covering Pulmonary, Systemic, and Fetal circulation, including physiological mechanisms, anatomical pathways, special circulatory systems, and clinical correlations. 3.1 Introduction The circulatory system is responsible for transporting blood throughout the body. In adults, there are two primary circuits: pulmonary circulation (blood flow between the heart and lungs) and systemic circulation (blood flow between the heart and all body tissues). During fetal development, a specialized fetal circulation exists to bypass the non-functioning lungs and liver. 3.2 Pulmonary Circulation 3.2.1 Definition and Purpose Pulmonary circulation is the portion of the cardiovascular system that transports deoxygenated blood from the right side of the heart to the lungs and returns oxygenated blood to the left side of the heart. Purpose: Gas exchange: Loading oxygen and unloading carbon dioxide in pulmonary capillaries. Blood volume reservoir: Pulmonary vessels contain approximately 9% of total blood volume. Filtration: Removal of small blood clots and air bubbles by pulmonary capillaries. 3.2.2 Pathway of Pulmonary Circulation The precise anatomical route follows this sequence: Right ventricle → Pulmonary valve → Pulmonary trunk → Right and left pulmonary arteries → Lobar and segmental arteries → Pulmonary capillaries (alveoli) → Pulmonary venules → Pulmonary veins (4 total: 2 from each lung) → Left atrium Key Features Pulmonary arteries carry deoxygenated blood (exception to the general rule). Pulmonary veins carry oxygenated blood (exception to the general rule). Pulmonary circulation is a low-pressure, low-resistance system. Pulmonary artery pressure: 15-30 mmHg systolic, 4-12 mmHg diastolic. Pulmonary vascular resistance is approximately 1/10 of systemic resistance. 3.2.3 Physiology of Pulmonary Circulation Hypoxic vasoconstriction: Unique response of pulmonary vessels: alveolar hypoxia causes local vasoconstriction. Directs blood away from poorly ventilated alveoli toward well-ventilated regions. Optimizes ventilation-perfusion (V/Q) matching. Contrast with systemic circulation: hypoxia causes vasodilation. Gravity effects: In upright position, blood flow is greater at lung bases than apices. Zone 1 (apex): Alveolar pressure > arterial pressure; minimal flow (potential for alveolar dead space). Zone 2 (mid-lung): Arterial pressure > alveolar pressure > venous pressure; intermittent flow. Zone 3 (base): Arterial and venous pressures > alveolar pressure; continuous flow. 3.2.4 Clinical Correlation Clinical Pearl Pulmonary Embolism (PE) Obstruction of pulmonary arteries by thrombus (usually from deep vein thrombosis). Symptoms include sudden dyspnea, pleuritic chest pain, tachypnea, tachycardia, and hypoxemia. Diagnosis via CT pulmonary angiography (CTPA), D-dimer, and Wells score. Management involves anticoagulation or thrombolysis in massive PE. Pulmonary Hypertension Mean pulmonary artery pressure > 20 mmHg (2022 ESC/ERS guidelines). Causes include left heart disease, lung disease, or idiopathic factors. Leads to right ventricular hypertrophy and eventually right heart failure (cor pulmonale). 3.3 Systemic Circulation 3.3.1 Definition and Purpose Systemic circulation is the portion of the cardiovascular system that transports oxygenated blood from the left side of the heart to all body tissues and returns deoxygenated blood to the right side of the heart. Purpose: Delivery of oxygen and nutrients to all body tissues. Removal of carbon dioxide and metabolic waste products. Transport of hormones from endocrine glands to target organs. Regulation of body temperature (thermoregulation via blood flow to skin). Maintenance of fluid and electrolyte balance. 3.3.2 Pathway of Systemic Circulation Left ventricle → Aortic valve → Ascending aorta → Aortic arch → Descending thoracic aorta → Abdominal aorta → Common iliac arteries → Arteries of lower limbs → Arterioles → Capillary beds (all tissues) → Venules → Veins → Inferior vena cava (from below heart) + Superior vena cava (from above heart) → Right atrium 3.3.3 Major Arterial Branches From aortic arch: Brachiocephalic trunk → right subclavian + right common carotid. Left common carotid → head and neck. Left subclavian → left upper limb. From descending aorta: Intercostal arteries → chest wall. Celiac trunk → liver, stomach, spleen. Superior mesenteric artery → small intestine, proximal colon. Renal arteries → kidneys. Inferior mesenteric artery → distal colon, rectum. Common iliac arteries → pelvis and lower limbs. 3.3.4 Major Venous Drainage Superior vena cava: Formed by union of brachiocephalic veins. Drains head, neck, upper limbs, chest wall, and upper thoracic organs. Inferior vena cava: Formed by union of common iliac veins. Drains lower limbs, pelvis, abdomen, kidneys, and liver (hepatic veins). Clinical Note Hepatic Portal System A unique venous system: capillaries (GI tract) → portal vein → capillaries (liver) → hepatic veins → IVC. Carries nutrient-rich, deoxygenated blood from digestive organs to the liver for processing. This is a critical site for first-pass metabolism and detoxification. 3.3.5 Special Circulations Coronary circulation: Supplies heart muscle itself. Arises from ascending aorta; drains into right atrium via coronary sinus. Cerebral circulation: Internal carotid arteries and vertebral arteries form the Circle of Willis. Protected by the blood-brain barrier (tight junctions in continuous capillaries). Renal circulation: High blood flow (20-25% of cardiac output) for filtration. Features two capillary beds in series: glomerular capillaries (filtration) and peritubular capillaries (reabsorption). Splanchnic circulation: Blood flow to GI tract, liver, spleen, and pancreas. Highly variable; increases after meals (active hyperemia). 3.3.6 Regulation of Systemic Circulation Short-term regulation (seconds to minutes): Baroreceptor reflex: carotid sinus and aortic arch receptors detect pressure changes; mediate heart rate and vasomotor tone via autonomic nervous system. Chemoreceptor reflex: carotid and aortic bodies detect changes in O2, CO2, and pH. Local autoregulation: myogenic response (Bayliss effect) and metabolic factors. Long-term regulation (hours to days): Renin-angiotensin-aldosterone system (RAAS): regulates blood volume and pressure. Antidiuretic hormone (ADH/vasopressin): regulates water reabsorption in kidneys. Atrial natriuretic peptide (ANP): promotes sodium and water excretion. 3.4 Fetal Circulation 3.4.1 Overview Fetal circulation is distinctly different from adult circulation because the fetus does not use its lungs for gas exchange. Instead, the placenta serves as the site of oxygenation, nutrient delivery, and waste removal. The fetal heart and blood vessels contain special shunts that bypass the lungs and liver. 3.4.2 Key Structures in Fetal Circulation Placenta: Organ of exchange between maternal and fetal circulations. Maternal oxygenated blood and nutrients diffuse across placental barrier into fetal blood. Fetal waste products (CO2, urea) diffuse into maternal blood. Connected to fetus via umbilical cord. Umbilical Cord: Contains two umbilical

Structure and functions of blood vessels
Anatomy

Structure and functions of blood vessels

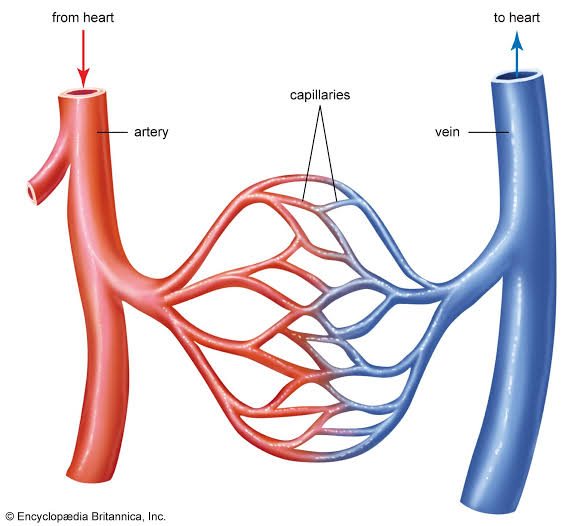
Structure and Functions of Blood Vessels Complete study notes covering the histology of vessel walls, classification of the vascular tree, hemodynamics, capillary exchange mechanisms, and major systemic vessels. 2.1 Introduction Blood vessels form a closed system of tubes that transport blood between the heart and body tissues. There are five main types: arteries, arterioles, capillaries, venules, and veins. Together, they regulate blood flow, blood pressure, and the exchange of substances between blood and tissues. 2.2 General Structure of Blood Vessels Most blood vessels share a common three-layered (tunica) wall structure: Layer Name Composition Function Tunica externa Outer layer Connective tissue (collagen) with elastic fibers Protection, anchoring, nerve/vessel passage Tunica media Middle layer Smooth muscle, elastic fibers (lamellae) Vasoconstriction, vasodilation, pressure regulation Tunica intima Inner layer Endothelium (simple squamous epithelium) on basement membrane Smooth surface for blood flow; prevents clotting Key Histological Difference Capillaries consist only of a single layer of endothelium (tunica intima) and a basement membrane, allowing for efficient nutrient and gas exchange. 2.3 Arteries Arteries carry blood away from the heart. They are classified by size and structure into three categories: 2.3.1 Elastic (Conducting) Arteries Largest arteries: Aorta, pulmonary trunk, brachiocephalic, common carotid, subclavian, common iliac arteries. Structure: Tunica media contains abundant elastic fibers (lamellae) with less smooth muscle. Function: Conduct blood from heart to medium-sized arteries; elastic recoil maintains continuous blood flow during diastole (Windkessel effect). 2.3.2 Muscular (Distributing) Arteries Medium-sized arteries: Radial, ulnar, femoral, tibial, coronary arteries. Structure: Tunica media contains more smooth muscle (40-60% of wall thickness) and less elastic tissue. Function: Distribute blood to specific organs and tissues; vasoconstriction and vasodilation regulate blood flow to organs. 2.3.3 Arterioles Smallest arteries: 10-100 um diameter. Structure: Tunica media has 1-3 layers of smooth muscle cells. Function: Major resistance vessels; regulate blood flow into capillary beds; primary site of peripheral vascular resistance. Precapillary sphincters: Rings of smooth muscle that control capillary blood flow. Arterial Blood Pressure Systolic pressure: 90-120 mmHg (peak pressure during ventricular systole). Diastolic pressure: 60-80 mmHg (minimum pressure during ventricular diastole). Mean arterial pressure (MAP): ~93 mmHg = diastolic + 1/3 pulse pressure. Pulse pressure: systolic – diastolic (normally 30-40 mmHg). 2.4 Capillaries Capillaries are the smallest blood vessels (5-10 um diameter) and form extensive networks (capillary beds) between arterioles and venules. They are the primary site of exchange between blood and tissues. 2.4.1 Structure Wall composed of a single layer of endothelial cells on a basement membrane. No tunica media or tunica externa. Total surface area: Approximately 600 m² (enormous exchange capacity). Total length: Approximately 96,000 km if all capillaries were placed end-to-end. 2.4.2 Types of Capillaries Type Structure Location Function Continuous Endothelial cells joined by tight junctions; complete basement membrane Muscle, skin, lungs, brain (blood-brain barrier) Most common; controlled exchange of water, ions, small molecules Fenestrated Endothelial cells have pores (fenestrae); thin/continuous basement membrane Kidneys, intestines, endocrine glands Rapid exchange of fluids, solutes; filtration, absorption Sinusoidal Large, irregular lumen; incomplete basement membrane; gaps between endothelial cells Liver, spleen, bone marrow, lymph nodes Allow passage of large molecules, cells (RBCs, WBCs) 2.4.3 Capillary Exchange Mechanisms Diffusion: Primary mechanism for exchange of gases, nutrients, and waste products. — Lipid-soluble: (O2, CO2, steroid hormones) pass directly through endothelial membranes. — Water-soluble: (glucose, amino acids, ions) pass through intercellular clefts or fenestrae. Transcytosis: Transport of large molecules (proteins, hormones) via vesicles (endocytosis + exocytosis). Bulk Flow (Filtration and Reabsorption): Driven by hydrostatic and osmotic pressure differences (Starling forces). — At arterial end: net filtration (fluid moves out into interstitium). — At venous end: net reabsorption (fluid moves back into capillary). — Approximately 85% of filtered fluid is reabsorbed; 15% returns via lymphatic vessels. Starling Equation Net filtration = Kf x [(Pc – Pi) – (πc – πi)] Pc = capillary hydrostatic pressure Pi = interstitial hydrostatic pressure πc = plasma colloid osmotic pressure πi = interstitial colloid osmotic pressure 2.5 Veins and Venules Veins carry blood toward the heart. They have larger lumens and thinner walls than corresponding arteries. 2.5.1 Venules Smallest veins: 10-100 um; formed by union of capillaries. Postcapillary venules: Major site of leukocyte extravasation during inflammation. Tunica media is very thin (1-2 layers of smooth muscle). 2.5.2 Veins Medium and large veins have all three tunics, but tunica media is thinner than in arteries. Tunica externa is the thickest layer in large veins. Luminal diameter is larger than corresponding arteries. Blood pressure is low (approximately 10-15 mmHg in vena cava). Blood volume capacity is high (approximately 60% of total blood volume at rest). Venous Return Mechanisms: Skeletal muscle pump: Contraction of surrounding muscles compresses veins, pushing blood toward the heart (one-way valves prevent backflow). Respiratory pump: During inspiration, thoracic pressure decreases and abdominal pressure increases, drawing blood toward the heart. One-way valves: Prevent backflow of blood, especially in lower limbs. Gravity: Aided by upright posture and venous tone. Clinical Correlation Varicose Veins Dilated, tortuous, elongated superficial veins (commonly saphenous veins). Caused by incompetent venous valves, increased venous pressure, or weakened vein walls. Risk factors: prolonged standing, pregnancy, obesity, family history. Complications: venous stasis ulcers, thrombophlebitis, bleeding. 2.6 Comparison of Blood Vessels Feature Arteries Capillaries Veins Wall thickness Thick Very thin (1 cell) Thin Tunica media Thick (smooth muscle + elastic) Absent Thin Lumen diameter Smaller than vein Smallest (5-10 um) Larger than artery Blood pressure High (80-120 mmHg) Low (20-40 mmHg) Very low (5-15 mmHg) Blood velocity Fast Very slow Slow Blood volume Low (~15%) Low (~5%) High (~60%) Valves None (except near heart) None Present (especially in limbs) Function Transport blood away from heart Exchange of gases, nutrients, wastes Return blood to heart; blood reservoir 2.7 Major Blood Vessels of the Body 2.7.1 Aorta and Major Arteries Ascending aorta: Gives rise to right and left coronary arteries. Aortic arch: — Brachiocephalic trunk -> right subclavian + right common carotid — Left common carotid artery — Left subclavian artery Thoracic aorta: Bronchial, esophageal, mediastinal, posterior intercostal arteries. Abdominal aorta: — Celiac trunk (liver, stomach, spleen) — Superior mesenteric artery (small intestine, proximal

Structure and functions of the heart
Anatomy

Structure and functions of the heart

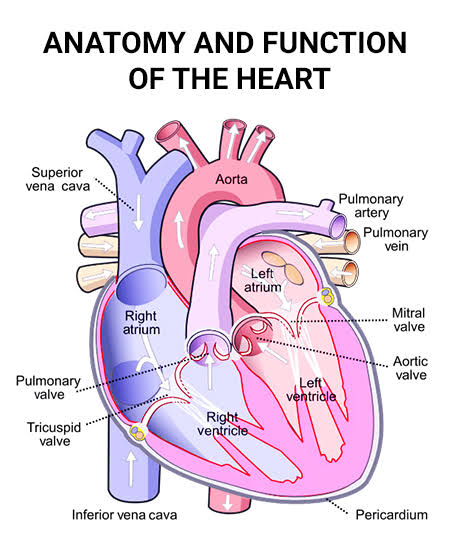
Structure and Functions of the Heart Complete study notes covering macroscopic and microscopic anatomy, the cardiac cycle, neurovascular supply, and physical examination correlations. 1. Introduction The heart is a hollow, muscular, cone-shaped organ located in the mediastinum, between the lungs. Approximately two-thirds of its mass lies to the left of the midline. It functions as a double pump maintaining continuous blood circulation through the pulmonary and systemic circuits. Key Parameters: Size: Approximately 12 cm long, 9 cm wide, 6 cm thick. Weight: Approximately 250-350 g in adult males; slightly less in females. Location: Posterior to the sternum, anterior to the vertebral column at levels T5-T8. Apex: Directed anteriorly, inferiorly, and to the left (located at the 5th intercostal space, midclavicular line). Base: Directed posteriorly, superiorly, and to the right. 2. Structure of the Heart 2.1 Pericardium The heart is enclosed within the pericardium, a double-walled sac consisting of two main layers: Fibrous pericardium: A tough, outer layer of dense connective tissue that prevents overfilling and anchors the heart to surrounding structures. Serous pericardium: Parietal layer: Lines the inner surface of the fibrous pericardium. Visceral layer (epicardium): Covers the external surface of the heart. Pericardial cavity: The potential space between the parietal and visceral layers containing 10-20 mL of serous fluid to reduce friction. 2.2 Heart Wall The heart wall consists of three distinct layers: Layer Name Characteristics Outer Epicardium Visceral layer of serous pericardium; contains coronary vessels, nerves, and adipose tissue. Middle Myocardium Cardiac muscle tissue; the thickest layer; responsible for the pumping action/contraction. Inner Endocardium Endothelium-lined; smooth surface that reduces friction and prevents blood clot formation; covers valves. 2.3 Chambers of the Heart The heart has four chambers: two atria (upper) and two ventricles (lower). Right Atrium: Receives deoxygenated blood from systemic circulation via the superior vena cava (head, neck, limbs), inferior vena cava (abdomen, pelvis, lower limbs), and coronary sinus (heart wall). Contains the fossa ovalis (remnant of fetal foramen ovale). Houses the sinoatrial (SA) node — the natural pacemaker. Right Ventricle: Receives blood from the right atrium via the tricuspid valve. Pumps blood through the pulmonary valve into the pulmonary trunk. Wall is thinner than the left ventricle as it pumps against low pulmonary resistance (15-30 mmHg). Contains the moderator band (septomarginal trabecula) carrying the right bundle branch. Left Atrium: Receives oxygenated blood from the lungs via four pulmonary veins (two from each lung). Smaller but thicker-walled than the right atrium. Left Ventricle: Receives oxygenated blood from the left atrium via the mitral (bicuspid) valve. Pumps blood through the aortic valve into the ascending aorta for systemic circulation. Wall is 2-3 times thicker than the right ventricle to pump against high systemic pressure (80-120 mmHg). Forms the apex of the heart. 3. Valves and Blood Flow 3.1 Atrioventricular (AV) Valves Tricuspid Valve (Right AV): Three cusps (anterior, posterior, septal). Prevents backflow to RA during ventricular systole. Mitral (Bicuspid) Valve (Left AV): Two cusps (anterior, posterior). Most commonly affected by rheumatic heart disease and mitral valve prolapse. Both are anchored by chordae tendineae to papillary muscles of the ventricles. 3.2 Semilunar Valves Pulmonary Valve: Three semilunar cusps. Located between RV and pulmonary trunk. Aortic Valve: Three semilunar cusps (right, left, non-coronary). Right and left coronary cusps give rise to the coronary arteries. Mechanism of Valve Closure AV valves close when ventricular pressure exceeds atrial pressure during systole. Chordae tendineae prevent the cusps from everting into the atria. Semilunar valves close when arterial pressure exceeds ventricular pressure during diastole. 3.3 Fibrous Skeleton of the Heart A dense connective tissue framework that: Provides attachment for valves and cardiac muscle fibers. Electrically insulates atria from ventricles. The AV bundle (Bundle of His) is the only normal electrical connection between atria and ventricles. 4. Coronary Circulation 4.1 Arterial Supply Right Coronary Artery (RCA): Arises from the right aortic sinus. Supplies the RA, most of the RV, SA node (in 60%), AV node (in 80%), and posterior 1/3 of the septum. Left Coronary Artery (LCA): Arises from the left aortic sinus. Divides into: Left Anterior Descending (LAD): Supplies anterior 2/3 of septum, apex; known as the “widow maker” when occluded. Circumflex artery: Supplies LA and lateral/posterior walls of the LV. Coronary Dominance Dominance is determined by which artery gives rise to the posterior interventricular artery (PDA). — Right-dominant (85%): PDA from RCA. — Left-dominant (10%): PDA from Circumflex. — Co-dominant (5%): PDA from both. 4.2 Venous Drainage Great cardiac vein: Accompanies LAD; drains into coronary sinus. Middle cardiac vein: Accompanies posterior interventricular artery. Coronary sinus: Drains into the right atrium (main venous return). 5. Functions and Physiology 5.1 The Cardiac Cycle Sequence of events in one heartbeat (~0.8 seconds at 75 bpm): Atrial Systole (0.1 sec): SA node fires; atria contract, forcing 20-30% of blood into ventricles (“atrial kick”). Isovolumetric Ventricular Contraction (0.05 sec): Ventricular pressure rises; AV valves close (S1 sound). All valves closed. Ventricular Ejection (0.25 sec): Pressure exceeds arterial pressure; semilunar valves open. SV is ~70 mL. Isovolumetric Ventricular Relaxation (0.08 sec): Semilunar valves close (S2 sound). All valves closed. Ventricular Filling (0.4 sec): AV valves open; blood flows passively from atria. 5.2 Heart Sounds Sound Timing Cause Clinical Significance S1 (Lubb) Beginning of systole Closure of AV valves Loud in mitral stenosis; soft in mitral regurgitation. S2 (Dubb) End of systole Closure of Semilunar valves Splitting: normal (A2 then P2 on inspiration). S3 Early diastole Rapid ventricular filling Normal in children; pathological in heart failure. S4 Late diastole Atrial contraction against stiff ventricle Indicates decreased compliance (HTN, AS). 5.3 Cardiac Output and Stroke Volume Cardiac Output (CO): Volume of blood pumped per minute (SV x HR). Normal: 4.0-8.0 L/min. Ejection Fraction (EF): Percentage of end-diastolic volume ejected. Normal: 55-70%. Factors Affecting Stroke Volume: Preload: Frank-Starling mechanism (increased venous return stretches muscle, increasing force). Contractility: Force of contraction (increased by Sympathetics, Digoxin). Afterload: Systemic vascular resistance (pressure the heart must pump against). 6. Conduction System Sinoatrial (SA) Node: Pace-maker; generates impulses at 60-100 bpm. Atrioventricular (AV) Node: Located in

Common blood disorders (Anaemia, Leukemia, Hemophilia)
Anatomy

Common blood disorders (Anaemia, Leukemia, Hemophilia)

Common Blood Disorders Complete study notes covering the classification, pathophysiology, investigation, and management of Anaemia, Leukemia, and Hemophilia. 4.1 ANAEMIA 4.1.1 Definition Anaemia is defined as a reduction in the oxygen-carrying capacity of blood due to decreased hemoglobin (Hb) concentration, reduced red blood cell (RBC) count, or low hematocrit levels relative to the physiological needs of the individual. 4.1.2 WHO 2024 Diagnostic Criteria The World Health Organization updated hemoglobin cutoffs in 2024 using systematic review and GRADE methodology. These thresholds are critical for clinical diagnosis: Population Hb Threshold (g/dL) Children 6-59 months <11.0 (revised to <10.5 for 6-23 months) Children 5-12 years <11.5 Non-pregnant women <12.0 Pregnant women (all trimesters) <11.0 Pregnant women (2nd trimester) <10.5 Men <13.0 Severity Classification (WHO): Mild: 10.0 — threshold Moderate: 7.0 — 9.9 Severe: <7.0 4.1.3 Classification by Morphology (MCV) Type MCV (fL) MCH (pg) Common Causes Microcytic hypochromic <80 fL <27 pg Iron deficiency, thalassemia, sideroblastic anemia, chronic disease Normocytic normochromic 80-100 fL 27-33 pg Acute blood loss, hemolytic anemia, chronic disease, aplastic anemia, renal failure Macrocytic >100 fL >33 pg B12 deficiency, folate deficiency, liver disease, alcoholism, hypothyroidism 4.1.4 Classification by Pathophysiology Decreased production: Iron deficiency, B12/folate deficiency, aplastic anemia, chronic disease, renal failure. Increased destruction (hemolysis): Sickle cell disease, thalassemia, autoimmune hemolytic anemia, G6PD deficiency, malaria. Blood loss: Trauma, menorrhagia, GI bleeding (peptic ulcer, hookworm, colorectal cancer). 4.1.5 Iron Deficiency Anaemia (IDA) Etiology: Chronic blood loss (menorrhagia, GI bleeding, hookworm infestation), inadequate dietary intake (vegetarian/vegan diets), malabsorption (celiac disease, gastrectomy), and increased demand (pregnancy, infancy, adolescence). Clinical Features: General: Pallor (conjunctival, palmar, tongue), fatigue, weakness, dizziness. Cardiovascular: Tachycardia, palpitations, systolic flow murmur, heart failure (severe). Epithelial: Angular cheilitis, glossitis, koilonychia (spoon-shaped nails), pica. Neurological: Headache, irritability, reduced work capacity. Investigations: CBC: Low Hb, low MCV, low MCH, low MCHC, high RDW. Peripheral smear: Microcytic, hypochromic RBCs; pencil cells; target cells. Iron studies: Low serum iron, low ferritin, high TIBC, low transferrin sat. Reticulocytes: Low or inappropriately normal. Management: Oral iron: Ferrous sulfate 200 mg TDS (or 65 mg elemental iron). Dietary advice: Iron-rich foods (red meat, leafy greens); Vitamin C enhances absorption. Treat underlying cause: Control bleeding, treat hookworm, manage menorrhagia. Parenteral iron: For malabsorption, intolerance, or non-compliance. Transfusion: Reserved for severe anemia (Hb <7 g/dL) with hemodynamic compromise. 4.1.6 Megaloblastic Anaemia Causes: — B12 deficiency: Pernicious anemia (autoimmune), gastrectomy, ileal disease, vegan diet. — Folate deficiency: Poor nutrition, alcoholism, malabsorption, pregnancy, hemolysis. Clinical Features: General anemia symptoms plus: B12 deficiency: Neurological — subacute combined degeneration of spinal cord: loss of vibration/position sense, ataxia, spasticity, dementia; glossitis. Folate deficiency: No neurological symptoms; neural tube defects in pregnancy. Investigations: CBC: Low Hb, high MCV (>100 fL), pancytopenia possible. Peripheral smear: Macrocytic RBCs, hypersegmented neutrophils (>5 lobes). B12/Folate level: Low (B12 <200 pg/mL; Folate <3 ng/mL). Anti-IF antibodies: Positive in pernicious anemia. IMPORTANT Never give folate alone if B12 deficiency is possible — it corrects the anemia but allows neurological damage to progress. 4.1.7 Sickle Cell Disease Autosomal recessive hemoglobinopathy (HbS). Point mutation in beta-globin gene (Glu -> Val at position 6). RBCs sickle under low oxygen, causing vaso-occlusion and hemolysis. Clinical: Painful crises, dactylitis, splenic sequestration, acute chest syndrome, stroke, priapism. Diagnosis: Hb electrophoresis. Management: Hydration, analgesia, oxygen, hydroxyurea, blood transfusion, penicillin prophylaxis in children. Key Clinical Pearls — Anaemia Always investigate the cause of iron deficiency in adult males and postmenopausal females — GI malignancy must be excluded. Never give folate alone if B12 deficiency is possible. Peripheral blood smear is essential for morphological classification. 4.2 LEUKEMIA 4.2.1 Definition Leukemia is a malignant neoplasm of hematopoietic stem cells characterized by uncontrolled proliferation of abnormal white blood cells (blasts) in the bone marrow and peripheral blood, with subsequent suppression of normal hematopoiesis. 4.2.2 Classification Classification Acute Chronic Myeloid Acute Myeloid Leukemia (AML) Chronic Myeloid Leukemia (CML) Lymphoid Acute Lymphoblastic Leukemia (ALL) Chronic Lymphocytic Leukemia (CLL) — Acute leukemias: Rapid onset, immature blasts (>20% in bone marrow), fatal without treatment. — Chronic leukemias: Insidious onset, more mature cells, slower progression. 4.2.3 Etiology and Risk Factors Genetic: Down syndrome (ALL risk 10-20x), Fanconi anemia, Bloom syndrome. Radiation: Atomic bomb survivors, therapeutic radiation. Chemicals: Benzene, alkylating agents, topoisomerase II inhibitors. Viruses: HTLV-1 — associated with adult T-cell leukemia/lymphoma. Prior chemo: Myelodysplastic syndrome progressing to AML. 4.2.4 Clinical Features Result from bone marrow failure and organ infiltration: System Manifestations General Fatigue, malaise, weight loss, fever, night sweats Anemia Pallor, dyspnea, tachycardia Infections Recurrent bacterial, viral, fungal infections (neutropenia) Bleeding Petechiae, ecchymoses, epistaxis, gingival bleeding (thrombocytopenia) Organomegaly Hepatomegaly, splenomegaly (especially CML, ALL) Lymphadenopathy Generalized lymph node enlargement (ALL, CLL) Bone pain Metaphyseal pain in children with ALL CNS Headache, cranial nerve palsies, meningismus (CNS involvement in ALL) Other Gum hypertrophy (AML M4/M5), skin infiltration (chloromas), testicular enlargement (ALL relapse) 4.2.5 Investigations CBC: Anemia, thrombocytopenia, high/low WBC; blasts may be seen. Peripheral blood smear: Blasts (large, high N:C ratio, fine chromatin, prominent nucleoli, Auer rods in AML). Bone marrow aspirate/biopsy: Hypercellular marrow with >20% blasts (diagnostic gold standard). Flow cytometry (immunophenotyping): Identifies cell lineage (CD3, CD7 = T-cell; CD19, CD20 = B-cell; CD13, CD33 = myeloid). Cytogenetics/Karyotyping: Philadelphia chromosome t(9;22) in CML; t(8;21), inv(16) in AML. Lumbar puncture: CSF cytology for CNS involvement (ALL). Chest X-ray: Mediastinal mass (T-cell ALL). 4.2.6 Management Chemotherapy: Induction, consolidation, maintenance; combination regimens (e.g., 7+3 for AML: cytarabine + anthracycline). Targeted therapy: Tyrosine kinase inhibitors (imatinib, dasatinib) for BCR-ABL1+. Immunotherapy: CAR-T cell therapy, blinatumomab (CD19-directed) for B-ALL. Stem cell transplant: Allogeneic transplant for high-risk or relapsed disease. Supportive care: Blood transfusions, infection prophylaxis, growth factors (G-CSF), tumor lysis syndrome prevention. Clinical Pearl Acute leukemia is a medical emergency. Tumor lysis syndrome can be fatal without prophylaxis (hydration, allopurinol, rasburicase). 4.3 HEMOPHILIA 4.3.1 Definition Hemophilia is a group of inherited bleeding disorders caused by deficiency of specific coagulation factors, resulting in impaired secondary hemostasis and prolonged bleeding. 4.3.2 Classification Type Deficient Factor Inheritance Incidence Hemophilia A (Classic) Factor VIII X-linked recessive 1 in 5,000-10,000 male births (80%) Hemophilia B (Christmas Disease) Factor IX

Scroll to Top