Doctors Revision

Author name: doctorsrevision@gmail.com

Transport Across Nephron Segments 1
Anatomy

Renal Clearance and Micturition

Renal Clearance & Micturition Systems Physiology: Renal Clearance & Micturition Unit: Systems Physiology Renal Clearance Clearance is a quantitative measure of how effectively the kidneys remove a particular substance from the blood plasma. It represents the hypothetical volume of plasma that would be completely cleared of a substance per unit of time. Mathematical Definition: The general formula for clearance (Cx) of any substance X is: Cx = (Ux * V) / Px Cx = Renal clearance of substance X (in mL/min or mL/s) Ux = Concentration of substance X in urine (e.g., mg/dL or mg/mL) V = Urine flow rate (e.g., mL/min) Px = Concentration of substance X in plasma (e.g., mg/dL or mg/mL) Interpretation of the Formula: (Ux * V) represents the excretion rate of substance X – the total amount of X removed from the body via urine per minute. Px represents the concentration of X in the “incoming” plasma. Thus, clearance essentially asks: “What volume of plasma must have been ‘purified’ to account for the amount of substance X excreted in the urine?” Relationship to Renal Handling: The amount of substance excreted is a net result of three processes: Excretion Rate = Filtration Rate – Reabsorption Rate + Secretion Rate Ux * V = (GFR * Px) – T_reabsorption + T_secretion GFR = Glomerular Filtration Rate T_reabsorption = Tubular reabsorption rate T_secretion = Tubular secretion rate Importance of Renal Clearance Renal clearance measurements are invaluable tools for assessing various aspects of renal function: Quantifying Glomerular Filtration Rate (GFR): The gold standard for measuring kidney function. Estimating Renal Plasma Flow (RPF): Gives insight into blood supply to the kidneys. Assessing Severity of Renal Damage: Decreased GFR and RPF can indicate kidney disease progression. Characterizing Tubular Reabsorption: By comparing a substance’s clearance to GFR, we can determine if it’s reabsorbed. Characterizing Tubular Secretion: Similarly, by comparison to GFR, we can determine if a substance is secreted. Clearance Tests: Endogenous vs. Exogenous Markers Endogenous Markers Substances naturally produced by the body. Creatinine: Clinically most common for GFR estimation. Urea: Not a good GFR marker due to significant reabsorption. Uric Acid: Significant reabsorption and secretion. Exogenous Markers Substances administered externally for diagnostic purposes. Inulin: The gold standard for GFR research. Para-aminohippuric acid (PAH): Gold standard for RPF measurement. Diodrast: Similar properties to PAH, historically used for RPF. Measurement of Glomerular Filtration Rate (GFR) GFR is the volume of fluid filtered from the glomerular capillaries into Bowman’s capsule per unit time. It’s the best overall index of kidney function. Criteria for an Ideal GFR Marker: An ideal substance for measuring GFR must possess the following characteristics: Freely Filtered: It must pass unimpeded across the glomerular filtration barrier. Not Reabsorbed: No reabsorption from the renal tubules back into the blood. Not Secreted: No secretion from the blood into the renal tubules. Not Metabolized: It should not be broken down by the kidneys or other tissues. Not Stored: Should not accumulate in the body. Not Protein Bound: If bound, only the free fraction is filtered. Physiologically Inert/Non-toxic: Should not affect renal function or be harmful. Easily Measured: Detectable in plasma and urine with reliable assays. 1. Inulin Clearance: The Gold Standard for Research GFR Properties: Perfectly fits all criteria for an ideal GFR marker. It is a polysaccharide, freely filtered, and neither reabsorbed nor secreted. Method: Requires continuous intravenous infusion to maintain a steady plasma concentration. Urine is collected over a timed period. Limitation: It is exogenous and requires continuous infusion, making it impractical for routine clinical use. Calculation Example: Assume: – [inulin]urine = 30mg/ml – [inulin]plasma = 0.5mg/ml – Urine flow rate = 2ml/ml GFR = 120ml/min 2. Creatinine Clearance: The Clinical Standard for GFR Estimation Properties: Endogenously produced by muscle metabolism at a relatively constant rate. Freely filtered at the glomerulus. A small amount is secreted by the proximal tubule (error 1: amount excreted > amount filtered). This means creatinine clearance slightly overestimates true GFR. Analytical Interference: Older spectrophotometric methods (e.g., Jaffe reaction) detect chromogens other than true creatinine, leading to an overestimation of plasma creatinine concentration (error 2). Clinical Utility: Convenience: Does not require intravenous infusion. Can be estimated from a 24-hour urine collection or, more commonly, estimated from serum creatinine using prediction equations (e.g., Cockcroft-Gault, MDRD, CKD-EPI). Fortuitous Cancellation of Errors: In healthy individuals, the overestimation of GFR due to secretion is often roughly canceled out by the overestimation of plasma creatinine by older assays. However, this balance is disturbed in kidney disease, extreme muscle mass, or with certain medications. General Principle: Relating Clearance to Renal Handling The comparison of a substance’s clearance (Cx) with the GFR (measured by Cinulin or estimated by Ccreatinine) provides insight into how the kidney handles that substance: If Cx = Cinulin (or GFR): The substance is only filtered (not reabsorbed, not secreted). Example: Inulin. If Cx < Cinulin (or GFR): The substance is filtered and net reabsorbed by the renal tubules. The kidneys remove less of the substance from the plasma than the volume of plasma filtered. Example: Glucose (normally 100% reabsorbed, so clearance is 0 unless plasma glucose exceeds tubular maximum), sodium, urea. Note: If a substance is completely reabsorbed (e.g., glucose at normal plasma levels), its clearance is effectively 0. If Ux * V = 0, then Cx = 0. If Cx > Cinulin (or GFR): The substance is filtered and net secreted by the renal tubules. The kidneys remove more of the substance from the plasma than the volume of plasma filtered. This indicates that the tubules are actively adding the substance to the urine. Example: PAH, creatinine (to a small extent). Measurement of Renal Plasma Flow (RPF) RPF is the volume of plasma flowing through the kidneys per unit time. Ideal RPF Marker Criteria: An ideal substance for measuring RPF must be: Freely Filtered. Completely Secreted: All of the substance that enters the renal artery (both filtered and non-filtered) must be removed by either filtration or tubular secretion in a single pass through the kidney. Not Reabsorbed. Not Metabolized
Renal Physiology and Renal Haemodynamics
Anatomy

Renal Physiology and Renal Haemodynamics

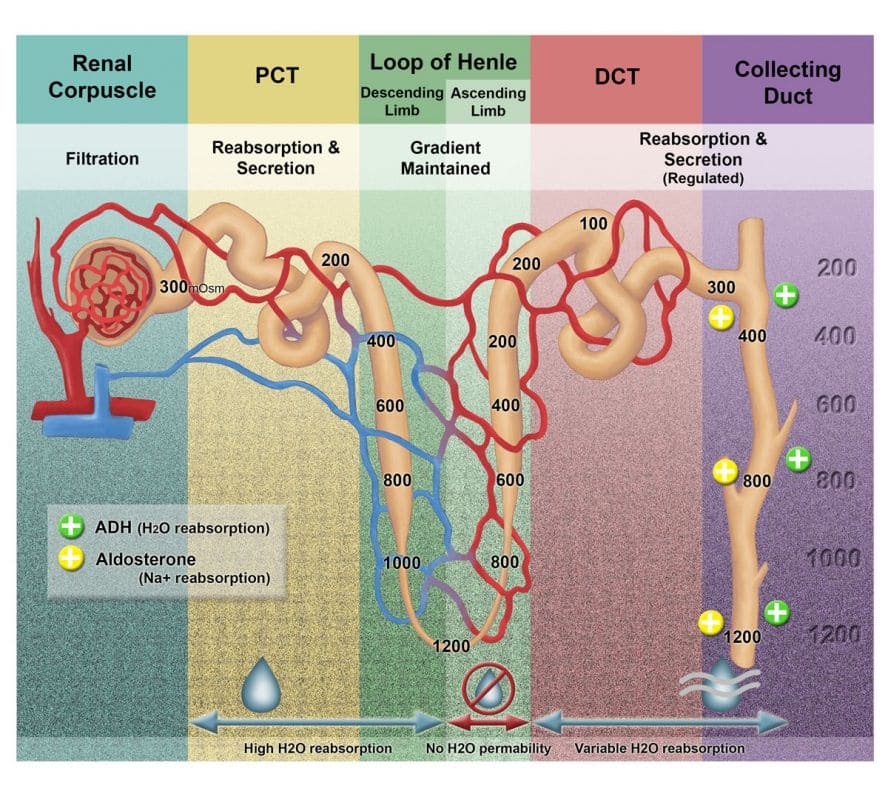
Haemodynamics GFR & Diuretics Systems Physiology: Kidneys, Filtration, GFR & Starling Forces RENAL PHYSIOLOGY Functional Anatomy of the Kidneys The urinary system is a vital organ system responsible for filtering blood, maintaining fluid and electrolyte balance, and excreting waste products. Components of the Urinary System Paired Kidneys: These are the primary organs, responsible for blood filtration and urine formation. A Ureter for Each Kidney: Muscular tubes that transport urine from the kidneys to the urinary bladder. Urinary Bladder: An expandable muscular sac that stores urine until it’s expelled from the body. Urethra: A tube that carries urine from the bladder to the outside of the body. Main Functions of the Urinary System Blood Filtration and Waste Excretion: Filter blood: They continuously process blood, removing unwanted substances. Dispose of nitrogenous wastes: These are toxic byproducts of protein metabolism. Urea: The most abundant nitrogenous waste, formed from ammonia in the liver. Uric acid: A byproduct of nucleic acid metabolism. Creatinine: A waste product from muscle metabolism (creatine phosphate breakdown). Remove other toxins: Including drugs, environmental toxins, and various metabolic byproducts. Eliminate excess water and ions: Maintaining appropriate body fluid volume and electrolyte concentrations. Regulation of Homeostasis: Regulate the balance of water and electrolytes: Essential for maintaining cell volume, nerve impulse transmission, and muscle contraction. Regulate acid-base balance: By excreting hydrogen ions and reabsorbing bicarbonate ions, the kidneys play a crucial role in maintaining blood pH. Endocrine Functions (Hormone Production): Erythropoietin (EPO): Stimulates red blood cell production in the bone marrow in response to hypoxia. Renin: An enzyme that initiates the Renin-Angiotensin-Aldosterone System (RAAS), which regulates blood pressure and fluid balance. Activation of Vitamin D: Converts inactive vitamin D into its active form (calcitriol), essential for calcium absorption and bone health. Gross Anatomy of the Kidneys Location: Retroperitoneal organs: This means they are located posterior to the parietal peritoneum, against the posterior abdominal wall. This is a key anatomical landmark. Superior lumbar region: Extending from the T12 to L3 vertebrae. The right kidney is often slightly lower than the left due to the presence of the liver. Shape and Orientation: Bean-shaped: With a characteristic convex lateral surface and a concave medial surface. Hilus (or Hilum): This is the prominent indentation on the medial surface. It serves as the entry and exit point for the renal artery, renal vein, nerves, and the ureter. Associated Structures: Adrenal glands (Suprarenal glands): These endocrine glands sit superior to each kidney, but are functionally separate from the kidneys. Internal Anatomy of the Kidney: Macroscopic Structure Upon dissection, the kidney reveals two main regions and further subdivisions: Renal Cortex (Outer Region): Lighter in color, granular texture. Renal Columns: Extensions of the cortex that project down into the medulla, dividing it into distinct pyramid-shaped sections. These columns contain blood vessels and parts of the nephrons. Renal Medulla (Inner Region): Darker, cone-shaped structures. Renal Pyramids (Medullary Pyramids): 8-18 cone-shaped masses, with their bases facing the cortex and their apices (renal papillae) pointing towards the renal pelvis. These contain parallel bundles of urine-collecting tubules and loops of Henle. Renal Papilla: The apex of each renal pyramid, from which urine drains into a minor calyx. Renal Lobe: Consists of a renal pyramid and the cortical tissue surrounding it (the renal column on either side and the cortical tissue overlying its base). Number: 5-11 lobes per kidney. Each lobe functions somewhat independently in urine production. Collecting System: Minor Calyx (plural: Calices): Cup-shaped structures that collect urine directly from the renal papillae of individual pyramids. Major Calyx: Two or three minor calices merge to form a major calyx. Renal Pelvis: The expanded, funnel-shaped superior part of the ureter. It is formed by the convergence of the major calices and acts as a reservoir for urine before it enters the ureter. Blood Supply to the Kidneys The kidneys receive a disproportionately large blood supply (about 20-25% of cardiac output) due to their role in blood filtration. Cortex receives >90%. Aorta: The abdominal aorta gives rise to the right and left renal arteries. Renal Artery: Enters the kidney at the hilus. Segmental Arteries: Within the hilus, the renal artery typically divides into 5 segmental arteries. Interlobar Arteries: Segmental arteries branch into interlobar arteries, which pass through the renal columns between the renal pyramids, extending towards the cortex. Arcuate Arteries: At the junction of the medulla and cortex (the corticomedullary junction), the interlobar arteries arch over the bases of the pyramids to become arcuate arteries. Cortical Radiate Arteries (Interlobular Arteries): Arcuate arteries give off numerous cortical radiate arteries that project into the cortex. Afferent Arterioles: Each cortical radiate artery gives rise to numerous afferent arterioles, which supply blood to individual glomeruli. The Unique Renal Vasculature Glomerular Capillary Bed Afferent Arteriole: Carries blood to the glomerulus. Larger in diameter, bringing blood to the glomerulus. Efferent Arteriole: Carries blood away from the glomerulus. Smaller in diameter, carrying blood away from the glomerulus. This is distinct from most capillary beds, which drain into venules. SIGNIFICANCE: The difference in diameter between the afferent and efferent arterioles creates resistance to blood flow, maintaining the high hydrostatic pressure within the glomerulus. This high pressure is the primary driving force for glomerular filtration, literally “forcing” filtrate out of the blood. Two Capillary Beds in Series This is a defining feature of the renal circulation: Glomerulus: The first capillary bed, specialized for filtration. Peritubular Capillaries (or Vasa Recta): The second capillary bed, arising from the efferent arteriole, specialized for reabsorption and secretion. A. Peritubular Capillaries Origin: Arise from the efferent arterioles. Location: Primarily surround the PCT and DCT in the renal cortex. Structure: Low-pressure, porous capillaries. Function: Specialized for reabsorption, readily taking up water, solutes, and nutrients that are reabsorbed by the tubule cells. They also play a role in secretion. B. Vasa Recta Specific Portion of Peritubular Capillary System. Long, straight capillaries that extend deep into the medulla, running parallel to the loops of Henle of juxtamedullary nephrons. They are crucial for maintaining the medullary osmotic gradient. Function: The Vasa Recta acts as a

LOWER RESPIRATORY TRACT 1
Anatomy

Lower Respiratory Anatomy

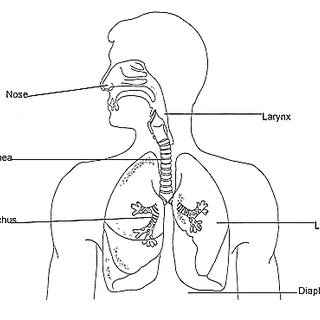
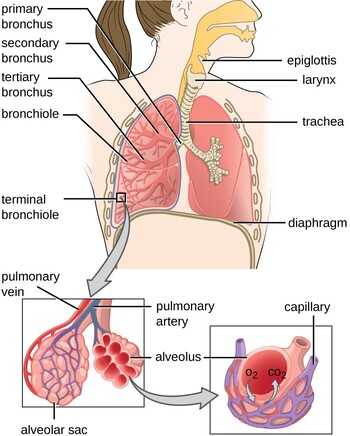
Lower Respiratory Anatomy Systems Anatomy: Lower Respiratory Tract Lower Respiratory Tract Overview The lower respiratory tract is responsible for conducting air deep into the lungs and for the vital process of gas exchange. It begins immediately inferior to the larynx. Components: It consists of the trachea, the main bronchi (primary, secondary, tertiary), progressively smaller bronchioles, and ultimately the microscopic alveolar sacs (which contain alveoli). Functional Unit: The lungs are the primary organs of respiration, formed by the branching bronchial tree culminating in the respiratory bronchioles, alveolar ducts, and alveolar sacs, all encased within pleural membranes. The statement “Bronchioles and alveolar sacs collectively form lungs” is an oversimplification; the lungs also include the larger bronchi, blood vessels, nerves, lymphatic tissue, and connective tissue. Functions: Air Conduction: Transporting inhaled air from the upper respiratory tract to the alveoli, and exhaled air in the opposite direction. Respiration (Gas Exchange): Facilitating the exchange of oxygen and carbon dioxide between the air in the alveoli and the blood in the pulmonary capillaries. Trachea The trachea, or windpipe, is a crucial component of the lower respiratory tract, providing a patent pathway for air to and from the lungs. Structure: It is a mobile, flexible fibrocartilaginous and membranous tube. Origin: It begins in the neck as a direct continuation of the larynx, specifically at the inferior border of the cricoid cartilage, typically at the level of the C6 vertebra. Course: It descends anterior to the esophagus, initially in the midline of the neck, and then slightly deviates in the thorax. Termination: The trachea terminates in the thorax by bifurcating into the right and left main (principal) bronchi. This bifurcation point is known as the carina. Anatomical Landmark: The carina is located approximately at the level of the sternal angle anteriorly, and between the T4 and T5 vertebral bodies posteriorly. Structure of the Trachea The unique structure of the trachea is adapted for its function of maintaining an open airway while allowing some flexibility. Cartilaginous Support: The trachea is supported by 16-20 C-shaped (incomplete) cartilaginous rings, primarily composed of hyaline cartilage. These rings are crucial for keeping the tracheal lumen continuously patent, preventing collapse during inspiration or changes in neck position. Posterior Deficiency: The tracheal rings are deficient posteriorly. This allows the trachea to flatten slightly against the esophagus during swallowing, facilitating the passage of food. Trachealis Muscle: The posterior, open ends of the C-shaped cartilages are connected by the trachealis muscle, a band of smooth muscle. Function: Contraction of the trachealis muscle can narrow the tracheal lumen, which is important during coughing to increase the velocity of air expulsion, aiding in clearing mucus and foreign material. Shape of Lumen: Due to the posterior trachealis muscle, the trachea’s lumen is not perfectly circular but rather slightly D-shaped or flattened posteriorly. The statement “the posterior wall of the trachea is flat” accurately describes this. Dimensions: Adults: The average diameter of the trachea in adults is about 2.5 cm (1 inch). The length is typically 10-12 cm. Infants: In infants, the tracheal diameter is much smaller, roughly equivalent to the diameter of a pencil (or the child’s little finger), making them more susceptible to airway obstruction. Histology of the Trachea The tracheal wall is composed of several layers, each contributing to its function: Mucosa: Epithelium: Lined by pseudostratified ciliated columnar epithelium with abundant goblet cells. This is characteristic respiratory epithelium. Cilia: Beat synchronously to propel mucus and trapped particles upwards, towards the pharynx. Goblet Cells: Produce mucus, which traps inhaled dust, pollen, and microorganisms. Lamina Propria: A layer of loose connective tissue rich in elastic fibers, lymphoid cells, and mucous glands. Submucosa: Contains seromucous glands (tubular mucous glands in the original description) that supplement the mucus produced by goblet cells, along with blood vessels and nerves. Cartilaginous Layer: Composed of the C-shaped hyaline cartilage rings. Adventitia: The outermost layer of connective tissue, blending with surrounding tissues. Function: The mucociliary escalator system (ciliated epithelium + mucus) is a critical defense mechanism, continuously trapping and moving inhaled foreign particles and pathogens out of the lower respiratory tract, preventing them from reaching the delicate alveoli. Relations of the Trachea Understanding the anatomical relations of the trachea is vital, especially in surgical procedures involving the neck and mediastinum. A. Cervical Trachea (in the Neck) Anteriorly: Skin, superficial fascia, deep cervical fascia (investing layer). Infrahyoid Muscles: Sternohyoid and sternothyroid muscles. Thyroid Gland Isthmus: Typically lies anterior to the 2nd, 3rd, and 4th tracheal rings. Vascular Structures: Inferior thyroid veins (form a plexus), jugular venous arch, and sometimes the thyroidea ima artery (an anomalous artery arising from the brachiocephalic trunk or aorta). In Children: The left brachiocephalic vein (innominate vein) is higher and may be more anteriorly related to the trachea. Posteriorly: Esophagus: The trachea is always anterior to the esophagus. Recurrent Laryngeal Nerves: These nerves ascend in the tracheoesophageal grooves on either side. Laterally: Thyroid Gland Lobes: The lateral lobes of the thyroid gland lie on either side of the trachea. Carotid Sheath Contents: Common carotid artery, internal jugular vein, and vagus nerve are located lateral to the trachea, within their respective carotid sheaths. B. Thoracic Trachea (in the Thorax) Anteriorly: Manubrium of Sternum. Thymus: In children, the thymus gland is prominent. Major Vessels: Arch of aorta (initially to the left, then over the trachea), brachiocephalic trunk, left common carotid artery, left subclavian artery, left brachiocephalic vein. Posteriorly: Esophagus: Continues its posterior relation. Right Side: Right vagus nerve, azygos vein, right pleura. Left Side: Arch of aorta, left common carotid artery, left subclavian artery, left vagus nerve, left recurrent laryngeal nerve, left pleura. Neurovascular Supply & Lymph Drainage of the Trachea A. Nerve Supply Sensory Innervation: Primarily supplied by branches of the vagus nerves (CN X) and the recurrent laryngeal nerves. These nerves convey sensory information (e.g., irritation, cough reflex) from the tracheal mucosa. Autonomic Innervation: Parasympathetic (Vagus/Recurrent Laryngeal): Stimulates tracheal gland secretion and smooth muscle contraction (trachealis muscle). Sympathetic (Sympathetic Trunks): Causes bronchodilation and inhibits glandular secretion (less significant in trachea than bronchioles).

Respiratory System
Anatomy

Upper Respiratory Anatomy

Upper Respiratory Anatomy Systems Anatomy: Respiratory Tract UNIT: SYSTEMS ANATOMY Respiratory Tract The respiratory tract is the pathway for air, comprising structures that transport, filter, warm, and humidify air for gas exchange in the lungs. It is divided into the upper (nose, nasal cavity, pharynx, larynx) and lower (trachea, bronchi, bronchioles, alveoli) tracts. Key functions include oxygenating blood and removing carbon dioxide. The respiratory system is functionally and anatomically divided into two main parts: Upper Respiratory Tract (URT) Extends from the external nares (nostrils) to the larynx (voice box). Includes the nose (external nose and nasal cavity), pharynx (throat), and larynx. Primary Functions: Air Conditioning: Crucial for cleaning, warming, and humidifying inhaled air before it reaches the delicate lower airways and lungs. Olfaction (Smell): Specialized receptors in the nasal cavity detect odors. Resonance for Speech: The nasal cavity and paranasal sinuses act as resonating chambers for the voice. Protection: Filters out airborne particles and pathogens. Aesthetics: The external nose significantly contributes to facial appearance. Weight Reduction of Skull: The air-filled paranasal sinuses lighten the skull. Lower Respiratory Tract (LRT) Extends from the trachea (windpipe) down to the alveoli (air sacs) within the lungs. Includes the trachea, bronchi, bronchioles, and lungs (which contain respiratory bronchioles, alveolar ducts, and alveoli). Primary Functions: Air Conduction: Structures like the trachea and bronchi act as passageways for air. Gas Exchange (Respiration): The respiratory bronchioles and, most importantly, the alveoli are the primary sites where oxygen enters the blood and carbon dioxide leaves it. Some classifications might place the larynx, its lower part (below the vocal cords) as part of the LRT from a functional airway perspective. However, anatomically, it’s consistently taught as the lowest structure of the URT. Upper Respiratory Tract The upper respiratory tract (URT) comprises the nose, nasal cavity, sinuses, pharynx, and larynx, acting as the primary entry point for air, which it filters, warms, and humidifies. The Nose The nose is the most prominent anterior structure of the face, serving multiple vital roles. Functions of the Nose: Olfaction (Smell): Houses olfactory receptors. Respiration: Provides the primary entry point for air into the respiratory system. Air Conditioning: Cleans, warms, and humidifies inspired air. Voice Resonance: Contributes to the timbre of the voice. Aesthetics: A key determinant of facial appearance. Divisions: The nose is divided into the external nose and the nasal cavity. External Nose This is the visible part of the nose, projecting from the face. Its shape and size vary significantly among individuals due to genetics, sex, and ethnicity. Key Features: Root: The superior attachment of the nose to the forehead. Bridge: The superior, bony part of the nose. Dorsum Nasi: The anterior border from the root to the apex. Apex (Tip): The free, rounded end of the nose. Nares (Nostrils): The two external openings of the nasal cavity, separated by the nasal septum. Alae Nasi: The flared, cartilaginous expansions that form the lateral boundaries of the nares. Framework of the External Nose The external nose is supported by a combination of bone and hyaline cartilage. Bony Framework (Superior Part – “Bridge”): Nasal Bones (paired): Form the superior part of the bridge. Frontal Processes of Maxillae (paired): Extend upwards along the sides of the nasal bones. Nasal Part of Frontal Bone: Forms the root of the nose. Cartilaginous Framework (Inferior Part – “Apex and Alae”): These are plates of hyaline cartilage that provide flexibility and shape. Septal Nasal Cartilage: Forms the anterior part of the nasal septum, extending from the perpendicular plate of the ethmoid bone and vomer, maintaining the midline structure. Lateral Nasal Cartilages (paired): Located superior to the major alar cartilages, contributing to the side walls of the nose. Major Alar Cartilages (paired): Form the apex and alae of the nose. Each has: Medial Crus: Forms part of the mobile nasal septum. Lateral Crus: Forms the ala of the nose. Minor Alar Cartilages (variable): Small, accessory cartilages within the alae. Alar Fibrofatty Tissue: Connective tissue and fat that contribute to the shape and flexibility of the alae, especially in the most inferior part. Summary of Support: Bones: Support the upper one-third (bridge). Upper Cartilages (Lateral Nasal): Support the sides of the mid-nose. Lower Cartilages (Major Alar): Primarily support the tip and help define the shape and patency of the nostrils. Skin and connective tissue: Also contribute to the overall shape and covering. Nasal Cavity The nasal cavity is the internal space within the external nose, extending posterior to the pharynx. Boundaries: Anteriorly: Communicates with the exterior via the nares (nostrils). Posteriorly: Opens into the nasopharynx via the choanae (posterior nasal apertures). Walls of the Nasal Cavity: Floor: Formed primarily by the hard palate (maxilla and palatine bones) and, to a lesser extent, the anterior part of the soft palate. This separates the nasal cavity from the oral cavity. Roof: Narrow and arched, composed of several bones: Nasal Bone: Anteriorly. Frontal Bone: Anteriorly, between the nasal bones and ethmoid. Cribriform Plate of Ethmoid Bone: Mid-portion, perforated by olfactory nerve filaments. This is a critical anatomical landmark as it is thin and can be damaged. Body of Sphenoid Bone: Posteriorly. Medial Wall (Nasal Septum): Divides the nasal cavity into right and left halves. It has both bony and cartilaginous components: Bony Parts: Perpendicular Plate of Ethmoid Bone: Forms the superior posterior part. Vomer: Forms the inferior posterior part. Cartilaginous Part: Septal Nasal Cartilage: Forms the anterior superior part, making up a significant portion of the septum. (Add: “Vomeronasal cartilage” is often a historical or minor finding; focus on the main three components for clarity.) Lateral Wall: Complex and irregular, characterized by three shelf-like bony projections: Superior Nasal Concha (Turbinate): Part of the ethmoid bone. Middle Nasal Concha (Turbinate): Part of the ethmoid bone. Inferior Nasal Concha (Turbinate): A separate bone, not part of the ethmoid. These conchae increase the surface area of the nasal cavity and create turbulent airflow, facilitating air conditioning. Nasal Meatus (Air Passages): These are the spaces inferior to each concha. Spheno-ethmoidal Recess: Location: A small area located

Common Disorders of Tissues (1)
Anatomy

Common Disorders of Tissues

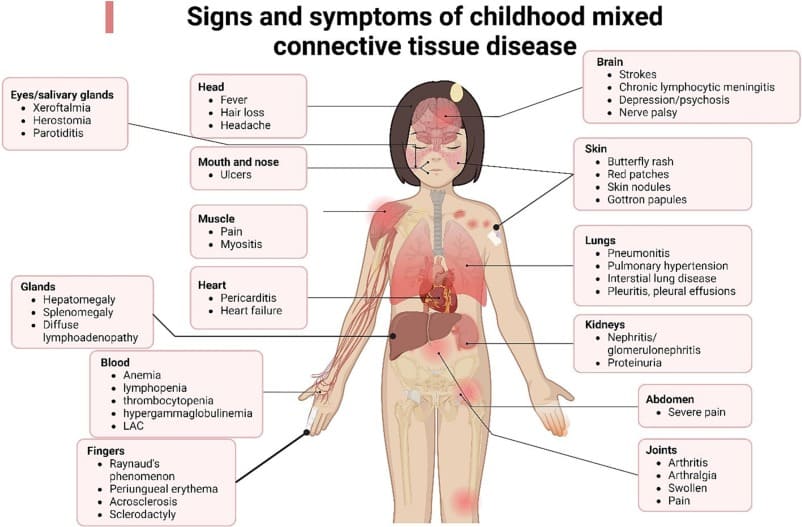
Common Disorders of Tissues Pathology Reference: Common Disorders of Tissues TISSUE PATHOLOGY Common Disorders of Tissues Connective tissues are one of the four basic types of animal tissue (along with epithelial, muscle, and nervous tissues). They are the most abundant and widely distributed of the primary tissues, playing a crucial role in binding, supporting, and protecting organs, as well as storing energy and providing immunity. Unlike epithelial tissue, which is primarily composed of cells, connective tissue is characterized by its extracellular matrix (ECM). Key Characteristics of Connective Tissues: Abundant Extracellular Matrix (ECM): This is the distinguishing feature. The ECM consists of two main components: Ground Substance: An amorphous gel-like material that fills the space between cells and fibers. It can be fluid, semi-fluid, gelatinous, or calcified. It contains water, proteoglycans, and glycoproteins. Protein Fibers: Provide strength and elasticity. Collagen fibers: Strongest and most abundant, providing high tensile strength (resistance to stretching). Elastic fibers: Composed of elastin, providing elasticity and recoil. Reticular fibers: Fine, branching collagenous fibers that form delicate networks, providing support in soft organs. Relatively Few Cells: Compared to epithelial tissue, connective tissues generally have fewer cells, which are often widely dispersed within the ECM. Vascularity: Most connective tissues are highly vascular (rich blood supply), though there are notable exceptions (e.g., cartilage is avascular, tendons and ligaments have limited vascularity). No Free Surface: Unlike epithelial tissue, connective tissue does not have a free surface exposed to the environment. Diverse Functions: Support, binding, protection, insulation, transport, and energy storage. Major Types of Connective Tissues and Their Functions Connective tissues are broadly categorized into several types, each with specialized functions and compositions of cells and ECM. A. Loose Connective Tissue (Areolar, Adipose, Reticular) These tissues have a relatively open, loose arrangement of fibers and a more abundant ground substance. 1. Areolar Connective Tissue Description: The most widely distributed connective tissue. It has a gel-like matrix with all three fiber types (collagen, elastic, reticular) loosely interwoven. Contains various cell types, including fibroblasts (most common), macrophages, mast cells, and some white blood cells. Location: Underlies epithelia; forms lamina propria of mucous membranes; packages organs; surrounds capillaries. Functions: Support and cushion: Provides flexible support. Fluid reservoir: Holds tissue fluid, acting as a “sponge.” Immunity: Plays a role in inflammation due to its high cell diversity. Binding: Connects skin to underlying structures. 2. Adipose Tissue (Fat Tissue) Description: Primarily composed of adipocytes (fat cells), which store triglycerides. These cells are so large that they push the nucleus and cytoplasm to the periphery, giving them a “signet ring” appearance. Very little ECM. Location: Under skin (subcutaneous), around kidneys and eyeballs, within abdomen, breasts. Functions: Energy storage: Primary site for long-term energy reserves. Insulation: Reduces heat loss through the skin. Protection/Cushioning: Protects organs from mechanical shock. Endocrine function: Produces hormones like leptin. 3. Reticular Connective Tissue Description: Contains a delicate network of reticular fibers (a type of collagen) in a loose ground substance. Reticular cells (a type of fibroblast) are prominent. Location: Lymphoid organs (lymph nodes, spleen, bone marrow), liver. Functions: Structural support (Stroma): Forms a soft internal framework (stroma) that supports blood cells, lymphocytes, and other cell types in lymphoid organs. B. Dense Connective Tissue These tissues have a high density of collagen fibers, providing significant strength. There is less ground substance and fewer cells than loose connective tissue. 1. Dense Regular Connective Tissue Description: Primarily parallel collagen fibers, providing great tensile strength in one direction. Fibroblasts are the main cell type, squeezed between collagen bundles. Poorly vascularized. Location: Tendons (muscle to bone), ligaments (bone to bone), aponeuroses (sheet-like tendons). Functions: Strong attachment: Connects muscles to bones (tendons) and bones to bones (ligaments). Resists unidirectional pull: Withstands great tensile stress when pulling force is applied in one direction. 2. Dense Irregular Connective Tissue Description: Primarily irregularly arranged collagen fibers. Some elastic fibers and fibroblasts. Provides tensile strength in multiple directions. Location: Dermis of the skin, fibrous capsules of organs and joints, submucosa of digestive tract. Functions: Structural strength: Withstands tension exerted in many directions. Protection: Forms protective capsules around organs. 3. Elastic Connective Tissue Description: Predominantly elastic fibers, allowing for significant stretch and recoil. Also contains some collagen fibers and fibroblasts. Location: Walls of large arteries (aorta), bronchial tubes, vocal cords, ligaments associated with vertebral column (ligamentum nuchae). Functions: Elasticity: Allows recoil of tissue following stretching. Pulsatile flow: Maintains pulsatile flow of blood through arteries; aids passive recoil of lungs following inspiration. C. Cartilage A specialized, semi-rigid connective tissue. It is avascular (lacks blood vessels) and aneural (lacks nerves), relying on diffusion from surrounding perichondrium for nutrients. Chondrocytes (cartilage cells) reside in lacunae (small cavities) within a solid, yet flexible, matrix. 1. Hyaline Cartilage Description: Most abundant type. Amorphous but firm matrix; imperceptible collagen fibers (type II); chondroblasts produce the matrix and, when mature, lie in lacunae as chondrocytes. Location: Covers the ends of long bones in joint cavities (articular cartilage), costal cartilage (ribs to sternum), nose, trachea, larynx. Functions: Support and cushioning: Supports and reinforces. Resilient cushioning: Has resilient properties. Reduces friction: Resists compressive stress at joints. 2. Elastic Cartilage Description: Similar to hyaline cartilage, but contains abundant elastic fibers in the matrix. Location: External ear (pinna), epiglottis. Functions: Flexibility and shape retention: Maintains the shape of a structure while allowing great flexibility. 3. Fibrocartilage Description: Matrix similar to hyaline cartilage but less firm, with thick collagen fibers (type I) predominant. Rows of chondrocytes alternating with thick collagen fibers. Location: Intervertebral discs, pubic symphysis, menisci of the knee. Functions: Tensile strength: Possesses tensile strength with the ability to absorb compressive shock. Shock absorption: Acts as a strong shock absorber. D. Bone (Osseous Tissue) A hard, rigid connective tissue. It is highly vascular and well-innervated. The hard matrix is primarily composed of collagen fibers and inorganic calcium salts (hydroxyapatite). Osteocytes (bone cells) reside in lacunae within the matrix. Description: Hard, calcified matrix containing many collagen fibers; osteocytes in lacunae. Very well vascularized. Functions: Support and protection, Leverage for movement (provides levers for muscles), Mineral storage

Mutations, Genetic Disorders, and Malignancy
Anatomy

Mutations, Genetic Disorders, and Malignancy

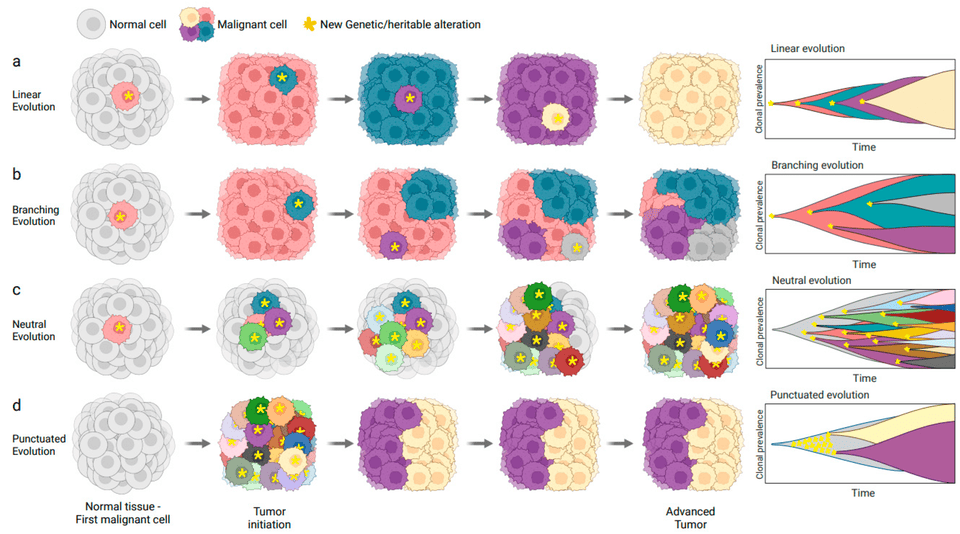
Mutations, Genetic Disorders & Malignancy Pathology: Mutations, Genetic Disorders, and Malignancy CELLULAR PATHOLOGY Mutations, Genetic Disorders & Malignancy At the heart of every living organism, from the simplest bacterium to the most complex human, lies the cell. Within each cell, the nucleus houses the genome – a meticulously organized instruction manual written in DNA. This manual dictates everything from cell structure and function to growth, division, and death. When this blueprint is altered, or when the cellular machinery designed to read and execute its instructions malfunctions, the consequences can range from subtle inefficiencies to devastating diseases. Our focus in this section is to lay down the precise definitions of three fundamental categories of cellular disorders: Mutations, Genetic Disorders, and Malignancy (Cancer). While intimately linked, they represent distinct levels of biological organization and clinical presentation. Understanding their individual definitions and how they relate to one another is crucial for grasping cellular pathology. Defining Key Terms A. Mutation Definition: A mutation is defined as a heritable change in the nucleotide sequence of the genetic material (DNA or RNA in some viruses). This change can involve a single base pair, a segment of a chromosome, or an entire chromosome. Mutations are the ultimate source of all genetic variation and serve as the raw material for evolution. However, they are also the primary cause of many diseases. Key Characteristics: Fundamental Unit of Change: A mutation is the most granular level of alteration in the genetic code. It’s a change to the DNA itself. Heritable: The change must be capable of being passed on to daughter cells during cell division (mitosis) or to offspring (meiosis, if in germ cells). Random Occurrence: Mutations are generally random events, not occurring in anticipation of beneficial or harmful effects. Variability in Impact: The consequences of a mutation can be: Neutral (Silent): No change in protein function or phenotype. Beneficial: Rare, providing an evolutionary advantage. Harmful (Pathogenic): Leading to disease or impaired function. Context: Mutations can occur in any cell of the body. Germline Mutations: Occur in germ cells (sperm or egg) and are heritable, meaning they can be passed down to offspring. Somatic Mutations: Occur in somatic cells (body cells) after conception. They are not heritable but can contribute to diseases in the affected individual, most notably cancer. B. Genetic Disorder Definition: A genetic disorder is a disease caused, in whole or in part, by a change in an individual’s DNA sequence. These disorders arise directly from specific mutations or abnormalities in the genome. The presence of these genetic alterations leads to an abnormal or absent gene product (protein), which in turn disrupts normal cellular function and manifests as a disease. Key Characteristics: Etiology: The primary cause is a genetic abnormality. Inherited or De Novo: Genetic disorders can be inherited from parents (germline mutations) or can arise spontaneously (de novo mutations) in the egg, sperm, or early embryonic development. Range of Presentation: They can present at any stage of life, from prenatal development to old age, and vary widely in severity and penetrance (the proportion of individuals with the mutation who express the phenotype). Predictable Inheritance Patterns: For many genetic disorders, their inheritance follows Mendelian patterns (e.g., autosomal dominant, recessive, X-linked), allowing for genetic counseling and risk assessment. Relationship to Mutation: A genetic disorder is the clinical manifestation of one or more underlying mutations. Without a mutation (or a chromosomal abnormality, which itself is a large-scale mutation), a genetic disorder cannot exist. The mutation is the cause; the genetic disorder is the effect/disease. C. Malignancy (Cancer) Definition: Malignancy, commonly known as cancer, is a broad group of diseases characterized by the uncontrolled growth and division of abnormal cells, with the ability to invade adjacent tissues (invasion) and spread to distant sites in the body (metastasis). These abnormal cells form masses called tumors (neoplasms), which can be benign (non-cancerous) or malignant (cancerous). Malignancy specifically refers to the latter. Key Characteristics: Uncontrolled Proliferation: Cancer cells ignore normal growth-regulating signals, leading to continuous and excessive cell division. Loss of Differentiation: Cancer cells often lose their specialized features and functions, becoming more primitive or anaplastic. Invasion: Malignant cells can breach normal tissue boundaries and infiltrate surrounding healthy tissues. Metastasis: The hallmark of malignancy, where cancer cells detach from the primary tumor, travel through the bloodstream or lymphatic system, and establish secondary tumors in distant organs. Genomic Instability: Cancer cells typically accumulate numerous genetic alterations (mutations) over time, contributing to their abnormal behavior. Relationship to Mutation: Cancer is fundamentally a disease of accumulated somatic mutations. It arises when a series of specific mutations occur in critical genes that control cell growth, division, differentiation, and DNA repair. While some cancers have an inherited genetic predisposition (due to germline mutations in cancer-susceptibility genes), the vast majority of cancers develop from a series of acquired somatic mutations throughout an individual’s lifetime. These mutations allow cells to bypass normal regulatory mechanisms and acquire the “hallmarks of cancer.” Differentiating and Recognizing Interconnectedness While all three terms are linked by changes in DNA, their scope and implications differ significantly: Mutation (The Event/Change): This is the fundamental alteration in the DNA sequence. It’s the cause. Think of it as a typo in the instruction manual. Example: A single base pair change from A to T in a specific gene. Genetic Disorder (The Inherited Disease): This is a disease condition that results directly from one or more specific mutations (germline or de novo) that are present in all cells of the affected individual (or at least in the germline if inherited). It’s the disease state stemming from a genetic blueprint flaw. Example: Sickle Cell Anemia is a genetic disorder caused by a single point mutation in the beta-globin gene, leading to abnormal hemoglobin. This mutation is present in almost all cells of affected individuals from conception. Malignancy (The Acquired Disease of Uncontrolled Growth): This is a complex disease driven by the accumulation of multiple somatic mutations (and sometimes initial germline mutations) in a subset of cells within a tissue, leading to

Body Regions, Abdominal Quadrants, and Terminology (1)
Physiology

Body Regions, Abdominal Quadrants, and Terminology

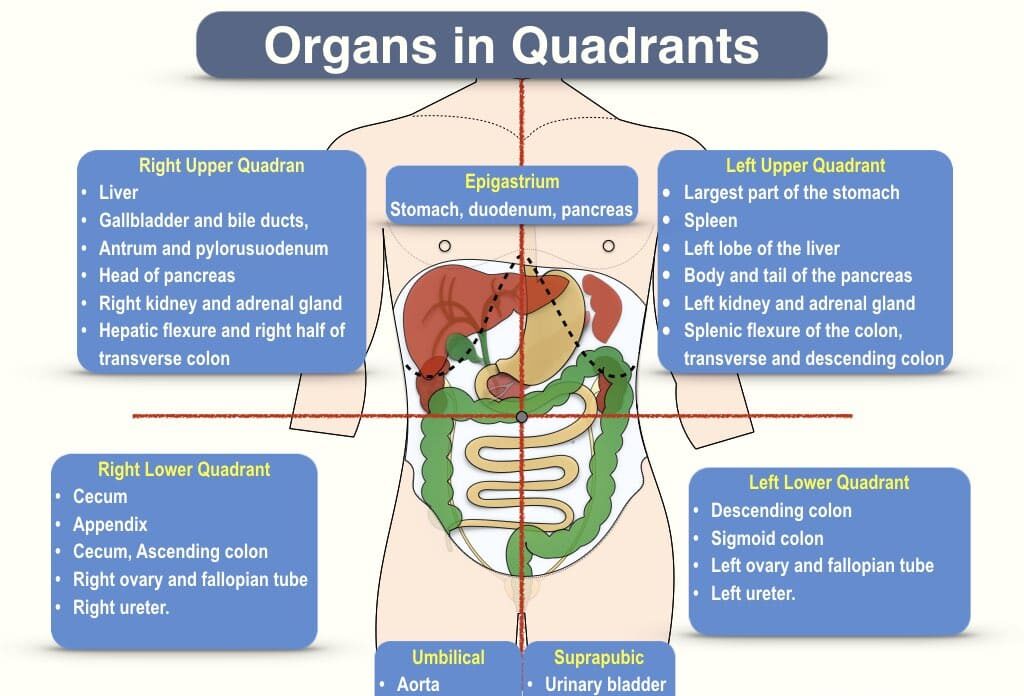
Body Regions, Abdominal Quadrants & Terminology Anatomy: Body Regions, Quadrants, and Terminology ANATOMY & PHYSIOLOGY I. Introduction to Body Regions The human body is divided into various anatomical regions to facilitate precise localization, communication, and study. This regional approach helps in systematically understanding the organization of structures (muscles, bones, nerves, vessels) and organs, which is crucial for physical examination, diagnosis, and surgical interventions. The body is broadly divided into two main parts: Axial Region: Forms the main axis of the body, comprising the head, neck, and trunk. Appendicular Region: Consists of the limbs (appendages) attached to the axial skeleton. II. The Axial Region The axial region forms the central core of the body and includes the most vital organs for survival. A. Head (Caput): Boundaries: Superior: Vertex (highest point of the skull). Inferior: Mandible (jawbone) and the base of the skull, connecting to the neck. Anterior: Face, extending from the forehead to the chin. Posterior: Occipital region. Lateral: Temporal and parietal regions. Key Features/Subdivisions: Cranium (Skull): Encloses and protects the brain. Subdivided into: Frontal: Forehead. Parietal: Sides and roof of the skull. Temporal: Sides of the head, inferior to parietal. Occipital: Back and base of the skull. Face (Facies): Contains sensory organs and the entry points for the digestive and respiratory systems. Subdivided into: Orbital: Around the eyes. Nasal: Nose region. Oral (Buccal): Mouth and cheeks. Mental: Chin. Zygomatic: Cheekbones. Auricular: Ear region. Clinical Significance (Head): Houses the brain (CNS), major sense organs (eyes, ears, nose, tongue), and is a common site for trauma, neurological assessment, and ENT (Ear, Nose, Throat) conditions. B. Neck (Cervix): Boundaries: Superior: Base of the skull and inferior border of the mandible. Inferior: Superior border of the clavicles (collarbones) and the superior border of the sternum (breastbone), extending posteriorly to the first thoracic vertebra. Anterior: From chin to suprasternal notch. Posterior: From occipital region to upper back. Key Features/Subdivisions: Anterior Cervical Region: Contains the trachea, larynx, thyroid gland, major blood vessels (carotid arteries, jugular veins), and neck muscles. Posterior Cervical Region (Nuchal Region): Contains the cervical vertebrae and deep back muscles. Lateral Cervical Region: Defined by the sternocleidomastoid muscle, dividing it into anterior and posterior triangles. Clinical Significance (Neck): Critical passageway for vital structures (airway, esophagus, major vessels, nerves, spinal cord). Common site for lymph node examination, thyroid assessment, and trauma. C. Trunk (Truncus): The trunk is the largest region of the axial body, divided into the thorax, abdomen, and pelvis. 1. Thorax (Chest): Boundaries: Superior: Thoracic inlet (superior aperture of the thorax), continuous with the neck. Inferior: Diaphragm, separating it from the abdomen. Anterior: Sternum and costal cartilages. Posterior: Thoracic vertebrae. Lateral: Ribs and intercostal muscles. Key Features/Subdivisions: Thoracic Wall: Provides bony protection (rib cage). Thoracic Cavity: Contains the heart, lungs, great vessels, esophagus, trachea, and thymus gland. Breasts (Mammary Region): Located anteriorly, superficial to the pectoralis major muscle. Clinical Significance: Houses vital respiratory and circulatory organs. Site for respiratory and cardiac examinations, chest trauma, and breast pathologies. 2. Abdomen: Boundaries: Superior: Diaphragm. Inferior: Continuous with the pelvis at the level of the pelvic inlet. Anterior/Lateral: Abdominal wall muscles (rectus abdominis, obliques, transversus abdominis). Posterior: Lumbar vertebrae and associated muscles. Key Features/Subdivisions: Abdominal Cavity: Contains most of the digestive organs, spleen, kidneys, adrenal glands. Abdominal Wall: Muscular layers provide support and protect organs. Clinical Significance: Site of many digestive, urinary, and reproductive system pathologies. Crucial for abdominal examination, assessment of pain, and surgical access. 3. Pelvis: Boundaries: Superior: Pelvic inlet (linea terminalis), continuous with the abdomen. Inferior: Pelvic outlet (pelvic diaphragm/floor). Lateral: Hip bones (ilium, ischium, pubis). Posterior: Sacrum and coccyx. Key Features/Subdivisions: Pelvic Cavity: Contains the urinary bladder, rectum, and reproductive organs. Perineum: Region inferior to the pelvic diaphragm, containing external genitalia and anal canal. Clinical Significance: Houses urinary, reproductive, and terminal digestive organs. Important for urological, gynecological, and colorectal examinations. III. The Appendicular Region The appendicular region consists of the upper and lower limbs, specialized for movement and manipulation. A. Upper Limb (Extremitas Superior): Boundaries: Attached to the axial skeleton via the pectoral girdle (scapula and clavicle). Key Features/Subdivisions: Shoulder (Deltoid Region): Proximal attachment to the trunk, site of glenohumeral joint. Arm (Brachium): Between shoulder and elbow. Contains humerus. Elbow (Cubital Region): Joint between arm and forearm. Forearm (Antebrachium): Between elbow and wrist. Contains radius and ulna. Wrist (Carpus): Joint between forearm and hand. Hand (Manus): Distal end, highly mobile and manipulative. Subdivided into: Palm (Palmar/Volar aspect): Anterior surface. Dorsum (Dorsal aspect): Posterior surface. Digits (Fingers): Phalanges. Clinical Significance: High mobility, frequent site of fractures, dislocations, nerve entrapments (e.g., carpal tunnel syndrome), and vascular issues. B. Lower Limb (Extremitas Inferior): Boundaries: Attached to the axial skeleton via the pelvic girdle (hip bones). Key Features/Subdivisions: Hip (Coxal Region): Proximal attachment to the trunk, site of hip joint. Thigh (Femoral Region): Between hip and knee. Contains femur. Knee (Patellar/Popliteal Region): Joint between thigh and leg. Patellar: Anterior aspect (kneecap). Popliteal: Posterior aspect (back of knee). Leg (Crus): Between knee and ankle. Contains tibia and fibula. Ankle (Tarsus): Joint between leg and foot. Foot (Pes): Distal end, weight-bearing and propulsion. Subdivided into: Dorsum: Superior surface. Plantar: Inferior surface (sole). Digits (Toes): Phalanges. Clinical Significance: Weight-bearing, locomotion. Common site for fractures, sprains (ankle), degenerative joint disease (knee, hip), and vascular conditions (e.g., DVT). Region Subdivision(s) Key Bony/Muscular Boundaries Key Contents/Features Axial: Head Cranium, Face Skull bones, Mandible Brain, Sense organs (eyes, ears, nose, mouth) Axial: Neck Anterior, Posterior, Lateral Base of skull, Mandible, Clavicles, Sternum, C7 vertebra Trachea, Larynx, Thyroid, Carotids, Jugulars, Cervical spine Axial: Trunk (Thorax) Thorax Rib cage, Sternum, Thoracic vertebrae, Diaphragm (inferior) Heart, Lungs, Esophagus, Trachea, Great vessels, Breasts Axial: Trunk (Abdomen) Abdomen Diaphragm (superior), Pelvic inlet (inferior), Abdominal muscles, Lumbar vertebrae Most digestive organs, Kidneys, Spleen, Adrenals Axial: Trunk (Pelvis) Pelvis Pelvic inlet (superior), Pelvic floor (inferior), Hip bones, Sacrum, Coccyx Bladder, Rectum, Reproductive organs Appendicular: Upper Limb Shoulder, Arm, Elbow, Forearm, Wrist, Hand Pectoral girdle, Humerus, Radius, Ulna, Carpals, Metacarpals, Phalanges Muscles, Nerves (e.g., Brachial plexus), Vessels (e.g., Brachial artery)

Introduction to Body Cavities
Physiology

Introduction to Body Cavities

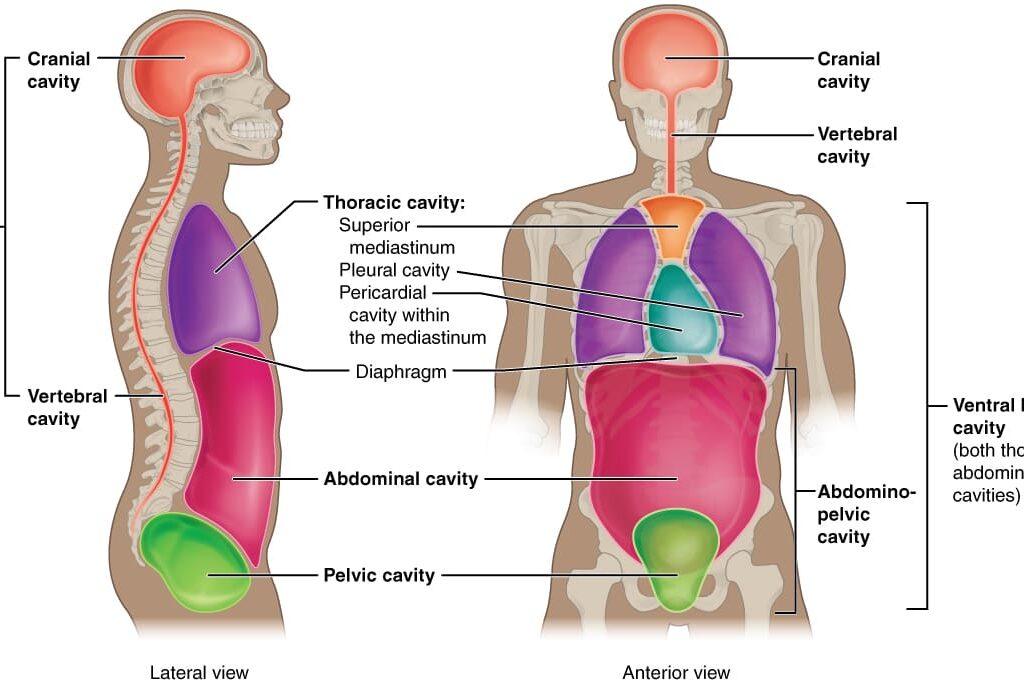
INTRODUCTION TO BODY CAVITIES Anatomy: Body Cavities Reference HUMAN ANATOMY I. Introduction to Body Cavities Body cavities are enclosed, fluid-filled spaces within the human body that contain and protect internal organs. They are crucial for: Protection: Cushioning delicate organs from shocks and impacts. Support: Providing a stable environment for organs. Permitting organ movement: Allowing organs to change size and shape (e.g., heart beating, lungs expanding, stomach distending) without friction or damage to surrounding tissues. The human body possesses two main sets of internal cavities: the Dorsal Body Cavity and the Ventral Body Cavity. These cavities are formed during embryonic development and house organs of the nervous, circulatory, respiratory, digestive, urinary, and reproductive systems. II. The Dorsal Body Cavity The dorsal body cavity is located posteriorly and protects the fragile organs of the central nervous system. It has two continuous subdivisions: A. Cranial Cavity Definition: The space enclosed by the cranium (skull). Boundaries: Superior, Lateral, Posterior: Formed by the cranial bones (frontal, parietal, temporal, occipital, sphenoid, ethmoid). Inferior: Formed by the floor of the cranium, which contains the foramen magnum (a large opening through which the brainstem connects to the spinal cord). Contents: Brain: The primary organ of the central nervous system, responsible for thought, sensation, and coordination. Meninges: Three protective membranes (dura mater, arachnoid mater, pia mater) that surround the brain and spinal cord. Cerebrospinal Fluid (CSF): A clear fluid that circulates within the meninges and ventricles of the brain, providing cushioning and nutrient transport. Blood Vessels: Arteries, veins, and venous sinuses that supply and drain blood from the brain. Cranial Nerves: Twelve pairs of nerves that emerge directly from the brain. B. Vertebral (Spinal) Cavity Definition: The space formed by the vertebral column, extending from the foramen magnum to the sacrum. Boundaries: Anterior, Lateral, Posterior: Formed by the vertebral arches of the individual vertebrae, which collectively create the vertebral canal. Superior: Continuous with the cranial cavity at the foramen magnum. Inferior: Ends at the sacrum. Contents: Spinal Cord: A long, delicate structure that extends from the brainstem, transmitting nerve signals throughout the body. Meninges: (Dura mater, arachnoid mater, pia mater) that continue from the brain, enclosing the spinal cord. Cerebrospinal Fluid (CSF): Circulates within the subarachnoid space around the spinal cord. Spinal Nerves: Nerves that branch off the spinal cord at each vertebral level. Blood Vessels: Supplying and draining the spinal cord. III. The Ventral Body Cavity The ventral body cavity is much larger than the dorsal cavity and is located anteriorly. It houses a wide range of visceral organs (organs of the digestive, urinary, respiratory, and reproductive systems) and is subdivided by the diaphragm into two main parts: the Thoracic Cavity (superior) and the Abdominopelvic Cavity (inferior). A. Thoracic Cavity: Definition: The superior subdivision of the ventral body cavity, enclosed by the rib cage. Boundaries: Superior: Thoracic inlet (formed by the first thoracic vertebra, first pair of ribs, and manubrium of the sternum). Inferior: Diaphragm (a large, dome-shaped muscle that separates the thoracic and abdominopelvic cavities). Anterior: Sternum and costal cartilages. Posterior: Thoracic vertebrae. Lateral: Ribs and intercostal muscles. Subdivisions within the Thoracic Cavity: Pleural Cavities (x2): Definition: Two lateral compartments, each surrounding a lung. These are potential spaces between the parietal and visceral pleura. Contents: Lungs. Mediastinum: Definition: The central compartment of the thoracic cavity, located between the two pleural cavities. It extends from the sternum anteriorly to the vertebral column posteriorly, and from the thoracic inlet superiorly to the diaphragm inferiorly. Contents: Heart: Enclosed within the pericardial cavity. Great Vessels: Aorta, pulmonary trunk, superior and inferior vena cava. Trachea: Windpipe. Esophagus: Food pipe. Thymus Gland: Located anteriorly in the superior mediastinum (larger in children, atrophies in adults). Lymph Nodes, Nerves: (e.g., vagus, phrenic), Major Bronchi. B. Abdominopelvic Cavity: Definition: The inferior subdivision of the ventral body cavity, located inferior to the diaphragm. It is generally described as having two indistinct parts: the abdominal cavity and the pelvic cavity, as there is no physical barrier separating them. Boundaries: Superior: Diaphragm. Inferior: Pelvic floor (pelvic diaphragm), formed by muscles and fascia. Anterior/Lateral: Abdominal wall muscles. Posterior: Lumbar vertebrae and associated muscles. Subdivisions within the Abdominopelvic Cavity: Abdominal Cavity: Definition: The superior and larger portion of the abdominopelvic cavity. Contents: Digestive Organs: Stomach, small intestine, most of the large intestine, liver, gallbladder, pancreas, spleen. Kidneys and Adrenal Glands: Located retroperitoneally (behind the peritoneum). Portions of Ureters. Many major blood vessels: (e.g., abdominal aorta, inferior vena cava). Pelvic Cavity: Definition: The inferior and smaller portion of the abdominopelvic cavity, located within the bony pelvis. Boundaries: Formed by the bony pelvis (ilium, ischium, pubis, sacrum, coccyx) and the muscles of the pelvic floor. Contents: Urinary Bladder. Sigmoid Colon and Rectum: (terminal part of the large intestine). Reproductive Organs: Females: Uterus, ovaries, fallopian tubes, vagina. Males: Prostate gland, seminal vesicles. Summary Table of Major Body Cavities: Cavity Name Subdivisions Major Boundaries Key Contents Dorsal Body Cavity Cranial Cavity Cranium Brain, Meninges, CSF Vertebral Cavity Vertebral Column Spinal Cord, Meninges, CSF Ventral Body Cavity Thoracic Cavity Rib Cage, Sternum, Thoracic Vertebrae, Diaphragm (inferior) Lungs (in pleural cavities), Heart (in pericardial cavity), Trachea, Esophagus, Thymus Pleural Cavities (x2) Within Thoracic Cavity, surrounding lungs Lungs Mediastinum Central compartment of Thoracic Cavity Heart, Great Vessels, Trachea, Esophagus, Thymus Abdominopelvic Cavity (Full Cavity) Diaphragm (superior), Pelvic Floor (inferior), Abdominal Muscles, Lumbar Vertebrae Digestive Organs (stomach, intestines, liver, etc.), Kidneys, Bladder, Reproductive Organs Abdominal Cavity Superior portion of Abdominopelvic Cavity Stomach, Small/Large Intestines, Liver, Spleen, Pancreas, Kidneys Pelvic Cavity Inferior portion of Abdominopelvic Cavity, within bony pelvis Bladder, Rectum, Reproductive Organs IV. Protective Functions of Body Cavities Body cavities provide much more than just space for organs; they are integral to their protection and optimal function. A. Mechanical Protection: Cushioning: The fluid within cavities (like CSF in the dorsal cavity, or serous fluid in the ventral cavity) and the surrounding structures (bone, muscle) help absorb shock and impact, protecting delicate organs from external trauma. Containment: The rigid bony structures surrounding the dorsal cavity (cranium, vertebral column) and

Anatomical movements
Physiology

Anatomical movements

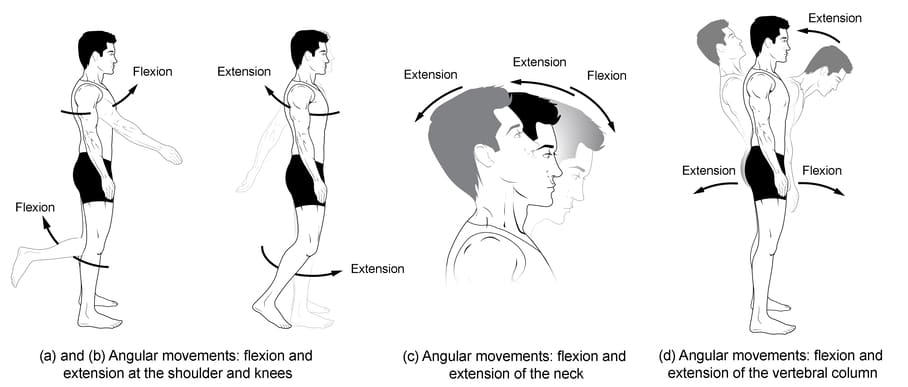
ANATOMICAL MOVEMENTS Anatomy: Planes, Axes, and Movements ANATOMY & KINESIOLOGY Introduction to Anatomical Planes Understanding anatomical planes is fundamental to describing the location of structures and, more importantly, the direction of movement within the human body. These are imaginary flat surfaces that pass through the body, dividing it into sections. All movements occur within or parallel to these planes. A. Standard Anatomical Position Reminder: Before discussing planes, it’s crucial to recall the standard anatomical position: Body erect Feet slightly apart Palms facing forward Thumbs pointing away from the body All descriptions of planes and movements assume the body is in this position. B. The Three Cardinal Planes: 1. Sagittal Plane Definition: A vertical plane that divides the body or an organ into right and left parts. Orientation: Runs vertically from front to back. Key Divisions: Midsagittal (Median) Plane: Lies exactly in the midline, dividing the body into equal right and left halves. Often used as a reference point. Parasagittal Planes: All other sagittal planes offset from the midline, dividing the body into unequal right and left parts. Movements Associated: Primarily flexion and extension. These involve anterior-posterior motion. Analogy: Imagine a wall cutting through your body from your nose to your spine. 2. Frontal (Coronal) Plane Definition: A vertical plane that divides the body or an organ into anterior (front) and posterior (back) parts. Orientation: Runs vertically from side to side, perpendicular to the sagittal plane. Movements Associated: Primarily abduction and adduction. These involve medial-lateral motion. Analogy: Imagine a wall cutting through your body from one shoulder to the other. 3. Transverse (Horizontal) Plane Definition: A horizontal plane that divides the body or an organ into superior (upper) and inferior (lower) parts. Orientation: Runs horizontally, perpendicular to both sagittal and frontal planes. Key Divisions: Often referred to as cross-sectional planes, especially in imaging (e.g., CT scans, MRIs). Movements Associated: Primarily rotational movements (medial/internal and lateral/external rotation). Analogy: Imagine a table slicing through your body at the waist. C. Clinical Relevance of Planes: Medical Imaging: Radiologists extensively use these planes to orient images (e.g., MRI, CT, ultrasound) and describe the location of pathologies. Surgical Planning: Surgeons plan incisions and approaches based on anatomical planes. Rehabilitation: Therapists describe exercises and patient movements in relation to these planes to ensure correct form and target specific muscle groups. Biomechanics: Researchers analyze human movement by breaking it down into components occurring in specific planes. II. Anatomical Axes of Rotation Movement at a joint occurs around an imaginary line called an axis of rotation. Each axis is perpendicular to the plane in which the movement occurs. Think of the axis as a pivot point around which the bone rotates. A. The Three Major Axes: Mediolateral (Transverse) Axis: Orientation: Runs horizontally from side to side (left to right or right to left). Relationship to Planes: Perpendicular to the sagittal plane. Movements Associated: Movements that occur in the sagittal plane, such as flexion and extension. Example: Bending your elbow (flexion) or straightening it (extension) occurs around a mediolateral axis passing through the elbow joint. Anteroposterior (Sagittal) Axis: Orientation: Runs horizontally from front to back (anterior to posterior or posterior to anterior). Relationship to Planes: Perpendicular to the frontal (coronal) plane. Movements Associated: Movements that occur in the frontal plane, such as abduction and adduction. Example: Lifting your arm out to the side (abduction) or bringing it back to your body (adduction) occurs around an anteroposterior axis passing through the shoulder joint. Vertical (Longitudinal) Axis: Orientation: Runs vertically from superior to inferior (up and down). Relationship to Planes: Perpendicular to the transverse (horizontal) plane. Movements Associated: Movements that occur in the transverse plane, primarily rotational movements (medial/internal rotation, lateral/external rotation). Example: Turning your head left and right (rotation of the neck) occurs around a vertical axis passing through the cervical spine. Rotating your arm inward or outward at the shoulder also occurs around a vertical axis. B. Summary Table: Plane of Movement Axis of Rotation Primary Movements Sagittal Mediolateral (Transverse) Flexion, Extension Frontal (Coronal) Anteroposterior (Sagittal) Abduction, Adduction Transverse (Horizontal) Vertical (Longitudinal) Rotation (Medial/Lateral) C. Importance of Axes: Biomechanics: Crucial for analyzing the mechanics of movement and understanding forces acting on joints. Exercise Science: Helps in designing exercises that target specific planes of motion and strengthen muscles responsible for movements around particular axes. Prosthetics and Orthotics: Design of artificial limbs and braces must consider the natural axes of human joint movement. Activity for Students: To reinforce understanding, perform simple movements and identify the plane and axis for each: Nodding head “yes” (flexion/extension) Shaking head “no” (rotation) Jumping jacks (abduction/adduction of arms and legs) Bicep curl (flexion/extension of elbow) Trunk rotation III. Classification of Anatomical Movements Anatomical movements are typically described at synovial joints, which allow for a wide range of motion. Movements are often described in pairs, as they are opposing actions. A. Movements in the Sagittal Plane (around a Mediolateral Axis): 1. Flexion: Definition: Movement that decreases the angle between two body parts. For most joints, this involves bringing the anterior surfaces closer together, or in the case of the knee and elbow, bringing posterior surfaces closer. Examples: Shoulder: Bringing the arm forward and upward. Elbow: Bending the arm, bringing the forearm closer to the upper arm. Wrist: Bending the hand anteriorly towards the forearm. Hip: Bringing the thigh forward and upward. Knee: Bending the leg, bringing the heel towards the buttocks. Trunk/Spine: Bending forward at the waist. Neck: Bending the head forward, chin towards the chest. Key Muscles (Examples): Biceps brachii (elbow), Pectoralis major (shoulder), Iliopsoas (hip), Hamstrings (knee). 2. Extension: Definition: Movement that increases the angle between two body parts, effectively straightening the joint. It is generally the reverse of flexion. Hyperextension: Extension beyond the normal anatomical limit. This can indicate injury or hypermobility. Examples: Shoulder: Moving the arm backward from the anatomical position. Elbow: Straightening the arm. Wrist: Straightening the hand with the forearm (or moving it posteriorly). Hip: Moving the thigh backward. Knee: Straightening the leg. Trunk/Spine: Bending backward at the waist. Neck: Extending

Scroll to Top