Doctors Revision

Author name: doctorsrevision@gmail.com

ELECTROCARDIOGRAM INTERPRETATION
Physiology

ELECTROCARDIOGRAM INTERPRETATION

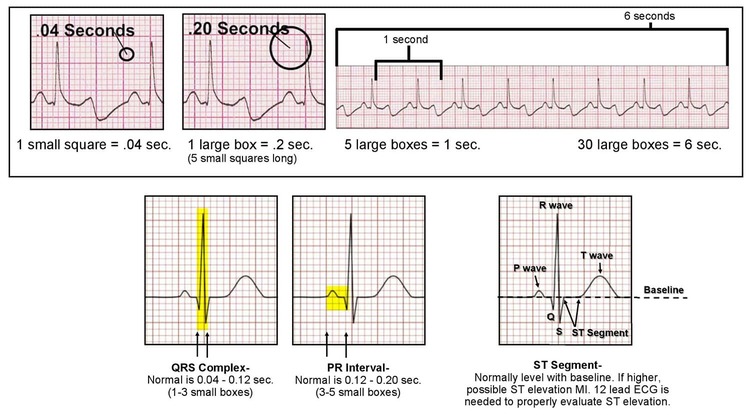
ELECTROCARDIOGRAM INTERPRETATION ELECTROCARDIOGRAM (ECG) Electrocardiogram is a graphic record of algebraic summed potentials generated by the heart, recorded from the surface of the body using an electrocardiograph machine. The magnitude, polarity, and configuration of the recorded electrocardiogram depends on the location of the recording leads placed on the body surface. The process of recording an electrocardiogram is called electrocardiography. Aims and Objectives Carry out electrocardiography correctly and successfully. Interpret the electrocardiogram recorded. Relate the interpretation with the heart status. Assess the functional integrity of the heart. Suggest the appropriate remedy if any that can improve the status detected. Requirements Functional Electrocardiograph machine & accessories Volunteer subject Volunteer ECG operator Couch with linen Screen (for privacy) Cotton wool/tissue and spirit/alcohol Procedure The lab technician/tutor will introduce the electrocardiograph machine in use with its operational procedures. The procedure of electrocardiography will be thoroughly explained to the volunteer subject by the volunteer operator. The subject will be screened off, asked to undress to expose the chest, both upper limbs and both legs. The subject then lies on his or her back on the couch, and relaxes while breathing quietly throughout the procedure. The rest of the body surface that is not to be used is covered with linen. The volunteer ECG operator prepares the surfaces for the leads electrodes attachment by clearing it with cotton wool soaked in alcohol or spirit. Thinly coat the surfaces prepared with salt enriched electrode jelly and proceed to strap electrodes appropriately. Record manually lead by lead till you get all the 12 leads designated, then proceed to record automatically all the 12 leads record as well. Label the electrocardiogram recorded with the volunteer’s particulars namely: Name, Sex, Age, time of recording, any medicines taken, and finally any known medical condition the volunteer subject has. Switch off the electrocardiograph machine and disconnect off the subject. Clean off the jelly applied on the subject with water and dry with cotton wool or tissue. Results Analysis of Results Note: Attached is a tracing of a normal 12 lead electrocardiogram (ECG) and the relationship of the events of the cardiac cycle to the waves and intervals of the normal left ventricular surfaces complex. Use these to help you analyze your recorded ECG. 1. Estimate the frontal and horizontal plane QRS axes: 2. Describe the atrial pace maker and indicate its rate and regulating: 3. Describe the nature and duration of atrial activation (P wave): 4. Describe any supra ventricular premature contractions: 5. Describe the AV junction conductions: 6. Describe the rate duration and regularity of ventricular activation and site of its pace maker (QRS complex wave): 7. Describe the course of ventricular activation and the shape of the QRS complex: 8. Describe any abnormalities in J point and S-T segments: 9. Describe T wave changes: 10. Describe alteration in Q-T interval in relation to rate: Conclusion Recommendation / Suggestions Discussion Questions 1. What is the significance of: i. P wave: ii. QRS complex: iii. T wave: 2. Why is P wave usually largest in standard lead II? 3. Why is T wave small or absent in lead aVL? 4. What is the significance of the interval between the end of P wave and the beginning of the QRS complex? 5. What factors influence the duration of the: i. P-R interval: ii. Q-T interval: Reference: A Normal 12-Lead Electrocardiogram Layout I aVR V1 V4 II aVL V2 V5 III aVF V3 V6 Physiology Steeplechase: ECG Interpretation ECG Steeplechase Experiment: Electrocardiography Must Know: Waves: P (Atrial), QRS (Ventricular), T (Repolarization). Calculations: 300 / Big Squares = Rate. Placement: V4 is at the Apex (5th ICS, Mid-Clavicular). Pathology: ST Elevation = Infarction. Start ECG Quiz Station 1 Interpretation Check Answer Next Station Exam Completed! Results for . Score 0/0 Accuracy 0% Download ECG Report Processing images and generating PDF…
RED BLOOD CELL COUNT
Physiology

RED BLOOD CELL COUNT

RED BLOOD CELL COUNT & WBC COUNT DETERMINATION OF RED BLOOD CELL COUNT Principle The methods generally used are based on the estimation of the number of cells in a small volume of diluted blood. The counting is carried out in a glass counting chamber. The volume of the fluid over each square is calculated from the area of a square and the depth of the fluid layer over it. Core Concept: The average number of cells lying on one square is found from the counts of a series of squares. The product of this average number by the dilution gives the average number of cells in the undiluted blood. Aim: To enumerate the number of RBCs per cubic millimeter of blood. Student Objectives After completion of this experiment, you should be able to: Describe the relevance determining the red cell count. Identify the different equipment and reagents used in this experiment. List the normal red cell count in different age groups. Outline the common physiological and pathological conditions that cause an increase or decrease in the red cell count. Materials and Apparatus 1. RBC Diluting Pipette Specifications: Bulb type. Graduated to give a dilution of 1 in 100 or 1 in 200. Stem Markings: 0.5 and 1.0. Upper Line: 101 (immediately above the bulb). Red Bead: Located in the bulb to facilitate mixing of the blood and diluting fluid. 2. Hayem’s Fluid (Diluting Fluid) Properties: Must be isotonic; causes neither hemolysis nor crenation. Contains a fixative to preserve shape and prevent autolysis. Prevents agglutination/rouleaux. Composition (per 200ml) NaCl (3.8%): 1.0 g Sodium Sulfate (Na₂SO₄): 5.0 g Mercuric Chloride (HgCl₂): 0.5 g Distilled Water: 200 ml Function of Ingredients NaCl & Na₂SO₄: Provide isotonicity (prevents shape change) and anticoagulant properties (prevents rouleaux). Mercuric Chloride: Fixative, antifungal, and antimicrobial agent. 3. Neubauer Haemocytometer Consists of a thick glass slide with a central platform 0.1mm lower than the side platforms (Depth of chamber = 0.1mm). The Ruled Area (Center): Divided into 16 medium sized squares. Each medium square is subdivided into 16 small squares. Area of smallest square = 1/400 sq. mm. Counting Area: The red cells lying in 5 of the medium squares (E1, E2, E3, E4, and E5) are counted. NB: For use, the haemocytometer as well as the diluting pipette must be clean, dry and absolutely grease free. Procedure Sampling: Fill the pipette up to mark 0.5 on the scale with blood from the finger tip. Diluting: Wipe the outside of the pipette. Draw Hayem’s fluid up to mark 101. Close the tip, detach sucker, and mix well (shaking 3-4 mins). Chamber Prep: Place coverslip on counting chamber. Apply gentle pressure until Newton rings (rainbow colors) appear. Discarding: Discard the first few drops (they contain no cells). Charging: Fill the chamber by holding the pipette tip against the edge of the coverslip. Do not overfill into troughs. Settling: Allow several minutes for cells to settle. Counting: Count red cells in 80 small squares (5 groups of 16 squares: E1-E5). Rule: Include cells touching top and right border lines only. CALCULATION Dimensions Area of 1 small square = 1/400 sq mm Depth of chamber = 1/10 mm Volume of 1 square = 1/4000 cu mm Variables N = Total cells counted in 80 squares Dilution Factor = 200 Squares Counted = 80 Final Formula (Cells per cu mm): Total = N × 10,000 Derivation: (N × 4000 × 200) / 80 QUESTIONS When blood is taken to the mark 0.5 and diluent to mark 101, why is the dilution 1 in 200 and not 1 in 202? Why is blood diluted 200 times for red cell count? What is the function of the bead in the bulb? If Hayem’s solution is not available, can you use any other? How will you differentiate red cells from dust particles? What is the fate of leukocytes in this experiment? Since the mature red cells do not contain ‘nuclei’, are they dead cells? Explain your answer. Explain the possible errors that could arise in obtaining and diluting blood, due to uneven distribution of cells in the counting chamber, due to mechanical causes and from other sources. DETERMINATION OF THE DIFFERENTIAL WHITE BLOOD CELL COUNT Student Objectives At the end of this experiment, you should be able to: Identify all equipment and reagents used in the determination of the differential WBC count. Describe the relevance and importance of preparing and staining a blood smear and doing a differential leukocyte count. Prepare satisfactory blood films, fix and stain them and describe the features of a well stained film. Identify different blood cells in a film and indicate the identifying features of each type of leukocyte. Differentiate between neutrophils, eosinophils, basophils, monocytes, and lymphocytes. Describe the functions of each type of the different leukocytes. Outline the conditions in which the leukocyte numbers increase or decrease. Relevance & Principle Relevance: Many hematological and other disorders can be diagnosed by a careful examination of a stained blood film. A physician may order a differential leukocyte count (always along with the total leukocyte count) to differentiate between the different causes of infection (e.g. bacterial vs. viral causes) depending on which sub-category of leukocyte is greatly affected. The differential leukocyte count is also done to monitor blood diseases like leukemia, or to detect allergic or parasitic infection. Principle: A blood film is stained with Leishman’s stain and scanned under oil immersion, from one end to the other. As each WBC is encountered, it is identified until 100 leukocytes have been examined. The percentage distribution of each type of WBC is then calculated. Procedure Wipe the punctured finger with a piece of cotton wool soaked in alcohol, and allow a fresh drop of blood to accumulate. Hold a clean, dry microscope slide between the thumb and forefinger of the left hand. The slide is held by the corners of its right hand end so that its length extends at an approximate angle of 45 degrees above the left thumb and forefinger.

BLOOD TYPING
Physiology

BLOOD TYPING & CROSSMATCHING

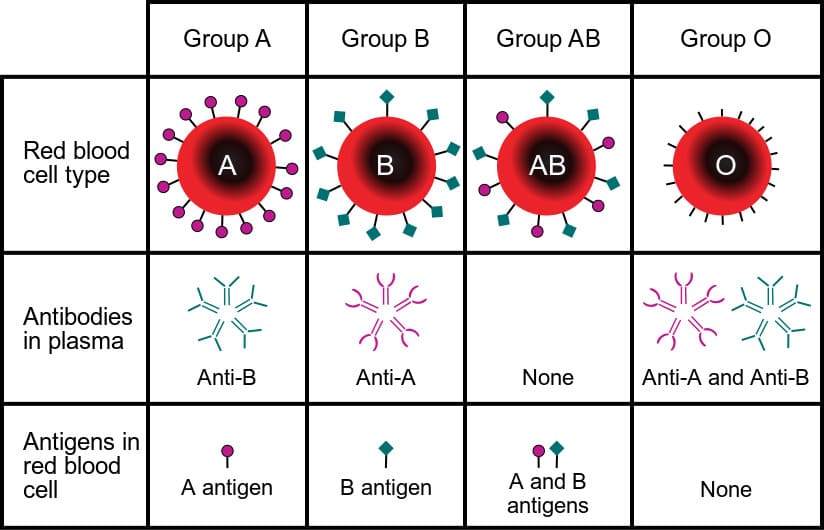
BLOOD TYPING & CROSSMATCHING BLOOD TYPING & CROSSMATCHING EXPERIMENT : BLOOD TYPING This experiment is a collection of measurements routinely carried out in hospital laboratories. The method chosen in the hospital will be a compromise between available instruments and wanted accuracy. Here we want you to get familiar with some of the most commonly used methods in this country. Student Objectives At the end of the experiment, you should be able to: Identify the different equipment and reagents used in this experiment stating the relevance of each. Define the terms blood “groups” and “blood types”, and name the various blood grouping systems. Describe the physiological basis of blood grouping and state its clinical significance. Explain the basis of the terms “universal donor” and “universal recipient”. Describe the significance of Rh factor determination. Determine blood groups by using commercially available anti-sera, and precautions to be observed. Explain how blood is screened and stored in blood banks, and outline the changes that occur when blood is stored. List the indications for blood transfusion. Explain the relevance of matching donor and recipient blood groups before transfusion. Blood Groups / Types The membrane of each red blood cell contains millions of antigens that are ignored by the immune system. However, when patients receive blood transfusions, their immune systems will attack any donor red blood cells that contain antigens that differ from their self-antigens. Therefore, ensuring that the antigens of transfused red blood cells match those of the patient’s red blood cells is essential for a safe blood transfusion. The most common and relevant of these antigens are the 3 antigens that form the ABO blood group system and Rhesus antigens that make up the Rhesus blood group. The presence of the three ABO agglutinogens (determined by three allelic genes) residing on the surface of red blood cells and the presence in the serum of three specific antibodies (agglutinins) to these genetically determined antigens is responsible for the major blood group antigen-antibody reactions, which may occur as a result of blood transfusions. Genotypes & Phenotypes Six genotypes in the ABO blood grouping system may exist: Genotype OO Group O Genotype AA, AO Group A Genotype BB, BO Group B Genotype AB Group AB Note: A and B are dominant over the gene O. Therefore, genotype BO cannot be serologically distinguished from BB, and AO cannot be serologically distinguished from AA. In addition, there exists other less common blood grouping systems like: the Duffy, Kell, Diego, Kidd, and MNS blood groups among others. This practical session however will focus on the ABO and Rhesus blood grouping systems since they are the most assessed clinically in hospital, and contribute the major bulk of blood transfusion reactions. Principle Landsteiner’s Law States that if a particular antigen is present in the red blood cells, the corresponding antibody must be absent in the serum. If the particular antigen is absent in the red blood cells the corresponding antibody must be present in the serum. Blood typing is performed on the basis of agglutination. Agglutination occurs if an antigen is mixed with its corresponding antibody. Instructions The normal procedure is to mix the unknown cells with two known sera containing A or B agglutinogens. You are provided with unknown red blood cells and a series of known sera samples. Later in the practical, you will be required to obtain samples of your own (or your friends) blood by cleaning the fourth fingertip with alcohol and puncturing it with a sterile blood lancet. This has a shoulder that prevents too deep entry; therefore a sharp stab with the lancet gives a better blood supply, than a tiny prick. Group Tasks: Typing of unknown red blood cells. Typing of own blood both ABO and Rh. Cross-matching of incompatible bloods. Procedures 1. ABO Blood Grouping Label a series of grooves on a tile: Anti A, Anti B, Anti AB, and Control. Divide it into two halves with a grease pencil for blood sample X (known) and Y (unknown). Place one drop of serum in each groove with a glass rod. Repeat for each sample, taking care to wash and dry the rod between samples. Prepare a control groove using 0.9% saline instead of serum. Using one end of the glass rod mix the blood in the sera in each trough thoroughly for 30 seconds. Stir for 2 minutes and observe for agglutination. Record your findings and determine the group of the unknown blood and own blood used. Observation: Agglutination may be visible to the naked eye as microscopic clumps like cayenne pepper grains or will be seen as smaller clumps under the microscope. The control will appear unaltered at the end of fifteen minutes when a final inspection should be made. 2. Rh Blood Grouping Follow steps 1-6 of the ABO system above using the Anti-D sera. Examine for evidence of agglutination. If agglutination did not occur within 2 minutes, record the blood as Rh negative. If agglutination occurred within 2 minutes, record the blood as Rh positive. OBSERVATIONS Name/ID Anti-A Anti-B Anti-AB Rh (Anti-D) Blood Group Sample X Sample Y Own Blood Note: Mark (+) for agglutination and (-) for no agglutination. EXPERIMENT : CROSS-MATCHING This experiment is designed to imitate the conditions appertaining to a transfusion of incompatible blood. Re-group partners so that incompatible bloods work together. Call one the ‘donor’ and the other the ‘recipient’. Principle The Reaction: Place on a slide one drop of a 1/10 dilution of ‘donor’ blood in citrate-saline. Add 1 drop of undiluted ‘recipient’ blood and mix immediately. Observation: The donor’s cells are outnumbered ten to one by the recipient’s but are observed clumped together in small groups. The recipient’s cells float freely in the plasma in which the donor’s agglutinins are diluted twenty times. Universal Donor Concept: That such a dilution of agglutinins fails to affect the recipient’s cells is the basis for the use of Group O blood for transfusion into any recipient in an emergency. Group O is thus sometimes called the

HAEMATOLOGICAL INDICES
Physiology

HAEMATOLOGICAL INDICES

HAEMATOLOGICAL INDICES – PCV, MCV, MCH HAEMATOLOGICAL INDICES: PCV ESTIMATION Student Objectives (PCV Experiment) At the end of this experiment, you should be able to: Identify all equipment and reagents used in the determination of PCV. Define hematocrit, and explain its clinical significance. Briefly describe physiological/pathological factors that cause decrease PCV. List the possible sources of error in the determination of PCV. Instruments & Reagents For Venous Blood Wintrobe tube Pasteur pipette Centrifuge Anticoagulant: Potassium Oxalate crystals (EDTA can also be used) For Capillary Blood Heparinized capillary tubes Micro-centrifuge Procedure for Venous Blood PCV Using Wintrobe Method Blood Collection: Perform venipuncture to collect blood into a tube with a pinch of oxalate crystals mixture. Mixing: Mix the blood with anticoagulant by rolling the tube between the palms of both hands. Transfer: Draw blood into a Pasteur pipette and introduce it into the Wintrobe tube. Wintrobe Tube Details: Special centrifuge tube with uniform diameter throughout. Holds about 1 ml of blood. Graduations are scaled in reversed directions on each side so either plasma or cell volume can be read. Filling: Fill the Wintrobe tube with blood from a fine teat pipette up to the 100 mark (equivalent to 100%). Centrifugation: Centrifuge the tube. Reading: Read the PCV as a percentage of the total volume. Procedure for Capillary Blood PCV Using Microhematocrit Method Labeling: Using labeling paper, mark two micro capillary tubes as X and Y. Blood Sample: Place blood into watch glass X. Tube Filling: Dip one end of tube X into the blood at an angle. Allow tube to fill to 3/4 full by capillary attraction. Sealing: Close the open end with index finger. Lift tube off the blood and seal the end with plasticine wax. Open the tip to remove excess wax. Centrifuge Setup: Open micro centrifuge lid and unscrew top to expose segment carrier. Fix micro capillary tubes (sealed end first) in segments X and Y. Centrifugation: Close lid and start centrifuge. Centrifuge for 5 minutes. Gradually increase speed to 10,000 rpm. Reading: Remove segments and place into micro hematocrit reader. Position tube so total blood column reads from 0% to 100%. Place movable arm so line cuts the interface between cells and plasma. Record results in % volumes. RESULTS Measurements PCV of Male: PCV of Female: Thickness of Buffy Coat: Components Separated Plasma (Top) Buffy Coat (Middle) Red Cells (Bottom) DISCUSSION TOPICS Comparison of both methods: Discuss the differences, advantages, and disadvantages between Venous (Wintrobe) vs Capillary (Microhematocrit) methods. Clinical Application: Describe the use of PCV (Packed Cell Volume) in clinical practice. CLINICAL SIGNIFICANCE OF ABSOLUTE CORPUSCULAR VALUES Knowledge of hemoglobin level, RBC count, and PCV (Hematocrit) alone does not provide information about: Average red blood cell volume. Hb content per cell. Percentage saturation with hemoglobin. These parameters are crucial for diagnosing anemia types. While not obtainable directly through experimental methods, they can be calculated from three basic values: Hemoglobin (Hb), RBC count, and PCV. Student Objectives (Corpuscular Values) Explain the clinical significance of calculating absolute corpuscular values. Describe the macro-corpuscular values and different formulas used in calculations. Describe the classification of anemia based on hematological indices. Calculations & Formulas Required Basic Measurements: 1. Hb (g/100ml) 2. RBC count (×10⁶ cells/mm³) 3. PCV (% per 100ml blood) 1. Mean Corpuscular Volume (MCV) Definition: Average volume of a single red blood cell, expressed in femtoliters (fl). Formula: MCV = (PCV × 10) / RBC count OR: MCV = PCV per liter / RBC (10¹²/L) Normal Range: 74 – 95 femtolitres 2. Mean Corpuscular Hemoglobin (MCH) Definition: Average hemoglobin content (weight) in a single red blood cell, expressed in picograms (pg). Clinical Use: Basis for classifying anemia into hypochromic, normochromic, and hyperchromic types. Formula: MCH = (Hb in g/100ml) / RBC count (RBC count in million/mm³) Normal Range: 27 – 32 pg 3. Mean Corpuscular Hemoglobin Concentration (MCHC) Definition: Relationship between hemoglobin and volume in red blood cells, expressed as percentage saturation of cells with Hb (not whole blood). Key Principle: RBCs cannot exceed ~36% Hb concentration due to limitations in Hb synthesizing machinery. Formula: MCHC = (Hb × 100) / PCV Normal Range: 30 – 36% Other Hematological Indices (for further reading): Mean Corpuscular Diameter (MCD) Color Index (CI) QUESTIONS 1. Reliability Giving a reason, state which of the corpuscular values (MCV, MCH or MCHC) is most reliable and useful clinically? 2. Physiological Limits Why can’t RBCs be filled beyond 36% with Hb? 3. Classification How can you classify anemias on the basis of MCV and MCH? Hematology Steeplechase: Hb, PCV & Indices Hematology Steeplechase Hb Estimation, PCV & Clinical Indices Exam Focus: Calculations: Know your formulas for MCV, MCH, and MCHC. Equipment: Identify Sahli’s vs. Wintrobe’s tubes. Layers: Locate the Buffy Coat. Principles: Acid Hematin vs. Cyanmethemoglobin. Start Blood Lab Quiz Station 1 Equipment Check Answer Next Station Lab Session Completed! Results for . Score 0/0 Accuracy 0% Download Hematology Report Processing images and generating PDF…
TOAD HEART IN SITU AND PROPERTIES OF CARDIAC MUSCLE
Physiology

TOAD HEART IN SITU AND PROPERTIES OF CARDIAC MUSCLE

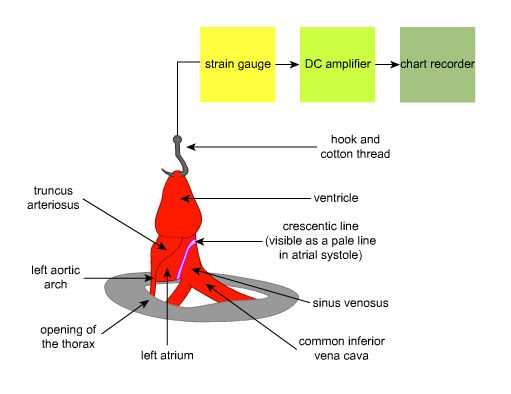
TOAD HEART IN SITU & PROPERTIES OF CARDIAC MUSCLE EXPERIMENT 1: TOAD HEART IN SITU AND PROPERTIES OF CARDIAC MUSCLE Objectives Describe the method of isolation of the toad heart. Determine the effect of temperature on cardiac muscle. List the effect of different ions and drugs on the isolated heart muscle. Explain the mechanism of action of drugs and ions on the cardiac muscle. List the properties of the cardiac muscle. Elaborate the physiological basis of different properties of the cardiac muscle. Introduction The naturally beating toad heart is first observed in situ with its apex connected to a writing lever for recording the sequence of events during contraction. The heart rate is altered by changing the temperature of the bathing fluid. Electrical stimuli are applied between beats to illustrate properties of the conducting system of the heart. Once the conducting system has been inactivated by crushing, cardiac muscle can be studied as a muscle preparation. Cardiac muscle has a different stimulus-response relationship from skeletal muscle, and it shows refractoriness to a second stimulus at some stimulus intervals. Apparatus Kymograph A motor-driven rotating drum that operates at four different speeds, equipped with a clutch mechanism. The drum carries smoked paper that is written on by various levers. Note: Traces must be fully labeled including student names before being shelled. Induction Coil Provides either single stimuli or repetitive stimuli. Note: Relative stimulus strength must always be recorded as the distance in centimeters between primary and secondary coils. Preparation A. Dissection Use a pithed toad (brain and spinal cord destroyed) placed on its back on a cork board. Pin through the web of each foot and the lower jaw. Expose the xiphisternum (cartilaginous extension of the sternum). Make a transverse incision through the abdominal wall below the xiphisternum. Cut through both sides of the sternum and pectoral girdle. Remove anterior thoracic wall. CRITICAL: Frequently irrigate tissues with physiological saline to prevent dessication (drying out). Display thoracic contents by repinning front feet wider apart. Carefully incise the pericardium laterally and reflect it back. Observe heart action and identify successive contractions of the sinus venosus, atria, ventricles, and truncus arteriosus. B. Mounting for Recording Tie silk thread to a fine hook and pass through the ventricle tip without puncturing tissue. Gently lift heart and cut the transverse pericardial ligament (between atria and venous side). Transfer toad to recording stand bath. Anchor heart base with pin through connective tissue near the aorta. Keep heart moist with Ringer’s solution but do not fill the bath yet. WARNING: Skin secretions are toxic—prevent bath fluid contamination. Tie silk thread to the hole nearest the heart lever pivot (must be precisely vertical). Adjust lever vertically so it’s horizontal when heart is relaxed and thread is just taut. Adjust kymograph for maximum friction. Adjust lever spring for 1-2 cm amplitude tracing. EXPERIMENTAL PROCEDURES A. Heart Beat & Temperature Effects 1. Baseline Recording Speed: Moderate (25 mm/sec). Observation: Make a short record. Relate lever movements to actual heart chambers—identify up to four contractile events. 2. Temperature Effects (General) Speed: Slow (2.5 mm/sec). Temps: Bathe heart with saline at approx 0°C, 10°C, and 20°C. Note: Ensure pipette is cooled/heated by solution. Measure temperature accurately. Use signal marker and clock for time traces. Alternate Temperature Procedure Label beakers: 0°C, 10°C, 20°C, 30°C, 40°C. Add 3 mL frog Ringer’s to each. Immerse muscle at 0°C, record twitch. Replace with 20°C and 30°C, wait 30 seconds, record. Replace with 10°C, wait 1 minute, record. Replace with 40°C, record irregular twitches. Analysis: Draw lines from curve summits to baseline. Record graph heights (cm) and durations. Data Table 1: Heart Rate vs Temperature Temperature (°C) Heart Rate (beats/min) Observations 0 10 20 30 40 B. Refractory Period of Conducting System 1 Place Electrodes: One against auricles, other against ventricle. Note: Must not impede movement. 2 Settings: Set signal marker in primary circuit for single break stimuli. Run drum at moderate speed (25 mm/sec). 3 Stimulus Strength: Move secondary coil to produce supra-maximal stimuli (8-10 cm on scale). 4 Procedure: Apply single stimuli at various times during the cardiac cycle (systole and diastole). Measurement Required: Determine refractory period duration and maximum “compensatory pause”. C. Mechanical Block of Conduction (Stannius Ligatures) Preparation: Pass moistened silk thread between aortae and veins, tie loosely. Record at slow speed (2.5 mm/sec). First Ligature (Sinus-Atrial) Tighten ligature across the sinus venosus-atrial junction (white crescent). Effect: Crushes conducting tissues to auricles; sinus continues beating alone while the rest of the heart may stop temporarily. Second Ligature (Atrio-Ventricular) Tie between atrium and ventricle across the atrioventricular bundle. Effect: Isolates the ventricles from the atria. Measurement Required: Determine the inherent rates of the auricles and ventricles separately after isolation. D. PROPERTIES OF CARDIAC MUSCLE 1. Stimulus-Response Relationship Set secondary coil at maximum distance from primary coil. Apply single break stimuli to ventricle (both electrodes) at ~15-second intervals. Between stimuli, turn drum ~1 cm by hand to separate traces. Successively increase stimulus strength (move coils closer) until ventricle responds. Record cm position of secondary coil for each response. Find sub-threshold stimulus, then switch to repetitive stimulation. Observe response to brief repetitive stimulation. 2. Refractory Period of Directly Stimulated Muscle Reconnect for single stimuli. Set supra-threshold stimulus strength. Run drum at moderate speed (25 mm/sec). Apply paired stimuli by two quick taps of telegraph key (< 1 second intervals). Measurement: Determine the maximum interval without a second contraction. This represents the refractory period. Repeat with increased stimulus strength (refractory period should shorten). Apply brief repetitive supra-threshold stimuli—compare response to single stimulus. E. EFFECT OF IONS ON HEART IN SITU Ion Effects Overview: Isotonic NaCl: Rhythm disappears, beating ceases. CaCl₂: Heart beats briefly, then stops in systole (contraction). KCl: Heart stops in diastole (relaxation). Ringer’s solution (all three ions): Beating continues indefinitely. Ringer’s Solution Composition: NaCl: 0.9 g CaCl₂: 0.024 g KCl: 0.042 g NaHCO₃: 0.02 g Distilled water to 100 mL Procedure Bathe heart with Ringer’s until baseline rate established. Prepare NaCl, KCl, CaCl₂ at 3× concentration.

The steeplechase exam in Human Anatomy practical 1 2048
Physiology

Anatomy steeplechase questions pdf

Anatomy Steeplechase Anatomy Steeplechase: Embryology, Histology & Limbs Anatomy Steeplechase Embryology, Histology, Upper & Lower Limb Exam Rules: Be Specific: Don’t just identify the bone; identify the landmark. Side Matters: In a real exam, always specify Left/Right. Clinical Correlation: Think about nerve supplies and injuries. Start Spotter Exam Station 1 Histology Check Answer Next Station Steeplechase Completed! Great job, . Score 0/0 Accuracy 0% Download PDF Report (with Images) Processing images and generating PDF…
Respiratory Function Tests
Physiology

Respiratory Function Tests

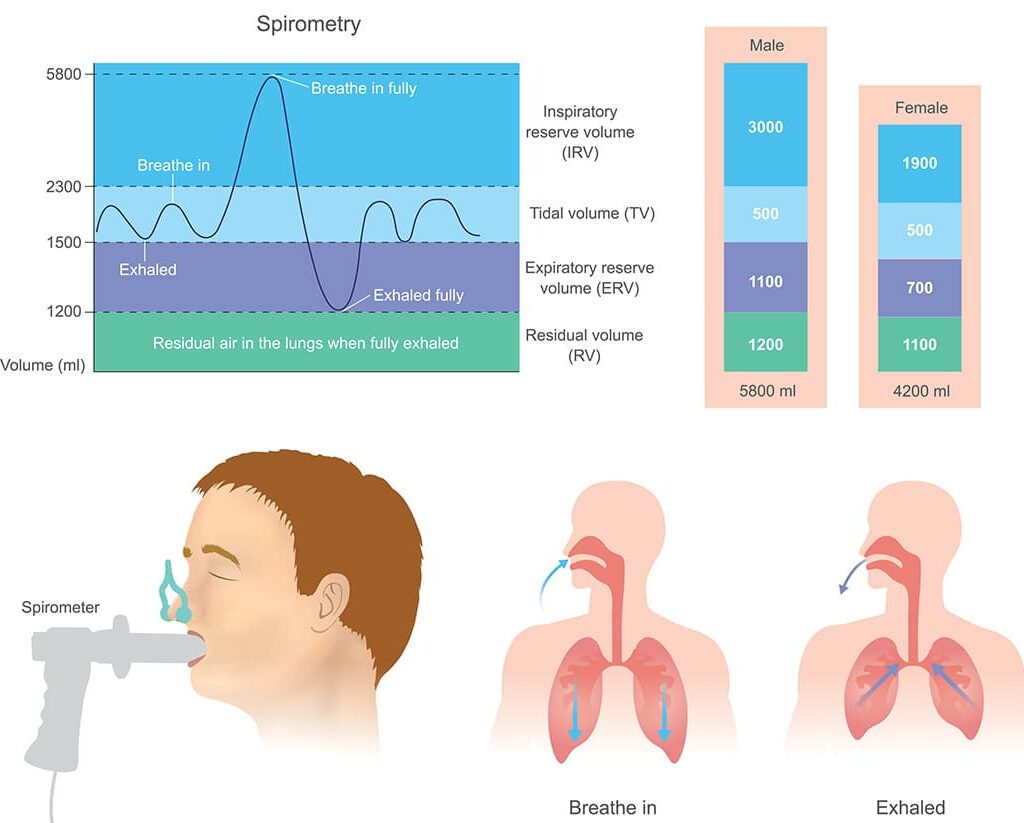
Respiratory Function Tests Respiratory Function Tests Respiratory Function Tests (RFTs), or lung function tests, are painless breathing evaluations measuring how well your lungs take in air, move it in and out, and transfer oxygen to blood, using tools like spirometry (how fast you breathe out) and plethysmography (total lung capacity in a booth) to diagnose breathing issues, monitor lung diseases, and assess lung health before surgery. These tests provide crucial data for managing asthma, COPD, and other respiratory conditions. Overall Objective To understand the principles, methodologies, and clinical significance of various tests used to assess pulmonary function, differentiate between obstructive and restrictive lung diseases, and monitor disease progression. Objective 1: Describe the principles and interpretation of spirometry, including FEV1, FVC, and FEV1/FVC ratio. Spirometry is the most common and fundamental pulmonary function test. It measures how much air a person can inhale and exhale, and how quickly they can exhale it. It’s an indispensable tool for diagnosing and managing a wide range of respiratory conditions. A. Spirometry Basics Definition and Purpose Definition: Spirometry is a simple, non-invasive test that measures the volume and flow of air that can be inhaled and exhaled. Purpose: Diagnose respiratory diseases (e.g., asthma, COPD). Monitor disease progression and response to treatment. Assess severity of lung impairment. Evaluate disability for legal or insurance purposes. Pre-operative assessment of respiratory risk. How Spirometry is Performed (Forced Exhalation Maneuver) The patient takes the deepest breath possible (maximal inspiration) to reach Total Lung Capacity (TLC). Then, they forcefully and rapidly exhale all the air they can, for as long as they can (at least 6 seconds, or until no more air can be exhaled) into a mouthpiece connected to a spirometer. It requires good patient cooperation and effort to obtain reliable and reproducible results. Parameters Measured Spirometry primarily measures two key volumes, from which a crucial ratio is derived: FVC Forced Vital Capacity (Total Volume Exhaled) Definition: The total volume of air exhaled during a maximal forced expiration, starting from a maximal inspiration. Represents: Total “usable” air. Reflects overall size/elasticity of lungs and chest wall. Normal Value: ~4-6 liters (varies by age/height). FEV1 Volume in 1st Second Definition: The volume of air exhaled in the first second of the FVC maneuver. Represents: Speed/ease of expulsion. Indicator of airway patency/resistance. Normal Value: 75-85% of FVC. FEV1/FVC Ratio The Critical Ratio Definition: Ratio of FEV1 to FVC, expressed as percentage. Represents: Most important parameter for differentiating obstructive vs. restrictive disease. Normal Value: ≥ 70-75% (or ratio ≥ 0.70-0.75). Flow-Volume Loops Description: A graphical representation generated during spirometry that plots instantaneous expiratory flow rate (y-axis) against lung volume (x-axis). Normal Loop: A rapid rise to peak expiratory flow, followed by a linear decrease in flow as lung volume decreases, forming a triangular or “sail-like” shape. Inspiratory limb is a smooth, concave curve. Obstructive Pattern: Characterized by a “scooped-out” or concave shape of the expiratory limb, reflecting significant airflow limitation. Peak flow may be reduced. Restrictive Pattern: Characterized by a “witch’s hat” appearance – smaller loop overall (reduced FVC) but with a relatively normal, preserved flow rate shape (proportional but scaled down). Fixed Airway Obstruction: Both inspiratory and expiratory limbs are flattened. B. Interpretation of Spirometry Results Interpretation involves comparing measured values to predicted normal values (based on age, sex, height, ethnicity). Normal Ratio: ≥ 70-75% FEV1: ≥ 80% predicted FVC: ≥ 80% predicted Suggests healthy lung function. Obstructive Example: COPD, Asthma Ratio: < 70-75% (KEY DIAGNOSTIC) FEV1: Reduced (< 80%) FVC: Normal or slightly reduced Loop: “Scooped-out” Increased resistance makes exhalation difficult. Restrictive Example: Fibrosis, Scoliosis Ratio: Normal/Increased (≥ 70%) FEV1: Reduced (< 80%) FVC: Reduced (< 80%) Loop: “Witch’s hat” (small) Reduced compliance/volume; both reduced proportionally. Severity Grading (e.g., COPD GOLD) Based on FEV1 % predicted: Mild: ≥ 80% Moderate: 50-79% Severe: 30-49% Very Severe: < 30% Bronchodilator Reversibility Purpose: Differentiate Asthma vs. COPD. Significant Reversibility: Increase in FEV1/FVC of >12% AND >200 mL. Asthma: Typically significant reversibility. COPD: Often less pronounced/consistent; obstruction is largely fixed. Objective 2: Understand additional lung volumes and capacities measured by methods other than spirometry, particularly Residual Volume (RV) and Total Lung Capacity (TLC). While spirometry is excellent for measuring dynamic lung function (how much air can be quickly moved), it has limitations. Specifically, it cannot measure volumes of air that cannot be exhaled from the lungs. This necessitates other techniques to determine the complete picture of lung volumes. A. Limitations of Spirometry Spirometry directly measures vital capacity (VC or FVC) and its components (IRV, TV, ERV). However, it cannot measure: Residual Volume (RV): The volume of air remaining in the lungs after a maximal forced expiration. Functional Residual Capacity (FRC): The volume of air remaining in the lungs after a normal tidal expiration (ERV + RV). Total Lung Capacity (TLC): The total volume of air in the lungs after a maximal inspiration (VC + RV, or FRC + IC). These volumes are essential for diagnosing and characterizing certain lung conditions, particularly restrictive lung diseases (where TLC is reduced) and obstructive diseases with air trapping (where RV and TLC might be increased). B. Methods for Measuring RV, FRC, and TLC Since RV, FRC, and TLC all include the residual volume, which cannot be exhaled, specialized techniques are required to measure them. 1. Helium Dilution Method Principle: Inert gas dilution. If a known quantity of a tracer gas (helium, insoluble in blood) is introduced into a closed system, it distributes throughout the available lung volume until equilibrium is reached. The extent of dilution is used to calculate the unknown volume. Procedure: Patient connected to spirometer with known volume/concentration of helium (C1). Patient breathes normally (tidal breathing) from closed system. Exhales to FRC, then circuit opens. Helium mixes with air in lungs (FRC volume). Breathing continues until equilibrium is reached (C2). Usually 5-7 minutes. Patient performs maximal expiration (ERV) and maximal inspiration (VC). Calculation: (Vspirometer * C1) = (Vspirometer + FRC) * C2 FRC = ( (Vspirometer * C1) / C2 ) – Vspirometer Once FRC is known:

Control of Respiration (Neural and Chemical Regulation)
Physiology

Control of Respiration (Neural and Chemical Regulation)

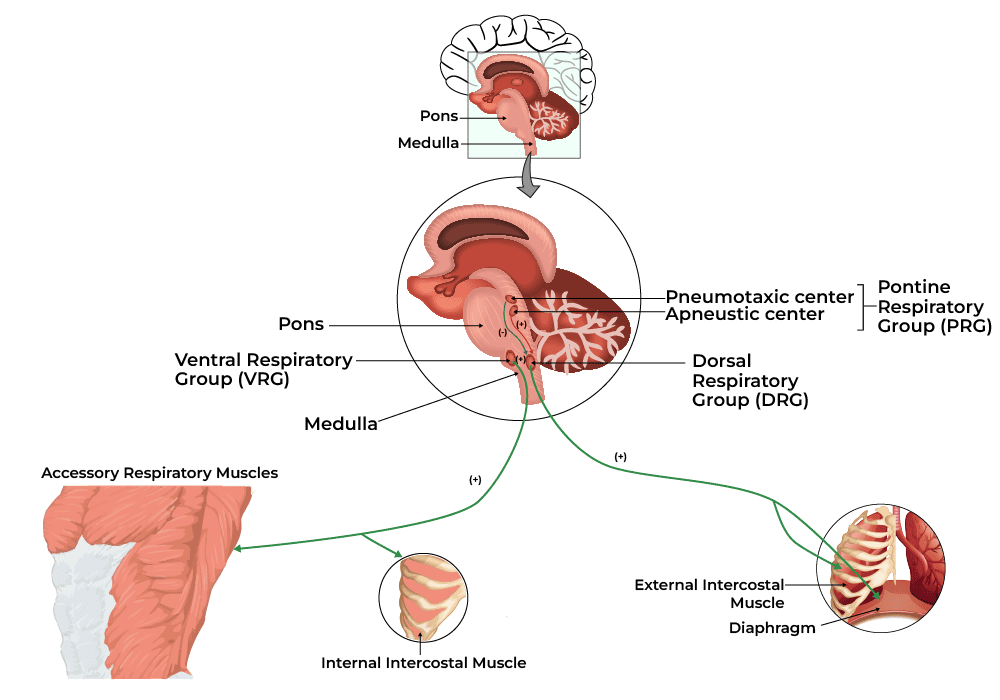
Control of Respiration: Neural and Chemical Regulation Control of Respiration (Neural and Chemical Regulation) Respiration is controlled by both the involuntary and voluntary nervous systems. Involuntary control, which governs automatic breathing, is managed by the respiratory centers in the brainstem (medulla oblongata and pons), which respond to blood levels of oxygen, carbon dioxide, and pH. Voluntary control comes from the cerebral cortex and allows you to control your breathing for activities like speaking or holding your breath. Overall Objective: To understand the neural pathways and chemical factors that regulate the rate and depth of breathing, ensuring appropriate gas exchange to meet metabolic demands and maintain blood gas homeostasis. Objective 1: Identify and describe the key neural control centers for respiration in the brainstem. The control of breathing is a complex process involving both voluntary and involuntary mechanisms. The involuntary, rhythmic control of breathing primarily originates in the brainstem, specifically in the medulla oblongata and the pons. These areas contain specialized groups of neurons that generate and modulate the respiratory rhythm. I. Medullary Respiratory Centers The medulla oblongata houses the most crucial respiratory control centers, responsible for setting the basic rhythm of breathing. These are broadly divided into two main groups: the Dorsal Respiratory Group (DRG) and the Ventral Respiratory Group (VRG). A. Dorsal Respiratory Group (DRG) Location: Located in the posterior portion of the medulla, near the nucleus of the tractus solitarius. Primary Function: The DRG is the most fundamental and active group involved in controlling the basic rhythm of breathing, especially during quiet (eupneic) respiration. It primarily controls inspiration. Neuronal Activity: Contains inspiratory neurons that fire rhythmically. These neurons generate a ramp-like signal: they start weakly and increase in intensity over approximately 2 seconds, then abruptly cease for about 3 seconds, allowing for elastic recoil and exhalation. This gradual increase helps to ensure a smooth, progressive filling of the lungs. Innervation: Sends efferent (motor) signals via the phrenic nerves to the diaphragm. Sends signals via the intercostal nerves to the external intercostal muscles. Activation of these muscles causes the diaphragm to contract and flatten, and the rib cage to expand, leading to inspiration. Afferent Input: Receives sensory input (afferent signals) from: Peripheral chemoreceptors: via glossopharyngeal (CN IX) and vagus (CN X) nerves, detecting changes in PO2, PCO2, and pH. Lung receptors: via vagus (CN X) nerve, detecting stretch and irritation in the lungs and airways. This sensory input allows the DRG to modify the basic respiratory rhythm in response to physiological demands. B. Ventral Respiratory Group (VRG) Location: Located in the anterior portion of the medulla, extending from the brainstem to the upper spinal cord, including the pre-Bötzinger complex. Primary Function: The VRG is largely inactive during quiet breathing. It becomes active and crucial for generating the respiratory rhythm only when there is an increased ventilatory demand, such as during forceful (active) inspiration and expiration. Neuronal Activity: Contains both inspiratory and expiratory neurons. Inspiratory neurons: When stimulated (e.g., by intense DRG signals or strong chemoreceptor input), they send signals to accessory muscles of inspiration (e.g., sternocleidomastoid, scalenes). Expiratory neurons: When stimulated, they send signals to the internal intercostals and abdominal muscles, which are primarily active during forceful exhalation. Rhythm Generation (Pre-Bötzinger Complex): Current research suggests that a small area within the VRG, known as the pre-Bötzinger complex, is the primary site responsible for generating the basic respiratory rhythm. It acts as the pacemaker for breathing, relaying signals to the DRG. Innervation: Inspiratory neurons: Innervate accessory muscles of inspiration. Expiratory neurons: Innervate internal intercostal and abdominal muscles (for active expiration). Role in Forced Breathing: During exercise or respiratory distress, the DRG activates the VRG. The VRG then significantly increases the strength of both inspiratory and expiratory signals, leading to a deeper and more rapid breathing pattern. II. Pontine Respiratory Centers (Pontine Respiratory Group – PRG) The pons contains centers that modify and fine-tune the activity of the medullary respiratory centers, ensuring smooth transitions between inspiration and expiration. These are often collectively referred to as the Pontine Respiratory Group (PRG) and include the Pneumotaxic and Apneustic centers. A. Pneumotaxic Center Upper Pons (Nucleus Parabrachialis) Primary Function: Primarily acts to limit inspiration and fine-tune the respiratory rate. It essentially “switches off” the inspiratory ramp signal from the DRG. Effect: By shortening the inspiratory phase, it leads to: Decreased tidal volume (shallower breaths). Increased respiratory rate. Analogy: Think of it as an “off switch” or a “brake” for inspiration. A strong pneumotaxic signal reduces the duration of inspiration. Clinical Significance: Damage to this center can lead to prolonged inspiration and decreased respiratory rate. B. Apneustic Center Lower Pons Primary Function: Has an excitatory effect on the medullary inspiratory neurons, particularly the DRG. It essentially prolongs inspiration. Effect: If unopposed by the pneumotaxic center, it would lead to: Prolonged, gasping inspirations followed by brief, insufficient expirations (a breathing pattern called apneusis). Interaction with Pneumotaxic Center: Normally, the pneumotaxic center overrides the apneustic center, preventing prolonged inspiration and ensuring rhythmic breathing. Clinical Significance: Damage to the pneumotaxic center or vagal nerves (which also inhibit inspiration) can allow the apneustic center to dominate, leading to apneustic breathing. Summary of Brainstem Control Medulla (DRG & VRG): Generates the basic rhythm of breathing. DRG for quiet inspiration; VRG for forceful inspiration/expiration and contains the pacemaker (pre-Bötzinger complex). Pons (Pneumotaxic & Apneustic): Modulates the medullary centers. Pneumotaxic center limits inspiration and increases rate; Apneustic center prolongs inspiration. This intricate interplay of neural centers ensures that breathing is a continuous, rhythmic process that can be finely adjusted to meet the body’s changing metabolic demands. Objective 2: Explain the roles of central chemoreceptors in regulating breathing. The chemical control of respiration is paramount for maintaining arterial blood gas homeostasis (PCO2, PO2, and pH). Chemoreceptors are specialized sensory receptors that detect changes in the chemical composition of the blood and cerebrospinal fluid (CSF) and send signals to the respiratory centers in the brainstem to adjust ventilation accordingly. Central chemoreceptors are the most potent and important regulators of ventilation under normal physiological

Gas Exchange and Transport
Physiology

Gas Exchange and Transport

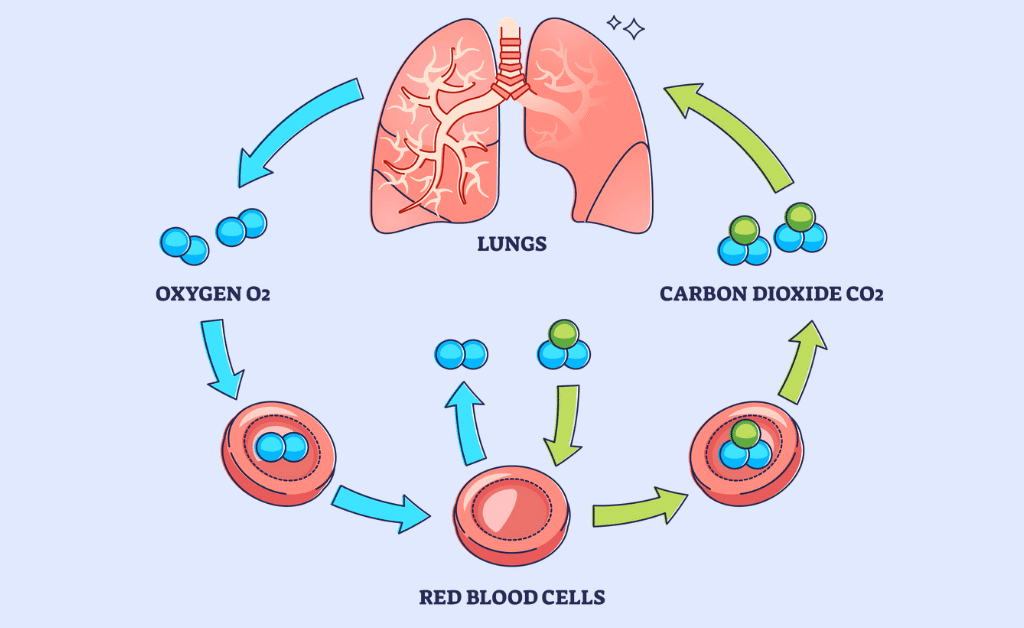
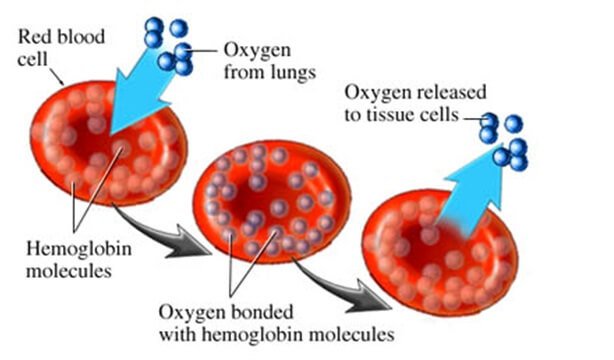
Gas Exchange &: Transport Gas Exchange and Transport Gas exchange is the process by which oxygen and carbon dioxide move between the lungs and the bloodstream, driven by simple diffusion along partial pressure gradients. This is coupled with the transport of these gases throughout the body via the circulatory system, primarily using hemoglobin in red blood cells. The entire process involves two main stages: I. External Respiration (in the Lungs) This is the exchange of gases between the air in the alveoli and the blood in the pulmonary capillaries. Oxygen uptake: Inhaled air has a high partial pressure of oxygen (PO2 ≈ 100 mmHg) in the alveoli, while the deoxygenated blood in the capillaries has a low PO2 ≈ 40 mmHg. This gradient causes oxygen to diffuse rapidly from the alveoli into the blood. Carbon dioxide release: The deoxygenated blood in the capillaries has a higher partial pressure of carbon dioxide (PCO2 ≈ 45 mmHg) compared to the air in the alveoli (PCO2 ≈ 40 mmHg). This causes carbon dioxide to diffuse from the blood into the alveoli to be exhaled. II. Internal Respiration (in the Tissues) This is the exchange of gases between the blood in systemic capillaries and the body’s tissue cells. Oxygen release: Oxygenated blood arriving at the tissues has a high PO2 ≈ 100 mmHg, while the metabolizing tissue cells have a low PO2 < 40 mmHg due to continuous consumption for cellular respiration. This gradient causes oxygen to dissociate from hemoglobin and diffuse into the cells. Carbon dioxide uptake: Tissue cells produce carbon dioxide as a waste product, resulting in a high PCO2 > 45 mmHg compared to the blood in the capillaries (PCO2 ≈ 40 mmHg). Carbon dioxide diffuses from the cells into the blood. Objective 1: Describe the partial pressures of oxygen and carbon dioxide in atmospheric air, alveoli, arterial blood, and venous blood. To understand gas exchange, we first need to grasp the concept of partial pressure. 1. Dalton’s Law of Partial Pressures Dalton’s Law states that in a mixture of non-reacting gases, the total pressure exerted is equal to the sum of the partial pressures of the individual gases. Ptotal = P1 + P2 + P3 + … Pn Where Ptotal is the total pressure of the gas mixture and P1, P2, etc. are the partial pressures of each individual gas. The partial pressure of an individual gas in a mixture is the pressure that gas would exert if it alone occupied the volume. It is directly proportional to its percentage concentration in the mixture. Partial Pressure of Gas (Px) = % Concentration of Gas x Total Pressure Example Calculation (Atmospheric Air at Sea Level): Total Pressure = 760 mmHg. Composition: Nitrogen (N2): ~79% Oxygen (O2): ~21% Carbon Dioxide (CO2): ~0.04% PO2 = 0.21 x 760 mmHg = ~160 mmHg 2. Partial Pressures in Different Locations Gases always diffuse down their partial pressure gradients from an area of higher partial pressure to an area of lower partial pressure. This is the driving force for gas exchange. Let’s examine the typical partial pressures of Oxygen (O2) and Carbon Dioxide (CO2) in four key locations: A. Atmospheric (Inspired) Air (at sea level, dry) This is the air we breathe in. PO2 (Atmospheric): Percentage: ~21% 0.21 x 760 = ~160 mmHg PCO2 (Atmospheric): Percentage: ~0.04% 0.0004 x 760 = ~0.3 mmHg (often rounded to 0 mmHg) B. Alveolar Air As atmospheric air enters the lungs, it mixes with the air already present in the dead space and alveoli, and it becomes saturated with water vapor. This significantly alters the partial pressures. Influencing Factors: Water Vapor: At 37°C, water vapor pressure is 47 mmHg. This dilutes other gases (Effective pressure: 760 – 47 = 713 mmHg). Gas Diffusion: CO2 continuously enters from blood; O2 continuously leaves into blood. PO2 (Alveolar – PAO2): ~104 mmHg Lower than atmospheric due to water vapor dilution and O2 diffusion into blood. PCO2 (Alveolar – PACO2): ~40 mmHg Higher than atmospheric due to CO2 diffusion from blood. C. Arterial Blood This is the blood leaving the pulmonary capillaries (oxygenated blood) and traveling to the systemic tissues. PO2 (Arterial – PaO2): ~95-100 mmHg Slightly lower than alveolar PO2 due to physiological shunts (bronchial circulation). PCO2 (Arterial – PaCO2): ~40 mmHg Same as alveolar PCO2; high solubility allows rapid equilibration. D. Venous Blood (Mixed Venous Blood) This is the blood returning to the lungs from the systemic tissues, carrying metabolic waste products. PO2 (Mixed Venous – PvO2): ~40 mmHg Lower than arterial because O2 was delivered to tissues. PCO2 (Mixed Venous – PvCO2): ~45 mmHg Higher than arterial because CO2 was picked up from tissues. Summary of Partial Pressures (Approximate Values at Sea Level) Location PO2 (mmHg) PCO2 (mmHg) Atmospheric Air 160 0.3 Alveolar Air 104 40 Arterial Blood 95-100 40 Mixed Venous Blood 40 45 Key Gradients for Gas Exchange O2 gradient for diffusion (Alveoli to Pulmonary Capillaries): 104 mmHg (alveolar) – 40 mmHg (venous) = 64 mmHg CO2 gradient for diffusion (Pulmonary Capillaries to Alveoli): 45 mmHg (venous) – 40 mmHg (alveolar) = 5 mmHg Note: Notice the much larger gradient for O2 compared to CO2. This is important because CO2 is much more soluble than O2, allowing it to diffuse efficiently even with a smaller pressure gradient. Checkpoint Question: Why is the partial pressure of oxygen in the alveoli (PAO2) significantly lower than the partial pressure of oxygen in atmospheric air (PO2)? Objective 2: Explain the principles governing gas exchange across the alveolar-capillary membrane (e.g., Dalton’s Law, Henry’s Law, Fick’s Law of Diffusion). Gas exchange, both between the alveoli and pulmonary capillaries, and between systemic capillaries and tissues, is driven by fundamental physical laws. We’ve already touched upon Dalton’s Law of Partial Pressures, which establishes the pressure gradient for individual gases. Now let’s integrate Henry’s Law and Fick’s Law of Diffusion to understand how these gases actually move and dissolve. 1. Dalton’s Law of Partial Pressures (Recap) Principle: The total pressure exerted by a mixture of gases is

Mechanics of Breathing (Pulmonary Ventilation)
Physiology

Mechanics of Breathing (Pulmonary Ventilation)

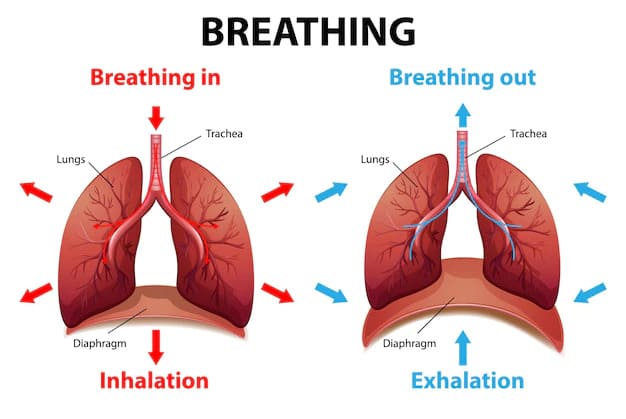
Mechanics of Breathing : Pulmonary Ventilation Mechanics of Breathing (Pulmonary Ventilation) The mechanics of breathing (pulmonary ventilation) involve creating pressure changes in the thoracic cavity to move air in (inspiration) and out (expiration) of the lungs, driven by muscle contraction and elastic recoil. During inhalation, the diaphragm and intercostal muscles contract, expanding the chest cavity, which lowers pressure, causing air to flow in (Boyle’s Law). Exhalation is usually passive, as muscles relax, the cavity shrinks, pressure increases, and air is pushed out, relying on lung elasticity. Precisely, Pulmonary ventilation, also known as breathing, involves the movement of air into and out of the lungs. Inspiration (inhalation) is an active process primarily driven by muscle contractions, such as the diaphragm. Objective 1: Identify and define the key pressures involved in the respiratory cycle, and explain the significance of each pressure, particularly the negative intrapleural pressure and positive transpulmonary pressure, in maintaining lung expansion. To understand how air moves into and out of the lungs, it’s crucial to grasp the various pressure gradients that drive this process. These pressures are always described relative to each other and, often, relative to atmospheric pressure. 1. Atmospheric Pressure (Patm) Definition: Atmospheric pressure is the pressure exerted by the column of air surrounding the Earth’s surface. It’s the “weight” of the air above us. Typical Value: At sea level, Patm is approximately 760 millimeters of mercury (mmHg) or 1 atmosphere (atm). This is equivalent to about 1033 cm H2O. Reference Point: In respiratory physiology, atmospheric pressure is often set as the reference point (0 mmHg or 0 cm H2O). This simplification allows us to discuss other pressures as positive (higher than atmosphere) or negative (lower than atmosphere) values. Significance: Air, like any fluid, moves from an area of higher pressure to an area of lower pressure. Therefore, differences between atmospheric pressure and pressures within the respiratory system are what ultimately drive the bulk flow of air during breathing. 2. Intrapulmonary Pressure (Ppul) / Alveolar Pressure (Palv) Definition: This is the pressure within the alveoli, the air sacs deep within the lungs where gas exchange occurs. It represents the pressure of the air inside the lungs. Characteristics and Changes during Breathing: Between Breaths (End-Expiration or End-Inspiration): At the end of a normal breath, when airflow momentarily ceases, Ppul equilibrates with Patm. Therefore, Ppul = 0 mmHg (relative to atmospheric). During Inspiration: For air to flow into the lungs from the atmosphere, Ppul must become lower than Patm. As the thoracic cavity expands (due to muscle contraction), the lung volume increases. According to Boyle’s Law (Volume and Pressure are inversely proportional), this increase in volume causes the pressure within the alveoli to drop slightly below atmospheric pressure (e.g., Ppul = -1 to -3 mmHg). This negative pressure gradient (Patm > Ppul) draws air into the lungs. During Expiration: For air to flow out of the lungs into the atmosphere, Ppul must become higher than Patm. As the thoracic cavity decreases in volume (due to elastic recoil of the lungs and chest wall), the lung volume decreases. This decrease in volume causes the pressure within the alveoli to rise slightly above atmospheric pressure (e.g., Ppul = +1 to +3 mmHg). This positive pressure gradient (Ppul > Patm) pushes air out of the lungs. Significance: Ppul is the direct driving force for airflow. Its fluctuations above and below atmospheric pressure determine the direction of air movement. 3. Intrapleural Pressure (Pip) Definition: This is the pressure within the pleural cavity—the narrow, fluid-filled space between the visceral pleura (lining the lungs) and the parietal pleura (lining the thoracic wall). Key Characteristic: Always Negative During normal breathing, Pip is always negative relative to both Patm and Ppul. At rest (between breaths), Pip is typically around -4 mmHg (-5 cm H2O). During inspiration, as the chest expands, it becomes even more negative (e.g., -6 to -8 mmHg). During expiration, it becomes less negative, returning towards -4 mmHg. Why is Pip always negative? This is a critical concept and results from two opposing elastic forces: 1. Lungs’ Natural Tendency to Recoil The elastic connective tissue within the lung parenchyma (especially around the alveoli) constantly pulls the lungs inward, trying to collapse them down to their smallest possible size. This creates an outward-pulling force on the visceral pleura. 2. Chest Wall’s Natural Tendency to Expand The thoracic wall (ribs, sternum, diaphragm) has its own natural elasticity, tending to spring outwards, increasing the volume of the thoracic cavity. This creates an inward-pulling force on the parietal pleura. These two opposing forces pull on the fluid in the pleural cavity, creating a “suction” effect that results in a sub-atmospheric (negative) pressure. The thin layer of pleural fluid, due to its surface tension, also acts as an adhesive, effectively “sticking” the two pleurae together, preventing the lungs from pulling away from the chest wall. Significance: The persistent negative intrapleural pressure is essential for: Maintaining Lung Expansion: It acts as a “suction” that keeps the lungs inflated and prevents them from collapsing due to their natural elastic recoil. Without this negative pressure, the lungs would collapse (atelectasis). Coupling Lung and Chest Wall Movement: It ensures that as the chest wall expands and contracts, the lungs follow suit, enabling effective changes in lung volume. Clinical Relevance: If the integrity of the pleural cavity is compromised (e.g., by a puncture wound, ruptured bleb), air can enter the pleural space, causing the Pip to equalize with Patm. This condition is called a pneumothorax, and without the negative Pip, the lung will collapse due to its inherent elastic recoil. 4. Transpulmonary Pressure (Ptp) Definition: Transpulmonary pressure is the pressure difference between the intrapulmonary pressure (Ppul) and the intrapleural pressure (Pip). Ptp = Ppul – Pip Key Characteristic: Always Positive: Since Pip is always negative relative to Ppul (and Patm), the transpulmonary pressure is always a positive value during normal breathing. For example: If Ppul = 0 mmHg and Pip = -4 mmHg, then Ptp = 0 – (-4) = +4 mmHg. Significance: Transpulmonary

Scroll to Top