
Antidepressant Drugs: Classification, Pharmacology and Safe Clinical Use
On this page
1 Overview
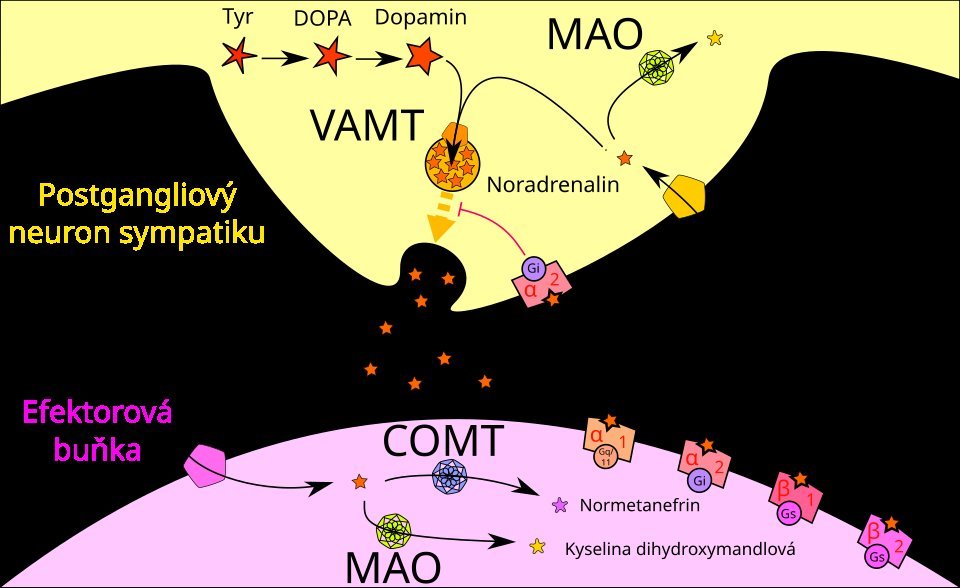
Antidepressants increase synaptic availability of monoamines — serotonin (5-HT), noradrenaline (NA) and dopamine (DA) — through reuptake blockade, receptor modulation or monoamine oxidase inhibition. The SSRIs are first-line for most depressive and anxiety disorders because they are effective and markedly safer than the older tricyclics and MAOIs, especially in overdose. Safe use means mastering a handful of recurring themes: therapeutic lag, class-specific adverse effects, discontinuation syndrome, serotonin syndrome, and toxicity in overdose.
2 Learning Objectives
- Explain the monoamine hypothesis and the reuptake/metabolism mechanisms of each class.
- Compare SSRIs, SNRIs, TCAs, MAOIs and atypical agents — efficacy, adverse effects, overdose risk.
- Select rationally using patient factors (age, comorbidity, suicide risk, symptoms).
- Manage the therapeutic lag, treatment duration, switching rules and discontinuation symptoms.
- Recognise and treat serotonin syndrome and antidepressant poisoning.
3 The Monoamine Rationale (and its Limits)
Depression associates with deficient monoamine signalling; reuptake inhibitors raise extracellular 5-HT/NA within hours, yet mood improves only after 2–4 weeks. The lag implies that benefit comes from slow postsynaptic receptor adaptations and neuroplasticity changes (including BDNF upregulation), not the acute chemistry. Monoamine deficiency is therefore a useful pharmacological handle rather than the whole disease — which is why antidepressants help whatever the "cause" (endogenous, reactive, post-stroke, somatic illness) and why combining psychological therapy improves outcomes.
4 Classes in Detail
SSRIs — selective serotonin reuptake inhibitors
Fluoxetine, sertraline, citalopram, escitalopram, paroxetine, fluvoxamine. Block SERT → ↑ synaptic serotonin; minimal action on NA/DA, cholinergic, histaminergic or adrenergic receptors, hence the safety margin. First-line for depression, GAD, panic, OCD, PTSD, social anxiety and bulimia (fluoxetine). Dosed once daily; start low in anxiety disorders (initial jitteriness). Common adverse effects: nausea, diarrhoea, insomnia or somnolence, headache, sexual dysfunction (the commonest cause of non-adherence), and hyponatraemia/SIADH in the elderly. Citalopram/escitalopram prolong QT (dose caps). Fluoxetine is a strong CYP2D6 inhibitor; sertraline is preferred in pregnancy among SSRIs. Overdose: lowest toxicity of all classes.
SNRIs — serotonin–noradrenaline reuptake inhibitors
Venlafaxine, duloxetine. Dual reuptake blockade: stronger NA effect at higher doses. Useful when an energy/fatigue-predominant depression, or coexisting neuropathic pain (duloxetine) or stress incontinence (duloxetine). Adverse effects: nausea, hypertension at higher venlafaxine doses (monitor BP), sweating, discontinuation symptoms prominent with venlafaxine. Overdose risk: cardiotoxicity and seizures — more dangerous than SSRIs, caution in suicidal patients.
TCAs — tricyclic antidepressants
Amitriptyline, imipramine, clomipramine, nortriptyline, dosulepin. Block 5-HT and NA reuptake plus muscarinic, histamine H1 and α1-adrenergic receptors. Efficacy equals SSRIs but adverse effects are the "triple A" burden: anticholinergic (dry mouth, constipation, urinary retention, blurred vision, confusion in elderly), anti-histaminic (sedation, weight gain) and anti-adrenergic (postural hypotension); plus QT prolongation and heart block. The most dangerous antidepressants in overdose — seizures and arrhythmias from Na-channel blockade (wide QRS → sodium bicarbonate); the main reason SSRIs displaced them in depression. Modern niche uses where anticholinergic/sedation is therapeutic: neuropathic pain (low-dose amitriptyline), migraine prophylaxis, nocturnal enuresis (imipramine), OCD (clomipramine).
MAOIs — monoamine oxidase inhibitors
Phenelzine, tranylcypromine, isocarboxazid (irreversible, non-selective) and the reversible MAO-A inhibitor moclobemide. Inhibit monoamine breakdown → ↑ 5-HT, NA, DA. Third-line for atypical or treatment-resistant depression (with reversed vegetative symptoms, hypersomnia, rejection sensitivity). The cost is interaction vigilance: hypertensive crisis with tyramine-rich foods (cheese, cured meats, fermented products) from NA potentiation — hence dietary restriction; and serotonin syndrome with any serotonergic drug — require washout intervals (14 days between MAOIs and SSRIs/SNRIs/TCAs; fluoxetine needs ~5 weeks). Moclobemide is gentler (reversible, selective) but still interacts.
Atypical agents
- Mirtazapine — presynaptic α2 antagonist (disinhibits 5-HT/NA release) with H1 antagonism: sedating and appetite-stimulating — best when depression has insomnia, weight loss, anxiety; fewer sexual effects and little nausea.
- Bupropion — NA/DA reuptake inhibitor: activating, weight-neutral, minimal sexual dysfunction; contraindicated in epilepsy and eating disorders (lowers seizure threshold).
- Trazodone — 5-HT2 antagonist + weak reuptake blockade: sedating; used at low dose for insomnia; priapism is its rare signature risk.
- Esketamine — intranasal NMDA antagonist for treatment-resistant depression under supervision; rapid onset (days), dissociative effects, misuse potential.
- Agomelatine — melatonin MT1/MT2 agonist + 5-HT2C antagonist: sleep-wake restoring, monitor LFTs; not available everywhere.
5 Drug Monographs: Doses, Indications & Safety
One full monograph per representative drug, in the same exam-ready structure: mechanism → indications → adult dose → paediatric dose → adverse effects → contraindications → interactions → patient advice. Doses are standard teaching doses — confirm against the current Uganda Clinical Guidelines before prescribing.
Fluoxetine (SSRI)
Scroll the table sideways on a smaller screen.
| Fluoxetine — selective serotonin reuptake inhibitor | |
|---|---|
| Mechanism | Blocks the serotonin transporter (SERT) → increased synaptic 5-HT; minimal receptor affinity; long-acting metabolite norfluoxetine (half-life ~1 week) |
| Indications | Major depression, OCD, bulimia nervosa, panic disorder; best-evidenced antidepressant in children and adolescents |
| Adult dose | 20 mg once daily (morning); usual 20–60 mg/day; onset of effect 2–4 weeks |
| Paediatric dose | Depression ≥8 years: 10 mg/day start, max 20 mg/day; OCD ≥7 years: 10 mg start, up to 60 mg/day (adolescents) |
| Adverse effects | Nausea, insomnia, agitation/anxiety, headache, sexual dysfunction, hyponatraemia (elderly); low overdose toxicity |
| Contraindications | MAOIs (washout: stop fluoxetine 5 weeks before starting MAOI); pimozide, thioridazine |
| Interactions | Strong CYP2D6 inhibitor — raises levels of TCAs, some antipsychotics, beta-blockers, tamoxifen (may reduce its activation); serotonergic combinations (tramadol, linezolid, triptans, St John's Wort) → serotonin syndrome |
| Patient advice / monitoring | Take in the morning (can be activating); warn of 2–4 week lag and initial jitteriness; report worsening mood or suicidal thoughts, especially in the young; long half-life → milder discontinuation symptoms than paroxetine/venlafaxine |
Sertraline (SSRI)
Scroll the table sideways on a smaller screen.
| Sertraline — selective serotonin reuptake inhibitor | |
|---|---|
| Mechanism | SERT blockade → increased synaptic 5-HT; also weakly inhibits dopamine reuptake at high doses; milder CYP profile than fluoxetine |
| Indications | Depression, OCD, panic disorder, PTSD, social anxiety disorder; preferred SSRI in pregnancy and breastfeeding |
| Adult dose | 50 mg once daily (any time); usual 50–200 mg/day after 1+ weeks |
| Paediatric dose | OCD: 6–12 years 25 mg start (max 200 mg); ≥13 years 50 mg start (max 200 mg) |
| Adverse effects | Nausea, diarrhoea, indigestion, dizziness, insomnia or somnolence, sexual dysfunction, hyponatraemia in the elderly |
| Contraindications | MAOIs, pimozide; disulfiram with oral concentrate |
| Interactions | Serotonergic drugs (syndrome risk); modest CYP2D6 inhibition; bleeding risk with NSAIDs/anticoagulants |
| Patient advice / monitoring | Take with food to reduce nausea; same time each day; expect benefit over 2–4 weeks; report unusual bleeding, confusion or fainting (SIADH) |
Venlafaxine (SNRI)
Scroll the table sideways on a smaller screen.
| Venlafaxine — serotonin–noradrenaline reuptake inhibitor | |
|---|---|
| Mechanism | Blocks SERT and NET; noradrenergic effect predominates at higher doses (≥150 mg/day) |
| Indications | Major depression (including more severe, anergic presentations), generalised anxiety disorder, social anxiety, panic disorder |
| Adult dose | Start 37.5 mg once daily (ER); usual 75–225 mg/day; >150 mg/day monitor blood pressure |
| Paediatric dose | Not routinely recommended — specialist use only (OCD evidence is limited) |
| Adverse effects | Nausea, sweating, dizziness, insomnia, sexual dysfunction; dose-related hypertension; anxiety at initiation |
| Contraindications | MAOIs; uncontrolled hypertension (caution) |
| Interactions | Serotonergic drugs (tramadol, triptans, St John's Wort); CYP2D6 inhibitors raise levels; alcohol and sedatives additive |
| Patient advice / monitoring | Never stop abruptly — worst discontinuation syndrome of the class ("electric shock" sensations, dizziness, irritability); taper over ≥2–4 weeks; monitor BP at higher doses; avoid in patients with high overdose risk until alternatives fail |
Duloxetine (SNRI)
Scroll the table sideways on a smaller screen.
| Duloxetine — serotonin–noradrenaline reuptake inhibitor | |
|---|---|
| Mechanism | Blocks SERT and NET in CNS — analgesic effect in neuropathic pain; minimal muscarinic/α1 affinity |
| Indications | Depression, generalised anxiety, diabetic peripheral neuropathic pain, fibromyalgia, chronic musculoskeletal pain; stress urinary incontinence (where licensed) |
| Adult dose | Start 30 mg once daily → usual 60 mg/day (max 120 mg/day) |
| Paediatric dose | GAD: 7–17 years 30 mg start, max 60 mg (specialist) |
| Adverse effects | Nausea, dry mouth, dizziness, insomnia or somnolence, sweating, constipation; hypertension; rare hepatotoxicity |
| Contraindications | MAOIs; substantial alcohol use or chronic liver disease; severe renal impairment (GFR <30) |
| Interactions | Serotonergic drugs; CYP1A2/2D6 substrates; potent CYP1A2 inhibitors (ciprofloxacin, fluvoxamine) raise levels |
| Patient advice / monitoring | Same time daily, with or without food; avoid heavy alcohol; report abdominal pain, jaundice; don't stop abruptly |
Amitriptyline (TCA)
Scroll the table sideways on a smaller screen.
| Amitriptyline — tricyclic antidepressant | |
|---|---|
| Mechanism | Blocks 5-HT and NA reuptake; potent muscarinic, histamine-H1 and α1-adrenergic antagonism |
| Indications | Second-line depression; neuropathic pain (low-dose); migraine prophylaxis; IBS; nocturnal sedation |
| Adult dose | Depression: 75 mg at night, up to 150–200 mg/day; neuropathic pain: 10–25 mg at night (max 75–100 mg) |
| Paediatric dose | Not first-line in depression; low-dose use for pain under specialist guidance |
| Adverse effects | Dry mouth, sedation, constipation, blurred vision, urinary retention, postural hypotension, weight gain, QT prolongation; delirium in the elderly |
| Contraindications | Recent myocardial infarction, heart block/arrhythmia, acute porphyria, narrow-angle glaucoma, urinary retention; avoid in overdose-risk patients |
| Interactions | CYP2D6 inhibitors (fluoxetine, paroxetine, bupropion) raise TCA levels → toxicity; additive anticholinergics (antihistamines, antipsychotics); alcohol potentiates sedation; quinidine-like conduction effects |
| Patient advice / monitoring | Take at night (sedation); rise slowly (postural hypotension); sugar-free gum for dry mouth; report palpitations or syncope; prescribe small quantities when suicide risk exists; most cardiotoxic antidepressant in overdose — wide QRS needs sodium bicarbonate |
Imipramine (TCA)
Scroll the table sideways on a smaller screen.
| Imipramine — tricyclic antidepressant | |
|---|---|
| Mechanism | Blocks 5-HT and NA reuptake; anticholinergic, antihistaminergic and anti-adrenergic activity |
| Indications | Depression (second-line); nocturnal enuresis in children; panic disorder |
| Adult dose | Depression: 75 mg at night, up to 150–200 mg/day |
| Paediatric dose | Nocturnal enuresis ≥6 years: 25 mg (6–8 years), 50 mg (9–11 years), 75 mg (≥12 years) at night — short-term, last-resort only, after behavioural measures |
| Adverse effects | Sedation, dry mouth, constipation, postural hypotension, tachycardia, sweating, appetite change; dangerous in overdose |
| Contraindications | As for amitriptyline; caution in children with cardiac conduction abnormalities |
| Interactions | CYP2D6 inhibitors raise levels; additive anticholinergics; MAOIs (serotonin syndrome/hypertension) |
| Patient advice / monitoring | For enuresis: use enuresis alarm and fluid restriction first; review regularly, stop after 2–3 months and reassess; cardiotoxic in overdose |
Mirtazapine (atypical)
Scroll the table sideways on a smaller screen.
| Mirtazapine — presynaptic α2 antagonist + H1 antagonist | |
|---|---|
| Mechanism | Blocks presynaptic α2 autoreceptors (disinhibits 5-HT and NA release); potent H1 antagonism → sedation and appetite stimulation |
| Indications | Depression with insomnia, poor appetite, weight loss or marked anxiety; elderly; nausea on SSRIs; minimal sexual dysfunction |
| Adult dose | 15 mg at night; usual 30–45 mg/day (single bedtime dose) |
| Paediatric dose | Not licensed — specialist use only |
| Adverse effects | Sedation (marked first 1–2 weeks, then tolerance), increased appetite, weight gain, dry mouth, dizziness; rare agranulocytosis |
| Contraindications | MAOIs; rare hypersensitivity |
| Interactions | Few CYP interactions; additive sedation with benzodiazepines, alcohol, opioids |
| Patient advice / monitoring | Take at night; sedation eases after 1–2 weeks — reassure patient; monitor weight (caution in diabetes/obesity); report fever or sore throat (blood count) |
Bupropion (atypical)
Scroll the table sideways on a smaller screen.
| Bupropion — noradrenaline–dopamine reuptake inhibitor | |
|---|---|
| Mechanism | Blocks NET and DAT → increased noradrenergic and dopaminergic transmission; also non-competitive nicotinic antagonist |
| Indications | Depression with fatigue/hypersomnia; smoking cessation; weight-conscious or SSRI sexual-dysfunction patients |
| Adult dose | 150 mg once daily morning → 150 mg twice daily or SR 300 mg once morning (max 450 mg/day) |
| Paediatric dose | Not established |
| Adverse effects | Insomnia, dry mouth, headache, nausea, anxiety, tremor, sweating; seizures (dose-related) |
| Contraindications | Epilepsy and eating disorders (bulimia/anorexia) — seizure risk; MAOIs; abrupt alcohol or benzodiazepine withdrawal |
| Interactions | CYP2B6 inhibitors (clopidogrel) raise levels; CYP2D6 inhibitor; stimulants and other seizure-lowering drugs additive |
| Patient advice / monitoring | Morning dosing only (insomnia); never crush or split extended-release; avoid evening doses and excess caffeine; report any seizure immediately |
6 Comparison Table
Scroll the table sideways on a smaller screen.
| Class | Mechanism | First-line use | Characteristic adverse effects | Overdose danger |
|---|---|---|---|---|
| SSRIs | SERT blockade | Depression, anxiety disorders, OCD, PTSD | Nausea, insomnia, sexual dysfunction, SIADH, QT (citalopram) | Low |
| SNRIs | SERT + NET blockade | Depression with fatigue; neuropathic pain (duloxetine) | Nausea, hypertension (venlafaxine), sweating | Moderate (seizures, cardiotoxicity) |
| TCAs | SERT/NET blockade + muscarinic/H1/α1 | Neuropathic pain, migraine, enuresis, OCD (clomipramine) | Anticholinergic, sedation, weight gain, postural hypotension, heart block | High (arrhythmia, seizures) |
| MAOIs | Monoamine oxidase inhibition | Atypical, resistant depression | Tyramine crisis, serotonin syndrome, insomnia | High + interactions |
| Mirtazapine | α2 antagonist + H1 | Depression with insomnia/weight loss | Sedation, weight gain | Low–moderate |
| Bupropion | NET/DAT blockade | Depression (activation), smoking cessation | Insomnia, anxiety; seizures | Moderate (seizures) |
7 Choosing an Agent
- Default — an SSRI (sertraline or escitalopram are clean choices): effective, safe, cheap, treat comorbid anxiety.
- Match to symptoms — insomnia/poor appetite → mirtazapine; fatigue/anergia → SNRI or bupropion; sexual dysfunction on SSRI → switch to mirtazapine/bupropion; chronic pain → SNRI or low-dose TCA.
- Match to comorbidity — cardiac disease/conduction disease → avoid TCAs; epilepsy → avoid bupropion; elderly → avoid TCAs and watch SIADH with SSRIs/SNRIs; prostatism/glaucoma → avoid TCAs.
- Suicide risk — overdose danger drives choice: SSRIs > mirtazapine > SNRIs; avoid TCAs and MAOIs in high-risk patients; prescribe small quantities.
- Interactions — check serotonergic load (tramadol, linezolid, St John's Wort, triptans), CYP inhibitors (fluoxetine/paroxetine), and never combine with MAOIs.
8 Onset, Duration & Switching
- Therapeutic lag — expect partial response by 2 weeks, clear benefit by 4–6; counsel the patient explicitly or they will stop early ("it isn't working").
- Adequate trial — 6–8 weeks at a therapeutic dose before declaring non-response.
- Continuation — continue at the same dose for 6–9 months after remission to prevent relapse; longer (≥2 years) after recurrent episodes.
- Stopping — taper over weeks (paroxetine, venlafaxine shortest half-lives, worst symptoms): discontinuation syndrome = dizziness, "electric shock" sensations, irritability, insomnia, nausea; distinguish from relapse (onset within days, rapid resolution, physical symptoms).
- Switching — cross-taper within/between most classes is possible; to or from MAOIs needs washout (≥14 days; fluoxetine → 5 weeks).
9 Safety: Serotonin Syndrome & Overdose
Serotonin syndrome
Excess serotonergic activity from combining serotonergic agents (SSRI + MAOI, SSRI + tramadol/linezolid/triptan/St John's Wort; MAOIs cause the most severe cases). Triad: mental status change (agitation, confusion), autonomic hyperactivity (fever, tachycardia, hypertension, sweating, diarrhoea), neuromuscular hyperexcitability (tremor, hyperreflexia — especially lower limbs, myoclonus). Onset hours after the trigger (distinguishes from NMS, which takes days, with lead-pipe rigidity). Management: stop all serotonergic drugs, supportive care, benzodiazepines for agitation; cyproheptadine (5-HT2A antagonist) in moderate–severe cases; cooling and intubation for severe hyperthermia.
Overdose
- SSRIs — usually mild (nausea, tachycardia, somnolence); citalopram: QT prolongation and seizures in large doses.
- SNRIs — venlafaxine: sedation, seizures, hypertension then cardiotoxicity; magnesium for torsades; severe cases may need ECLS.
- TCAs — anticholinergic signs (hot dry skin, dilated pupils, absent bowel sounds, urinary retention) + wide QRS, arrhythmias, seizures, coma. Management: ABC, sodium bicarbonate for QRS >100 ms, benzodiazepines for seizures; avoid class Ia/III antiarrhythmics.
- MAOIs — severe serotonin toxicity; delayed onset up to 24 h — observe.
- Bupropion — tachycardia, agitation, hallucinations and delayed seizures up to 48 h (extended-release) — observe at least 24 h.
10 Special Populations
- Children & adolescents — fluoxetine is the best-evidenced; all antidepressants carry a warning for increased suicidal ideation in young people — start low, review within 1–2 weeks, involve caregivers.
- Pregnancy — untreated depression also harms; sertraline (lowest breast-milk transfer) is a common choice; paroxetine avoided (cardiac malformations); neonatal adaptation syndrome if used late.
- Elderly — "start low, go slow"; watch SIADH, falls (TCAs/MAOIs), QT (citalopram); mirtazapine and SSRIs are usual choices.
- HIV and TB co-therapy — rifampicin induces metabolism of many antidepressants (esp. TCAs, some SSRIs); efavirenz adds neuropsychiatric effects — expect to adjust doses.
11 Viva & Exam Points
- First-line — SSRIs (SERT blockade): effective + safest in overdose.
- Therapeutic lag — 2–4 weeks; adequate trial 6–8 weeks; continue 6–9 months post-remission.
- Toxicity order — TCAs > MAOIs > venlafaxine/bupropion/mirtazapine > SSRIs.
- TCA overdose — anticholinergic + wide QRS + seizures; give sodium bicarbonate.
- Serotonin syndrome — triad, hours-onset; stop drug, benzos, cyproheptadine.
- MAOI rules — tyramine diet; 14-day washout (fluoxetine 5 weeks) with SSRIs.
- Choice by need — insomnia/weight loss → mirtazapine; activation/sexual-sparing → bupropion (avoid in epilepsy); pain → SNRI/TCA.
12 References
- Antidepressants. StatPearls. NCBI Bookshelf — classification, mechanisms, toxicity comparisons.
- Selective Serotonin Reuptake Inhibitors. StatPearls. NCBI Bookshelf — SERT mechanism and class effects.
- Tricyclic Antidepressants. StatPearls. NCBI Bookshelf — contraindications and toxicity.
- Serotonin Syndrome. StatPearls. NCBI Bookshelf — aetiology, recognition, management.
For education only. Apply current Uganda Clinical Guidelines and local protocols when managing patients.