Doctors Revision

Anatomy

Common Disorders of Tissues (1)
Anatomy

Common Disorders of Tissues

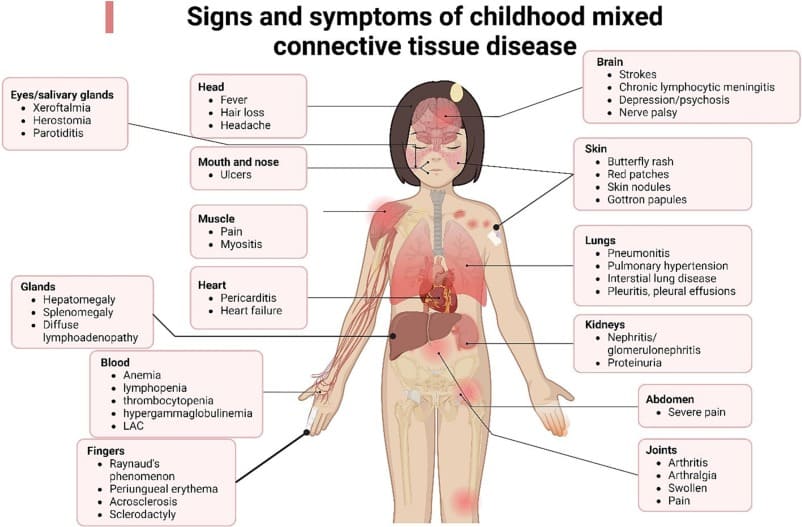
Common Disorders of Tissues Pathology Reference: Common Disorders of Tissues TISSUE PATHOLOGY Common Disorders of Tissues Connective tissues are one of the four basic types of animal tissue (along with epithelial, muscle, and nervous tissues). They are the most abundant and widely distributed of the primary tissues, playing a crucial role in binding, supporting, and protecting organs, as well as storing energy and providing immunity. Unlike epithelial tissue, which is primarily composed of cells, connective tissue is characterized by its extracellular matrix (ECM). Key Characteristics of Connective Tissues: Abundant Extracellular Matrix (ECM): This is the distinguishing feature. The ECM consists of two main components: Ground Substance: An amorphous gel-like material that fills the space between cells and fibers. It can be fluid, semi-fluid, gelatinous, or calcified. It contains water, proteoglycans, and glycoproteins. Protein Fibers: Provide strength and elasticity. Collagen fibers: Strongest and most abundant, providing high tensile strength (resistance to stretching). Elastic fibers: Composed of elastin, providing elasticity and recoil. Reticular fibers: Fine, branching collagenous fibers that form delicate networks, providing support in soft organs. Relatively Few Cells: Compared to epithelial tissue, connective tissues generally have fewer cells, which are often widely dispersed within the ECM. Vascularity: Most connective tissues are highly vascular (rich blood supply), though there are notable exceptions (e.g., cartilage is avascular, tendons and ligaments have limited vascularity). No Free Surface: Unlike epithelial tissue, connective tissue does not have a free surface exposed to the environment. Diverse Functions: Support, binding, protection, insulation, transport, and energy storage. Major Types of Connective Tissues and Their Functions Connective tissues are broadly categorized into several types, each with specialized functions and compositions of cells and ECM. A. Loose Connective Tissue (Areolar, Adipose, Reticular) These tissues have a relatively open, loose arrangement of fibers and a more abundant ground substance. 1. Areolar Connective Tissue Description: The most widely distributed connective tissue. It has a gel-like matrix with all three fiber types (collagen, elastic, reticular) loosely interwoven. Contains various cell types, including fibroblasts (most common), macrophages, mast cells, and some white blood cells. Location: Underlies epithelia; forms lamina propria of mucous membranes; packages organs; surrounds capillaries. Functions: Support and cushion: Provides flexible support. Fluid reservoir: Holds tissue fluid, acting as a “sponge.” Immunity: Plays a role in inflammation due to its high cell diversity. Binding: Connects skin to underlying structures. 2. Adipose Tissue (Fat Tissue) Description: Primarily composed of adipocytes (fat cells), which store triglycerides. These cells are so large that they push the nucleus and cytoplasm to the periphery, giving them a “signet ring” appearance. Very little ECM. Location: Under skin (subcutaneous), around kidneys and eyeballs, within abdomen, breasts. Functions: Energy storage: Primary site for long-term energy reserves. Insulation: Reduces heat loss through the skin. Protection/Cushioning: Protects organs from mechanical shock. Endocrine function: Produces hormones like leptin. 3. Reticular Connective Tissue Description: Contains a delicate network of reticular fibers (a type of collagen) in a loose ground substance. Reticular cells (a type of fibroblast) are prominent. Location: Lymphoid organs (lymph nodes, spleen, bone marrow), liver. Functions: Structural support (Stroma): Forms a soft internal framework (stroma) that supports blood cells, lymphocytes, and other cell types in lymphoid organs. B. Dense Connective Tissue These tissues have a high density of collagen fibers, providing significant strength. There is less ground substance and fewer cells than loose connective tissue. 1. Dense Regular Connective Tissue Description: Primarily parallel collagen fibers, providing great tensile strength in one direction. Fibroblasts are the main cell type, squeezed between collagen bundles. Poorly vascularized. Location: Tendons (muscle to bone), ligaments (bone to bone), aponeuroses (sheet-like tendons). Functions: Strong attachment: Connects muscles to bones (tendons) and bones to bones (ligaments). Resists unidirectional pull: Withstands great tensile stress when pulling force is applied in one direction. 2. Dense Irregular Connective Tissue Description: Primarily irregularly arranged collagen fibers. Some elastic fibers and fibroblasts. Provides tensile strength in multiple directions. Location: Dermis of the skin, fibrous capsules of organs and joints, submucosa of digestive tract. Functions: Structural strength: Withstands tension exerted in many directions. Protection: Forms protective capsules around organs. 3. Elastic Connective Tissue Description: Predominantly elastic fibers, allowing for significant stretch and recoil. Also contains some collagen fibers and fibroblasts. Location: Walls of large arteries (aorta), bronchial tubes, vocal cords, ligaments associated with vertebral column (ligamentum nuchae). Functions: Elasticity: Allows recoil of tissue following stretching. Pulsatile flow: Maintains pulsatile flow of blood through arteries; aids passive recoil of lungs following inspiration. C. Cartilage A specialized, semi-rigid connective tissue. It is avascular (lacks blood vessels) and aneural (lacks nerves), relying on diffusion from surrounding perichondrium for nutrients. Chondrocytes (cartilage cells) reside in lacunae (small cavities) within a solid, yet flexible, matrix. 1. Hyaline Cartilage Description: Most abundant type. Amorphous but firm matrix; imperceptible collagen fibers (type II); chondroblasts produce the matrix and, when mature, lie in lacunae as chondrocytes. Location: Covers the ends of long bones in joint cavities (articular cartilage), costal cartilage (ribs to sternum), nose, trachea, larynx. Functions: Support and cushioning: Supports and reinforces. Resilient cushioning: Has resilient properties. Reduces friction: Resists compressive stress at joints. 2. Elastic Cartilage Description: Similar to hyaline cartilage, but contains abundant elastic fibers in the matrix. Location: External ear (pinna), epiglottis. Functions: Flexibility and shape retention: Maintains the shape of a structure while allowing great flexibility. 3. Fibrocartilage Description: Matrix similar to hyaline cartilage but less firm, with thick collagen fibers (type I) predominant. Rows of chondrocytes alternating with thick collagen fibers. Location: Intervertebral discs, pubic symphysis, menisci of the knee. Functions: Tensile strength: Possesses tensile strength with the ability to absorb compressive shock. Shock absorption: Acts as a strong shock absorber. D. Bone (Osseous Tissue) A hard, rigid connective tissue. It is highly vascular and well-innervated. The hard matrix is primarily composed of collagen fibers and inorganic calcium salts (hydroxyapatite). Osteocytes (bone cells) reside in lacunae within the matrix. Description: Hard, calcified matrix containing many collagen fibers; osteocytes in lacunae. Very well vascularized. Functions: Support and protection, Leverage for movement (provides levers for muscles), Mineral storage
Mutations, Genetic Disorders, and Malignancy
Anatomy

Mutations, Genetic Disorders, and Malignancy

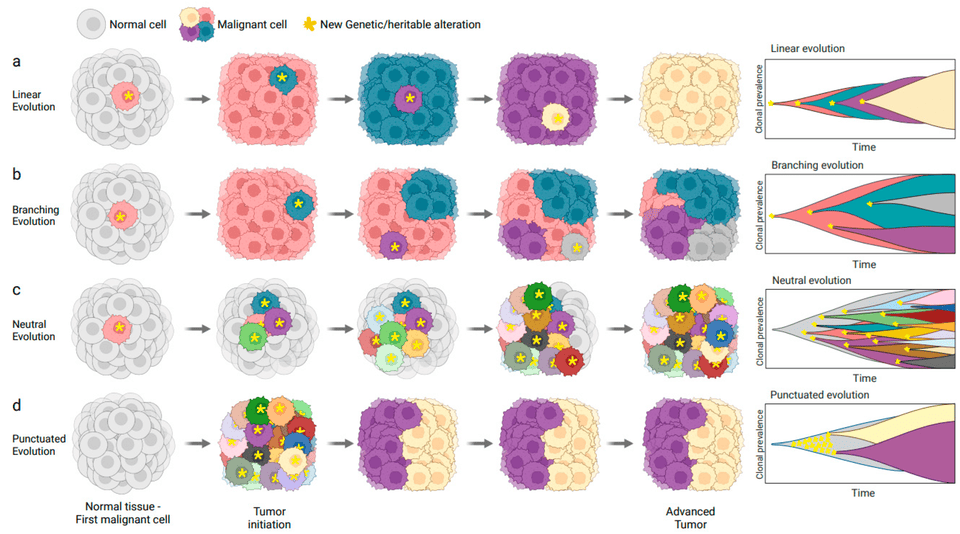
Mutations, Genetic Disorders & Malignancy Pathology: Mutations, Genetic Disorders, and Malignancy CELLULAR PATHOLOGY Mutations, Genetic Disorders & Malignancy At the heart of every living organism, from the simplest bacterium to the most complex human, lies the cell. Within each cell, the nucleus houses the genome – a meticulously organized instruction manual written in DNA. This manual dictates everything from cell structure and function to growth, division, and death. When this blueprint is altered, or when the cellular machinery designed to read and execute its instructions malfunctions, the consequences can range from subtle inefficiencies to devastating diseases. Our focus in this section is to lay down the precise definitions of three fundamental categories of cellular disorders: Mutations, Genetic Disorders, and Malignancy (Cancer). While intimately linked, they represent distinct levels of biological organization and clinical presentation. Understanding their individual definitions and how they relate to one another is crucial for grasping cellular pathology. Defining Key Terms A. Mutation Definition: A mutation is defined as a heritable change in the nucleotide sequence of the genetic material (DNA or RNA in some viruses). This change can involve a single base pair, a segment of a chromosome, or an entire chromosome. Mutations are the ultimate source of all genetic variation and serve as the raw material for evolution. However, they are also the primary cause of many diseases. Key Characteristics: Fundamental Unit of Change: A mutation is the most granular level of alteration in the genetic code. It’s a change to the DNA itself. Heritable: The change must be capable of being passed on to daughter cells during cell division (mitosis) or to offspring (meiosis, if in germ cells). Random Occurrence: Mutations are generally random events, not occurring in anticipation of beneficial or harmful effects. Variability in Impact: The consequences of a mutation can be: Neutral (Silent): No change in protein function or phenotype. Beneficial: Rare, providing an evolutionary advantage. Harmful (Pathogenic): Leading to disease or impaired function. Context: Mutations can occur in any cell of the body. Germline Mutations: Occur in germ cells (sperm or egg) and are heritable, meaning they can be passed down to offspring. Somatic Mutations: Occur in somatic cells (body cells) after conception. They are not heritable but can contribute to diseases in the affected individual, most notably cancer. B. Genetic Disorder Definition: A genetic disorder is a disease caused, in whole or in part, by a change in an individual’s DNA sequence. These disorders arise directly from specific mutations or abnormalities in the genome. The presence of these genetic alterations leads to an abnormal or absent gene product (protein), which in turn disrupts normal cellular function and manifests as a disease. Key Characteristics: Etiology: The primary cause is a genetic abnormality. Inherited or De Novo: Genetic disorders can be inherited from parents (germline mutations) or can arise spontaneously (de novo mutations) in the egg, sperm, or early embryonic development. Range of Presentation: They can present at any stage of life, from prenatal development to old age, and vary widely in severity and penetrance (the proportion of individuals with the mutation who express the phenotype). Predictable Inheritance Patterns: For many genetic disorders, their inheritance follows Mendelian patterns (e.g., autosomal dominant, recessive, X-linked), allowing for genetic counseling and risk assessment. Relationship to Mutation: A genetic disorder is the clinical manifestation of one or more underlying mutations. Without a mutation (or a chromosomal abnormality, which itself is a large-scale mutation), a genetic disorder cannot exist. The mutation is the cause; the genetic disorder is the effect/disease. C. Malignancy (Cancer) Definition: Malignancy, commonly known as cancer, is a broad group of diseases characterized by the uncontrolled growth and division of abnormal cells, with the ability to invade adjacent tissues (invasion) and spread to distant sites in the body (metastasis). These abnormal cells form masses called tumors (neoplasms), which can be benign (non-cancerous) or malignant (cancerous). Malignancy specifically refers to the latter. Key Characteristics: Uncontrolled Proliferation: Cancer cells ignore normal growth-regulating signals, leading to continuous and excessive cell division. Loss of Differentiation: Cancer cells often lose their specialized features and functions, becoming more primitive or anaplastic. Invasion: Malignant cells can breach normal tissue boundaries and infiltrate surrounding healthy tissues. Metastasis: The hallmark of malignancy, where cancer cells detach from the primary tumor, travel through the bloodstream or lymphatic system, and establish secondary tumors in distant organs. Genomic Instability: Cancer cells typically accumulate numerous genetic alterations (mutations) over time, contributing to their abnormal behavior. Relationship to Mutation: Cancer is fundamentally a disease of accumulated somatic mutations. It arises when a series of specific mutations occur in critical genes that control cell growth, division, differentiation, and DNA repair. While some cancers have an inherited genetic predisposition (due to germline mutations in cancer-susceptibility genes), the vast majority of cancers develop from a series of acquired somatic mutations throughout an individual’s lifetime. These mutations allow cells to bypass normal regulatory mechanisms and acquire the “hallmarks of cancer.” Differentiating and Recognizing Interconnectedness While all three terms are linked by changes in DNA, their scope and implications differ significantly: Mutation (The Event/Change): This is the fundamental alteration in the DNA sequence. It’s the cause. Think of it as a typo in the instruction manual. Example: A single base pair change from A to T in a specific gene. Genetic Disorder (The Inherited Disease): This is a disease condition that results directly from one or more specific mutations (germline or de novo) that are present in all cells of the affected individual (or at least in the germline if inherited). It’s the disease state stemming from a genetic blueprint flaw. Example: Sickle Cell Anemia is a genetic disorder caused by a single point mutation in the beta-globin gene, leading to abnormal hemoglobin. This mutation is present in almost all cells of affected individuals from conception. Malignancy (The Acquired Disease of Uncontrolled Growth): This is a complex disease driven by the accumulation of multiple somatic mutations (and sometimes initial germline mutations) in a subset of cells within a tissue, leading to

Nerve and Muscle Physiology
Anatomy

Nerve and Muscle Physiology

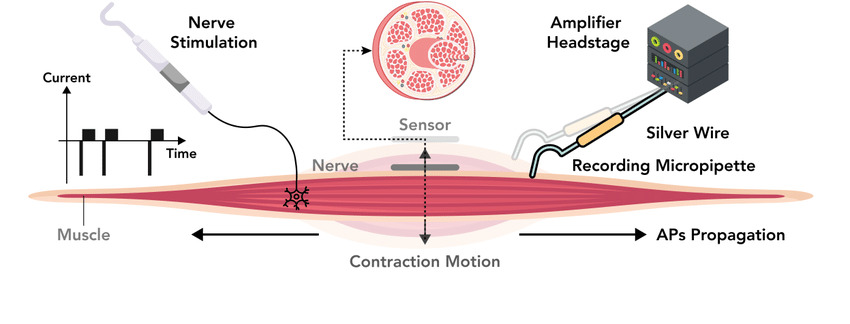
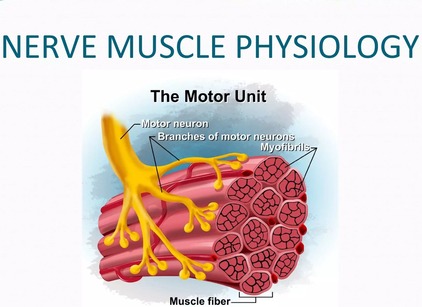
Nerve and Muscle Physiology:Basis and Application Nerve and Muscle Physiology Nerve and muscle physiology is a branch of physiology that specifically studies the function and mechanisms of nervous tissue (nerves) and muscle tissue (muscles). It explores how these “excitable tissues” generate and transmit electrical signals (like action potentials) and how these electrical signals are converted into specific cellular functions. For Nerves: It covers how neurons (nerve cells) generate electrical impulses, communicate with each other (synaptic transmission), process information, and transmit signals throughout the body to control various functions, from thought and sensation to movement and organ regulation. For Muscles: It focuses on how muscle cells (fibers) respond to electrical signals from nerves, leading to contraction (shortening) and the generation of force. This includes the molecular mechanisms of contraction, the regulation of muscle force, and the different types of muscle tissue and their distinct functional characteristics. Nervous System Excitability Nervous system excitability is the ability of nerve cells (neurons) to respond to a stimulus by generating and propagating an action potential, a self-propagating electrical impulse. This property is fundamental to the nervous system’s function and depends on the neuron’s membrane’s selective permeability, ion channels, and pumps. A change in membrane potential can lead to this event, which is essential for transmitting information throughout the body. The physiology of the nervous system involves its main divisions (the Central Nervous System (CNS) and Peripheral Nervous System (PNS)), which use neurons and electrochemical signals to sense stimuli, integrate information, and produce coordinated responses. Overall Structure & Function of a Motor Neuron (The Command Pathway) A motor neuron is a specialized nerve cell that transmits electrical signals from the central nervous system (brain and spinal cord) to muscles or glands, thereby initiating movement or secretion. It acts as the “final common pathway” by which the nervous system controls effector organs. 1. Motor Neuron Anatomy: Key Structural Components Cell Body (Soma/Perikaryon) The metabolic center of the neuron, containing the nucleus and other organelles. It synthesizes neurotransmitters and proteins and receives synaptic inputs from other neurons. Dendrites Branching, tree-like extensions that are the primary receptive (input) regions. They contain ligand-gated ion channels that receive chemical signals and generate graded potentials (EPSPs and IPSPs). Axon Hillock A cone-shaped region where the axon originates. This is the critical “trigger zone” with the highest density of voltage-gated Na⁺ channels. It integrates all incoming potentials, and if the sum reaches threshold, an action potential is generated. Axon A single, long projection that transmits the action potential (the output signal) away from the cell body. Its length can exceed a meter. Myelin Sheath A fatty, insulating layer that surrounds many axons, formed by Schwann cells in the PNS and oligodendrocytes in the CNS. It is crucial for increasing the speed of action potential conduction. Nodes of Ranvier Gaps in the myelin sheath that contain a high concentration of voltage-gated Na⁺ and K⁺ channels. The action potential is regenerated at these nodes, “jumping” from one to the next in a process called saltatory conduction. Axon Terminals (Synaptic Terminals) The branched ends of the axon that form synapses with other cells. They contain synaptic vesicles filled with neurotransmitters and are specialized for converting the electrical signal (action potential) into a chemical signal (neurotransmitter release). 2. Functional Zones: Relating Structure to Role We can map these anatomical components to four distinct functional zones, illustrating the flow of information: Input Zone (Dendrites & Cell Body): Receives and integrates incoming signals as graded potentials (EPSPs & IPSPs). Integration Zone (Axon Hillock): Sums all graded potentials. If the net depolarization reaches threshold, it triggers an action potential. Conduction Zone (Axon): Propagates the “all-or-nothing” action potential without loss of strength over long distances, facilitated by saltatory conduction. Output Zone (Axon Terminals): Converts the electrical action potential into a chemical signal by releasing neurotransmitters. 3. Role in Motor Control: The Final Common Pathway Motor neurons are often referred to as the “final common pathway” in motor control. This term emphasizes a fundamental principle: all the complex neural computations happening in higher brain centers (e.g., planning and coordination in the cerebral cortex, basal ganglia, and cerebellum) ultimately converge onto these lower motor neurons. It is only through the firing of a lower motor neuron that a skeletal muscle can be activated and a movement can occur. Regardless of whether a movement is voluntary or reflexive, the command signal ultimately travels down a lower motor neuron to its target muscle fibers. This makes the motor neuron a critical bottleneck and the ultimate determinant of muscle activity and all bodily movements. Synaptic Transmission (The Communication Bridge Between Neurons) Synaptic transmission is the fundamental process by which one neuron (the presynaptic neuron) communicates with another neuron (the postsynaptic neuron) or an effector cell. Most synapses in the nervous system are chemical synapses, meaning they utilize chemical messengers called neurotransmitters to bridge the microscopic gap between cells. Anatomy of a Chemical Synapse A chemical synapse consists of three main components: Presynaptic Terminal (Axon Terminal): The specialized end of the presynaptic axon. It contains synaptic vesicles filled with neurotransmitters, abundant mitochondria for energy, and crucial voltage-gated Ca²⁺ channels. Synaptic Cleft: The microscopic, fluid-filled space (typically 20-50 nm wide) that separates the presynaptic and postsynaptic membranes. Postsynaptic Membrane: The specialized region of the receiving cell’s membrane, containing a high density of specific neurotransmitter receptors. Neurotransmitter Synthesis & Storage Neurotransmitters are synthesized via distinct pathways and then packaged into synaptic vesicles. This packaging protects them from degradation, concentrates them for efficient release, and ensures their availability. Presynaptic Events: Neurotransmitter Release This phase converts the electrical signal into a chemical signal: Action Potential Arrives: An action potential propagates down the axon and depolarizes the presynaptic terminal. Depolarization Opens Voltage-Gated Ca²⁺ Channels: The change in membrane potential activates and opens these channels. Ca²⁺ Influx: Due to a steep electrochemical gradient, Ca²⁺ ions rapidly rush into the presynaptic terminal. This influx is the essential trigger for neurotransmitter release. Ca²⁺ Triggers Vesicle Fusion: The increase in intracellular Ca²⁺ causes synaptic vesicles

PHYSIOLOGY OF EXCITABLE TISSUES
Anatomy

PHYSIOLOGY OF EXCITABLE TISSUES

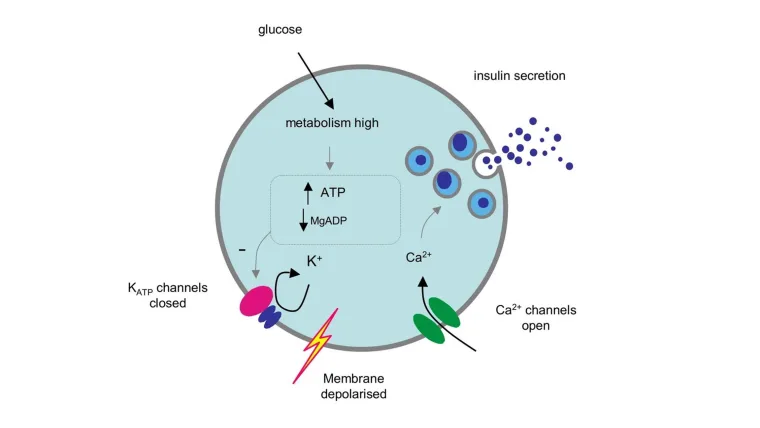
Excitability: PHYSIOLOGY OF EXCITABLE TISSUES Excitability Excitability: The Ability to Respond and Communicate Excitability refers to the ability of a cell to respond to a stimulus by generating an electrical signal called an action potential. It can be defined as a physical chemical change that occurs when a stimulus is applied on a tissue. A stimulus is an external agent that produces excitation in a tissue. This electrical signal is then propagated along the cell membrane or transmitted to other cells, leading to a specific physiological response. The action potential is a transient, rapid, and self-propagating reversal of the electrical potential across the cell membrane. This electrical signal is the medium through which cells rapidly transmit information, either along the length of an individual cell or to other cells via specialized junctions. This property is crucial for rapid communication and coordination within the body, underpinning virtually every complex physiological function, from perception and thought to movement and visceral regulation. Analogy for Understanding: The Tripwire Think of an excitable cell like a highly sensitive electrical tripwire or alarm system. The resting state is the armed system waiting for a trigger. The stimulus is the pressure that activates the tripwire. The action potential is the immediate, swift, and uniform “alarm bell” that rings loudly and clearly, sending its message through the system to orchestrate a coordinated response. 2. Excitable Cells While all living cells exhibit some degree of responsiveness, only a select group possess the highly specialized machinery to generate and propagate rapid electrical signals. These are the “excitable cells.” Neurons (Nerve Cells): The Master Communicators Expanded Role: Neurons are the fundamental units of the nervous system. Their primary function is the transmission of electrical and chemical signals for sensory input, integration, motor output, cognition, and emotion. Unique Features: They possess specialized structures like dendrites (to receive signals), a cell body (soma), and a long axon (to transmit signals), often insulated by a myelin sheath to speed conduction. Muscle Cells: The Effectors of Movement Muscle cells are specialized for contraction, which generates force and movement. Their excitability is the prerequisite for this mechanical action. Skeletal Muscle Cells: Responsible for all voluntary movements (walking, speaking, breathing). When a motor neuron sends an action potential, it triggers a muscle action potential, leading to contraction. Cardiac Muscle Cells: Found only in the heart, responsible for the rhythmic and involuntary pumping of blood. They possess autorhythmicity and have distinctively long action potentials for coordinated contractions. Smooth Muscle Cells: Mediate involuntary movements in the walls of internal organs like the digestive tract, blood vessels, and urinary bladder. Their excitability is influenced by stretch, local chemicals, and the autonomic nervous system. Glandular Cells: The Secretory Responders Role Expansion: Many glandular cells (e.g., in the adrenal medulla, pancreas) exhibit excitability. They can respond to an electrical stimulus from a neuron by generating their own electrical event (depolarization or action potential). Excitability Link: This electrical event is typically coupled to the release of their secretions (e.g., hormones, digestive enzymes). For example, adrenal medullary cells depolarize in response to a neuronal signal, triggering Ca²⁺ influx and the exocytosis of epinephrine. This ensures precise and rapid control over hormone release. Membrane Potential The capacity of these cells to generate electrical signals rests entirely on the idea of membrane potential. This is the voltage difference across the cell’s outer boundary, a stored electrical energy created by an uneven distribution of ions (electrically charged particles) inside the cell (ICF) and outside the cell (ECF). Resting Membrane Potential (RMP) When an excitable cell is quiet, it maintains a stable, baseline electrical charge called the Resting Membrane Potential (RMP). In this state, the inside of the cell consistently holds a negative charge relative to the outside (e.g., -70 mV in neurons, -90 mV in skeletal muscle). Creating and Maintaining the RMP The RMP is a dynamic state, constantly maintained by an interplay of three factors: Ion Gradients: The Concentration DivideThe foundation is the different concentrations of key ions: a high concentration of Na⁺ outside the cell and a high concentration of K⁺ inside the cell. Selective Permeability: The Leaky GatesAt rest, the membrane is significantly more permeable to K⁺ than to Na⁺ because there are many more open K⁺ “leak” channels than Na⁺ leak channels. Sodium-Potassium ATPase (Na⁺/K⁺-ATPase) Pump: The Gradient UpholderThis active transporter continually pumps 3 Na⁺ ions out for every 2 K⁺ ions it pumps in, directly maintaining the concentration gradients and contributing a small amount to the RMP’s negativity (making it an electrogenic pump). Equilibrium Potential (Nernst Potential) The equilibrium potential for a specific ion is the membrane voltage at which there is no net movement of that ion across the membrane. At this voltage, the electrical force is perfectly balanced by the chemical (concentration) force. The Nernst Equation calculates this value: E_ion = (RT / zF) * ln([ion]out / [ion]in) Ion Channels These are specialized proteins that form pores for specific ions to cross the membrane. Types Relevant to Excitability: Leak Channels: These channels are always open and are instrumental in establishing the RMP, particularly the K⁺ leak channels. Gated Channels: The Responsive Switches These channels open or close only in response to a particular trigger and are essential for generating action potentials. Voltage-Gated Channels Open or close in direct response to changes in membrane voltage. They are the key drivers of the action potential. Ligand-Gated Channels (Chemically Gated) Open or close when a specific chemical messenger (a ligand), such as a neurotransmitter, binds to them. Mechanically Gated Channels Open or close when they are physically deformed or stretched, critical for sensory perception like touch and pressure. Initiating the Response: Stimulus and Threshold The Stimulus: A Call to Action A stimulus is any detectable change (electrical, chemical, or mechanical) in the cell’s environment that has the potential to alter its RMP. Depolarization: A shift in membrane voltage where the inside of the cell becomes less negative (e.g., from -70 mV to -50 mV). Hyperpolarization: A shift where the inside of the

body water compartments 1620
Anatomy

Body Fluids and Compartments

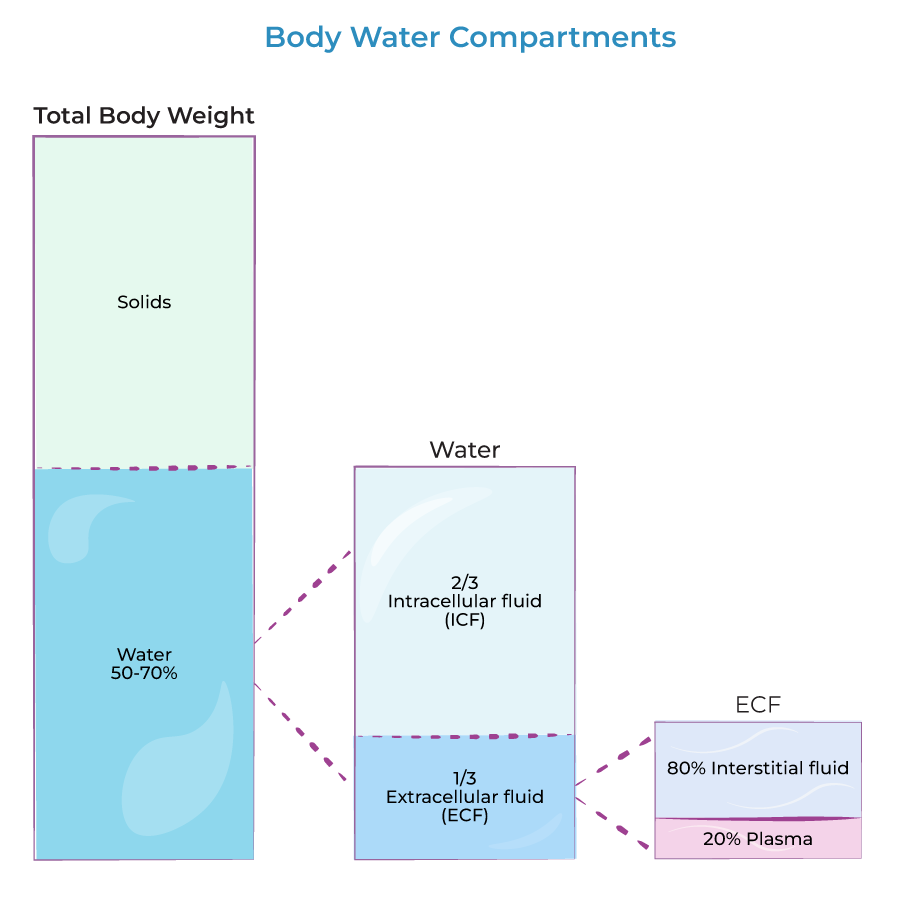
Body Fluids: And Compartments Body Fluids To truly appreciate the dynamics of body fluids, we first need to understand where all this fluid is located within the body. Imagine your body as a system of interconnected containers, each holding a specific type of fluid. These “containers” are what we call body fluid compartments. The human body is largely composed of water, and this water isn’t just free-flowing; it’s meticulously organized into various functional compartments. This compartmentalization is key to maintaining cellular and systemic homeostasis. 1. Total Body Water (TBW) TBW refers to all the water contained within the body. It represents a significant proportion of body mass. Proportion: Approximately 60% of an adult’s body weight is water. This percentage can vary significantly based on several factors: Age: Infants (up to 75-80%), Adults (~60%), and the Elderly (can drop to 45-50%). Sex: Females generally have a slightly lower TBW percentage than males because they typically have a higher percentage of adipose tissue (fat), which contains very little water. Body Fat Content: Individuals with higher body fat percentages will have lower TBW percentages, and vice-versa. Composition of Water: TBW is not pure water; it contains numerous dissolved solutes, including electrolytes, proteins, nutrients, gases, and waste products. The total amount of water in an adult human body constitutes about 50-70% of the total body weight. This water is not uniformly distributed but is divided into two primary compartments, which are further subdivided: A. Intracellular Fluid (ICF) Location: The ICF is the fluid found within the cells of the body. It is the immediate environment where the vast majority of cellular metabolic activities take place. Proportion and Significance: The ICF constitutes the largest single fluid compartment, accounting for approximately two-thirds (2/3) of the Total Body Water (TBW). In an adult male weighing 70 kg, this would be roughly 28 liters (40% of body weight). This large volume underscores its critical role: it directly bathes the cellular machinery, providing the aqueous medium for all intracellular biochemical reactions. Composition – The Cell’s Internal Environment: Major Cations: Potassium (K⁺): The predominant cation in the ICF. Its high concentration is crucial for nerve impulse transmission, muscle contraction, and maintaining cell volume. Magnesium (Mg²⁺): Vital as a cofactor for numerous enzymatic reactions, particularly those involving ATP. Major Anions: Phosphate (PO₄³⁻): A critical component of energy currency (ATP), nucleic acids, and intracellular buffering systems. Proteins: The ICF is rich in large, negatively charged protein molecules that contribute to osmolarity and act as important buffers. Low Concentrations: In stark contrast to the ECF, Sodium (Na⁺) and Chloride (Cl⁻) concentrations are very low within the ICF. Key Characteristics – Functional Blueprint: Selective Permeability of the Cell Membrane: The plasma membrane is the critical barrier separating the ICF from the ECF, maintaining the distinct chemical composition of the ICF. Metabolic Engine: The ICF houses the cell’s entire metabolic machinery – organelles like mitochondria, ribosomes, and the nucleus. Osmotic Equilibrium: Despite vastly different chemical compositions, the total osmotic concentration (osmolarity) of the ICF is normally in dynamic equilibrium with the ECF. B. Extracellular Fluid (ECF) Location: The ECF is all the fluid found outside the cells. It acts as the body’s internal environment that bathes all cells. Proportion: The ECF constitutes approximately one-third (1/3) of the TBW, which is roughly 14 liters (20% of body weight) in a 70 kg adult. Composition – The Body’s Transport Medium: Major Cations: Predominantly Sodium (Na⁺), which is the primary determinant of ECF osmolarity and volume. Major Anions: Predominantly Chloride (Cl⁻) and Bicarbonate (HCO₃⁻), a crucial component of the body’s buffering system. Other Components: A rich soup of nutrients, gases, hormones, and waste products. Sub-compartments of ECF: The ECF is not a monolithic entity; it is further subdivided into several distinct yet interconnected compartments: i. Interstitial Fluid (ISF) This is the “tissue fluid,” filling the microscopic spaces between the cells. It is the largest component of the ECF, comprising about 80% of ECF volume. Its ionic composition is similar to plasma, but it has a significantly lower protein concentration. The ISF is the critical medium for the exchange of nutrients, gases, and waste between the blood and the cells. ii. Plasma This is the fluid component of blood, circulating within the cardiovascular system. It accounts for about 20% of ECF volume. Its defining characteristic is its high concentration of plasma proteins (e.g., albumin). Plasma is the primary transport medium for blood cells, nutrients, hormones, and waste products. iii. Transcellular Fluid A small, specialized component of the ECF, representing only 1-2% of body weight. It consists of fluids secreted by specific cells into distinct, epithelial-lined spaces. The composition of these fluids is often unique and tailored to their specific function. Examples: Cerebrospinal Fluid (CSF), Intraocular Fluid, Synovial Fluid, Serous Fluids (pleural, pericardial), and Gastrointestinal Secretions. Fluid Movement Between Compartments and Regulatory Mechanisms The precise movement of water and solutes between the body’s fluid compartments is a cornerstone of physiological homeostasis. This dynamic equilibrium is meticulously regulated by physical forces, membrane properties, and complex neurohormonal systems. A. Fluid Movement Between Plasma and Interstitial Fluid (Across Capillary Walls) The exchange of fluid, nutrients, gases, and waste products between the blood (plasma) and the cells (via the ISF) occurs primarily across the thin walls of the capillaries. This movement is governed by Starling Forces, which represent the interplay of hydrostatic and oncotic pressures. Starling Forces – The Drivers of Capillary Exchange: Capillary Hydrostatic Pressure (Pc): Definition: This is the pressure exerted by the blood within the capillaries, effectively the “pushing” force of the blood against the capillary wall. Effect: It tends to force fluid out of the capillary and into the interstitial space (filtration). Dynamics: Pc is highest at the arterial end of the capillary (typically around 30-35 mmHg) and progressively drops to a lower value at the venous end (typically around 10-15 mmHg). Interstitial Fluid Hydrostatic Pressure (Pif): Definition: This is the pressure exerted by the fluid in the interstitial space surrounding the capillary. Effect: It tends to push fluid

homeostasis physiology
Anatomy

Homeostasis Physiology

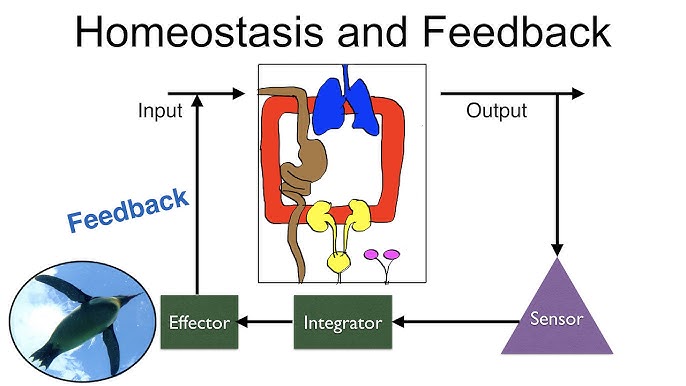
Homeostasis: Maintaining the Internal Balance Homeostasis Imagine you’re driving a car, aiming to maintain a constant speed of 60 mph. You press the gas going uphill and ease off going downhill. Your goal is to keep that speed constant despite external changes. That’s essentially what your body does, constantly, for hundreds of variables. Homeostasis (from Greek “homoios” meaning “similar” and “stasis” meaning “standing still”) is the ability of an organism to maintain a relatively stable internal environment despite continuous changes in the external environment. It’s not a static state, but a dynamic equilibrium where conditions fluctuate within narrow, acceptable limits around a set point. Many physiologists translate this into the saying, “constantly changing to stay the same.” The ability of the human body to quickly adapt to any changes and to re-establish stability is the essence of homeostasis. The Importance of Homeostasis Survival itself depends on the body’s ability to maintain this internal balance. Deviations outside the normal range can impair cell function, leading to disease or death. Enzyme and Protein Function Almost all biochemical reactions are catalyzed by enzymes (proteins), which are highly sensitive to their environment. Impact of Imbalance: Deviations in temperature or pH can denature enzymes, altering their 3D shape and halting vital metabolic pathways. Cellular Integrity and Volume The cell membrane’s selective permeability and active transport mechanisms are critical for maintaining appropriate solute concentrations. Impact of Imbalance: Changes in extracellular fluid osmolarity can cause cells to swell and burst (lysis) or shrink and die (crenation). Disrupted ion gradients incapacitate nerve and muscle function. Efficient Communication Systems The nervous and endocrine systems require specific conditions to transmit signals effectively. Impact of Imbalance: Improper electrolyte balance (Na⁺, K⁺, Ca²⁺) can lead to severe nerve and muscle dysfunction, including seizures, paralysis, and cardiac arrhythmias. Energy Production (ATP) Cells require a continuous supply of oxygen and nutrients, and efficient removal of waste, to produce ATP. Impact of Imbalance: Oxygen deprivation (hypoxia) leads to a cellular energy crisis and buildup of lactic acid. Accumulation of wastes like CO₂ can become toxic and alter pH, leading to organ failure. Immune System Function Immune cells and proteins need stable conditions to effectively fight off pathogens without harming healthy tissues. Impact of Imbalance: Uncontrolled fever can become detrimental to immune cells themselves. Chronic stress and elevated cortisol can suppress the immune system. Examples of Homeostatically Regulated Variables The body tightly regulates hundreds of variables to maintain this dynamic equilibrium. Key examples include: Body temperature Blood pressure Blood glucose levels Blood pH Oxygen and carbon dioxide levels Water balance Ion concentrations (Na⁺, K⁺, Ca²⁺) Homeostasis is Maintained by Feedback Loops The primary way the human body maintains homeostasis is with the use of feedback loops. A feedback loop is a mechanism that allows for continual assessment of the body’s physiology and a way to correct various elements if they should go out of balance. There are two types of feedback loops: negative and positive. Negative Feedback Loop The response opposes (or negates) the original stimulus. This is by far the most common type in the human body. Positive Feedback Loop The response augments (or intensifies) the original stimulus. The cycle repeats until it is broken. This type is very rare but critically important. Parameters and Set Points For any feedback loop, there is a parameter that is being monitored, and it has a set point, or a ‘normal range’ in which it exists when the body is in balance. The stimulus that starts the feedback loop is a change in that parameter that pushes it above or below its normal set point range. Table 1.1: Examples of Blood Parameters and Their Set Points Osmolarity of Blood 295-310 mOsM pH of Blood 7.35-7.45 Arterial PCO₂ 35-46 mmHg Arterial PO₂ 80-100 mmHg Glucose (fasting) 70-100 mg/dL Sodium (Na⁺) 135-145 mM Potassium (K⁺) 3-5 mM Example: Blood Glucose Regulation (Between Meals) A person’s blood glucose (parameter) has a normal range (set point) of 70 to 100 mg/dL. If a person has not eaten in a while, their blood glucose decreases. If it goes below 70 mg/dL, the person will have hypoglycemia (low blood sugar). This decrease is the stimulus. This decrease is detected by receptors in the pancreas, which responds by releasing the hormone glucagon into the bloodstream. Glucagon travels to the liver and stimulates hepatocytes (liver cells) to break down their glycogen stores and release glucose molecules into the blood. This increases blood glucose levels, opposing the original stimulus. Once glucose is restored to its normal range, the signal for glucagon release dissipates. This “off switch” is a key element of negative feedback. The Nitty Gritty of the Feedback Loop To describe feedback loops with consistent terms, we can identify seven general components that create the loop. 1. Stimulus: The change (above or below the set point) that starts the loop. 2. Receptor: The element or structure that detects this change. 3. Afferent Pathway: The incoming pathway used to convey information about this change. 4. Integration Center: The site where an evaluation is made about what to do. 5. Efferent Pathway: The outgoing pathway used to signal a tissue how to respond. 6. Effector Tissue: The structures acted upon to respond to the stimulus. 7. Response: The change created by the effector tissue in response to the original stimulus. Homeostatic Control Mechanisms (The “Feedback Loops”) To maintain homeostasis, the body uses control systems, most of which involve feedback loops. These loops constantly monitor conditions, detect changes, and initiate responses to bring variables back to their set point. Every feedback loop has three basic components: 1. Receptor (Sensor) Function: Monitors the environment and responds to changes (stimuli). It detects the deviation from the set point. Action: Sends information (input) along an afferent pathway (e.g., nerve impulses) to the control center. Example: Thermoreceptors in the skin and hypothalamus detect changes in body temperature. 2. Control Center (Integrator) Function: Receives and analyzes the input from the receptor. It compares the input to the set point (the ideal value) and

Physiology and Cell Physiology
Anatomy

Physiology and Cell Physiology

Physiology Intro: Cell Physio and Transport Introduction to Basic Physiology & The Cell Physiology is the science of studying the functional activities and its mechanisms in the biological body. For example: why can the heart automatically beat? Physiology derived from two Greek words – physis = nature; logos = study. Physiology Involves Process and Function Words, names and terms are very important in any discipline because most often they carry precise meaning in them. Knowing and understanding the relationships of the meanings of these words will help tremendously in remembering and comprehending the information in a much deeper way. This information will also stay with you long after the course is over, and you will recognize important elements in other disciplines when you connect to the deeper meanings. Physiology The etymology (word origin) of the term Physiology comes from the 1560’s French which comes directly from Latin physiologia, meaning “The study and description of natural objects, natural philosophy”. This is derived from ‘physios’ meaning “nature, natural, physical”; and ‘logia’ meaning “study”. This gives us the fuller meaning of Physiology as the “Science of the normal function of living things”. When studying physiology, it is imperative that we also understand the basic anatomy involved, as anatomy (structure) and physiology (function) go hand in hand. Anatomy The etymology (word origin) of the term Anatomy comes from the Late 1300’s terms in both Latin, anatomia and Greek, anatome. These words are derived from ana which means “up”; and tomos (or temnein) which means “to cut”. Together this gives “a cutting up”, which is clearly involved in dissection! In general, anatomy is considered the “Study or knowledge of the structure (form) and function of the human body“. Courses and textbooks for anatomy and physiology are different, but are inextricably connected to each other. Etymology for the Language of Physiology Another useful concept related to the importance of words in physiology (and anatomy) is knowing the etymology (origin of the word) of the vast array of scientific terms used in the health care field. Since many of these words are derived from Latin and Greek, it is incredibly helpful to know the origins and ‘translations’ of these terms. Becoming aware of the origins of words will greatly help students to: 1) understand what the term means; and 2) assist you in predicting what a brand new term means when you first encounter it. Here are two examples: The solution is hypertonic. Hyper means above normal and tonic means strength. The solution is strong or concentrated. The person has hypoglycemia. Hypo is the opposite of hyper and means below normal. The glyc portion means glucose (a type of sugar), and emia means blood. Therefore, this statement means the person has low blood sugar. One more example: A runner has hyponatremia. Hypo still means below normal. The natr portion means natrium which is the Latin word for sodium (hence why the chemical symbol for sodium is Na), and emia still means blood. Therefore, this statement means the person has low sodium levels in their blood. Along the way in this physiology course we will encounter many of these terms that, once we know the origin and meaning of, will help us figure out newer terms with ease and familiarity. Anyone who has taken a medical terminology course will know the value of understanding the meaning of roots, prefixes, and suffixes. Now you do this one: There is a diagnosis of pancytopenia. (Hint: there are 3 terms here: pan, cyto and penia). Please feel free to use any reference resource available to you, and remember there is a Glossary of Anatomy and Physiology Etymology terms provided in this text (page 649) to help find out what this diagnosis literally means. Compare Function and Process in Human Physiology As we look to understand the central themes of physiology, an important concept is how to ask questions about what’s occurring in the human body. In general, there are two basic approaches to physiology: 1) We can ask Functional Questions; and 2) We can ask Process Questions. 1. Functional Questions (Why) These are related to Why something occurs. For example, what is the purpose of the heart beating? These can often be answered without much detail. Q: Why does blood flow? A: To transport nutrients, wastes and gases around the body. Q: Why do RBCs transport O₂? A: To deliver O₂ to the body tissue that need it. Q: Why do we breathe? A: To extract the oxygen (O₂) from inhaling atmosphere air and also to release carbon dioxide (CO₂) when exhaling air back out of the body. 2. Process Questions (How) These are related to How something occurs. For example, how does the heart actually beat? Often these issues are answered in a detailed step-by-step manner. Q: How does blood flow? A: The tissue fluid pressures and the ventricles of the heart act in coordination to generate a pressure gradient down which blood flows throughout the body. Q: How do RBCs transport O₂? A: Inside the red blood cells (RBCs) the heme portion of the molecule hemoglobin has a high affinity for O₂ when the partial pressure of the surroundings for O₂ is high, and a low affinity for O₂ when the surrounding partial pressure for O₂ is low. Q: How do we breathe? A: Changes can be made in the volume of the thoracic cavity by the contraction and relaxation of the skeletal muscles of respiration. This causes inverse changes in the pressure of the thoracic cavity, causing air to move down its pressure gradient. Things to notice about Function and Process Notice the How part (process) requires more details and also involves a sort of ‘pathway’ approach. It is more like story telling compared to the less detailed functional aspects. The more arduous component of physiology is the detailed processes. This is the reason we need to take our time and fully understand the fundamentals before we delve into intricate details. What most students recognize about physiology

anatomy lecture doctors revision
Anatomy

Anatomy & Physiology 2023 Paper

Anatomy & Physiology — Final Examination Paper Final Examination Paper Anatomy & Physiology Bachelors in Nursing  •  Semester 2, 2023 3 Hrs Duration 100 Total Marks A · B · C Sections Instructions to Candidates Answer ALL questions in Section A (Objectives & Fill-ins). Answer any THREE questions from Section B. Answer any TWO questions from Section C. Write clearly and legibly. Do not write anything in the margins. Section A 40 MARKS Part I — Objectives (20 Marks). Answer ALL questions. Choose the most appropriate answer. 1. Which bone cell is responsible for resorbing (breaking down) bone matrix? A. OsteocyteB. Osteoblast C. OsteoclastD. Osteogenic cell Show Answer Answer: C. Osteoclast — Osteoclasts are large, multinucleated cells that break down bone tissue for remodeling. 2. The “Waiter’s Tip” position is a classic sign of injury to which part of the brachial plexus? A. Lower Trunk (C8, T1)B. Upper Trunk (C5, C6) C. Medial CordD. Posterior Cord Show Answer Answer: B. Upper Trunk (C5, C6) — This is known as Erb-Duchenne Palsy, affecting muscles like the deltoid and biceps. 3. All muscles of facial expression are innervated by which cranial nerve? A. Trigeminal Nerve (CN V)B. Facial Nerve (CN VII) C. Accessory Nerve (CN XI)D. Hypoglossal Nerve (CN XII) Show Answer Answer: B. Facial Nerve (CN VII) 4. During which stage of lung maturation does surfactant production begin? A. Pseudoglandular StageB. Canalicular Stage C. Saccular StageD. Alveolar Stage Show Answer Answer: C. Saccular Stage — Type II pneumocytes differentiate and begin surfactant production. 5. Which muscle is the primary flexor of the forearm at the elbow? A. Biceps BrachiiB. Brachialis C. Triceps BrachiiD. Brachioradialis Show Answer Answer: B. Brachialis — It is the “workhorse” of elbow flexion, regardless of forearm position. 6. The sella turcica, which houses the pituitary gland, is a feature of which cranial bone? A. Frontal BoneB. Ethmoid Bone C. Occipital BoneD. Sphenoid Bone Show Answer Answer: D. Sphenoid Bone — The sphenoid is the central “keystone” bone of the cranium. 7. In oogenesis, meiosis I is completed just before ovulation, resulting in: A. One ovum and three polar bodiesB. Four functional ova C. Two secondary oocytesD. One secondary oocyte and one polar body Show Answer Answer: D. One secondary oocyte and one polar body — The division is unequal to preserve cytoplasm. 8. Which muscle is NOT part of the rotator cuff (SITS) group? A. SupraspinatusB. Teres Major C. InfraspinatusD. Subscapularis Show Answer Answer: B. Teres Major — Teres Major is an adductor and medial rotator, but not a rotator cuff muscle. 9. The primary action of the muscles in the lateral compartment of the leg (Fibularis Longus and Brevis) is: A. DorsiflexionB. Inversion C. EversionD. Plantarflexion Show Answer Answer: C. Eversion — They are the primary everters of the foot. 10. An inability to abduct the thigh and a pelvic drop on the unsupported side (Trendelenburg sign) indicates damage to which nerve? A. Femoral NerveB. Obturator Nerve C. Inferior Gluteal NerveD. Superior Gluteal Nerve Show Answer Answer: D. Superior Gluteal Nerve — This nerve innervates the Gluteus Medius and Minimus, the main hip abductors. 11. The olecranon process is a prominent feature of which bone? A. RadiusB. Humerus C. UlnaD. Scapula Show Answer Answer: C. Ulna — It forms the point of the elbow. 12. All hamstring muscles are innervated by the tibial portion of the sciatic nerve EXCEPT: A. Long head of Biceps FemorisB. Short head of Biceps Femoris C. SemitendinosusD. Semimembranosus Show Answer Answer: B. Short head of Biceps Femoris — It is innervated by the common fibular portion of the sciatic nerve. 13. Which of the following is NOT part of the axial skeleton? A. SternumB. Ribs C. ClavicleD. Vertebrae Show Answer Answer: C. Clavicle — The clavicle is part of the pectoral girdle, which belongs to the appendicular skeleton. 14. The “anatomical snuffbox” is formed by the tendons of all the following muscles EXCEPT: A. Abductor Pollicis LongusB. Extensor Pollicis Brevis C. Abductor Pollicis BrevisD. Extensor Pollicis Longus Show Answer Answer: C. Abductor Pollicis Brevis — This is a thenar muscle in the hand, not a posterior forearm muscle. 15. Referred pain to the shoulder tip is often a sign of irritation to the diaphragmatic pleura, carried by which nerve? A. Vagus NerveB. Phrenic Nerve C. Intercostal NerveD. Long Thoracic Nerve Show Answer Answer: B. Phrenic Nerve — Its root values C3-C5 correspond to the shoulder dermatome. 16. The patella is classified as which type of bone? A. Long BoneB. Irregular Bone C. Flat BoneD. Sesamoid Bone Show Answer Answer: D. Sesamoid Bone — It is a bone embedded within a tendon. 17. Which muscle is responsible for the first 15 degrees of arm abduction? A. DeltoidB. Pectoralis Major C. SupraspinatusD. Latissimus Dorsi Show Answer Answer: C. Supraspinatus — The deltoid takes over as the primary abductor after the initial 15 degrees. 18. The Adductor Pollicis muscle in the hand is innervated by the: A. Median NerveB. Radial Nerve C. Musculocutaneous NerveD. Ulnar Nerve Show Answer Answer: D. Ulnar Nerve — It is the “odd one out” of the thenar group muscles. 19. The microscopic, cylindrical unit of compact bone is called a(n): A. TrabeculaB. Lamella C. OsteonD. Canaliculus Show Answer Answer: C. Osteon — Also known as a Haversian system. 20. The “sit bones” are technically known as the: A. Iliac CrestsB. Pubic Tubercles C. Ischial TuberositiesD. Sacral Promontory Show Answer Answer: C. Ischial Tuberosities — They bear the body’s weight when sitting. Part II — Fill in the Blanks (20 Marks). Answer ALL questions in this part. 21.The primary muscle of respiration that separates the thoracic and abdominal cavities is the click to reveal. 22.The nerve that innervates the muscles of facial expression is the click to reveal. 23.The final maturation stage where a round spermatid is remodeled into a spermatozoon is called click to reveal. 24.The mnemonic “PAD” helps to remember that the Palmar Interossei muscles click to reveal the fingers. 25.The C1 vertebra is known as the

Leg Muscles e1759753201440
Anatomy

Muscles of the Lower Limb

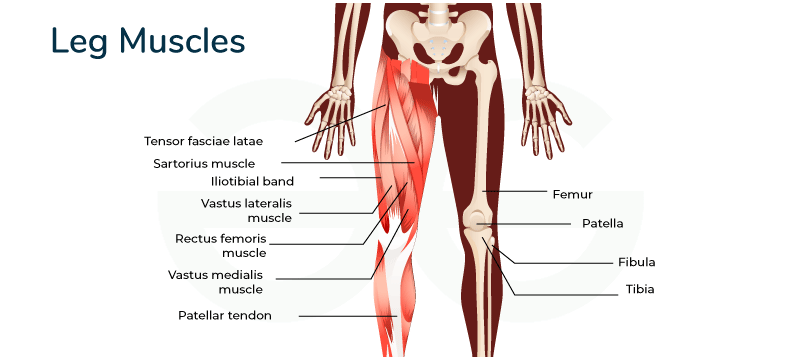
Muscles of the Lower Limb: From Pelvis to Toe. Anatomy of the Lower Extremities The Hip Joint The hip joint is one of the most important joints in the body for movement, like walking or dancing. Part 1: The Bony Pelvis & The Hip Bone The bony pelvis is a basin-shaped ring of bones connecting the vertebral column to the femurs, formed by the sacrum, coccyx, and the two hip bones (Os coxae). The Hip Bone (Os Coxa) Each large, irregularly shaped hip bone is a fusion of three primary bones that completes by the end of puberty: Ilium: The largest, most superior part, forming the prominent “wings” of the pelvis. Ischium: Forms the posteroinferior (lower-back) part of the hip bone. Pubic Bone (Pubis): Forms the anterior part of the hip bone. The Acetabulum The deep, cup-shaped socket on the lateral surface of the hip bone, formed by the union of all three bones. It articulates with the head of the femur. Key features include the crescent-shaped Lunate Surface (articular), the central Acetabular Fossa, and the fibrocartilaginous Acetabular Labrum that deepens the socket for increased stability. Detailed Anatomy of the Hip Bone Ilium: Iliac Crest: The palpable superior border, terminating anteriorly as the Anterior Superior Iliac Spine (ASIS) and posteriorly as the Posterior Superior Iliac Spine (PSIS). Other Spines: Anterior Inferior Iliac Spine (AIIS) and Posterior Inferior Iliac Spine (PIIS). Surfaces: The large, concave internal Iliac Fossa; the rough outer Gluteal Surface for gluteal muscle attachment; and the medial Auricular Surface for articulation with the sacrum. Notches: The Greater Sciatic Notch, a large indentation for passage of the sciatic nerve. Ischium: Ischial Tuberosity: The large, roughened “sitting bone” that supports body weight when seated. Ischial Spine: A pointed projection posterior to the acetabulum, separating the Greater and Lesser Sciatic Notches. Ramus of the Ischium: Projects forward to join with the pubis. Pubis: Body of Pubis: The central part that meets the other pubic bone at the Pubic Symphysis. Superior & Inferior Rami: Bars of bone that help form the acetabulum and obturator foramen. Key Markings: Includes the Pubic Tubercle and Obturator Crest for ligament and muscle attachments. Obturator Foramen The large opening created by the ischium and pubis. It is mostly closed by the obturator membrane but allows the obturator nerve and vessels to pass through the obturator canal into the thigh. The Femur (Thigh Bone) The femur is the longest, strongest, and heaviest bone in the body, transmitting weight from the hip to the tibia. Key Features of the Femur: Proximal End: Features the spherical Head (with its Fovea Capitis for the ligament of the head of the femur), the constricted Neck (a common fracture site), and the large Greater and Lesser Trochanters for muscle attachment. The Intertrochanteric Line (anterior) and Crest (posterior) connect the trochanters. Shaft: Includes the prominent posterior ridge, the Linea Aspera, for attachment of many thigh muscles. Proximally, it gives rise to the Pectineal Line and Gluteal Tuberosity. Distal End: Forms the knee joint with the large Medial and Lateral Condyles. The deep posterior notch between them is the Intercondylar Fossa. It also features the Medial and Lateral Epicondyles for ligament attachment and the anterior Patellar Surface. Key Ligaments of the Hip Joint Iliofemoral Ligament (Y-ligament of Bigelow): The strongest ligament in the body, located anteriorly. It prevents hyperextension of the hip. Pubofemoral Ligament: Located anteroinferiorly, it limits excessive abduction and extension. Ischiofemoral Ligament: Located posteriorly, it limits internal rotation and adduction. Ligament of the Head of the Femur (Ligamentum Teres): Located inside the joint, connecting the fovea capitis to the acetabulum. Transverse Acetabular Ligament: Bridges the acetabular notch, completing the socket. Muscles of the Lower Limb The powerful muscles of the lower limb are designed for stability, locomotion, and maintaining an upright posture. We will cover them regionally, starting with the hip and gluteal region. Hip Muscles: The Iliopsoas Group The Iliopsoas is the strongest hip flexor in the body. It’s a composite muscle formed by the Psoas Major and Iliacus, which merge to insert on the lesser trochanter of the femur. Psoas Major: Originates from the lumbar vertebrae. Iliacus: Originates from the iliac fossa. Main Actions: As the main flexor of the hip, it is essential for walking, running, and lifting the leg. 1. Muscles of the Gluteal Region (Buttocks) These muscles are essential for hip movement, stability, and posture, divided into superficial and deep layers. Superficial Gluteal Muscles Gluteus Maximus The largest and most superficial gluteal muscle. It is the main extensor of the thigh (crucial for climbing stairs or standing up) and a lateral rotator. Gluteus Medius Lies deep to Gluteus Maximus. It is the main abductor and a medial rotator of the thigh. It is crucial for stabilizing the pelvis during walking to prevent the hip from dropping on the unsupported side (Trendelenburg sign). Gluteus Minimus The smallest and deepest gluteal muscle. It works with the Gluteus Medius to abduct and medially rotate the thigh and stabilize the pelvis. Tensor Fasciae Latae (TFL) A small anterolateral muscle that flexes, abducts, and medially rotates the thigh. It tenses the iliotibial (IT) tract, which helps to stabilize the knee in extension. Deep Gluteal Muscles (Short External Rotators) This group of six smaller muscles lies deep to the gluteus maximus. They collectively function as powerful lateral rotators of the thigh and help stabilize the head of the femur in the acetabulum. Piriformis Origin: Anterior surface of sacrum. Insertion: Superior border of greater trochanter. Innervation: Nerve to Piriformis (S1, S2). Actions: Laterally rotates, abducts (when hip is flexed), and extends the thigh. Superior Gemellus Origin: Ischial spine. Insertion: Medial surface of greater trochanter (with Obturator Internus tendon). Innervation: Nerve to Obturator Internus (L5, S1). Actions: Laterally rotates and abducts the thigh. Obturator Internus Origin: Pelvic surface of obturator membrane. Insertion: Medial surface of greater trochanter. Innervation: Nerve to Obturator Internus (L5, S1). Actions: Laterally rotates and abducts the thigh. Inferior Gemellus Origin: Ischial tuberosity. Insertion: Medial surface of greater trochanter (with Obturator Internus

The Muscles of the Upper Extremity
Anatomy

Muscles of the Upper Limb

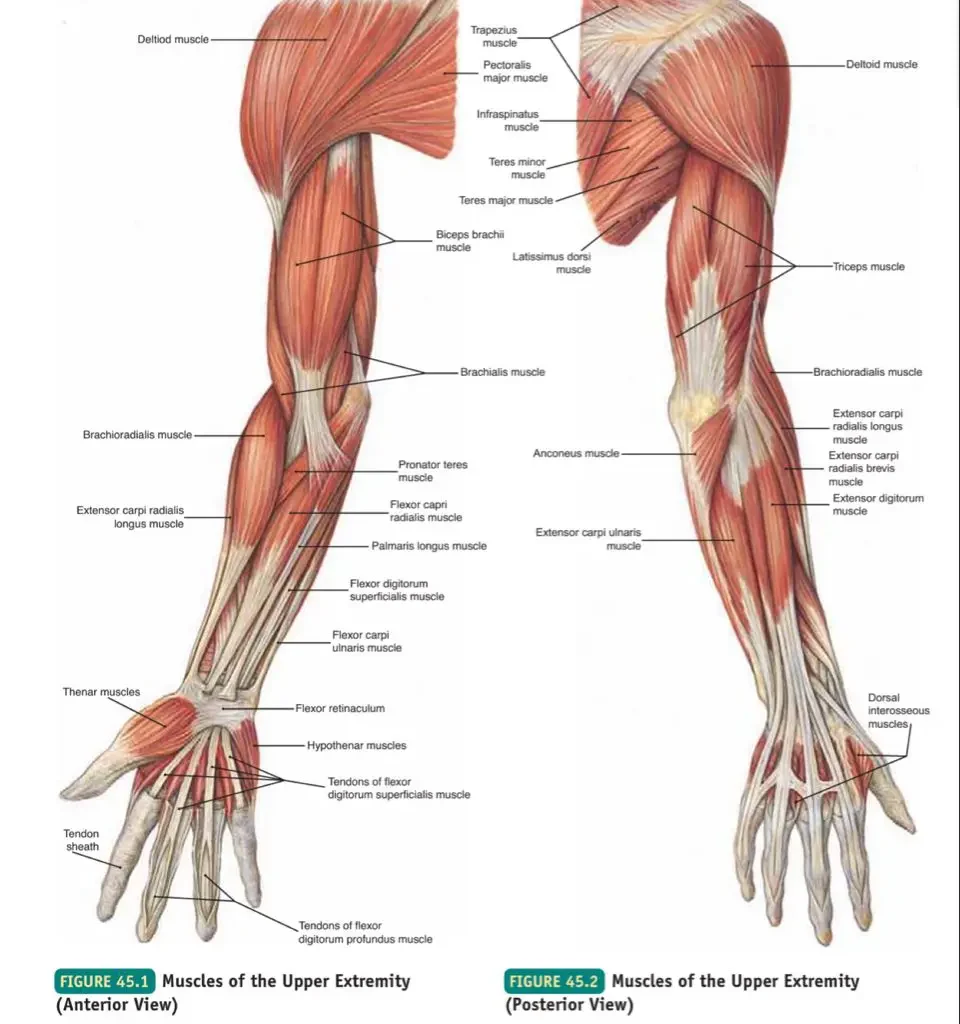
Musclesof the Upper Limbs: From Shoulder. The Brachial Plexus The brachial plexus is a complex network of nerves formed by the anterior rami of the lower four cervical nerves (C5, C6, C7, C8) and the first thoracic nerve (T1). It is responsible for the motor and sensory innervation of the entire upper limb. Understanding the plexus is best done by following its five main divisions, remembered by the mnemonic: “Real Texans Drink Cold Beer” (Roots, Trunks, Divisions, Cords, Branches). 1. Roots (C5, C6, C7, C8, T1) The five roots are the anterior primary rami of the spinal nerves, emerging between the anterior and middle scalene muscles in the neck. Key Branches from Roots: Dorsal Scapular Nerve (C5): Innervates Rhomboids and Levator Scapulae. Long Thoracic Nerve (C5, C6, C7): Innervates Serratus Anterior. 2. Trunks (Superior, Middle, Inferior) The five roots unite to form three trunks, which pass over the first rib. Upper Trunk: Formed by the union of C5 and C6 roots. Middle Trunk: A continuation of the C7 root. Lower Trunk: Formed by the union of C8 and T1 roots. Key Branches from Trunks: Suprascapular Nerve (C5, C6): From the Upper Trunk; innervates Supraspinatus and Infraspinatus. 3. Divisions (Anterior and Posterior) Each of the three trunks divides into an anterior and a posterior division, passing under the clavicle. The posterior divisions supply future extensors, while the anterior divisions supply future flexors. 4. Cords (Lateral, Posterior, Medial) The six divisions regroup to form three cords, named for their position relative to the axillary artery. Lateral Cord (C5-C7): From the anterior divisions of the upper and middle trunks. Posterior Cord (C5-T1): From the posterior divisions of all three trunks. Medial Cord (C8-T1): From the anterior division of the lower trunk. Key Branches from Cords: Lateral Pectoral Nerve: From the Lateral Cord. Upper & Lower Subscapular Nerves, Thoracodorsal Nerve: From the Posterior Cord. Medial Pectoral Nerve, Medial Cutaneous Nerves: From the Medial Cord. 5. Branches (The 5 Major Terminal Nerves) The three cords give rise to the five major terminal nerves that innervate the entire upper limb. Musculocutaneous Nerve (C5-C7) Motor: Anterior arm compartment (Biceps Brachii, Brachialis, Coracobrachialis).Sensory: Skin of the lateral forearm. Axillary Nerve (C5-C6) Motor: Deltoid and Teres Minor.Sensory: Skin over the lower deltoid (“regimental badge area”). Radial Nerve (C5-T1) Motor: All muscles of the posterior compartments of the arm and forearm (all extensors).Sensory: Posterior skin of arm and forearm, dorsal aspect of lateral 2.5 digits. Median Nerve (C5-T1) Motor: Most anterior forearm muscles (flexors/pronators), and thenar muscles of the thumb.Sensory: Skin of the lateral palm and palmar aspect of the lateral 3.5 digits. Ulnar Nerve (C8-T1) Motor: Two anterior forearm muscles (Flexor Carpi Ulnaris, medial half of FDP) and most intrinsic muscles of the hand.Sensory: Skin of the medial 1.5 digits (palmar and dorsal). Brachial Plexus Summary Table Level Components Key Nerve Branches Clinical Notes ROOTS Anterior Rami of C5, C6, C7, C8, T1 Dorsal Scapular N (C5): Rhomboids, Levator ScapulaeLong Thoracic N (C5-C7): Serratus Anterior Emerge between Scalenes. Injury to Long Thoracic N. → Winged Scapula. TRUNKS Upper: C5 + C6Middle: C7Lower: C8 + T1 Suprascapular N (C5, C6): Supraspinatus, InfraspinatusN. to Subclavius (C5, C6): Subclavius Pass over 1st rib. Erb-Duchenne palsy is an upper trunk injury. DIVISIONS Each trunk divides into an Anterior & Posterior Division No direct named branches. Posterior divisions supply extensors; Anterior supply flexors. CORDS Lateral: Ant. divisions of Upper & MiddlePosterior: Post. divisions of all 3Medial: Ant. division of Lower Lateral Pectoral N.Upper & Lower Subscapular N., Thoracodorsal N.Medial Pectoral N., Medial Cutaneous Nerves Named for position around axillary artery. BRANCHES Terminal Nerves Musculocutaneous N.Axillary N.Radial N.Median N.Ulnar N. Major nerves of the upper limb. Injuries lead to distinct motor & sensory deficits. Brachial Plexus Injuries and Clinical Correlates Upper Plexus Injury (Erb-Duchenne Palsy) Affects C5-C6 roots. Caused by an excessive angle between the neck and shoulder. Results in the classic “Waiter’s Tip” position (adducted shoulder, medially rotated arm, extended elbow). Lower Plexus Injury (Klumpke’s Palsy) Affects C8-T1 roots. Caused by excessive abduction of the arm. Affects intrinsic hand muscles, leading to a “Claw Hand” of the 4th and 5th digits. Radial Nerve Injury (Wrist Drop) Commonly caused by mid-shaft humeral fractures or compression in the axilla (“Saturday night palsy”). Results in an inability to extend the wrist and fingers. Median Nerve Injury (Carpal Tunnel Syndrome) Compression of the median nerve at the wrist. Causes numbness and tingling in the lateral 3.5 digits and weakness/atrophy of the thenar (thumb) muscles. Ulnar Nerve Injury (“Claw Hand”) Injury at the elbow (“funny bone”) or wrist. Affects intrinsic hand muscles, leading to “clawing” of the 4th and 5th digits and sensory loss over the medial hand. Muscles of the Chest (Pectoral Region) 1. Superficial Muscles of the Pectoral Region These muscles connect the upper limb to the anterior and lateral thoracic wall. a. Pectoralis Major A large, fan-shaped muscle covering the upper chest. It is a powerful adductor and medial rotator of the arm. Its clavicular head also flexes the arm, while the sternocostal head helps extend it from a flexed position. b. Pectoralis Minor A thin, triangular muscle lying deep to Pectoralis Major. It depresses the shoulder and protracts the scapula (pulls it forward and downward). c. Subclavius A small muscle located inferior to the clavicle. It anchors and depresses the clavicle, and helps protect the underlying subclavian vessels and brachial plexus. d. Serratus Anterior The “boxer’s muscle” on the lateral thoracic wall. It is the prime mover for protracting the scapula (punching/pushing) and is essential for rotating the scapula to allow for full arm elevation. Paralysis leads to “winged scapula”. 2. Deep Muscles of the Thorax (Associated with Respiration) These muscles are primarily involved in the mechanics of breathing. a. Intercostal Muscles (External, Internal, Innermost) Three layers of muscles in the intercostal spaces. The External Intercostals elevate the ribs for forced inspiration. The Internal and Innermost Intercostals depress the ribs for forced expiration. b. Transversus Thoracis A thin muscle on the inner anterior thoracic

Scroll to Top