Doctors Revision

Anatomy

Stomach and Intestines Anatomy
Anatomy

Stomach and Intestines Anatomy

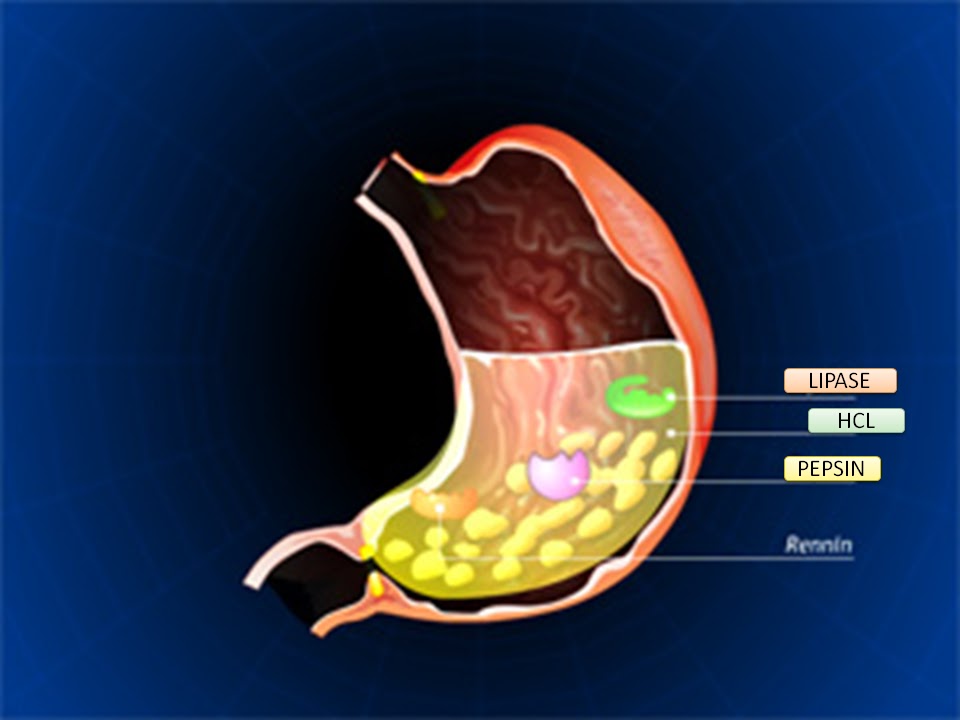
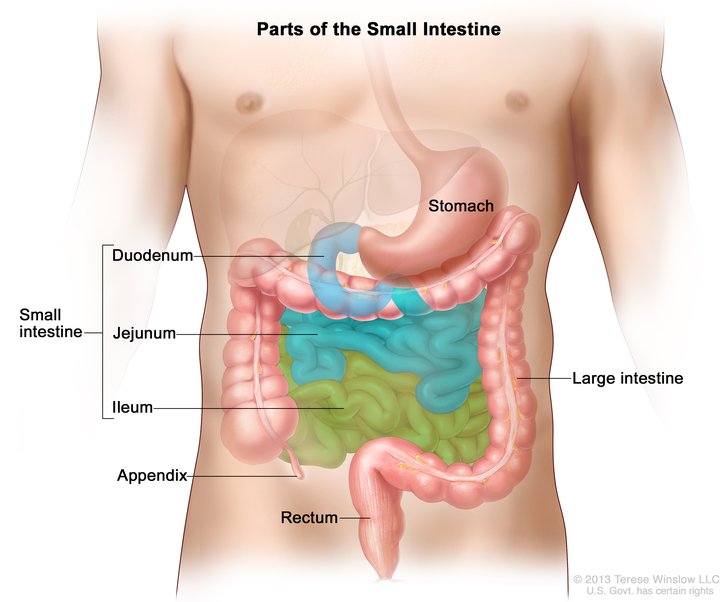
Stomach & Intestines Digestive System Anatomy: Stomach & Intestines GASTROINTESTINAL ANATOMY Stomach The stomach is a dilated, J-shaped organ of the alimentary canal, situated between the esophagus and the duodenum. Functions Storage of food: It acts as a temporary reservoir for ingested food. Mixing and mechanical digestion: It churns food with gastric juices to form chyme. Chemical digestion: Gastric juices (containing hydrochloric acid and enzymes like pepsin) initiate protein digestion. Controlled release: Regulates the slow release of chyme into the duodenum for further digestion and absorption. General Characteristics Capacity: The total capacity of the stomach is approximately 1500 ml. Shape and Position: Its position and shape vary significantly among individuals and with posture and respiration. In short and obese individuals, it tends to be high and more transverse. In tall and thin individuals, it is often elongated and vertical. It typically occupies the epigastric and umbilical regions of the abdomen and is partly covered by the costal diaphragm and the lower ribs. General Structure The stomach has two surfaces, two apertures (orifices), and two curvatures. Surfaces: Anterior surface, Posterior surface. Orifices (Apertures): Cardia: The opening from the esophagus into the stomach. Pylorus: The opening from the stomach into the duodenum. Curvatures: Lesser curvature: The shorter, concave, right border of the stomach. Greater curvature: The longer, convex, left and inferior border of the stomach. Specific Features: Cardia (Cardiac Orifice) Located at the esophagogastric junction. There is no anatomical sphincter in the traditional sense. Instead, a physiological sphincter mechanism is formed by the circular muscle layer of the distal esophagus and stomach, the acute angle of His (where the esophagus joins the stomach), and the diaphragmatic crus. This physiological sphincter relaxes during swallowing to allow food entry and closes afterward to prevent gastroesophageal reflux (regurgitation) of gastric contents back into the esophagus. Pylorus The distal opening of the stomach into the duodenum, located at the gastroduodenal junction. Lesser Curvature Located on the right margin of the stomach. Serves as the attachment site for the lesser omentum. The angular incisure (incisura angularis) is a constant notch on the lesser curvature, marking the junction between the body and the pyloric part of the stomach. Greater Curvature Located on the left margin and inferior border of the stomach. Provides attachment for the gastrosplenic ligament (connecting to the spleen) and the greater omentum (which extends inferiorly, folds back, and attaches to the transverse colon). Anterior Surface: Covered by the peritoneum. The left vagus nerve forms the anterior vagal trunk and predominantly supplies the anterior surface of the stomach. Posterior Surface: Also covered by the peritoneum. The right vagus nerve forms the posterior vagal trunk and predominantly supplies the posterior surface of the stomach. Parts of the Stomach The stomach is typically divided into four main parts: Cardia: The region immediately surrounding the cardiac orifice. Fundus: The dome-shaped part that projects superiorly and to the left of the cardia. It often contains gas. Body: The main part of the stomach, extending from the cardia/fundus to the angular incisure on the lesser curvature. Pylorus (Pyloric Part): The tubular distal part of the stomach connecting it to the duodenum. It is further divided into: Pyloric Antrum: Wider, more proximal part. Pyloric Canal: Narrower, distal part. Pyloric Sphincter: A thickened ring of circular smooth muscle at the gastroduodenal junction. It controls the discharge of chyme from the stomach into the duodenum. The pylorus typically lies on the transpyloric plane (L1). Peritoneal Attachments (Omenta): Lesser Omentum: A two-layered fold of peritoneum that extends from the porta hepatis (on the liver) to the lesser curvature of the stomach and the superior part of the duodenum. It is further divided into: Hepatogastric ligament: From the liver to the lesser curvature of the stomach. Hepatoduodenal ligament: From the liver to the superior part of the duodenum. This is clinically very important as it contains the portal triad: the common bile duct, the proper hepatic artery, and the hepatic portal vein. Greater Omentum: A large, apron-like fold of peritoneum that hangs down from the greater curvature of the stomach and covers the intestines. It contains varying amounts of fat. Gastrosplenic Omentum (Ligament): Connects the greater curvature of the stomach to the hilum of the spleen. Mucous Membrane of the Stomach: The internal lining of the stomach is thrown into numerous folds called rugae. These folds allow the stomach to expand significantly when filled with food and flatten out as it distends. Muscle Layer of the Stomach: The muscularis externa of the stomach is unique among the alimentary canal because it has three layers of smooth muscle, which contribute to its powerful churning action: Outer Longitudinal Layer: Primarily present along the curvatures (lesser and greater). Middle Circular Layer: Surrounds the entire stomach but is particularly prominent at the pylorus (forming the pyloric sphincter) and cardia. Innermost Oblique Layer: Found mainly in the body and fundus, allowing for a unique churning motion. Peritoneum of the Stomach: The stomach is almost entirely intraperitoneal, meaning it is nearly completely covered by visceral peritoneum. The peritoneum leaves the stomach to form the various omenta and ligaments (lesser omentum, greater omentum, gastrosplenic omentum). Relations of the Stomach Anteriorly Anterior abdominal wall Costal margin Left lobe of the liver Left pleura and lung (superiorly) Diaphragm Posteriorly (Stomach Bed) Separated by the lesser sac (omental bursa): Diaphragm (posteriorly, superiorly) Spleen (laterally) Splenic artery (superior border of the pancreas) Left kidney Left suprarenal gland Pancreas Transverse mesocolon and transverse colon Blood Supply of the Stomach The stomach has a rich arterial supply from branches of the celiac trunk, ensuring robust collateral circulation. Arterial Supply Lesser Curvature: Left Gastric Artery: Direct branch of the celiac trunk. Supplies the upper part of the lesser curvature and the abdominal esophagus. Right Gastric Artery: A branch of the proper hepatic artery (which comes from the common hepatic artery, a celiac trunk branch). Supplies the lower part of the lesser curvature. Greater Curvature: Left Gastro-omental (Gastroepiploic) Artery: A branch of the splenic artery. Supplies the upper part of
heart anatomy 1
Anatomy

Heart & Great Vessels

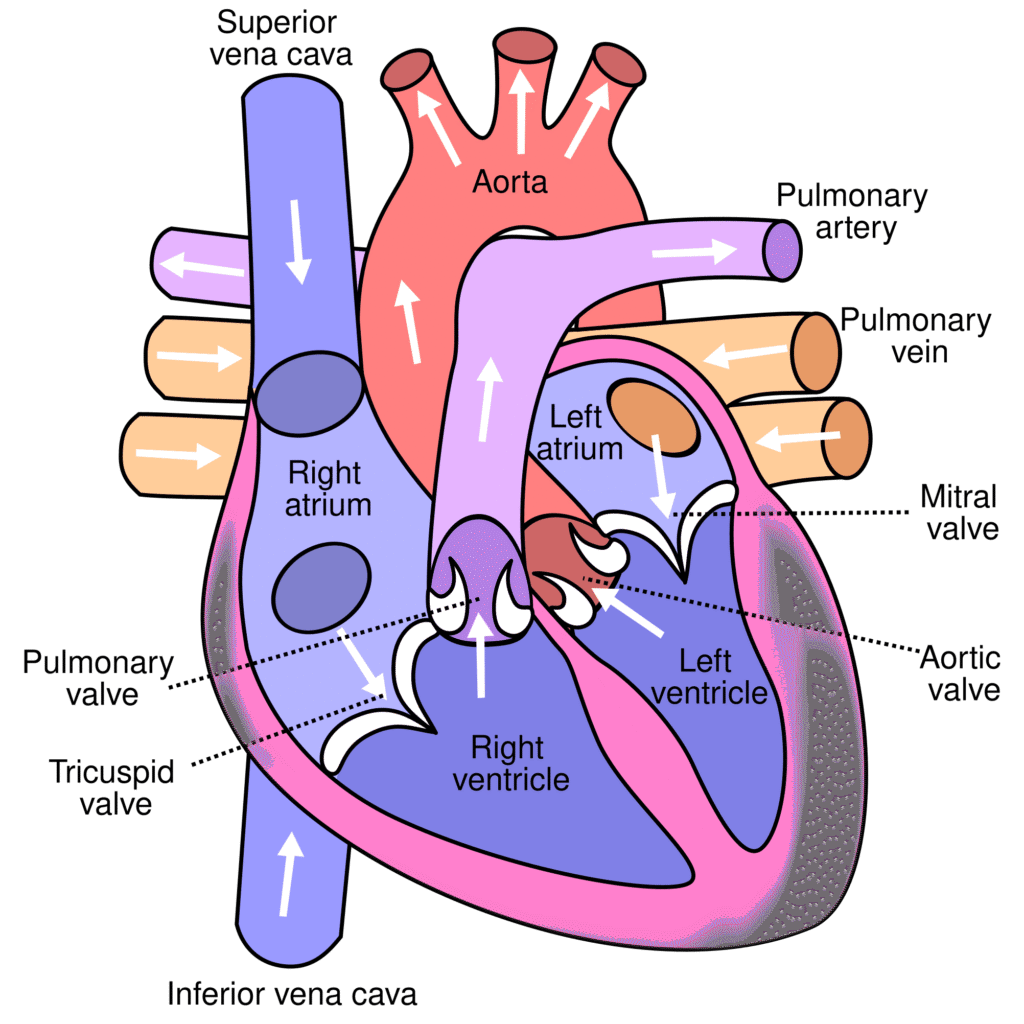
Heart & Great Vessels Anatomy: Heart, Pericardium, Great Vessels & Esophagus GROSS ANATOMY The Heart, Pericardium, and Great Vessels Pericardium The pericardium is a tough, double-layered fibroserous sac that encloses the heart and the roots of the great vessels (aorta, pulmonary trunk, venae cavae, pulmonary veins). Main Functions Lubrication: Contains a small amount of fluid that reduces friction between the moving heart and the surrounding structures. Restriction of Movement: Anchors the heart in the mediastinum, preventing excessive movement and overdistention during sudden increases in blood volume. Protection: Acts as a physical barrier against infection and external trauma. Components The pericardium is composed of two main layers: Fibrous Pericardium (Outer layer) Serous Pericardium (Inner layer) 1. Fibrous Pericardium The fibrous pericardium is the robust, outermost layer of the pericardial sac. Description: It is a thick, tough, inelastic, and conical-shaped fibrous bag that surrounds the heart. Attachments: Inferiorly (Base): It is firmly and broadly fused to the central tendon of the diaphragm. This attachment is crucial for the diaphragm’s role in cardiac stability. Anteriorly: It is loosely attached to the posterior surface of the sternum by the sternopericardial ligaments. Superiorly (Apex): It blends and is fused with the outer connective tissue coats (adventitia) of the great vessels as they enter and leave the heart (aorta, pulmonary trunk, superior vena cava, inferior vena cava, pulmonary veins). Posteriorly: It is attached to the structures in the posterior mediastinum, like the esophagus and aorta. Embryological Origin: Its primary origin is debated, but contributions are thought to come from the septum transversum (which also gives rise to the central tendon of the diaphragm) and pleuropericardial membranes. 2. Serous Pericardium The serous pericardium is a thin, delicate, two-layered membrane that lines the inner surface of the fibrous pericardium and covers the external surface of the heart. Layers: It is divided into two continuous layers: Parietal Layer of Serous Pericardium: This layer lines the inner surface of the fibrous pericardium. Visceral Layer of Serous Pericardium (Epicardium): This layer tightly adheres to the outer surface of the heart itself. It is considered the outermost layer of the heart wall. Pericardial Cavity: The potential space located between the parietal and visceral layers of the serous pericardium. This space normally contains a small amount of serous fluid. Pericardial Cavity and Sinuses A. Pericardial Cavity Description: A potential space located between the parietal and visceral layers of the serous pericardium. Contents: Normally contains a small amount (typically 15-50 mL) of thin, straw-colored serous fluid. Function of Fluid: The pericardial fluid acts as a lubricant, allowing the heart to beat smoothly and with minimal friction within the pericardial sac. Clinical Significance: a. Pericardial Effusion: An abnormal accumulation of fluid in the pericardial cavity. This can be caused by various conditions, including infections (e.g., tuberculosis), inflammation (e.g., pericarditis), autoimmune diseases, trauma, and malignancies (tumors). The term “water in the heart” is a colloquial and somewhat misleading description; it’s fluid around the heart. b. Cardiac Tamponade: A life-threatening condition where a large or rapidly accumulating pericardial effusion compresses the heart, restricting its ability to fill adequately with blood during diastole. This leads to reduced cardiac output and can be fatal if not treated promptly. c. Pericardiocentesis: A medical procedure to aspirate (remove) excess fluid from the pericardial cavity to relieve pressure in cases of pericardial effusion or cardiac tamponade. B. Pericardial Sinuses These are reflections of the serous pericardium that create cul-de-sacs or recesses. Oblique Pericardial Sinus: Location: A blind-ended, inverted U-shaped cul-de-sac located posterior to the heart’s left atrium. Boundaries: It is situated between the reflections of the serous pericardium around the four pulmonary veins and the inferior vena cava (IVC). The posterior wall of the left atrium forms its anterior boundary. Clinical Significance: Allows for surgical access to the posterior surface of the heart. Transverse Pericardial Sinus: Location: A short, transverse tunnel or passage that runs between the great arteries (aorta and pulmonary trunk) anteriorly and the great veins (superior vena cava, inferior vena cava, and pulmonary veins) posteriorly. Clinical Significance: This sinus is strategically important for cardiac surgeons. A surgical clamp can be passed through the transverse sinus to temporarily occlude the aorta and pulmonary trunk during cardiac surgery (e.g., for coronary artery bypass grafting or valve replacement), isolating the heart from the systemic circulation. Innervation and Blood Supply of Pericardium A. Blood Supply of the Pericardium The pericardium receives its arterial supply from several sources: Pericardiacophrenic Artery: The main arterial supply, a branch of the internal thoracic artery. It accompanies the phrenic nerve. Musculophrenic Artery: Another branch of the internal thoracic artery. Branches of the Thoracic Aorta: Small branches directly from the aorta (e.g., bronchial and esophageal arteries). Coronary Arteries: The visceral layer (epicardium) receives some small branches from the coronary arteries. Venous Drainage: Follows the arterial supply, draining into corresponding veins (e.g., pericardiacophrenic veins, internal thoracic veins, azygos system). B. Innervation of the Pericardium The innervation differs for the fibrous/parietal serous layers and the visceral serous layer. Fibrous Pericardium and Parietal Layer of Serous Pericardium: Innervation: Primarily supplied by the phrenic nerves (C3, C4, C5). Sensitivity: These layers are richly innervated and are sensitive to pain, temperature, pressure (touch), and stretch. Referred Pain: Because the phrenic nerves also supply sensory innervation to the C3-C5 dermatomes, pain originating from these pericardial layers is often referred to the ipsilateral (same side) shoulder, neck, and supraclavicular region. (The original mention of “left jaw” is less common for pericardial pain referral than the shoulder and neck). Visceral Layer of Serous Pericardium (Epicardium): Innervation: Supplied by the autonomic nervous system (sympathetic and parasympathetic fibers) from the cardiac plexuses. Sensitivity: This layer is generally considered insensitive to pain, temperature, and touch. It is primarily sensitive to stretch. Function: Autonomic innervation primarily modulates cardiac function rather than providing somatic sensation from the epicardium itself. The Heart The heart is a hollow, muscular organ that acts as a pump, circulating blood throughout the entire body to deliver oxygen and nutrients and remove waste products. Shape: It is

rib cage and diaphragm anatomy
Anatomy

Rib Cage & Diaphragm Anatomy

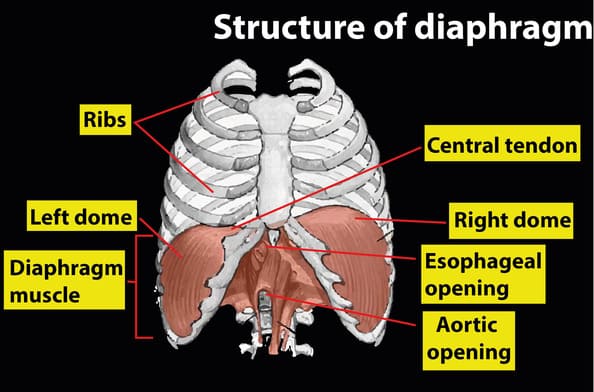
Rib Cage & Diaphragm Anatomy Anatomy: The Rib Cage and Diaphragm THORACIC ANATOMY The Rib Cage: An Overview The thoracic cage, commonly known as the rib cage, is a robust bony-cartilaginous framework that forms the skeletal wall of the chest. It serves several critical functions: Protection: Encapsulates and safeguards vital thoracic organs, including the heart, lungs, and great vessels, as well as parts of the upper abdominal organs (liver, spleen). Muscle Attachment: Provides numerous points of attachment for muscles of the neck, back, chest, and upper limbs, playing a role in posture and movement. Respiration: Its flexible, expandable structure is fundamental to the mechanics of breathing, allowing for changes in thoracic volume during inspiration and expiration. Support: Forms the central axial skeleton to which the pectoral girdle and upper limbs are attached. Shape and Location: The rib cage is situated in the thorax, the region of the trunk between the neck and the abdomen. Its overall shape is that of a truncated cone, wider inferiorly than superiorly. It is characteristically flattened anteriorly and posteriorly (dorsoventrally) but rounded laterally, creating a spacious cavity within. Boundaries of the Thoracic Cage The thoracic cage forms a well-defined compartment with distinct boundaries: Anterior Boundary: Formed by the sternum (breastbone) and the articulating costal cartilages. Posterior Boundary: Formed by the twelve thoracic vertebrae and their associated intervertebral discs. Lateral Boundaries: Consist of the twelve pairs of ribs, which extend from the thoracic vertebrae posteriorly to the sternum or costal cartilages anteriorly. Superior Boundary: Thoracic Inlet (Superior Thoracic Aperture): A relatively small, kidney-shaped opening. Formed by: The superior aspect of the first thoracic vertebra (T1) posteriorly, the medial border of the first ribs laterally, and the superior border of the manubrium anteriorly. This aperture provides passage for structures (e.g., trachea, esophagus, major vessels, nerves) between the neck and the thoracic cavity. Inferior Boundary: Thoracic Outlet (Inferior Thoracic Aperture): A much larger, irregular opening. Formed by: The 12th thoracic vertebra (T12) posteriorly, the 11th and 12th pairs of ribs laterally, and the costal margin (formed by the cartilages of ribs 7-10) and the xiphoid process anteriorly. This aperture is almost completely sealed by the diaphragm, which separates the thoracic cavity from the abdominal cavity. The Sternum (Breastbone) The sternum, or breastbone, is a flat, elongated bone positioned in the central anterior aspect of the thoracic cage. It forms the anterior articulation for the ribs via their costal cartilages. Composition: The sternum is typically divided into three fused parts: Manubrium Sterni (Handle) Location: The broadest, most superior part of the sternum. Vertebral Level: Roughly lies opposite the T3 and T4 vertebral bodies. Articulations: Superiorly: The suprasternal (jugular) notch is at its superior border. Lateral to the notch are the clavicular notches for articulation with the clavicles (forming the sternoclavicular joints). Laterally: Possesses facets for articulation with the costal cartilages of the first pair of ribs and the upper half of the second pair of ribs. These are synovial joints, permitting slight movement. Inferiorly: Articulates with the body of the sternum at the manubriosternal joint. Body of the Sternum (Gladiolus) Location: The longest, central part of the sternum. Articulations: Superiorly: Articulates with the manubrium at the manubriosternal joint. Laterally: Contains facets for articulation with the costal cartilages of the lower half of the second ribs through the seventh ribs. Inferiorly: Articulates with the xiphoid process at the xiphisternal joint. Xiphoid Process Location: The smallest, most inferior part of the sternum. Vertebral Level: The xiphisternal joint is typically at the level of the T9 vertebral body. Characteristics: It is highly variable in shape and size. It generally does not articulate with any ribs. It remains cartilaginous in young individuals and gradually undergoes ossification (hardens into bone) from its proximal end, a process that completes in adulthood and continues into old age. Joints of the Sternum: Manubriosternal Joint (Sternal Angle / Angle of Louis): A secondary cartilaginous joint (symphysis) between the manubrium and the body. It forms a palpable transverse ridge. Xiphisternal Joint: A secondary cartilaginous joint between the body and the xiphoid process. It typically fuses completely in older adults. Clinical Uses of the Sternum A. Diagnostic and Therapeutic Procedures Median Sternotomy (Median Thoracotomy): Procedure: A surgical incision made longitudinally down the center of the sternum, which is then divided using a saw. Purpose: Provides wide surgical access to the mediastinum (heart, great vessels, trachea, thymus) for procedures such as cardiac surgery (e.g., coronary artery bypass grafting, valve replacement) and lung transplantation. The sternum is typically rejoined with wires post-surgery. Bone Marrow Biopsy/Aspiration: Procedure: Due to its broad, flat, and relatively superficial nature, the sternum (particularly the manubrium) is a common site for obtaining bone marrow samples. A needle is inserted into the sternum to extract marrow for diagnostic purposes (e.g., in cases of leukemia, anemia, or other hematological disorders). This site is chosen to avoid vital organs directly below and due to its accessibility. B. Congenital Anomalies of the Sternum Congenital malformations of the sternum primarily involve abnormalities in its shape, which can affect respiratory and cardiac function in severe cases. Pectus Carinatum (Pigeon Chest): Description: A chest wall deformity characterized by an outward protrusion of the sternum and costal cartilages. Appearance: Gives the chest a prominent, “pigeon-breasted” appearance. Clinical Significance: Usually cosmetic, but severe cases can restrict lung expansion and cardiac function, especially during strenuous exercise. Pectus Excavatum (Funnel Chest): Description: The most common sternal deformity, characterized by an inward depression of the sternum and costal cartilages. Appearance: Creates a “funnel-shaped” indentation in the chest. Clinical Significance: Ranges from mild cosmetic concerns to severe cases where the sternum compresses the heart and lungs, potentially leading to respiratory and cardiac compromise (e.g., reduced exercise tolerance). (The “Cup-shaped deformity” and “Saucer-shaped” descriptions in the original text likely refer to variations or degrees of Pectus Excavatum.) Horns-of-Steer Deformity: (This term is less common in standard medical literature but may refer to a specific variant of chest wall deformity where the costal cartilages project laterally or superiorly, resembling horns, often associated

digestion
Anatomy

Digestion, Absorption & GIT Disorders

Digestion, Absorption & GIT Disorders Digestion, Absorption & GIT Disorders GASTROINTESTINAL PHYSIOLOGY Digestion, Absorption & GIT Disorders Digestion is the process of breaking down complex food molecules into simpler forms that can be absorbed by the body. Absorption is the subsequent process of transporting these digested nutrients from the lumen of the GI tract into the bloodstream or lymphatic system. I. Why Digestion? The human body relies on three main macronutrients: 1. Carbohydrates, 2. Fats, 3. Proteins. Additionally, small quantities of vitamins and minerals are essential. These macronutrients, in their natural, complex forms (e.g., starch, triglycerides, large proteins), cannot be directly absorbed through the gastrointestinal (GIT) mucosa. They are “useless as nutrients without preliminary digestion.” Digestion by Hydrolysis Digestion primarily occurs through hydrolysis, a chemical process where water molecules are added to break down larger molecules into smaller ones. This process reverses the condensation reactions that originally formed these macromolecules. Carbohydrates Exist mostly as large polysaccharides (e.g., starch) or disaccharides (e.g., sucrose, lactose). Formed by condensation (removal of a water molecule between monosaccharide units). Hydrolysis, catalyzed by specific enzymes, reverses this, yielding monosaccharides. Fats Exist as triglycerides (one glycerol molecule attached to three fatty acid molecules). Formed by condensation, with three water molecules removed. Hydrolysis, by fat-digesting enzymes, reverses this, forming fatty acids and glycerol. Proteins Formed from multiple amino acids linked by peptide bonds (a condensation reaction). Proteolytic enzymes (proteases) reverse this, breaking peptide bonds to yield smaller peptides and ultimately amino acids. II. Digestion of Specific Macronutrients A. Digestion of Carbohydrates Major Dietary Sources: Sucrose: Disaccharide, commonly known as cane sugar. Lactose: Disaccharide, found in milk. Starches: Large polysaccharides, present in almost all non-animal foods (e.g., potatoes, grains). Other Minor Sources: Amylose, glycogen, alcohol, lactic acid, pyruvic acid, pectins, dextrins, and minor carbohydrate derivatives in meats. Cellulose: Not digestible by humans as we lack the necessary enzymes. Locations of Digestion: Mouth: Salivary amylase (ptyalin) initiates starch digestion, breaking it into smaller polysaccharides (dextrins) and some maltose. Accounts for about 5% of carbohydrate digestion. Stomach: Salivary amylase continues to act in the fundus and body of the stomach until it is inactivated by the acidic gastric juice. Can digest 30-40% of starches into dextrins and maltose. Small Intestine (Final Stage): This is where the bulk of carbohydrate digestion occurs. Pancreatic Amylase: Secreted by the pancreas into the duodenum, it breaks down starches and dextrins into maltose and other small glucose polymers. Brush Border Enzymes: Located on the microvilli of enterocytes (intestinal epithelial cells). These enzymes are responsible for the final breakdown of disaccharides into monosaccharides: Lactase: Digests lactose into glucose and galactose. Sucrase: Digests sucrose into glucose and fructose. Maltase: Digests maltose and other small glucose polymers into glucose. Final Products: The final products of carbohydrate digestion are exclusively monosaccharides (glucose, galactose, fructose), which are the only forms absorbable into the bloodstream. B. Digestion of Proteins Locations of Digestion: Stomach: Pepsin: Secreted by chief cells as pepsinogen and activated by hydrochloric acid (HCl) at a pH of 2-3. Pepsin initiates protein digestion, breaking down proteins into proteoses, peptones, and large polypeptides. Accounts for 10-20% of total protein digestion. Small Intestine: Pancreatic Secretions: The majority of protein digestion occurs in the upper small intestine (duodenum and jejunum) due to powerful pancreatic proteolytic enzymes. Trypsin, Chymotrypsin, Carboxypolypeptidase, Proelastase: These enzymes (secreted as inactive zymogens and activated in the duodenum) break down proteins, proteoses, peptones, and large polypeptides into smaller polypeptides, tripeptides, dipeptides, and a few free amino acids. Brush Border Peptidases (in Enterocytes): Located on the luminal surface of enterocytes lining the intestinal villi (especially in the duodenum and jejunum). Aminopolypeptidase and Dipeptidases: These enzymes further digest the small polypeptides, tripeptides, and dipeptides into their final absorbable form: amino acids. End Products of Luminal Digestion: Dipeptides, tripeptides, and amino acids. Final Absorbable Form: Over 99% of the final protein products are absorbed as amino acids. C. Digestion of Fats Primary Location: Almost entirely occurs in the small intestine. Two Main Steps: Emulsification: Large fat globules are broken down into smaller droplets. Bile Acids and Lecithin: These components of bile, secreted by the liver, are amphipathic molecules that surround fat droplets, reducing their surface tension and preventing them from coalescing. This process increases the surface area of fat by approximately 1000-fold, making it accessible to water-soluble digestive enzymes. Enzymatic Action: Pancreatic Lipase: The most important enzyme for fat digestion, secreted by the pancreas. It hydrolyzes triglycerides into monoglycerides and free fatty acids. Enteric Lipase: Also present in the small intestine, contributing to fat digestion. Cholesterol Ester Hydrolase: Hydrolyzes cholesterol esters into cholesterol and fatty acids. Phospholipase A2: Hydrolyzes phospholipids (like lecithin) into lysophospholipids and fatty acids. Final Products: Monoglycerides, free fatty acids, cholesterol, and lysophospholipids. III. Absorption of Digested Food Absorption is the process by which digested food materials move from the lumen of the GIT into the blood or lymph. Mechanisms: Involves both passive processes (e.g., diffusion, osmosis) and active processes (e.g., active transport, co-transport). Fluid Balance: Total fluid ingested per day: ~1.5 liters. Total fluid secreted into GIT (saliva, gastric juice, bile, pancreatic juice, intestinal secretions): ~7 liters. Total fluid entering small intestine: ~8.5 liters. Total fluid absorbed per day: ~8-9 liters. Most absorption (all but ~1.5 liters) occurs in the small intestine. Only about 1.5 liters pass through the ileocecal valve into the colon each day. A. Absorptive Surface of the Small Intestine The small intestine has an enormous surface area, crucial for efficient absorption. This is achieved through multiple levels of folding: Valvulae Conniventes (Folds of Kerckring): Large circular folds of the mucosa and submucosa, particularly well-developed in the duodenum and jejunum (up to 8mm high), increasing surface area by ~3-fold. Villi: Millions of small, finger-like projections (0.5-1mm long) covering the entire surface of the small intestine. Each villus is covered by epithelial cells and contains a lacteal (lymphatic capillary) and a rich capillary network. Villi increase surface area by ~10-fold. Microvilli (Brush Border): Each epithelial cell covering the villi has thousands of microscopic, hair-like projections called

Gastrointestinal GIT Secretions 1
Anatomy

Gastrointestinal (GIT) Secretions

GIT Secretions Gastrointestinal Secretions Physiology SYSTEMS PHYSIOLOGY Gastrointestinal (GIT) Secretions The gastrointestinal tract is equipped with a diverse array of secretory glands that play two fundamental roles: Secretion of Digestive Enzymes: These enzymes are essential for breaking down complex food molecules into absorbable units. This enzymatic activity occurs from the mouth all the way to the distal end of the ileum. Provision of Mucus: Mucus serves as a lubricant and protective barrier for the entire GIT, from the mouth to the anus. Key Principle: The presence of food in the GIT is the primary stimulus for secretions. The quantity and type of secretions are precisely regulated to match the amount and type of food present, ensuring efficient digestion. Anatomical Types of Glands in the GIT The GIT houses several types of glands, each contributing to the overall secretory process: Goblet Cells/Simple Mucous Cells: These are single-celled glands interspersed among the epithelial cells. They directly extrude mucus onto the epithelial surface, providing immediate lubrication and protection. They are found throughout the GIT. Crypts of Lieberkühn: These are invaginations or pits found deep within the mucosa of the small intestine and large intestine. They contain various specialized secretory cells, including enterocytes (which secrete water and electrolytes), goblet cells, and enteroendocrine cells. Tubular Glands: These glands are typically found deeper within the mucosal layer. Stomach: Examples include the oxyntic glands (gastric glands) in the body and fundus, which secrete acid, pepsinogen, intrinsic factor, and mucus, and pyloric glands in the antrum, which secrete mucus and gastrin. Upper Duodenum: Brunner’s glands, located in the submucosa of the duodenum, secrete alkaline mucus to protect against acidic chyme from the stomach. Complex Glands (Extramural Glands): These are large, accessory glands located outside the wall of the GIT but connected to it by ducts. They provide copious secretions crucial for digestion or emulsification. Salivary Glands: Produce saliva for initial digestion and lubrication. Pancreas: Secretes pancreatic juice containing a wide array of digestive enzymes and bicarbonate. Liver: Produces bile, essential for fat emulsification. Mechanism of Secretion by Glandular Cells Glandular cells in the GIT typically secrete two main types of substances simultaneously: Organic Substances: This includes digestive enzymes (proteins), mucin (glycoproteins), and hormones. These are synthesized within the cells and packaged into vesicles before exocytosis. Water and Electrolytes: These are secreted to create a fluid environment for the organic substances and to aid in transport and hydration. The movement of water and electrolytes is often regulated by ion pumps and channels, creating osmotic gradients. Mucus: Properties and Role Mucus is a vital secretion found throughout the GIT, acting as both a lubricant and a protectant. Composition: Mucus is a thick, viscous secretion primarily composed of water, electrolytes, and a mixture of several glycoproteins. These glycoproteins are large polysaccharides with smaller quantities of protein attached. Key Properties: Adherent Qualities: Mucus readily adheres to surfaces, forming a continuous coating. Coats the Gut Wall: It has sufficient “body” or viscosity to effectively coat and protect the entire luminal surface of the GIT. Low Resistance for Slippage: Provides a slippery surface, allowing food (bolus or chyme) to move easily along the tract without causing damage. Causes Fecal Particles to Adhere: In the large intestine, mucus helps bind fecal particles together, facilitating their smooth passage. Strongly Resistant to Digestion: Its complex structure and chemical properties make it highly resistant to breakdown by digestive enzymes, ensuring its protective function. Amphoteric Glycoproteins: The glycoproteins in mucus are amphoteric, meaning they can act as both an acid and a base. This property allows mucus to buffer against both acidic and alkaline conditions, protecting the underlying mucosa. The 4 Main Secretions of the GIT 1. Saliva Saliva is the first major digestive secretion, produced by the salivary glands in the mouth. A. Salivary Glands Three Principal Glands (Major Salivary Glands): Parotid Glands: Largest salivary glands, located below and in front of the ears. They secrete entirely serous (watery, enzyme-rich) saliva. Submandibular Glands: Located under the floor of the mouth. They secrete a mixed serous and mucous saliva. Sublingual Glands: Smallest of the major glands, located under the tongue. They primarily secrete mucous saliva, with some serous component. Minor Salivary Glands: Numerous small buccal glands (and other minor glands throughout the oral cavity) secrete only mucus. Daily Secretion Volume: The total daily secretion of saliva ranges between 800 and 1500 ml, with an average of about 1000 ml. B. Composition of Saliva Saliva is a complex fluid containing two major types of protein secretions: Serous Secretion: A watery fluid containing digestive enzymes. The main enzyme is ptyalin (salivary α-amylase), which initiates carbohydrate digestion. Mucus Secretion: Contains mucin, a glycoprotein that provides lubrication. pH of Saliva: Between 6.0 and 7.0, which is slightly acidic to neutral. C. How Saliva is Secreted (Two-Stage Process) Saliva is not a simple ultrafiltrate. Its composition is modified as it passes through the ducts. A typical submandibular gland, being a compound gland, illustrates this two-stage process: Primary Secretion by Acini: The acinar cells (the secretory units) produce a “primary secretion” that is roughly isotonic with plasma. This primary secretion contains ptyalin (α-amylase) and/or mucin, along with water and ions (similar to extracellular fluid). Modification in Salivary Ducts: As the primary secretion flows through the salivary ducts, significant changes occur: Sodium (Na+) Reabsorption: Na+ is actively reabsorbed from the ductal lumen into the interstitial fluid. Potassium (K+) Secretion: K+ is actively secreted from the interstitial fluid into the ductal lumen. Chloride (Cl-) Reabsorption: Cl- is reabsorbed passively, following Na+ due to the electrical gradient. Bicarbonate (HCO3-) Secretion: Bicarbonate ions are actively secreted by the ductal epithelium into the duct lumen. Net Effect: The net reabsorption of Na+ and Cl- is greater than the secretion of K+ and HCO3-. This results in a hypotonic final saliva (more dilute than plasma), especially at lower flow rates. D. Function of Saliva in Oral Hygiene The mouth is constantly exposed to pathogenic bacteria and food particles. Saliva plays a crucial role in maintaining oral health: Washing Action: Saliva

git neuro and motility
Anatomy

GIT Neuro & Motility

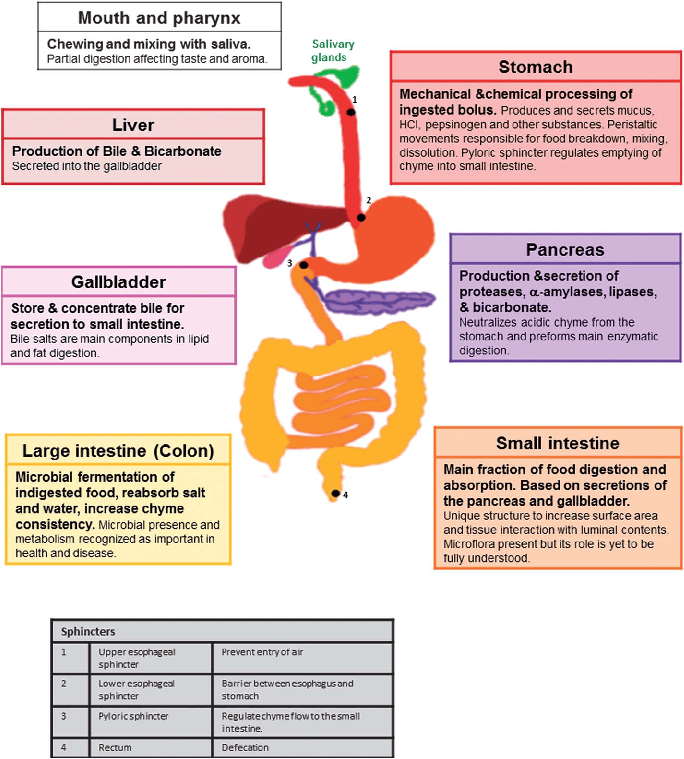
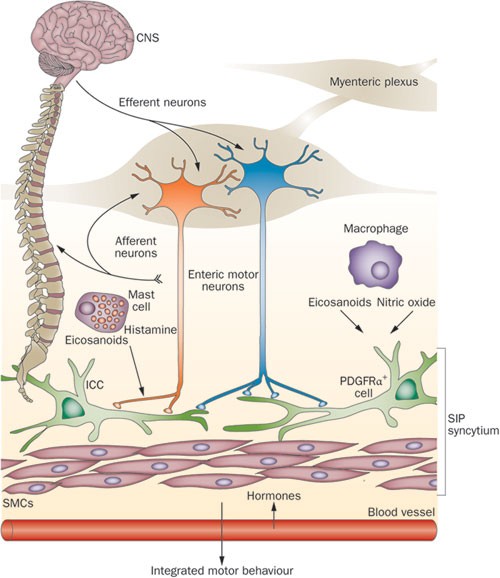
Digestive/GIT Neuro & Motility Digestive System Physiology SYSTEMS PHYSIOLOGY The Digestive System Physiology The digestive system is a vital organ system responsible for breaking down food into absorbable nutrients, water, and electrolytes, and then eliminating indigestible waste. It can be broadly divided into two main parts: the gastrointestinal tract (GIT), also known as the alimentary canal or gut, and accessory digestive organs. I. Components of the Digestive System A. The Gastrointestinal Tract (GIT) / Alimentary Canal This is a continuous, muscular tube that extends from the mouth to the anus, about 30 feet (9 meters) long in a cadaver (shorter in a living person due to muscle tone). It is the primary site where digestion and absorption occur. Mouth: The entrance, where mechanical digestion (chewing) and initial chemical digestion (salivary enzymes) begin. Pharynx: A common passageway for food and air. Esophagus: A muscular tube that transports food from the pharynx to the stomach via peristalsis. Stomach: A muscular sac for food storage, mechanical churning, and initiation of protein digestion. Small Intestine: The primary site for chemical digestion and nutrient absorption. It’s divided into the duodenum, jejunum, and ileum. Large Intestine (Colon): Primarily involved in water and electrolyte absorption, and formation/storage of feces. B. Accessory Digestive Organs These organs produce secretions that aid in digestion or help with the mechanical breakdown of food, but food does not pass directly through them. Teeth: Mechanically break down food (mastication). Tongue: Aids in tasting, chewing, and swallowing food. Salivary Glands (parotid, submandibular, sublingual): Produce saliva, containing enzymes (e.g., amylase for starch) and mucus. Liver: Produces bile (important for fat digestion), metabolizes nutrients, and detoxifies. Gallbladder: Stores and concentrates bile produced by the liver. Pancreas (exocrine part): Produces a wide range of digestive enzymes (for carbohydrates, proteins, fats) and bicarbonate to neutralize stomach acid. II. Key Roles of the GIT The primary function of the GIT is to provide the body with essential water, electrolytes, and nutrients. To achieve this, it performs six fundamental processes: Ingestion: Taking food into the digestive tract, typically through the mouth. Propulsion (Movement of Food): Moving food through the alimentary canal, which includes: Swallowing (Deglutition): Voluntary and involuntary. Peristalsis: Rhythmic waves of contraction and relaxation of smooth muscle in the organ walls, pushing food forward. Mechanical Digestion: Physical breakdown of food into smaller pieces to increase surface area for enzyme action. This includes chewing (mastication), churning in the stomach, and segmentation in the small intestine. Chemical Digestion: Enzymatic breakdown of complex food molecules into their simpler chemical building blocks (e.g., carbohydrates into monosaccharides, proteins into amino acids, fats into fatty acids and glycerol). Absorption: The passage of digested nutrients, vitamins, minerals, and water from the lumen of the GIT into the blood or lymph. Defecation: Elimination of indigestible substances and waste products from the body in the form of feces. III. Structure of the GIT Wall (The Four Tunics) The wall of the GIT from the esophagus to the anal canal has a consistent pattern of four distinct layers, or tunics, from the innermost to the outermost: Mucosa (Innermost Layer): Epithelium: Lines the lumen, specialized for secretion of mucus, digestive enzymes, and hormones, and for absorption of digested nutrients. Protects against disease. Lamina Propria: Loose connective tissue with capillaries (for absorption) and lymphoid follicles (MALT – mucosa-associated lymphoid tissue, for defense). Muscularis Mucosae: A thin layer of smooth muscle that produces local movements of the mucosa, facilitating absorption and secretion. Submucosa: Dense connective tissue containing blood and lymphatic vessels, lymphoid follicles, and nerve fibers (submucosal plexus/Meissner’s plexus). These nerves help regulate glands and smooth muscle in the mucosa. Muscularis Externa (Muscularis): Responsible for segmentation and peristalsis. Typically consists of two layers of smooth muscle: Inner Circular Layer: Fibers run around the circumference of the organ. Contraction constricts the lumen. Outer Longitudinal Layer: Fibers run parallel to the long axis of the organ. Contraction shortens the organ. An additional oblique muscle layer is found only in the stomach, aiding in its powerful churning action. Contains the myenteric plexus (Auerbach’s plexus) between the two muscle layers, which controls GIT motility. Serosa (Outermost Layer): The protective outermost layer, which is the visceral peritoneum in most parts of the alimentary canal. It is a thin layer of areolar connective tissue covered with mesothelium. In the esophagus, the outermost layer is an adventitia (fibrous connective tissue) instead of serosa. IV. Smooth Muscles of the GIT and Electrical Activity The smooth muscle of the muscularis externa is crucial for the motor functions of the GIT. A. Characteristics of GI Smooth Muscle: Individual fibers are small (200-500 µm long, 2-10 µm diameter). Arranged in bundles (up to 1000 fibers) separated by loose connective tissue. Functional Syncytium: Muscle fibers within a layer (and between layers) are electrically connected by gap junctions. This allows action potentials to spread rapidly from one fiber to the next, causing the entire muscle layer or bundle to contract as a single unit. B. Electrical Activity: The resting membrane potential (RMP) of GI smooth muscle is unstable and fluctuates, typically averaging around -56 mV. Two basic types of electrical waves characterize its activity: 1. Slow Waves (Basic Electrical Rhythm – BER) Not true action potentials. They are undulating, rhythmic fluctuations in the RMP, oscillating between -50 and -60 mV. Caused by pacemaker cells called Interstitial Cells of Cajal (ICCs), which act as electrical pacemakers. They set the maximum frequency of contraction. Slow waves themselves usually do not cause muscle contraction, except in some areas like the stomach where they might be strong enough. Their primary role is to set the stage for action potentials. 2. Spike Potentials (True Action Potentials) These are true action potentials that occur when the RMP of a slow wave depolarizes sufficiently (typically becoming less negative than -40 mV, reaching the threshold for excitation). The higher the peak of the slow wave rises above the threshold, the greater the frequency of spike potentials (1 to 10 spikes/second), leading to stronger and more prolonged muscle contraction. Ionic Basis: These action

Transport Across Nephron Segments 1
Anatomy

Renal Clearance and Micturition

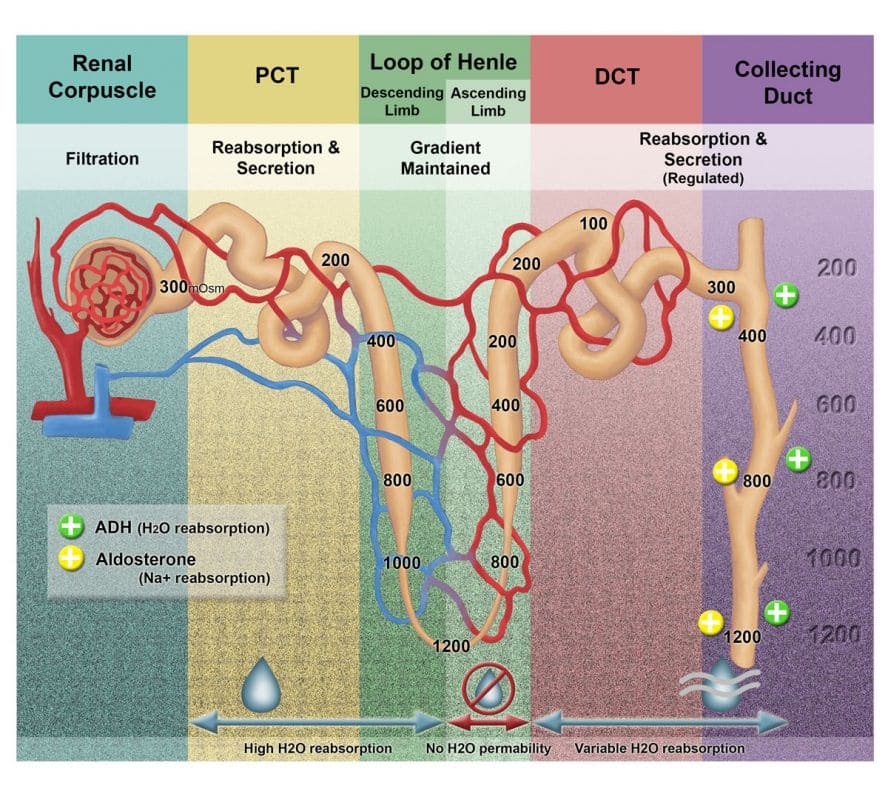
Renal Clearance & Micturition Systems Physiology: Renal Clearance & Micturition Unit: Systems Physiology Renal Clearance Clearance is a quantitative measure of how effectively the kidneys remove a particular substance from the blood plasma. It represents the hypothetical volume of plasma that would be completely cleared of a substance per unit of time. Mathematical Definition: The general formula for clearance (Cx) of any substance X is: Cx = (Ux * V) / Px Cx = Renal clearance of substance X (in mL/min or mL/s) Ux = Concentration of substance X in urine (e.g., mg/dL or mg/mL) V = Urine flow rate (e.g., mL/min) Px = Concentration of substance X in plasma (e.g., mg/dL or mg/mL) Interpretation of the Formula: (Ux * V) represents the excretion rate of substance X – the total amount of X removed from the body via urine per minute. Px represents the concentration of X in the “incoming” plasma. Thus, clearance essentially asks: “What volume of plasma must have been ‘purified’ to account for the amount of substance X excreted in the urine?” Relationship to Renal Handling: The amount of substance excreted is a net result of three processes: Excretion Rate = Filtration Rate – Reabsorption Rate + Secretion Rate Ux * V = (GFR * Px) – T_reabsorption + T_secretion GFR = Glomerular Filtration Rate T_reabsorption = Tubular reabsorption rate T_secretion = Tubular secretion rate Importance of Renal Clearance Renal clearance measurements are invaluable tools for assessing various aspects of renal function: Quantifying Glomerular Filtration Rate (GFR): The gold standard for measuring kidney function. Estimating Renal Plasma Flow (RPF): Gives insight into blood supply to the kidneys. Assessing Severity of Renal Damage: Decreased GFR and RPF can indicate kidney disease progression. Characterizing Tubular Reabsorption: By comparing a substance’s clearance to GFR, we can determine if it’s reabsorbed. Characterizing Tubular Secretion: Similarly, by comparison to GFR, we can determine if a substance is secreted. Clearance Tests: Endogenous vs. Exogenous Markers Endogenous Markers Substances naturally produced by the body. Creatinine: Clinically most common for GFR estimation. Urea: Not a good GFR marker due to significant reabsorption. Uric Acid: Significant reabsorption and secretion. Exogenous Markers Substances administered externally for diagnostic purposes. Inulin: The gold standard for GFR research. Para-aminohippuric acid (PAH): Gold standard for RPF measurement. Diodrast: Similar properties to PAH, historically used for RPF. Measurement of Glomerular Filtration Rate (GFR) GFR is the volume of fluid filtered from the glomerular capillaries into Bowman’s capsule per unit time. It’s the best overall index of kidney function. Criteria for an Ideal GFR Marker: An ideal substance for measuring GFR must possess the following characteristics: Freely Filtered: It must pass unimpeded across the glomerular filtration barrier. Not Reabsorbed: No reabsorption from the renal tubules back into the blood. Not Secreted: No secretion from the blood into the renal tubules. Not Metabolized: It should not be broken down by the kidneys or other tissues. Not Stored: Should not accumulate in the body. Not Protein Bound: If bound, only the free fraction is filtered. Physiologically Inert/Non-toxic: Should not affect renal function or be harmful. Easily Measured: Detectable in plasma and urine with reliable assays. 1. Inulin Clearance: The Gold Standard for Research GFR Properties: Perfectly fits all criteria for an ideal GFR marker. It is a polysaccharide, freely filtered, and neither reabsorbed nor secreted. Method: Requires continuous intravenous infusion to maintain a steady plasma concentration. Urine is collected over a timed period. Limitation: It is exogenous and requires continuous infusion, making it impractical for routine clinical use. Calculation Example: Assume: – [inulin]urine = 30mg/ml – [inulin]plasma = 0.5mg/ml – Urine flow rate = 2ml/ml GFR = 120ml/min 2. Creatinine Clearance: The Clinical Standard for GFR Estimation Properties: Endogenously produced by muscle metabolism at a relatively constant rate. Freely filtered at the glomerulus. A small amount is secreted by the proximal tubule (error 1: amount excreted > amount filtered). This means creatinine clearance slightly overestimates true GFR. Analytical Interference: Older spectrophotometric methods (e.g., Jaffe reaction) detect chromogens other than true creatinine, leading to an overestimation of plasma creatinine concentration (error 2). Clinical Utility: Convenience: Does not require intravenous infusion. Can be estimated from a 24-hour urine collection or, more commonly, estimated from serum creatinine using prediction equations (e.g., Cockcroft-Gault, MDRD, CKD-EPI). Fortuitous Cancellation of Errors: In healthy individuals, the overestimation of GFR due to secretion is often roughly canceled out by the overestimation of plasma creatinine by older assays. However, this balance is disturbed in kidney disease, extreme muscle mass, or with certain medications. General Principle: Relating Clearance to Renal Handling The comparison of a substance’s clearance (Cx) with the GFR (measured by Cinulin or estimated by Ccreatinine) provides insight into how the kidney handles that substance: If Cx = Cinulin (or GFR): The substance is only filtered (not reabsorbed, not secreted). Example: Inulin. If Cx < Cinulin (or GFR): The substance is filtered and net reabsorbed by the renal tubules. The kidneys remove less of the substance from the plasma than the volume of plasma filtered. Example: Glucose (normally 100% reabsorbed, so clearance is 0 unless plasma glucose exceeds tubular maximum), sodium, urea. Note: If a substance is completely reabsorbed (e.g., glucose at normal plasma levels), its clearance is effectively 0. If Ux * V = 0, then Cx = 0. If Cx > Cinulin (or GFR): The substance is filtered and net secreted by the renal tubules. The kidneys remove more of the substance from the plasma than the volume of plasma filtered. This indicates that the tubules are actively adding the substance to the urine. Example: PAH, creatinine (to a small extent). Measurement of Renal Plasma Flow (RPF) RPF is the volume of plasma flowing through the kidneys per unit time. Ideal RPF Marker Criteria: An ideal substance for measuring RPF must be: Freely Filtered. Completely Secreted: All of the substance that enters the renal artery (both filtered and non-filtered) must be removed by either filtration or tubular secretion in a single pass through the kidney. Not Reabsorbed. Not Metabolized

Renal Physiology and Renal Haemodynamics
Anatomy

Renal Physiology and Renal Haemodynamics

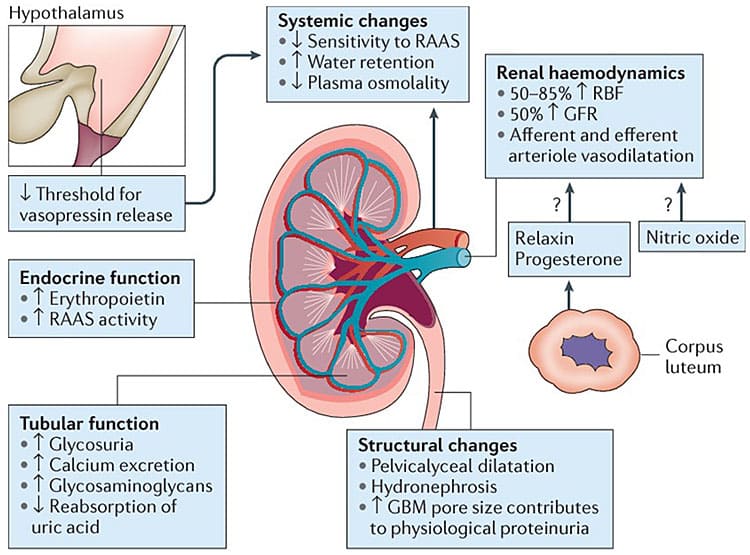
Haemodynamics GFR & Diuretics Systems Physiology: Kidneys, Filtration, GFR & Starling Forces RENAL PHYSIOLOGY Functional Anatomy of the Kidneys The urinary system is a vital organ system responsible for filtering blood, maintaining fluid and electrolyte balance, and excreting waste products. Components of the Urinary System Paired Kidneys: These are the primary organs, responsible for blood filtration and urine formation. A Ureter for Each Kidney: Muscular tubes that transport urine from the kidneys to the urinary bladder. Urinary Bladder: An expandable muscular sac that stores urine until it’s expelled from the body. Urethra: A tube that carries urine from the bladder to the outside of the body. Main Functions of the Urinary System Blood Filtration and Waste Excretion: Filter blood: They continuously process blood, removing unwanted substances. Dispose of nitrogenous wastes: These are toxic byproducts of protein metabolism. Urea: The most abundant nitrogenous waste, formed from ammonia in the liver. Uric acid: A byproduct of nucleic acid metabolism. Creatinine: A waste product from muscle metabolism (creatine phosphate breakdown). Remove other toxins: Including drugs, environmental toxins, and various metabolic byproducts. Eliminate excess water and ions: Maintaining appropriate body fluid volume and electrolyte concentrations. Regulation of Homeostasis: Regulate the balance of water and electrolytes: Essential for maintaining cell volume, nerve impulse transmission, and muscle contraction. Regulate acid-base balance: By excreting hydrogen ions and reabsorbing bicarbonate ions, the kidneys play a crucial role in maintaining blood pH. Endocrine Functions (Hormone Production): Erythropoietin (EPO): Stimulates red blood cell production in the bone marrow in response to hypoxia. Renin: An enzyme that initiates the Renin-Angiotensin-Aldosterone System (RAAS), which regulates blood pressure and fluid balance. Activation of Vitamin D: Converts inactive vitamin D into its active form (calcitriol), essential for calcium absorption and bone health. Gross Anatomy of the Kidneys Location: Retroperitoneal organs: This means they are located posterior to the parietal peritoneum, against the posterior abdominal wall. This is a key anatomical landmark. Superior lumbar region: Extending from the T12 to L3 vertebrae. The right kidney is often slightly lower than the left due to the presence of the liver. Shape and Orientation: Bean-shaped: With a characteristic convex lateral surface and a concave medial surface. Hilus (or Hilum): This is the prominent indentation on the medial surface. It serves as the entry and exit point for the renal artery, renal vein, nerves, and the ureter. Associated Structures: Adrenal glands (Suprarenal glands): These endocrine glands sit superior to each kidney, but are functionally separate from the kidneys. Internal Anatomy of the Kidney: Macroscopic Structure Upon dissection, the kidney reveals two main regions and further subdivisions: Renal Cortex (Outer Region): Lighter in color, granular texture. Renal Columns: Extensions of the cortex that project down into the medulla, dividing it into distinct pyramid-shaped sections. These columns contain blood vessels and parts of the nephrons. Renal Medulla (Inner Region): Darker, cone-shaped structures. Renal Pyramids (Medullary Pyramids): 8-18 cone-shaped masses, with their bases facing the cortex and their apices (renal papillae) pointing towards the renal pelvis. These contain parallel bundles of urine-collecting tubules and loops of Henle. Renal Papilla: The apex of each renal pyramid, from which urine drains into a minor calyx. Renal Lobe: Consists of a renal pyramid and the cortical tissue surrounding it (the renal column on either side and the cortical tissue overlying its base). Number: 5-11 lobes per kidney. Each lobe functions somewhat independently in urine production. Collecting System: Minor Calyx (plural: Calices): Cup-shaped structures that collect urine directly from the renal papillae of individual pyramids. Major Calyx: Two or three minor calices merge to form a major calyx. Renal Pelvis: The expanded, funnel-shaped superior part of the ureter. It is formed by the convergence of the major calices and acts as a reservoir for urine before it enters the ureter. Blood Supply to the Kidneys The kidneys receive a disproportionately large blood supply (about 20-25% of cardiac output) due to their role in blood filtration. Cortex receives >90%. Aorta: The abdominal aorta gives rise to the right and left renal arteries. Renal Artery: Enters the kidney at the hilus. Segmental Arteries: Within the hilus, the renal artery typically divides into 5 segmental arteries. Interlobar Arteries: Segmental arteries branch into interlobar arteries, which pass through the renal columns between the renal pyramids, extending towards the cortex. Arcuate Arteries: At the junction of the medulla and cortex (the corticomedullary junction), the interlobar arteries arch over the bases of the pyramids to become arcuate arteries. Cortical Radiate Arteries (Interlobular Arteries): Arcuate arteries give off numerous cortical radiate arteries that project into the cortex. Afferent Arterioles: Each cortical radiate artery gives rise to numerous afferent arterioles, which supply blood to individual glomeruli. The Unique Renal Vasculature Glomerular Capillary Bed Afferent Arteriole: Carries blood to the glomerulus. Larger in diameter, bringing blood to the glomerulus. Efferent Arteriole: Carries blood away from the glomerulus. Smaller in diameter, carrying blood away from the glomerulus. This is distinct from most capillary beds, which drain into venules. SIGNIFICANCE: The difference in diameter between the afferent and efferent arterioles creates resistance to blood flow, maintaining the high hydrostatic pressure within the glomerulus. This high pressure is the primary driving force for glomerular filtration, literally “forcing” filtrate out of the blood. Two Capillary Beds in Series This is a defining feature of the renal circulation: Glomerulus: The first capillary bed, specialized for filtration. Peritubular Capillaries (or Vasa Recta): The second capillary bed, arising from the efferent arteriole, specialized for reabsorption and secretion. A. Peritubular Capillaries Origin: Arise from the efferent arterioles. Location: Primarily surround the PCT and DCT in the renal cortex. Structure: Low-pressure, porous capillaries. Function: Specialized for reabsorption, readily taking up water, solutes, and nutrients that are reabsorbed by the tubule cells. They also play a role in secretion. B. Vasa Recta Specific Portion of Peritubular Capillary System. Long, straight capillaries that extend deep into the medulla, running parallel to the loops of Henle of juxtamedullary nephrons. They are crucial for maintaining the medullary osmotic gradient. Function: The Vasa Recta acts as a

LOWER RESPIRATORY TRACT 1
Anatomy

Lower Respiratory Anatomy

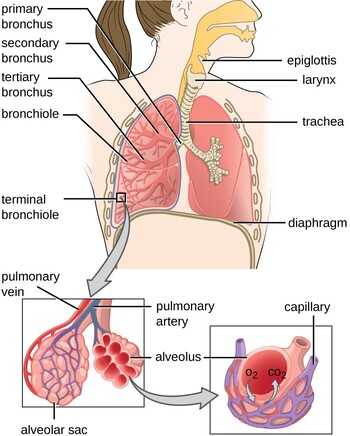
Lower Respiratory Anatomy Systems Anatomy: Lower Respiratory Tract Lower Respiratory Tract Overview The lower respiratory tract is responsible for conducting air deep into the lungs and for the vital process of gas exchange. It begins immediately inferior to the larynx. Components: It consists of the trachea, the main bronchi (primary, secondary, tertiary), progressively smaller bronchioles, and ultimately the microscopic alveolar sacs (which contain alveoli). Functional Unit: The lungs are the primary organs of respiration, formed by the branching bronchial tree culminating in the respiratory bronchioles, alveolar ducts, and alveolar sacs, all encased within pleural membranes. The statement “Bronchioles and alveolar sacs collectively form lungs” is an oversimplification; the lungs also include the larger bronchi, blood vessels, nerves, lymphatic tissue, and connective tissue. Functions: Air Conduction: Transporting inhaled air from the upper respiratory tract to the alveoli, and exhaled air in the opposite direction. Respiration (Gas Exchange): Facilitating the exchange of oxygen and carbon dioxide between the air in the alveoli and the blood in the pulmonary capillaries. Trachea The trachea, or windpipe, is a crucial component of the lower respiratory tract, providing a patent pathway for air to and from the lungs. Structure: It is a mobile, flexible fibrocartilaginous and membranous tube. Origin: It begins in the neck as a direct continuation of the larynx, specifically at the inferior border of the cricoid cartilage, typically at the level of the C6 vertebra. Course: It descends anterior to the esophagus, initially in the midline of the neck, and then slightly deviates in the thorax. Termination: The trachea terminates in the thorax by bifurcating into the right and left main (principal) bronchi. This bifurcation point is known as the carina. Anatomical Landmark: The carina is located approximately at the level of the sternal angle anteriorly, and between the T4 and T5 vertebral bodies posteriorly. Structure of the Trachea The unique structure of the trachea is adapted for its function of maintaining an open airway while allowing some flexibility. Cartilaginous Support: The trachea is supported by 16-20 C-shaped (incomplete) cartilaginous rings, primarily composed of hyaline cartilage. These rings are crucial for keeping the tracheal lumen continuously patent, preventing collapse during inspiration or changes in neck position. Posterior Deficiency: The tracheal rings are deficient posteriorly. This allows the trachea to flatten slightly against the esophagus during swallowing, facilitating the passage of food. Trachealis Muscle: The posterior, open ends of the C-shaped cartilages are connected by the trachealis muscle, a band of smooth muscle. Function: Contraction of the trachealis muscle can narrow the tracheal lumen, which is important during coughing to increase the velocity of air expulsion, aiding in clearing mucus and foreign material. Shape of Lumen: Due to the posterior trachealis muscle, the trachea’s lumen is not perfectly circular but rather slightly D-shaped or flattened posteriorly. The statement “the posterior wall of the trachea is flat” accurately describes this. Dimensions: Adults: The average diameter of the trachea in adults is about 2.5 cm (1 inch). The length is typically 10-12 cm. Infants: In infants, the tracheal diameter is much smaller, roughly equivalent to the diameter of a pencil (or the child’s little finger), making them more susceptible to airway obstruction. Histology of the Trachea The tracheal wall is composed of several layers, each contributing to its function: Mucosa: Epithelium: Lined by pseudostratified ciliated columnar epithelium with abundant goblet cells. This is characteristic respiratory epithelium. Cilia: Beat synchronously to propel mucus and trapped particles upwards, towards the pharynx. Goblet Cells: Produce mucus, which traps inhaled dust, pollen, and microorganisms. Lamina Propria: A layer of loose connective tissue rich in elastic fibers, lymphoid cells, and mucous glands. Submucosa: Contains seromucous glands (tubular mucous glands in the original description) that supplement the mucus produced by goblet cells, along with blood vessels and nerves. Cartilaginous Layer: Composed of the C-shaped hyaline cartilage rings. Adventitia: The outermost layer of connective tissue, blending with surrounding tissues. Function: The mucociliary escalator system (ciliated epithelium + mucus) is a critical defense mechanism, continuously trapping and moving inhaled foreign particles and pathogens out of the lower respiratory tract, preventing them from reaching the delicate alveoli. Relations of the Trachea Understanding the anatomical relations of the trachea is vital, especially in surgical procedures involving the neck and mediastinum. A. Cervical Trachea (in the Neck) Anteriorly: Skin, superficial fascia, deep cervical fascia (investing layer). Infrahyoid Muscles: Sternohyoid and sternothyroid muscles. Thyroid Gland Isthmus: Typically lies anterior to the 2nd, 3rd, and 4th tracheal rings. Vascular Structures: Inferior thyroid veins (form a plexus), jugular venous arch, and sometimes the thyroidea ima artery (an anomalous artery arising from the brachiocephalic trunk or aorta). In Children: The left brachiocephalic vein (innominate vein) is higher and may be more anteriorly related to the trachea. Posteriorly: Esophagus: The trachea is always anterior to the esophagus. Recurrent Laryngeal Nerves: These nerves ascend in the tracheoesophageal grooves on either side. Laterally: Thyroid Gland Lobes: The lateral lobes of the thyroid gland lie on either side of the trachea. Carotid Sheath Contents: Common carotid artery, internal jugular vein, and vagus nerve are located lateral to the trachea, within their respective carotid sheaths. B. Thoracic Trachea (in the Thorax) Anteriorly: Manubrium of Sternum. Thymus: In children, the thymus gland is prominent. Major Vessels: Arch of aorta (initially to the left, then over the trachea), brachiocephalic trunk, left common carotid artery, left subclavian artery, left brachiocephalic vein. Posteriorly: Esophagus: Continues its posterior relation. Right Side: Right vagus nerve, azygos vein, right pleura. Left Side: Arch of aorta, left common carotid artery, left subclavian artery, left vagus nerve, left recurrent laryngeal nerve, left pleura. Neurovascular Supply & Lymph Drainage of the Trachea A. Nerve Supply Sensory Innervation: Primarily supplied by branches of the vagus nerves (CN X) and the recurrent laryngeal nerves. These nerves convey sensory information (e.g., irritation, cough reflex) from the tracheal mucosa. Autonomic Innervation: Parasympathetic (Vagus/Recurrent Laryngeal): Stimulates tracheal gland secretion and smooth muscle contraction (trachealis muscle). Sympathetic (Sympathetic Trunks): Causes bronchodilation and inhibits glandular secretion (less significant in trachea than bronchioles).

Respiratory System
Anatomy

Upper Respiratory Anatomy

Upper Respiratory Anatomy Systems Anatomy: Respiratory Tract UNIT: SYSTEMS ANATOMY Respiratory Tract The respiratory tract is the pathway for air, comprising structures that transport, filter, warm, and humidify air for gas exchange in the lungs. It is divided into the upper (nose, nasal cavity, pharynx, larynx) and lower (trachea, bronchi, bronchioles, alveoli) tracts. Key functions include oxygenating blood and removing carbon dioxide. The respiratory system is functionally and anatomically divided into two main parts: Upper Respiratory Tract (URT) Extends from the external nares (nostrils) to the larynx (voice box). Includes the nose (external nose and nasal cavity), pharynx (throat), and larynx. Primary Functions: Air Conditioning: Crucial for cleaning, warming, and humidifying inhaled air before it reaches the delicate lower airways and lungs. Olfaction (Smell): Specialized receptors in the nasal cavity detect odors. Resonance for Speech: The nasal cavity and paranasal sinuses act as resonating chambers for the voice. Protection: Filters out airborne particles and pathogens. Aesthetics: The external nose significantly contributes to facial appearance. Weight Reduction of Skull: The air-filled paranasal sinuses lighten the skull. Lower Respiratory Tract (LRT) Extends from the trachea (windpipe) down to the alveoli (air sacs) within the lungs. Includes the trachea, bronchi, bronchioles, and lungs (which contain respiratory bronchioles, alveolar ducts, and alveoli). Primary Functions: Air Conduction: Structures like the trachea and bronchi act as passageways for air. Gas Exchange (Respiration): The respiratory bronchioles and, most importantly, the alveoli are the primary sites where oxygen enters the blood and carbon dioxide leaves it. Some classifications might place the larynx, its lower part (below the vocal cords) as part of the LRT from a functional airway perspective. However, anatomically, it’s consistently taught as the lowest structure of the URT. Upper Respiratory Tract The upper respiratory tract (URT) comprises the nose, nasal cavity, sinuses, pharynx, and larynx, acting as the primary entry point for air, which it filters, warms, and humidifies. The Nose The nose is the most prominent anterior structure of the face, serving multiple vital roles. Functions of the Nose: Olfaction (Smell): Houses olfactory receptors. Respiration: Provides the primary entry point for air into the respiratory system. Air Conditioning: Cleans, warms, and humidifies inspired air. Voice Resonance: Contributes to the timbre of the voice. Aesthetics: A key determinant of facial appearance. Divisions: The nose is divided into the external nose and the nasal cavity. External Nose This is the visible part of the nose, projecting from the face. Its shape and size vary significantly among individuals due to genetics, sex, and ethnicity. Key Features: Root: The superior attachment of the nose to the forehead. Bridge: The superior, bony part of the nose. Dorsum Nasi: The anterior border from the root to the apex. Apex (Tip): The free, rounded end of the nose. Nares (Nostrils): The two external openings of the nasal cavity, separated by the nasal septum. Alae Nasi: The flared, cartilaginous expansions that form the lateral boundaries of the nares. Framework of the External Nose The external nose is supported by a combination of bone and hyaline cartilage. Bony Framework (Superior Part – “Bridge”): Nasal Bones (paired): Form the superior part of the bridge. Frontal Processes of Maxillae (paired): Extend upwards along the sides of the nasal bones. Nasal Part of Frontal Bone: Forms the root of the nose. Cartilaginous Framework (Inferior Part – “Apex and Alae”): These are plates of hyaline cartilage that provide flexibility and shape. Septal Nasal Cartilage: Forms the anterior part of the nasal septum, extending from the perpendicular plate of the ethmoid bone and vomer, maintaining the midline structure. Lateral Nasal Cartilages (paired): Located superior to the major alar cartilages, contributing to the side walls of the nose. Major Alar Cartilages (paired): Form the apex and alae of the nose. Each has: Medial Crus: Forms part of the mobile nasal septum. Lateral Crus: Forms the ala of the nose. Minor Alar Cartilages (variable): Small, accessory cartilages within the alae. Alar Fibrofatty Tissue: Connective tissue and fat that contribute to the shape and flexibility of the alae, especially in the most inferior part. Summary of Support: Bones: Support the upper one-third (bridge). Upper Cartilages (Lateral Nasal): Support the sides of the mid-nose. Lower Cartilages (Major Alar): Primarily support the tip and help define the shape and patency of the nostrils. Skin and connective tissue: Also contribute to the overall shape and covering. Nasal Cavity The nasal cavity is the internal space within the external nose, extending posterior to the pharynx. Boundaries: Anteriorly: Communicates with the exterior via the nares (nostrils). Posteriorly: Opens into the nasopharynx via the choanae (posterior nasal apertures). Walls of the Nasal Cavity: Floor: Formed primarily by the hard palate (maxilla and palatine bones) and, to a lesser extent, the anterior part of the soft palate. This separates the nasal cavity from the oral cavity. Roof: Narrow and arched, composed of several bones: Nasal Bone: Anteriorly. Frontal Bone: Anteriorly, between the nasal bones and ethmoid. Cribriform Plate of Ethmoid Bone: Mid-portion, perforated by olfactory nerve filaments. This is a critical anatomical landmark as it is thin and can be damaged. Body of Sphenoid Bone: Posteriorly. Medial Wall (Nasal Septum): Divides the nasal cavity into right and left halves. It has both bony and cartilaginous components: Bony Parts: Perpendicular Plate of Ethmoid Bone: Forms the superior posterior part. Vomer: Forms the inferior posterior part. Cartilaginous Part: Septal Nasal Cartilage: Forms the anterior superior part, making up a significant portion of the septum. (Add: “Vomeronasal cartilage” is often a historical or minor finding; focus on the main three components for clarity.) Lateral Wall: Complex and irregular, characterized by three shelf-like bony projections: Superior Nasal Concha (Turbinate): Part of the ethmoid bone. Middle Nasal Concha (Turbinate): Part of the ethmoid bone. Inferior Nasal Concha (Turbinate): A separate bone, not part of the ethmoid. These conchae increase the surface area of the nasal cavity and create turbulent airflow, facilitating air conditioning. Nasal Meatus (Air Passages): These are the spaces inferior to each concha. Spheno-ethmoidal Recess: Location: A small area located

Scroll to Top