
Beta-Lactam Antibiotics: Penicillins, Cephalosporins and Carbapenems
On this page
Overview
Mechanism of action
All beta-lactams share a four-membered beta-lactam ring whose shape mimics the D-alanyl-D-alanine terminus of the peptidoglycan building block. The drug binds penicillin-binding proteins (PBPs) — the transpeptidases that cross-link peptidoglycan — irreversibly blocking cell-wall synthesis. Water then enters the weakened cell and the bacterium lyses (autolysins assist). Because human cells have no peptidoglycan, toxicity is remarkably low.
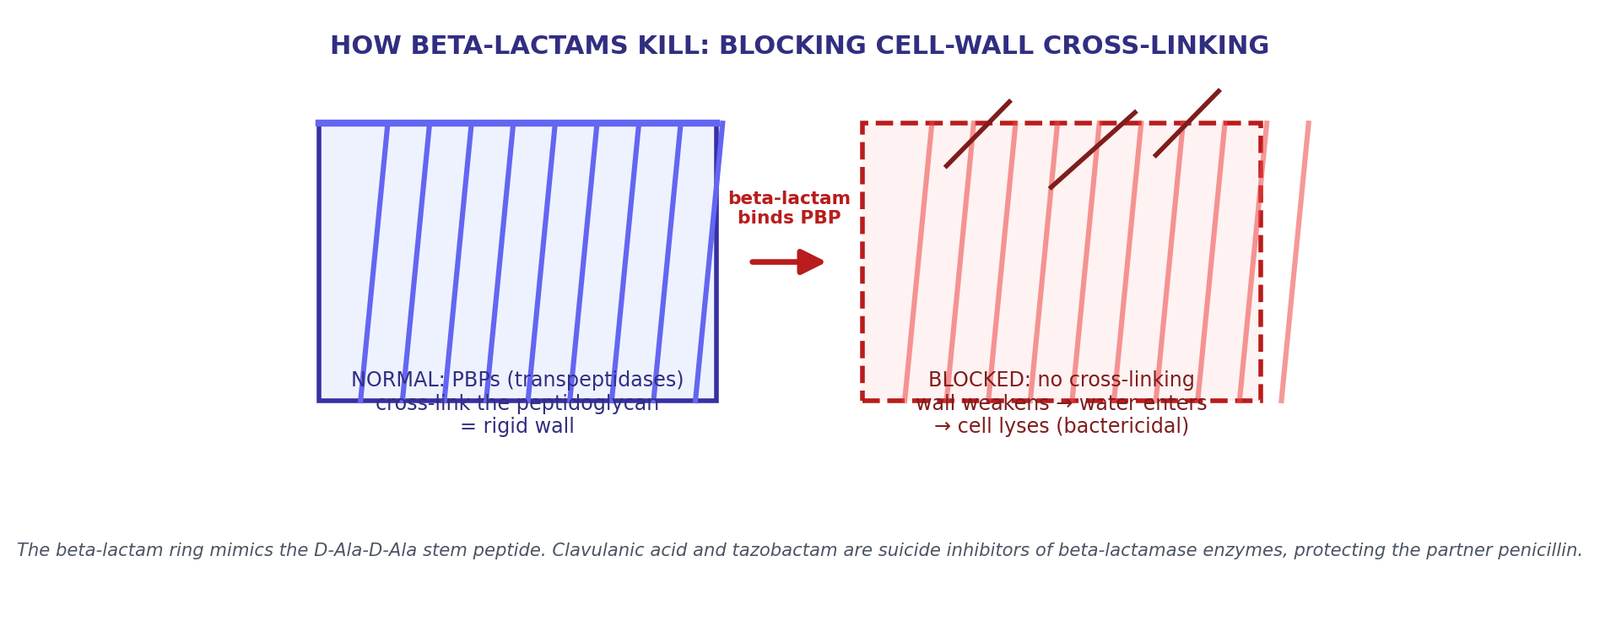
- Bactericidal, time-dependent: killing correlates with the time free drug concentration stays above the MIC (T>MIC) — hence frequent dosing or continuous infusion in severe infection, not bigger single doses.
- Selective toxicity rests on the bacterial wall: no wall, no target (sterile-site synergy, e.g. with gentamicin, is explained in the aminoglycoside post).
- Resistance: beta-lactamase enzymes hydrolyse the ring (blocked by clavulanic acid, sulbactam, tazobactam); altered PBPs (MRSA's PBP2a, resistant pneumococcus); porin loss and efflux.
The penicillins in detail
Classify penicillins by their spectrum and penicillinase stability. The master table below gives adult and paediatric dosing, indications, adverse effects, contraindications and counselling — doses follow the Uganda Clinical Guidelines and standard formularies; always confirm against the current UCG and EMHSLU.
Scroll the table sideways on a smaller screen.
| Drug (class) | Adult dose (usual) | Paediatric dose | Main indications | Mechanism / spectrum | Side & adverse effects | Contraindications & cautions | Counselling points |
|---|---|---|---|---|---|---|---|
| Benzylpenicillin (penicillin G) — natural | Meningitis: 3–4 MU IV/IM every 4 h (UCG). Severe streptococcal infection: 2.4 MU q4–6h | 100,000–150,000 units/kg/day divided q4–6h; neonatal sepsis 50,000 units/kg q12h (day 1–7) | Meningococcal and pneumococcal meningitis (with chloramphenicol or ceftriaxone per UCG), syphilis (alternative to benzathine), gas gangrene, tetanus, actinomycosis, severe streptococcal sepsis | Binds PBPs; narrow spectrum — streptococci, meningococci, Treponema, anaerobes (mouth); not stable to penicillinase | Hypersensitivity (urticaria → anaphylaxis, serum sickness, haemolytic anaemia); pain at IM site; high-dose CNS toxicity (seizures), electrolyte load (K⁺) | Penicillin allergy; give test dose where facilities allow; renal dose adjustment in severe impairment | Complete the full course even when fever resolves in 48 h; report rash, wheeze or swelling immediately |
| Phenoxymethylpenicillin (penicillin V) — natural, oral | 250–500 mg 6-hourly | 6.25–12.5 mg/kg 6-hourly | Streptococcal pharyngitis (first choice per UCG), mild streptococcal skin infection, rheumatic-fever treatment course | Oral, acid-stable penicillin G; same narrow spectrum; not penicillinase-stable | GI upset, rash, oral/vaginal candidiasis | Penicillin allergy; take on an empty stomach for absorption | Space doses around meals; complete 10 days for pharyngitis to prevent rheumatic fever |
| Procaine penicillin — depot natural | Syphilis early: 1.2 MU IM daily ×10–14 days (per UCG); neonatal congenital syphilis (aqueous preferred) | Per weight, IM depot; painful injection | Early syphilis where benzathine unavailable; neonatal syphilis regimens per UCG | Slow-release benzylpenicillin; narrow spectrum | Injection-site pain, sterile abscess; inadvertent IV → anxiety, hallucination, seizures (procaine reaction) | Never give IV; penicillin allergy | Deep IM injection; warm the site; report faintness or confusion during administration |
| Benzathine penicillin — long-acting depot | Early syphilis: 2.4 MU IM single dose. Late latent/tertiary (non-neurosyphilis): 2.4 MU IM weekly ×3. Rheumatic-fever prophylaxis: 1.2 MU IM every 3–4 weeks | Rheumatic-fever prophylaxis: <30 kg → 600,000 units IM every 3–4 weeks. Syphilis (child): 50,000 units/kg IM single dose (max 2.4 MU) | Syphilis (first line per UCG), secondary prophylaxis after acute rheumatic fever/rheumatic heart disease, yaws, streptococcal skin infection outbreaks | Very slow absorption → prolonged low levels; bactericidal only at high continuous levels — never for meningitis or endocarditis | Severe injection pain, sterile abscess; Jarisch–Herxheimer reaction in syphilis (fever, headache, transient worsening within 24 h — self-limiting, counsel the patient) | Penicillin allergy; never IV; not for CNS infection | Expect sore injection site 1–2 days; fever the night after a syphilis dose is common and passes; keep every monthly prophylaxis appointment |
| Cloxacillin / flucloxacillin — penicillinase-resistant | 500 mg 6-hourly oral; severe: 1–2 g IV q4–6h | 25–50 mg/kg/day divided q6h (max 2 g/day oral) | MSSA skin and soft-tissue infection, boils/abscesses, impetigo, staphylococcal osteomyelitis (IV), surgical wound infection | Isoxazolyl penicillin: bulky side chain blocks staphylococcal penicillinase; narrow, Gram-positive only (no activity vs MRSA) | GI upset, rash, candidiasis; cholestatic jaundice with flucloxacillin (>2 weeks); neutropenia on prolonged IV | Penicillin allergy; hepatic impairment (flucloxacillin jaundice) | Take 1 h before food; report dark urine or itching (jaundice) on long courses |
| Amoxicillin — broad-spectrum aminopenicillin | 500 mg 8-hourly (respiratory 1 g 8-hourly in severe); dental 500 mg 8-hourly; typhoid (sensitive) 500–750 mg 8-hourly | 20–40 mg/kg/day divided q8h; otitis media/high-dose regimens up to 80–90 mg/kg/day divided q12h | First choice (Access, AWaRe/UCG): community pneumonia, otitis media, sinusitis, pharyngitis (alternative), UTI, enteric fever if sensitive, Helicobacter pylori (combination), dental abscess | Broader Gram-negative cover (Haemophilus, E. coli, Salmonella) via enhanced cell-wall penetration; destroyed by beta-lactamase unless combined with clavulanate | GI upset, diarrhoea, rash; non-blanching rash with glandular fever/infective endocarditis (not true allergy); rare anaphylaxis | Penicillin allergy; infectious mononucleosis (rash); renal dose adjustment | With or without food; complete course; rash — stop and seek review; space from oral typhoid vaccine |
| Ampicillin — aminopenicillin IV | 1–2 g IV q4–6h | Neonatal sepsis: 50–100 mg/kg/day divided q12h (q8h after day 7); child 100–200 mg/kg/day divided q6h | Neonatal sepsis (with gentamicin), listeriosis, enterococcal endocarditis (with gentamicin), severe community pneumonia (step-down) | Same class as amoxicillin but IV; slightly better enterococcal cover | Rash (mono), GI upset, candidiasis, phlebitis | Penicillin allergy; EBV infection | Hospital use; report any rash |
| Co-amoxiclav (amoxicillin + clavulanic acid) — beta-lactamase inhibitor combination | 625 mg (500/125) 8-hourly; severe: 1.2 g IV q8h | 25/3.1 mg/kg/dose 8-hourly (dose by amoxicillin component) | Animal and human bites, infected wounds, otitis media/sinusitis failing first line, diabetic foot infection, aspiration pneumonia, intra-abdominal infection (combination) | Clavulanate suicide-inhibits beta-lactamases, restoring amoxicillin's spectrum (staphylococci, H. influenzae, E. coli, Klebsiella) | Diarrhoea (common), nausea, rash, candidiasis; cholestatic jaundice (long/ repeated courses), hepatic dysfunction | Penicillin allergy; previous co-amoxiclav cholestatic jaundice; hepatic impairment | Take at start of meal; diarrhoea usually mild — seek help if severe or bloody |
Special benzathine and benzylpenicillin regimens
Two regimens recur in exams and clinic and must be learned as protocols:
Syphilis (per Uganda Clinical Guidelines)
- Early syphilis (primary, secondary, early latent): benzathine penicillin 2.4 MU IM single dose. Doxycycline 100 mg twice daily ×14 days if penicillin-allergic (excluding pregnancy).
- Late latent or tertiary (non-neurosyphilis): benzathine penicillin 2.4 MU IM weekly ×3 doses.
- Neurosyphilis: aqueous benzylpenicillin IV (or procaine penicillin IM with probenecid) — benzathine does not reach CSF.
- Warn about the Jarisch–Herxheimer reaction: fever, headache and transient flare of lesions within 24 h of the first dose — self-limiting, managed with paracetamol and fluids.
Rheumatic fever secondary prophylaxis
- Benzathine penicillin IM every 3–4 weeks (commonly monthly) until age 25–35 or 10 years after the last attack: <30 kg → 600,000 units; ≥30 kg → 1.2 million units per MSF/standard protocols.
- Adherence, not drug failure, is the usual cause of recurrent rheumatic carditis — every missed month raises recurrence risk.
Meningitis (per UCG)
- Empiric bacterial meningitis in Uganda: ceftriaxone 2 g IV/IM 12-hourly (child 100 mg/kg/day divided 12-hourly), or benzylpenicillin 3–4 MU IV 4-hourly plus chloramphenicol 1 g 6-hourly where ceftriaxone is unavailable; add doxycycline where tick-borne relapsing fever is suspected.
Cephalosporins by generation
Cephalosporins share the beta-lactam mechanism but carry a dihydrothiazine ring that confers beta-lactamase stability, increasing with generation — at the price of a shifting (not simply widening) spectrum and poor activity against enterococci and Listeria. They are Watch agents from the second generation upward.
Scroll the table sideways on a smaller screen.
| Generation | Agents | Typical dose | Spectrum / indications | Notes |
|---|---|---|---|---|
| First (Access) | Cefalexin (oral); cefazolin (IV) | Cefalexin 500 mg 8–12-hourly; cefazolin 1–2 g IV q8h, or single dose pre-op | Gram-positive cocci (staph, strep) and some E. coli: skin/soft tissue, UTI, surgical prophylaxis (cefazolin) | Safe in most penicillin allergy (see below); no MRSA, no enterococci |
| Second (Watch) | Cefuroxime (oral/IV) | 250–500 mg 12-hourly oral | Adds Haemophilus, Moraxella, some anaerobes: sinusitis, otitis media, community pneumonia, Lyme disease | Oral step-down after ceftriaxone |
| Third (Watch) | Ceftriaxone, cefotaxime, ceftazidime | Ceftriaxone 1–2 g IV/IM once daily (child 50–75 mg/kg/day); meningitis 2 g 12-hourly (child 100 mg/kg/day). Gonorrhoea: ceftriaxone 500 mg IM single dose (1 g if ≥150 kg) | Strong Gram-negative (enteric fever, pyelonephritis, Gram-negative sepsis) plus pneumococcus and meningococcus — empiric meningitis; ceftazidime for Pseudomonas | Crosses inflamed meninges; ceftriaxone — biliary sludging, avoid with calcium-containing IV lines in neonates; ESBL-producing organisms are resistant |
| Fourth / Fifth | Cefepime; ceftaroline | Per specialist protocol | Cefepime: extended Gram-negative including Pseudomonas; ceftaroline: MRSA pneumonia/skin infection | Specialist/tertiary use; Reserve-adjacent stewardship |
Carbapenems and other beta-lactams
- Meropenem / imipenem (Reserve agents): the broadest beta-lactams — stable to most beta-lactamases including ESBLs; reserved for confirmed ESBL infection, febrile neutropenia and polymicrobial sepsis per stewardship protocols. Dose: meropenem 1 g IV 8-hourly (child 20 mg/kg/dose q8h). Adverse: seizures (imipenem > meropenem), GI upset, rash. Interaction: markedly lowers valproate levels — an under-recognised cause of breakthrough seizures; probenecid raises meropenem levels.
- Aztreonam (monobactam): Gram-negative only (including Pseudomonas); safe in penicillin anaphylaxis (no cross-reactivity). Specialist use.
- Beta-lactamase inhibitors: clavulanic acid, sulbactam, tazobactam — no antibacterial effect alone; combined with amoxicillin, ampicillin or piperacillin to extend spectrum.
Penicillin allergy and cross-reactivity
True IgE-mediated penicillin allergy (urticaria, wheeze, anaphylaxis) affects about 1–10% of patients; the often-quoted 10% cross-reactivity with cephalosporins is historical and overstated — modern data put it at ~2%, driven largely by shared side chains, not the core ring:
- Cephalosporins with side chains different from the culprit penicillin (e.g., ceftriaxone, cefalexin) can usually be given with monitoring; those with similar chains carry more risk.
- Carbapenem cross-reactivity is very low (<1%).
- Ampicillin/amoxicillin rash of infectious mononucleosis or EBV infection is not an allergy — avoid labelling for life.
- Document what happened (hives vs. vague "reaction"); in low-risk histories a graded challenge or penicillin allergy testing can de-label patients — important because "penicillin allergy" pushes prescribers toward broader, costlier, more resistance-prone agents.
Important interactions and counselling
Scroll the table sideways on a smaller screen.
| Interacting drug | Effect | Action |
|---|---|---|
| Methotrexate | Penicillins reduce renal clearance → methotrexate toxicity (mucositis, marrow suppression) | Avoid or monitor levels/toxicity closely |
| Warfarin | Antibiotic-induced gut flora change and diarrhoea destabilise INR (up or down) | Check INR more frequently during and after course |
| Probenecid | Blocks tubular secretion → higher, prolonged penicillin/cephalosporin levels (used therapeutically in some syphilis regimens) | Usually deliberate; avoid accidental combination |
| Oral contraceptives | Vomiting/diarrhoea from any antibiotic can reduce absorption | If severe GI upset, use extra precautions during illness |
| Calcium-containing IV solutions (neonatal) | Ceftriaxone–calcium precipitation | Never co-infuse in neonates |
| Aminoglycosides (penicillins in same syringe) | Chemical inactivation of both drugs | Give through separate lines; the combination is excellent in synergy (see aminoglycoside post) |
Clinical scenarios
Scenario 1 — Empiric meningitis at the regional referral hospital
A 23-year-old presents with fever, severe headache, neck stiffness and a purpuric rash, 6 hours of symptoms. You start ceftriaxone 2 g IV immediately (do not delay for lumbar puncture if the patient is shocked or the CT is delayed), take blood cultures, and admit. Ceftriaxone crosses the inflamed meninges, covers meningococcus and pneumococcus, and is given 12-hourly for meningitis doses. A history of childhood penicillin "rash" would not stop ceftriaxone in life-threatening infection — but true anaphylaxis would prompt chloramphenicol plus vancomycin per protocol.
Scenario 2 — Syphilis at the STI clinic
A 29-year-old has a painless genital ulcer and inguinal lymphadenopathy; RPR positive, confirmed by treponemal test. You give benzathine penicillin 2.4 MU IM as a single dose, explain the Jarisch–Herxheimer reaction (fever and headache tonight, settling by 24 h), treat the asymptomatic partner after testing, and document allergy status. Why not oral amoxicillin? Because benzathine's depot achieves the sustained treponemicidal levels that short-course oral therapy cannot reliably deliver, and directly observed single-dose treatment guarantees adherence.
Scenario 3 — The "penicillin-allergic" patient who needs a cephalosporin
A 60-year-old with a hip prosthesis needs revision surgery; the card says "penicillin allergy (childhood rash)". Cefazolin prophylaxis is standard. You clarify: a vague non-urticarial childhood rash is low risk; modern cross-reactivity with a first-generation cephalosporin is about 2% and the benefit of prophylaxis in prosthetic joint surgery is large. You give a test dose, observe, and proceed — and you correct the record to "low-risk childhood rash; first-generation cephalosporin tolerated", de-labelling the patient for life.
Key points
References
- WHO AWaRe Antibiotic Book, 2022/2023 — first-choice penicillin regimens by syndrome (Library reference.)
- Uganda Clinical Guidelines 2023: meningitis, STI/syphilis and pneumonia chapters (Library reference.)
- Uganda Essential Medicines and Health Supplies List 2023 (Library reference.)
- Katzung's Basic & Clinical Pharmacology — penicillins and cephalosporins chapters (Library reference.)
- Goodman & Gilman's The Pharmacological Basis of Therapeutics (Library reference.)
- MSF Clinical Guidelines: benzathine penicillin dosing for rheumatic-fever prophylaxis and syphilis (Library reference.)
Further reading
For deeper study, compare this lesson with current guidance and standard references from recognised medical and pharmaceutical organisations.
- WHO: The AWaRe Antibiotic Book
- Uganda MoH Knowledge Management Portal (UCG 2023 & EMHSLU 2023)
- WHO Model List of Essential Medicines 2023
- DCM Year One Semester Two curriculum
For education only. Doses change with guideline updates — always verify against the current Uganda Clinical Guidelines, the EMHSLU 2023 and your facility formulary before prescribing.