
Aminoglycosides, Sulphonamides and Trimethoprim
On this page
Overview
Aminoglycosides in detail
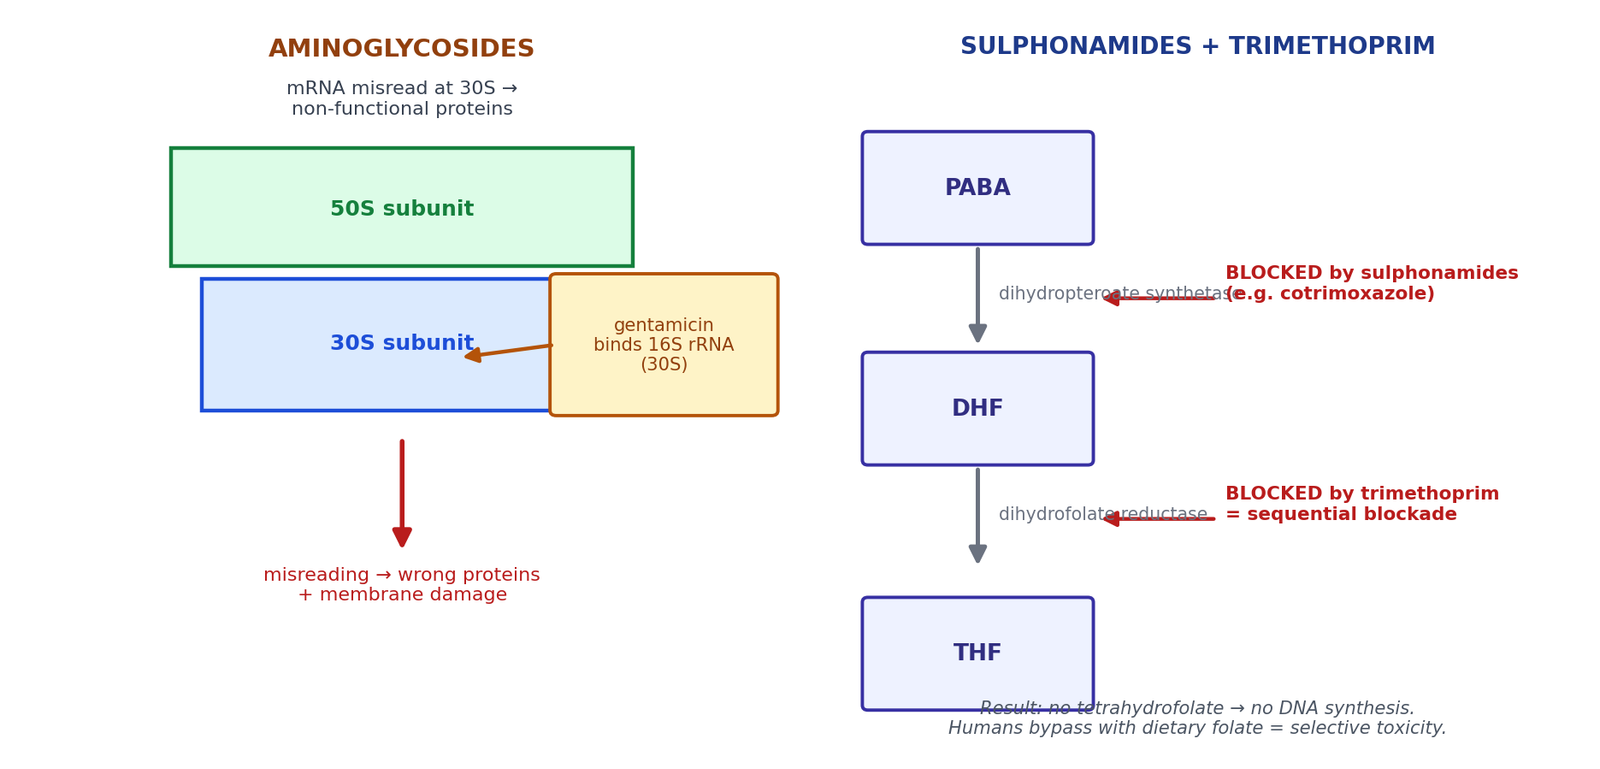
Aminoglycosides bind the 30S ribosomal subunit, misreading mRNA and inserting wrong amino acids into the growing peptide — bactericidal concentration-dependent killing with a marked post-antibiotic effect. They are polar molecules with poor oral absorption (given IV/IM, except for bowel decontamination), negligible CSF penetration, and no activity against anaerobes (they need oxygen-dependent uptake into the bacterial cell).
Scroll the table sideways on a smaller screen.
| Drug | Adult dose (usual) | Paediatric dose | Main indications | Side & adverse effects | Contraindications & cautions | Counselling / monitoring |
|---|---|---|---|---|---|---|
| Gentamicin (Access) | Once-daily dosing: 5–7 mg/kg IV/IM daily (per local protocol); traditional dosing 80 mg q8h adjusted to levels | Neonatal sepsis: 3–5 mg/kg once daily (age/weight bands per protocol); child: 5–7 mg/kg once daily | Empiric Gram-negative sepsis, neonatal sepsis (with ampicillin/benzylpenicillin), pyelonephritis, endocarditis synergy (with beta-lactam), pelvic inflammatory disease | Nephrotoxicity (non-oliguric AKI, usually reversible), ototoxicity (vestibular > cochlear — imbalance, tinnitus, high-tone deafness, often irreversible), neuromuscular blockade at high dose | Pregnancy (fetal VIIIth-nerve damage — use only if life-threatening), myasthenia gravis (worsens block), renal impairment (level-guided dosing), avoid with loop diuretics and other nephro/ototoxins | Report dizziness, ringing or hearing change immediately; ensure hydration; levels taken around the dose; ototoxicity can be permanent |
| Amikacin (Access) | 15 mg/kg once daily IV/IM; max 1.5 g/day | 15 mg/kg once daily | Severe Gram-negative infection resistant to gentamicin (many gentamicin-resistant organisms remain amikacin-sensitive), multidrug-resistant TB (injectable second-line, specialist), nocardiosis | Same class profile; somewhat lower resistance rates; ototoxicity especially after prolonged use | As gentamicin | Levels mandatory; audiometry on prolonged courses |
| Streptomycin | TB (combination): 15 mg/kg IM once daily, max 1 g; brucellosis/plague/tularemia regimens per protocol | TB: 15 mg/kg IM once daily | Second-line injectable anti-TB drug (with isoniazid/rifampicin in retreatment per national TB guidelines), brucellosis (combination), plague | Vestibular toxicity (dose/duration-related), nephrotoxicity, injection-site pain | Pregnancy; renal impairment; vestibular disease | Report unsteadiness early; IM injections are prolonged courses |
| Neomycin (topical/oral, not absorbed) | Hepatic encephalopathy gut decontamination: 1 g 6-hourly orally ×5–7 days; topical eye/skin per preparation | Not for systemic use in children except specialist gut decontamination | Oral/topical only — pre-operative bowel preparation, hepatic encephalopathy adjunct, superficial infection | Oral: diarrhoea, C. difficile; prolonged gut use can still cause deafness in renal impairment (absorbed fraction) | Never systemic IV/IM (systemic nephro/ototoxicity); renal impairment; bowel obstruction | Oral course is short; report hearing change on long use |
Synergy — the classic combinations
- Aminoglycoside + beta-lactam is synergistic in endocarditis and Gram-negative sepsis: the beta-lactam opens the cell wall, improving aminoglycoside entry. (Never mix them in the same syringe — chemical inactivation.)
- Classic pairings: ampicillin/benzylpenicillin + gentamicin for enterococcal or neonatal sepsis; cloxacillin + gentamicin for staphylococcal endocarditis.
Nephro- and ototoxicity: monitoring
- Check renal function (creatinine, eGFR) before starting and every 2–3 days on therapy.
- Serum levels: for once-daily dosing, a random level ~6–14 h after the dose is compared with a nomogram, or trough before the next dose — follow your facility's protocol. Aim for a high peak and an undetectable trough.
- Clinical surveillance: daily ask about tinnitus, fullness, balance; bedside testing of hearing (whisper/finger-rub) on prolonged courses.
- Neuromuscular blockade: aminoglycosides potentiate blockers — caution in myasthenia gravis and around surgery/ventilation.
Sulphonamides, trimethoprim and cotrimoxazole
The sulphonamides (synthetic, not true antibiotics) are p-aminobenzoic acid (PABA) analogues that competitively inhibit dihydropteroate synthetase, blocking folate synthesis; trimethoprim inhibits the next enzyme, dihydrofolate reductase (DHFR). Humans obtain folate from food, so the block is selectively toxic. Alone, each drug is bacteriostatic; combined as cotrimoxazole (co-trimoxazole) in the classic 5:1 ratio (sulphamethoxazole 400 mg + trimethoprim 80 mg per tablet) they become bactericidal — sequential blockade of one pathway, the same logic as multi-drug TB therapy.
Scroll the table sideways on a smaller screen.
| Drug | Adult dose (usual) | Paediatric dose | Main indications | Side & adverse effects | Contraindications & cautions | Counselling |
|---|---|---|---|---|---|---|
| Cotrimoxazole (co-trimoxazole) (Access) | UTI: 960 mg 12-hourly ×3 days. Dysentery: 960 mg 12-hourly ×5 days. Pneumocystis (PCP): high-dose 120 mg/kg/day in 3–4 divided doses ×21 days. HIV prophylaxis: 960 mg daily or 3×/week | 6–12 mg TMP/kg/day divided 12-hourly (per indication); PCP 15–20 mg TMP/kg/day | UTI and dysentery, PCP treatment and prophylaxis, HIV/OI prophylaxis (with isoniazid per national guidelines), skin/soft-tissue infection, brucellosis/toxoplasmosis (combination) | Skin eruptions incl. SJS/TEN (most feared — any rash: stop the drug), nausea, marrow suppression (folate antagonism), hyperkalaemia (trimethoprim blocks renal ENaC like a potassium-sparing diuretic), photosensitivity, crystalluria | Sulphonamide allergy or prior SJS/TEN; pregnancy (teratogenic folate antagonism — avoid first trimester; give folate if essential); severe renal impairment; avoid in G6PD-deficiency crisis (haemolysis) and with methotrexate, warfarin, phenytoin, ACE inhibitors in renal impairment | Drink plenty of fluids; stop immediately for any rash, mouth ulcers or sore throat; expect mild nausea; report palpitations/weakness (high K⁺) on high-dose or renal disease |
| Trimethoprim alone | 200 mg 12-hourly ×3 days (uncomplicated UTI, per local resistance) | 2 mg/kg 12-hourly | Uncomplicated lower UTI where local E. coli resistance is low | Same profile but less severe; hyperkalaemia; marrow suppression (megaloblastic changes) | As above; renal impairment (dose-adjust) | Complete short course; report rash or unusual bruising |
| Silver sulfadiazine (topical) | Burns dressing 1% cream daily/bd | As adult, topical | Second/third-degree burns (broad cover incl. Pseudomonas), leg ulcers (short term) | Local rash, transient neutropenia/leucopenia on large-area use, kernicterus risk in newborn (absorbed sulphonamide) | Sulphonamide allergy; neonates; large burns in G6PD deficiency | Report spreading rash; painless peeling skin is a red flag |
Cotrimoxazole in detail
Cotrimoxazole deserves its own section because of its outsized role in HIV care and common syndromes:
- HIV prophylaxis: 960 mg daily (or thrice weekly) prevents PCP, toxoplasmosis and bacterial infections in eligible patients per national ART guidelines; co-trimoxazole prophylaxis is one of the highest-impact, cheapest interventions in HIV medicine.
- PCP (Pneumocystis pneumonia): treatment is high-dose (15–20 mg/kg/day of the trimethoprim component) for 21 days — oral in mild disease, IV in severe; add prednisolone when PaO₂ is low, per protocol.
- Resistance: high E. coli resistance in many regions has eroded its role in empiric UTI — check local antibiograms; in dysentery and PCP it retains strong activity.
- SJS/TEN warning: sulphonamide hypersensitivity is the classic trigger of Stevens–Johnson syndrome and toxic epidermal necrolysis. Any mucosal involvement, blistering or spreading rash on cotrimoxazole = stop the drug, admit, and never re-challenge.
Interactions and counselling
Scroll the table sideways on a smaller screen.
| Drug | Interacting agent | Effect | Action |
|---|---|---|---|
| Aminoglycosides | Loop diuretics (furosemide), vancomycin, amphotericin B, platinum agents | Additive nephro- and ototoxicity — deafness risk | Avoid combination; if unavoidable, monitor renal function and hearing closely |
| Aminoglycosides | Neuromuscular blockers (suxamethonium, vecuronium) | Prolonged paralysis / respiratory depression | Caution peri-operatively and in ITU; reverse block before extubation |
| Cotrimoxazole / trimethoprim | Warfarin | Marked INR rise → bleeding | Avoid or monitor INR every 2–3 days |
| Cotrimoxazole / trimethoprim | Methotrexate | Additive DHFR inhibition → severe marrow suppression | Contraindicated together |
| Cotrimoxazole / trimethoprim | Phenytoin, sulphonylureas (glibenclamide), digoxin | Reduced clearance → phenytoin toxicity, hypoglycaemia, raised digoxin | Monitor levels/clinical effect; counsel on hypoglycaemia |
| Cotrimoxazole / trimethoprim | ACE inhibitors, ARBs, spironolactone, potassium supplements | Additive hyperkalaemia (trimethoprim blocks ENaC) | Avoid in renal impairment; check potassium |
| Sulphonamides | Other sulphonamides/sulfonylureas ("sulfa" drugs), thiazides | "Sulfa allergy" cross-reactions — but sulphonamide antibiotics are distinct from non-antibiotic sulfa (e.g., furosemide) for most patients | Document carefully; true antibiotic-sulphonamide SJS/TEN is an absolute contraindication to all sulphonamide antibiotics |
Clinical scenarios
Scenario 1 — Neonatal sepsis on the postnatal ward
A 3-day-old, born at home, presents with poor feeding, hypothermia and fast breathing. You start the UCG empiric regimen: ampicillin plus gentamicin (gentamicin 3–5 mg/kg once daily by weight band). Gentamicin covers the Gram-negative enteric flora that colonise the birth canal; ampicillin covers Group B streptococcus, Listeria and pneumococcus. You take blood cultures first, check the mother's syphilis/HIV status, and arrange gentamicin level monitoring. On day 3 the cultures grow Escherichia coli sensitive to gentamicin — you continue, reassessing daily, and stop ampicillin (de-escalation).
Scenario 2 — The dizzy patient on gentamicin
A 67-year-old on day 6 of gentamicin for pyelonephritis reports new unsteadiness and a "full" feeling in the ears. Gentamicin preferentially damages the vestibular division — the onset of imbalance after several days is classic ototoxicity, and it may be irreversible. You stop the drug (switch to a safer alternative guided by sensitivities), document the adverse drug reaction, and check that the renal function had not quietly deteriorated — the accumulation that caused it. Teaching point: ask about hearing and balance daily; the patient rarely volunteers it until late.
Scenario 3 — HIV clinic: starting cotrimoxazole prophylaxis
A newly diagnosed 34-year-old with CD4 180 cells/µL starts ART; per national guidelines you also start cotrimoxazole 960 mg daily to prevent PCP and bacterial infections. You counsel: take with food if nauseated, drink well, and stop immediately for any rash or mouth ulcers — sulphonamides can cause a dangerous skin reaction (SJS). If she were on warfarin or had renal disease with ACE-inhibitor therapy, you would reconsider or monitor potassium and INR.
Key points
References
- WHO AWaRe Antibiotic Book, 2022/2023 — UTI, dysentery and PCP regimens (Library reference.)
- Uganda Clinical Guidelines 2023: neonatal sepsis, UTI and HIV/OI prophylaxis chapters (Library reference.)
- Uganda Essential Medicines and Health Supplies List 2023 (Library reference.)
- Katzung's Basic & Clinical Pharmacology — aminoglycoside and sulfonamide chapters (Library reference.)
- Goodman & Gilman's The Pharmacological Basis of Therapeutics (Library reference.)
- Uganda National ART/PMTCT guidelines — cotrimoxazole prophylaxis schedule (Library reference.)
Further reading
For deeper study, compare this lesson with current guidance and standard references from recognised medical and pharmaceutical organisations.
- WHO: The AWaRe Antibiotic Book
- Uganda MoH Knowledge Management Portal (UCG 2023 & EMHSLU 2023)
- NIH AIDSinfo — PCP and OI prophylaxis guidance
- DCM Year One Semester Two curriculum
For education only. Doses change with guideline updates — always verify against the current Uganda Clinical Guidelines, the EMHSLU 2023 and your facility formulary before prescribing.