
The renal system: glomerular filtration, tubular transport & acid-base regulation
On this page 19 sections
Primary renal functions
The kidneys are paired retroperitoneal organs that maintain whole-body extracellular fluid (ECF) homeostasis. Beyond clearing metabolic end-products, the kidneys regulate hemodynamic stability, electrolyte osmolarity, systemic acid-base equilibrium, and endocrine signaling.
Core Homeostatic & Metabolic Roles
- Excretion of Metabolic Wastes & Xenobiotics: Eliminates end-products of metabolism, including urea (amino acid catabolism), creatinine (muscle phosphocreatine breakdown), uric acid (purine turnover), bilirubin end-products (hemoglobin breakdown), and metabolites of hormones, environmental toxins, and pharmaceutical drugs.
- Regulation of Water & Electrolyte Balance: Matches renal excretion of water, sodium (Na+), potassium (K+), chloride (Cl-), calcium (Ca2+), magnesium (Mg2+), and phosphate (PO43-) to dietary intake and metabolic generation.
- Regulation of Arterial Blood Pressure: Mediates long-term blood pressure control through the pressure natriuresis mechanism (adjusting urinary excretion of Na+ and water) and short-to-intermediate control via the renin-angiotensin-aldosterone system (RAAS).
- Regulation of Acid-Base Balance: Works alongside pulmonary ventilation and chemical buffer systems to buffer non-volatile (fixed) metabolic acids (~80 mmol/day) by reabsorbing filtered bicarbonate (HCO3-) and generating new bicarbonate via titratable acid and ammonium excretion.
- Endocrine Secretion: Synthesizes and releases erythropoietin (EPO), which drives erythropoiesis in the bone marrow; renin, an enzymatic hormone triggering angiotensin II formation; and activates vitamin D via conversion to 1,25-dihydroxycholecalciferol (calcitriol).
- Gluconeogenesis: During prolonged fasting or metabolic acidosis, renal cortical proximal tubule cells deaminate glutamine and utilize glycerol, lactate, and pyruvate to synthesize glucose, contributing up to 20% to 50% of endogenous glucose release.
Macroanatomy & vasculature
The medial border of each kidney presents a deep vertical fissure—the renal hilum—which transmits the renal artery, renal vein, lymphatic trunks, autonomic nerve plexuses, and the funnel-shaped renal pelvis.
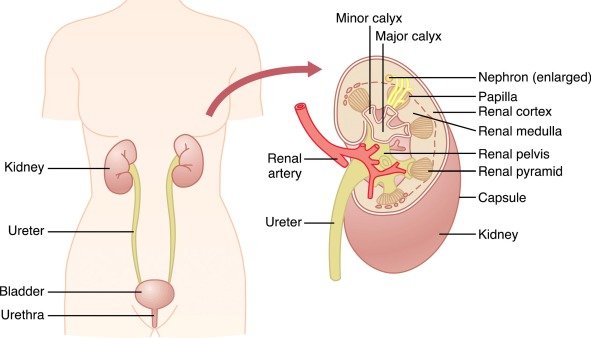
Internal Zonation & Urine Transport
- Renal Cortex: The outer granular zone beneath the fibrous capsule, containing all glomeruli, proximal convoluted tubules, and distal convoluted tubules.
- Renal Medulla: Divided into 8 to 18 striated conical masses termed renal pyramids. The broad base of each pyramid faces the cortico-medullary junction, while its apex—the renal papilla—terminates in a minor calyx.
- Pelvicalyceal System: Minor calyces (each draining several papillae) coalesce to form 2 to 3 major calyces, which unite into the funnel-shaped renal pelvis. The walls of the calyces, pelvis, and ureters contain intrinsic pacemaker cells and smooth muscle layers that generate rhythmic peristaltic contractions, propelling urine forward into the urinary bladder.
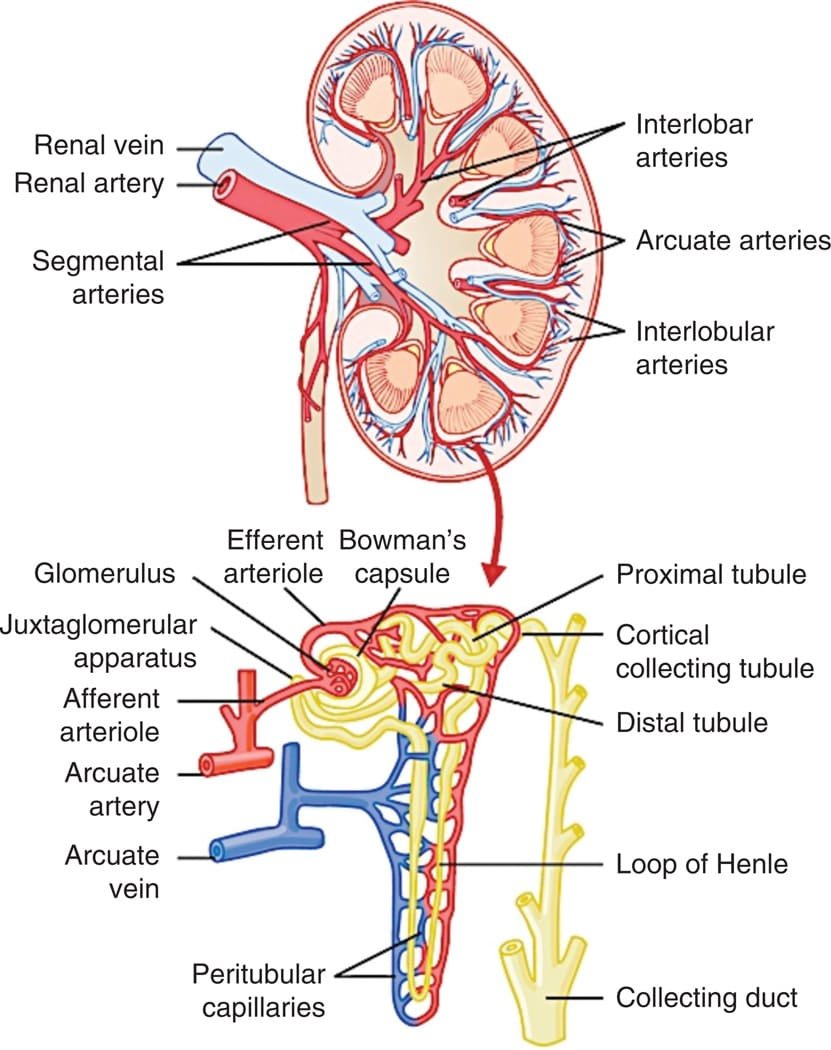
Renal Blood Supply: The Dual Capillary Portal Bed
The kidneys receive approximately 21% to 22% of total resting cardiac output (CO), corresponding to a renal blood flow (RBF) of roughly 1200 mL/min (or a renal plasma flow [RPF] of ~650 mL/min). This high blood flow serves filtration demands rather than metabolic needs.
Sequential Vascular Branching
Renal Artery → Segmental Arteries → Interlobar Arteries (passing between renal pyramids) → Arcuate Arteries (arching over pyramid bases along the cortico-medullary border) → Interlobular (Cortical Radiate) Arteries → Afferent Arterioles → Glomerular Capillaries → Efferent Arterioles → Peritubular Capillaries / Vasa Recta → Interlobular Veins → Arcuate Veins → Interlobar Veins → Renal Vein.
Hydrostatic Pressures in Renal Capillary Beds
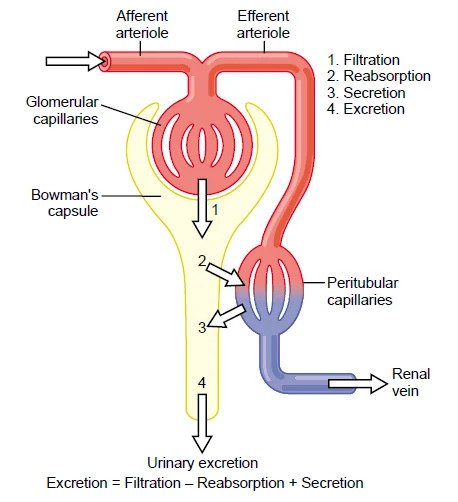
The renal circulation arranged in series forms two distinct capillary beds separated by high-resistance efferent arterioles:
- Glomerular Capillaries: Maintain a high hydrostatic pressure of ≈ 60 mmHg. This high pressure is sustained by resistance across the downstream efferent arteriole and provides the driving force for rapid fluid ultrafiltration across the glomerular membrane.
- Peritubular Capillaries: Positioned downstream of efferent arteriolar resistance, maintaining a low hydrostatic pressure of ≈ 13 mmHg. Combined with an elevated colloid osmotic pressure (≈ 32 mmHg) resulting from fluid filtration upstream in the glomerulus, this net inward force drives rapid fluid and solute reabsorption from the renal interstitium back into blood.
- Medullary Blood Flow (Vasa Recta): The renal medulla receives only ≈ 1% to 2% of total RBF via the hairpin loops of the vasa recta. This sluggish, low-volume perfusion is essential to prevent wash-out of the hyperosmotic medullary gradient.
The nephron: cortical vs. juxtamedullary
The nephron is the structural and functional unit of the kidney. Each human kidney contains approximately 800,000 to 1,200,000 nephrons. Nephrons cannot regenerate after injury; beyond 40 years of age, the number of functional nephrons declines by approximately 10% every 10 years due to physiologic glomerulosclerosis.
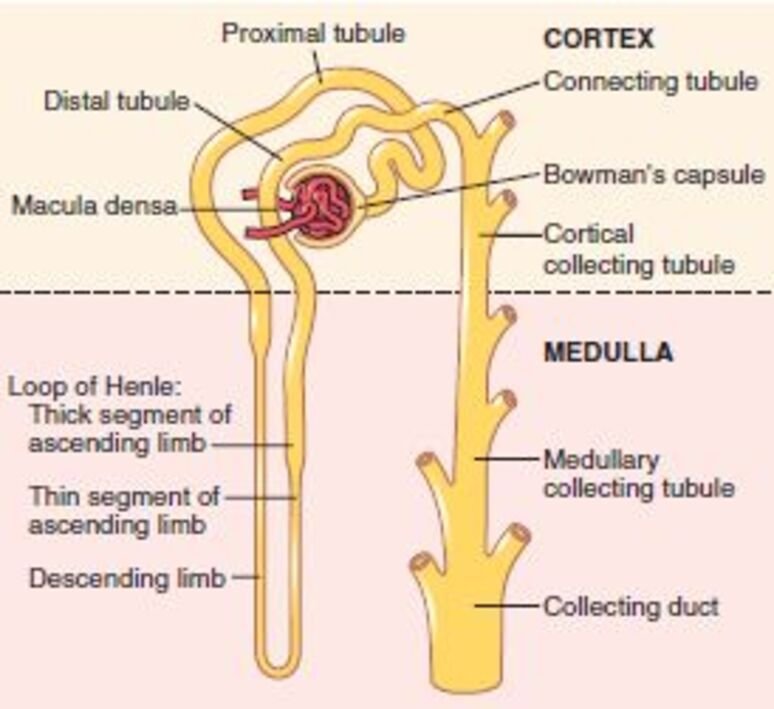
Nephron Segments
- Renal Corpuscle: Composed of an anastomosing network of branching glomerular capillaries encased within a blind, double-walled epithelial pouch: Bowman’s capsule.
- Proximal Convoluted & Straight Tubules: Located within the renal cortex; lined by high cuboidal epithelial cells with dense apical microvillar brush borders and abundant basolateral mitochondria.
- Loop of Henle: Dips from the cortex into the medulla. Divided into a thin descending limb (highly permeable to water), a thin ascending limb (present in long loops), and a thick ascending limb (TAL) (impermeable to water, with active solute extrusion).
- Macula Densa: A plaque of specialized tubular epithelial cells located at the transition between the thick ascending limb and early distal tubule, situated in physical contact with its parent glomerulus' afferent and efferent arterioles.
- Distal Tubule & Collecting Duct System: Comprises the early distal convoluted tubule, the late distal tubule, the connecting tubule, and the cortical collecting tubule. Approximately 8 to 10 cortical collecting ducts merge to form a single medullary collecting duct, which traverses the inner medulla to terminate at the tip of the renal papilla in the duct of Bellini.
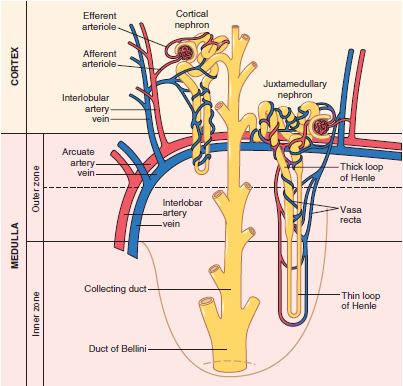
| Feature | Cortical Nephrons (70% – 80%) | Juxtamedullary Nephrons (20% – 30%) |
|---|---|---|
| Glomerular Location | Outer and mid-cortex | Deep cortex near the cortico-medullary junction |
| Loop of Henle Length | Short; loops penetrate only outer medulla or remain in cortex | Long; loops descend deep into the inner medulla down to the papilla tips |
| Thin Ascending Limb | Absent (thick ascending limb begins near the hairpin bend) | Present and well developed |
| Associated Post-Glomerular Capillaries | Extensive peritubular capillary meshwork encircling cortical tubules | Long efferent arterioles dividing into specialized hairpin loops: vasa recta |
| Primary Physiological Role | Bulk solute and water reabsorption; filtration clearance | Generation and maintenance of hyperosmotic medullary gradient for urine concentration |
Glomerular membrane & GFR determinants
Glomerular filtration is the non-selective first step in urine formation, producing an essentially protein-free ultrafiltrate of plasma within Bowman’s space at a rate of approximately 125 mL/min (180 L/day). This equals roughly 20% of renal plasma flow (Filtration Fraction, FF = GFR / RPF = 125 / 650 ≈ 0.20).
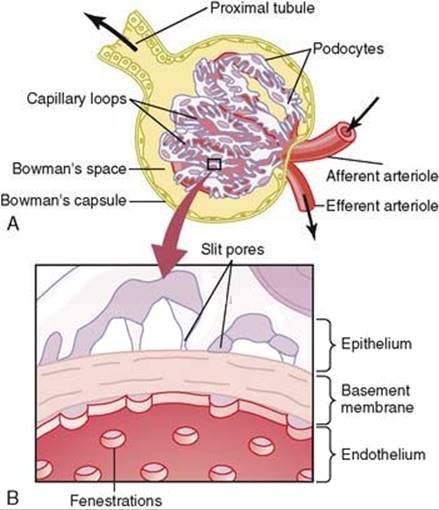
The Three Layers of the Glomerular Filtration Barrier
- 1. Capillary Endothelium: Perforated by thousands of fenestrae (70 to 90 nm in diameter). While preventing passage of cellular elements (erythrocytes, leukocytes, platelets), fenestrae allow free movement of plasma solutes and proteins.
- 2. Glomerular Basement Membrane (GBM): An acellular trilaminar meshwork (lamina rara interna, lamina densa, lamina rara externa) composed of type IV collagen, laminin, entactin, and negatively charged heparan sulfate proteoglycans. The negative charges exert an electrostatic barrier, repelling polyanionic macromolecules like serum albumin.
- 3. Visceral Epithelial Podocytes: Epithelial cells resting on the outer GBM surface that project primary and secondary foot processes (pedicels) which interdigitate around capillaries. Spaces between pedicels form filtration slit pores bridged by a porous protein diaphragm containing nephrin and podocin.
Determinants of Molecular Filterability: Size & Electrical Charge
| Substance | Molecular Weight (Da) | Relative Filterability (Water = 1.0) |
|---|---|---|
| Water | 18 | 1.0 |
| Sodium (Na+) | 23 | 1.0 |
| Glucose | 180 | 1.0 |
| Inulin | 5,500 | 1.0 |
| Myoglobin | 17,000 | 0.75 |
| Serum Albumin | 69,000 | 0.005 |
Physical Forces Determining GFR: The Starling Equation
The Glomerular Filtration Rate (GFR) is determined by the balance of transcapillary Starling physical forces and the capillary filtration coefficient (Kf):
Starling Equilibrium Formula
GFR = Kf × Net Filtration Pressure (NFP)
NFP = (PG − PB) − (ΠG − ΠB)
- Capillary Filtration Coefficient (Kf): The product of hydraulic conductivity and total filtering surface area (≈ 12.5 mL/min/mmHg in humans; ~400 times higher than most other systemic capillary beds).
- Glomerular Hydrostatic Pressure (PG): Promotes filtration; estimated at ≈ 60 mmHg.
- Bowman’s Capsule Hydrostatic Pressure (PB): Opposes filtration; estimated at ≈ 18 mmHg.
- Glomerular Capillary Colloid Osmotic Pressure (ΠG): Opposes filtration; averages ≈ 32 mmHg. Rises from ~28 mmHg at the afferent end to ~36 mmHg at the efferent end as protein-free filtrate leaves the capillary.
- Bowman’s Capsule Colloid Osmotic Pressure (ΠB): Promotes filtration; essentially 0 mmHg under physiological conditions because filtrate is protein-free.
- Net Filtration Pressure Calculation: NFP = (60 − 18) − (32 − 0) = 42 − 32 = +10 mmHg.
Autoregulation & tubuloglomerular feedback
The kidney possesses intrinsic regulatory mechanisms that hold renal blood flow (RBF) and GFR relatively constant across systemic mean arterial pressures ranging from 80 to 170 mmHg. This protects the delicate glomerular capillaries from hypertensive injury and prevents large fluctuations in fluid and solute excretion.
1. The Myogenic Mechanism
An intrinsic property of vascular smooth muscle. An increase in perfusion pressure stretches the afferent arteriolar wall, activating stretch-sensitive non-selective cation channels. Depolarization opens voltage-gated L-type Ca2+ channels, triggering smooth muscle contraction. The resulting increase in afferent arteriolar resistance prevents elevations in downstream glomerular hydrostatic pressure (PG) and preserves a stable GFR.
2. Tubuloglomerular Feedback (TGF)
A negative feedback circuit executed by the juxtaglomerular apparatus (JGA), linking changes in sodium chloride (NaCl) concentration at the macula densa with the control of renal arteriolar resistance.
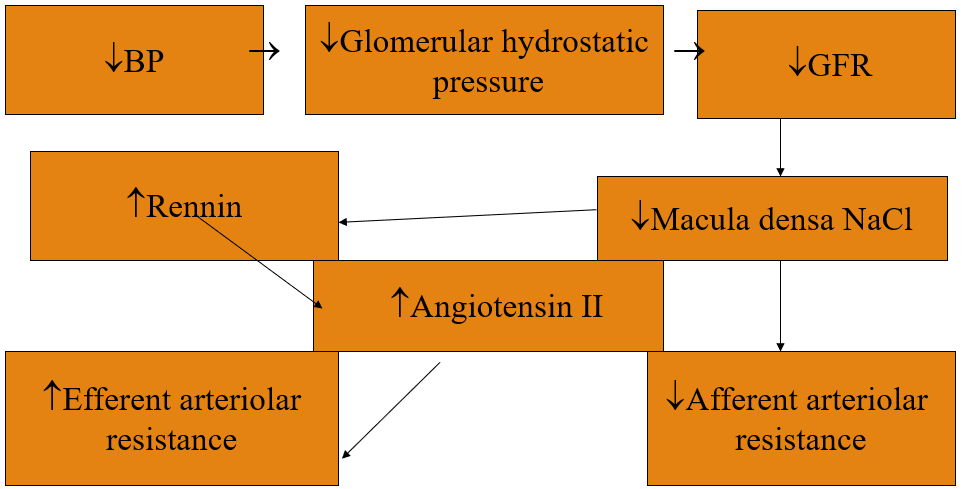
Dual-Effector Mechanisms of Tubuloglomerular Feedback
- Response to Elevated GFR: Increased GFR increases fluid delivery to the loop of Henle, overwhelming reabsorptive capacity. High luminal NaCl reaches the macula densa via the Na+-2Cl--K+ cotransporter (NKCC2). Intracellular Na+ accumulation promotes ATP breakdown into adenosine. Adenosine binds vascular A1 receptors on the afferent arteriole, inducing afferent vasoconstriction, which lowers PG and restores GFR to baseline.
- Response to Decreased GFR (Hypoperfusion/Hypotension): Decreased arterial pressure lowers PG and decreases GFR, slowing tubular flow rate. Slower transit allows more complete NaCl reabsorption in the thick ascending limb, resulting in reduced NaCl concentration at the macula densa. This triggers two coordinated responses:
- Afferent Arteriolar Vasodilation: Decreased adenosine and increased local nitric oxide (nNOS) and prostaglandins (PGI2) dilate the afferent arteriole, raising glomerular hydrostatic pressure.
- Stimulation of Renin Release: Juxtaglomerular (granular) cells on the afferent arteriole release renin into the circulation. Renin cleaves hepatic angiotensinogen into angiotensin I, converted by pulmonary/endothelial ACE to angiotensin II. Angiotensin II selectively constricts the efferent arteriole (which possesses higher AT1 receptor sensitivity). Efferent constriction increases PG back toward normal, preventing precipitous declines in GFR during hypovolemia.
Extrinsic Neurohumoral Modulators of GFR & RBF
- Renal Sympathetic Nerves & Catecholamines: Mild or moderate sympathetic stimulation has minimal effect on GFR. Intense sympathetic activation (hemorrhage, severe shock, strenuous exercise) constricts both afferent and efferent arterioles via α1 receptors, decreasing RBF and GFR to preserve systemic cerebral and coronary perfusion.
- Endothelial Nitric Oxide (NO): Basal endothelial NO release decreases renal vascular resistance, buffering against excessive vasoconstriction and promoting normal excretion of Na+ and water.
- Prostaglandins (PGE2, PGI2) & Bradykinin: Locally produced renal prostaglandins cause vasodilation, particularly at the afferent arteriole, maintaining renal perfusion during periods of high sympathetic or angiotensin II activity. Nonsteroidal anti-inflammatory drugs (NSAIDs) block cyclooxygenase (COX-1/COX-2), eliminating this protective vasodilation and precipitating acute pre-renal renal failure during hypovolemia.
Tubular transport & peritubular forces
As the 180 L/day of glomerular ultrafiltrate traverses the tubular nephron, its volume and composition are modified. Tubular reabsorption is quantitatively more significant than secretion: over 99% of filtered water and electrolytes are recovered, while waste products (urea, creatinine) are poorly reabsorbed and concentrated in the urine.
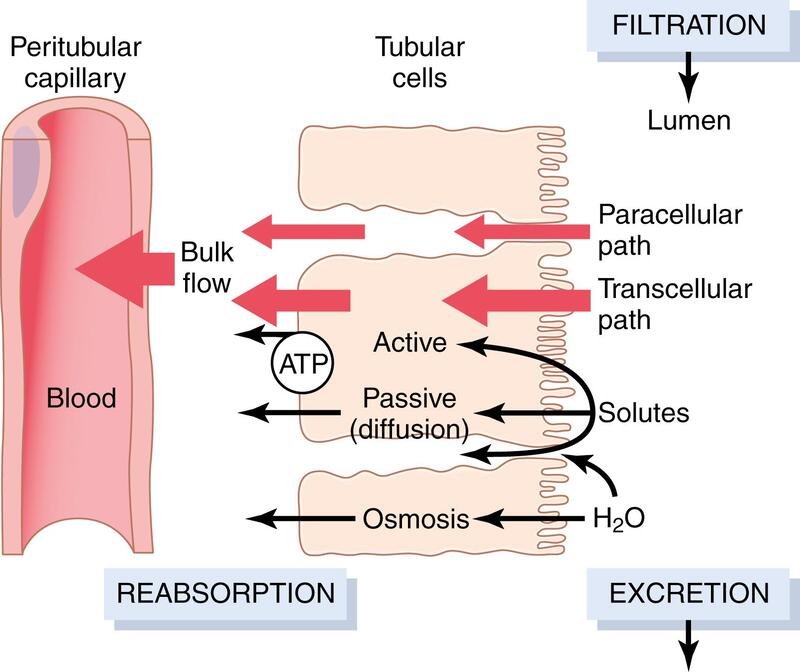
Transport Pathways & Energetics
- Transcellular Transport: Solutes cross the apical luminal membrane, traverse the intracellular cytoplasm, and are extruded across the basolateral membrane into the renal interstitial fluid (ISF).
- Paracellular Transport: Solutes and water diffuse across intercellular tight junctions (zonula occludens) and lateral intercellular spaces, driven by passive electrochemical or osmotic gradients.
- Primary Active Transport: Directly hydrolyzes ATP. Key renal primary active pumps include the basolateral Na+/K+-ATPase, apical and basolateral H+-ATPase, H+/K+-ATPase, and Ca2+-ATPase.
- Secondary Active Transport: Couples the “downhill” movement of an ion (typically Na+, moving down its steep basolateral Na+/K+-ATPase-maintained electrochemical gradient) to the “uphill” transport of a second solute against its gradient:
- Symport (Cotransport): Both molecules move in the same direction across the membrane (e.g., SGLT2 Na+-glucose cotransport; Na+-amino acid cotransport; Na+-K+-2Cl- cotransport).
- Antiport (Countertransport): Driving and driven molecules move in opposite directions (e.g., NHE3 Na+/H+ exchanger).
- Pinocytosis: Large filtered molecules (e.g., small peptides and albumin that escape the glomerulus) bind to apical megalin-cubilin receptor complexes, are internalized via endocytosis, and are degraded in lysosomes into amino acids that return to blood.
Transport Maximum (Tm)
For most actively reabsorbed or secreted substances, there is a physical saturation limit to the rate of transport (Transport Maximum, Tm). This occurs when the filtered tubular load exceeds the capacity of available membrane carrier proteins and associated enzymes.
- Glucose Tm & Renal Threshold: The normal glucose Tm in adults is approximately 375 mg/min. Under normal conditions (filtered load ≈ 125 mg/min), all filtered glucose is reabsorbed in the proximal tubule. If plasma glucose exceeds ~180 to 200 mg/dL (“renal threshold”), the filtered load begins to exceed the Tm of individual nephrons (due to glomerulotubular splay), and glucose appears in the urine (glucosuria), driving an osmotic diuresis.
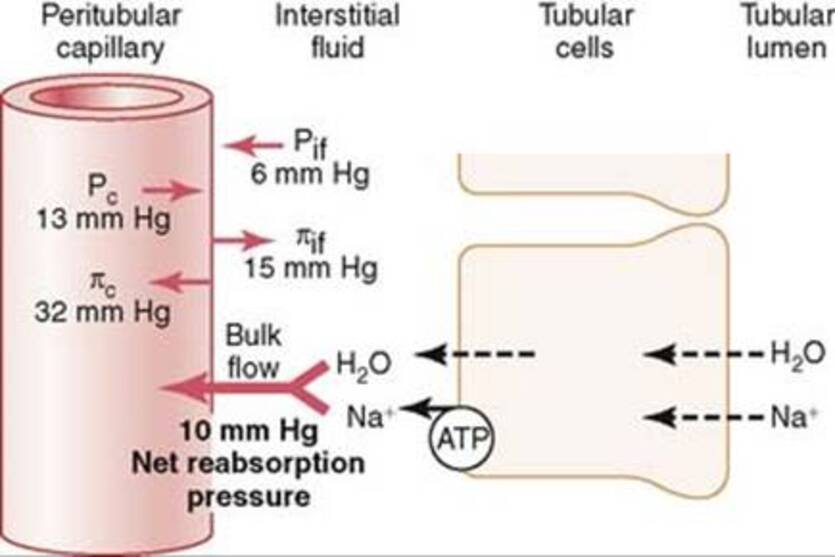
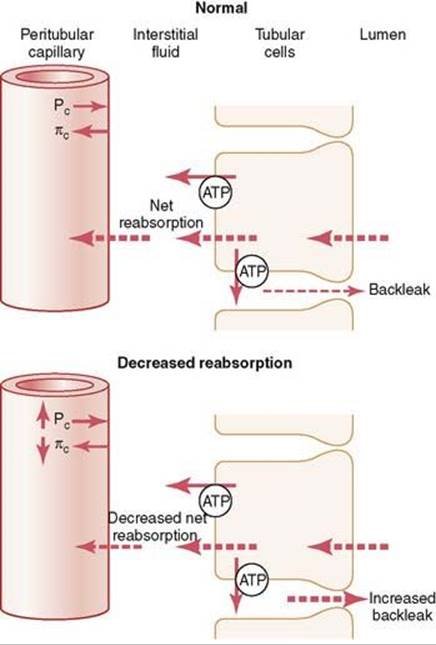
Starling Forces Governing Peritubular Capillary Uptake
Fluid reabsorption from the renal interstitium into peritubular capillaries is governed by the net reabsorptive pressure (NRP) and the peritubular capillary filtration coefficient (Kf):
Peritubular Reabsorption Starling Forces
Reabsorption Rate = Kf × Net Reabsorptive Force
- Peritubular Capillary Hydrostatic Pressure (Pc): Opposes reabsorption; estimated at ≈ 13 mmHg.
- Renal Interstitium Hydrostatic Pressure (Pif): Promotes reabsorption; estimated at ≈ 6 mmHg.
- Peritubular Capillary Colloid Osmotic Pressure (Πc): Promotes reabsorption; estimated at ≈ 32 mmHg.
- Renal Interstitial Colloid Osmotic Pressure (Πif): Opposes reabsorption; estimated at ≈ 15 mmHg.
- Net Reabsorptive Force: (Πc − Πif) − (Pc − Pif) = (32 − 15) − (13 − 6) = 17 − 7 = +10 mmHg.
- Normal Capillary Reabsorption Rate: Approximately 124 mL/min (leaving ~1 mL/min as final urine output).
Glomerulotubular Balance (GTB)
Glomerulotubular balance is an intrinsic property of the renal tubules (especially the proximal convoluted tubule and loop of Henle) to automatically increase their absolute reabsorption rate in direct proportion to an increase in tubular load (GFR). If GFR increases from 125 to 150 mL/min, proximal tubular reabsorption rises from ~81 to ~97.5 mL/min, holding the fraction of filtered water and sodium reabsorbed relatively constant at ≈ 65%. GTB operates independent of hormonal signals and prevents downstream distal tubule segments from being overwhelmed by fluctuations in GFR.
Proximal tubule transport
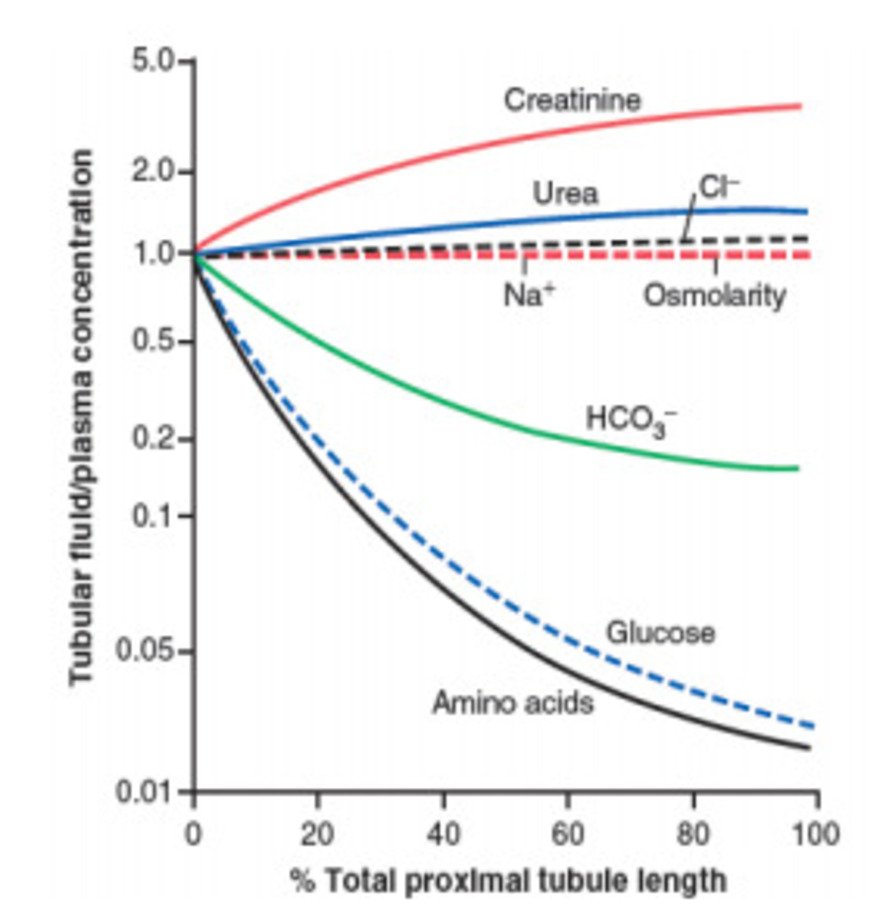
The proximal convoluted tubule (PCT) is responsible for the bulk reabsorption of filtered fluid and solutes. Because water follows sodium isotonically through abundant aquaporin-1 (AQP-1) water channels and paracellular tight junctions, proximal tubular fluid remains isها-osmotic to plasma (~300 mOsm/L) along its entire length.
Solute Handling in the Proximal Tubule
- Bulk Reabsorption Quantities: Reabsorbs ≈ 65% of filtered Na+, water, and K+, ≈ 85% of filtered HCO3-, and ≈ 100% of filtered glucose and amino acids.
- Sodium-Coupled Entry: The basolateral Na+/K+-ATPase maintains a low intracellular Na+ concentration (~12 mM) and a negative cell interior (−70 mV). Na+ enters across the apical brush border down this electrochemical gradient via:
- SGLT2 / SGLT1: Sodium-glucose cotransporters.
- Na+-Amino Acid Cotransporters: Clear amino acids from the lumen.
- NHE3: Sodium-hydrogen antiporter (exchanging 1 luminal Na+ for 1 intracellular H+, driving bicarbonate reabsorption).
- NaPi-IIa / NaPi-IIc: Sodium-phosphate cotransporters (inhibited by parathyroid hormone [PTH] and FGF-23).
- Chloride Reabsorption & Lumen Potential: In the early PCT, preferred reabsorption of glucose, amino acids, and HCO3- concentrates chloride in the lumen. In the late PCT, chloride diffuses down its concentration gradient via paracellular routes and apical Cl-/formate exchangers, generating a slightly lumen-positive transepithelial potential (+2 to +4 mV) that drives passive paracellular reabsorption of Na+, Ca2+, and Mg2+.
- Organic Acid & Base Secretion: The PCT actively secretes endogenous waste metabolites and xenobiotics into the lumen:
- Organic Anion Transporters (OATs): Secrete urate, oxalate, bile salts, para-aminohippurate (PAH), penicillin, furosemide, and cephalosporins via tertiary active transport coupled to α-ketoglutarate exchange.
- Organic Cation Transporters (OCTs): Secrete catecholamines, choline, creatinine, cimetidine, and morphine via proton/cation exchange.
Loop of Henle dynamics
The loop of Henle reabsorbs approximately 25% of filtered Na+, Cl-, and K+, alongside 15% of filtered water, playing a central role in generating the corticomedullary osmotic gradient.
1. Thin Descending Limb
Has a thin epithelial membrane with few mitochondria and minimal active transport capacity. Expresses high densities of constitutive aquaporin-1 (AQP-1) channels, making it highly permeable to water, but virtually impermeable to NaCl and urea. As tubular fluid descends into the hyperosmotic medullary interstitium, water exits by osmosis, concentrating the luminal fluid up to 1200–1400 mOsm/L at the hairpin bend of juxtamedullary nephrons.
2. Thin Ascending Limb
Present in long-looped juxtamedullary nephrons. It is impermeable to water, but moderately permeable to NaCl. NaCl diffuses passively down its concentration gradient out of the concentrated tubular fluid into the medullary interstitium.
3. Thick Ascending Limb (TAL)
Composed of tall, metabolic cuboidal epithelial cells with prominent basolateral infoldings and high Na+/K+-ATPase density. The TAL is completely impermeable to water, a property that remains true even in the presence of high circulating concentrations of antidiuretic hormone (ADH).
Electrogenic Mechanisms in the Thick Ascending Limb
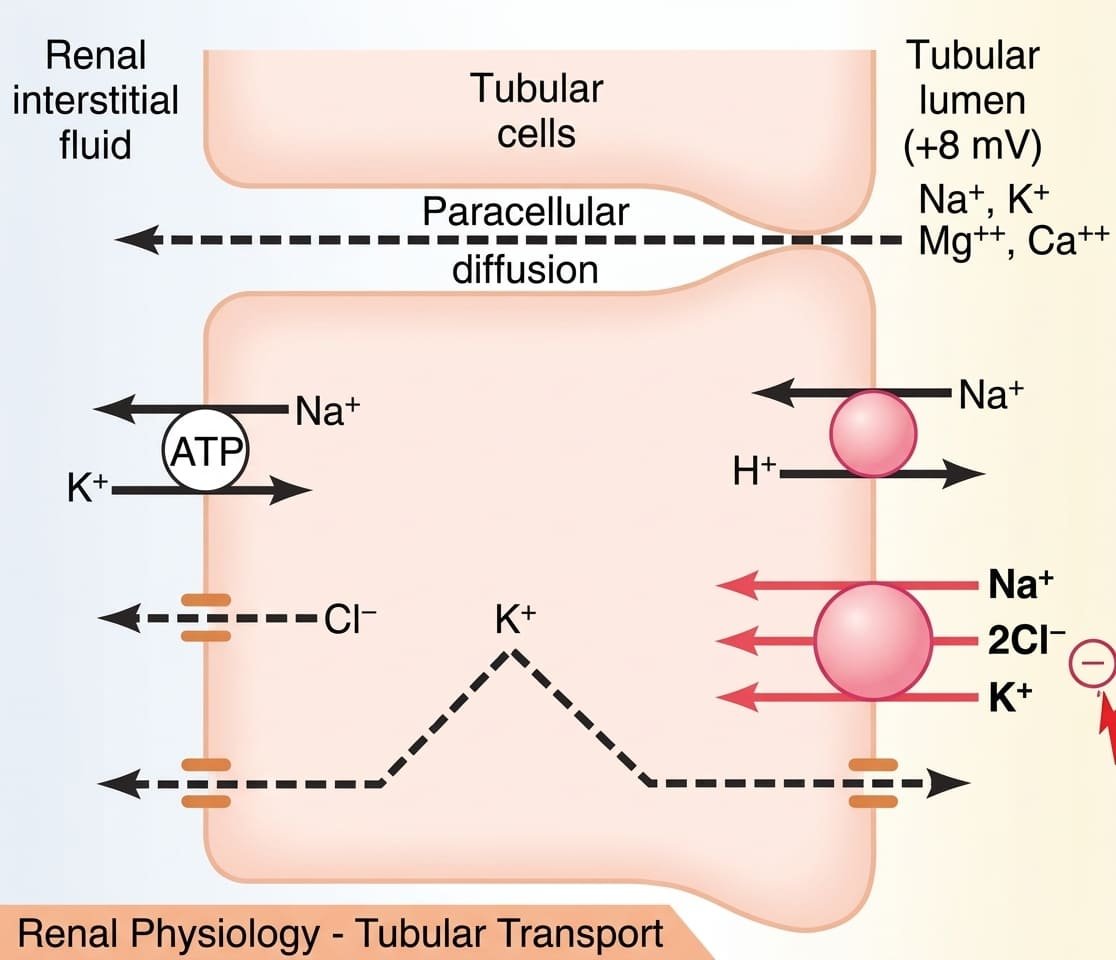
- The NKCC2 Cotransporter: Translocates 1 Na+, 2 Cl-, and 1 K+ electroneutrally across the apical membrane into the tubular cell. Target of loop diuretics (e.g., furosemide, bumetanide, torsemide), which bind the chloride-binding site of NKCC2, halting transport.
- ROMK K+ Back-Leak: To prevent luminal K+ depletion from stalling the NKCC2 carrier, K+ recycles back into the lumen through apical ROMK (renal outer medullary potassium) channels.
- Lumen-Positive Potential: The return of K+ into the lumen alongside basolateral extrusion of Cl- (via ClC-Kb channels) and Na+ (via Na+/K+-ATPase) creates an electrogenic lumen-positive potential (+8 mV). This provides the primary driving force for passive paracellular reabsorption of divalent cations: Mg2+ (~60%) and Ca2+ (~25%) through tight junction proteins (claudin-16 and claudin-19). Loop diuretics dissipate this potential, increasing urinary excretion of Ca2+ and Mg2+.
- Diluting Segment: Because active solute reabsorption occurs without water movement, tubular fluid leaving the thick ascending limb becomes hypoosmotic to plasma, exiting at ≈ 100 mOsm/L into the early distal tubule.
Distal tubule & collecting system
The distal nephron and collecting system fine-tune the final composition of urine according to homeostatic requirements.
1. Early Distal Convoluted Tubule
- Macula Densa: The initial short segment forms the macula densa of the juxtaglomerular complex, executing tubuloglomerular feedback.
- Cortical Diluting Segment: The remainder of the early DCT continues solute reabsorption while remaining completely impermeable to water and urea. Expresses the apical electroneutral Na+-Cl- cotransporter (NCCT), which is selectively inhibited by thiazide diuretics (e.g., hydrochlorothiazide). Also reabsorbs Ca2+ transcellularly via apical TRPV5 channels and basolateral Na+/Ca2+ exchangers under the control of parathyroid hormone (PTH).
2. Late Distal Tubule & Cortical Collecting Tubules
Impermeable to urea, but permeability to water is dynamically controlled by antidiuretic hormone (ADH). Composed of two distinct cell types:
Principal Cells (~90% of Epithelial Cells)
- Sodium Reabsorption & Potassium Secretion: Reabsorbs Na+ and water while secreting K+ into the lumen.
- Basolateral & Luminal Machinery: Basolateral Na+/K+-ATPase pumps Na+ out and brings K+ in. Na+ enters passively from the lumen through apical epithelial sodium channels (ENaC) (blocked by potassium-sparing diuretics like amiloride and triamterene). The net inward movement of Na+ generates a lumen-negative potential (−10 to −20 mV), which pulls K+ out of principal cells through apical ROMK and BK channels.
- Aldosterone Control: Aldosterone diffuses into principal cells, binds cytoplasmic mineralocorticoid receptors (MR), and upregulates transcription of ENaC, ROMK, and basolateral Na+/K+-ATPase pumps, stimulating Na+ retention and K+ excretion. (Spironolactone and eplerenone are competitive MR antagonists).
Intercalated Cells (~10% of Epithelial Cells)
- Acid-Base & Potassium Transport: Key regulators of hydrogen ion secretion and potassium reabsorption.
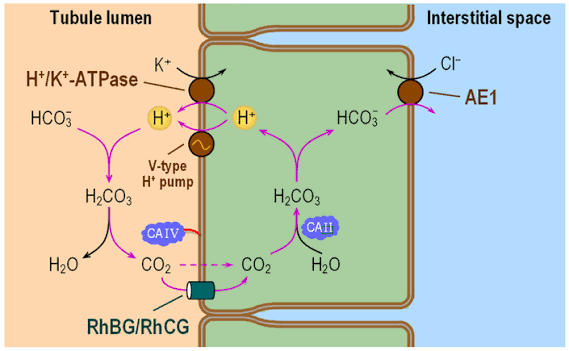
- Type A Intercalated Cells: Secrete H+ into the lumen via apical primary active H+-ATPase and H+/K+-ATPase pumps while reabsorbing HCO3- and K+ into peritubular capillaries via basolateral AE1 (anion exchanger 1) Cl-/HCO3- antiporters. Active during acidosis.
- Type B Intercalated Cells: Feature reversed polarity (apical pendrin Cl-/HCO3- exchanger, basolateral H+-ATPase). Secrete HCO3- into the urine and reabsorb H+ into the blood. Active during systemic alkalosis.
3. Medullary Collecting Duct
- Transport Role: Reabsorbs less than 10% of filtered water and sodium, acting as the final site for urine concentration.
- ADH-Dependent Water Permeability: Expresses basolateral V2 receptors. ADH binding activates Gs, elevating cAMP to trigger exocytic insertion of aquaporin-2 (AQP-2) water channels into the apical membrane.
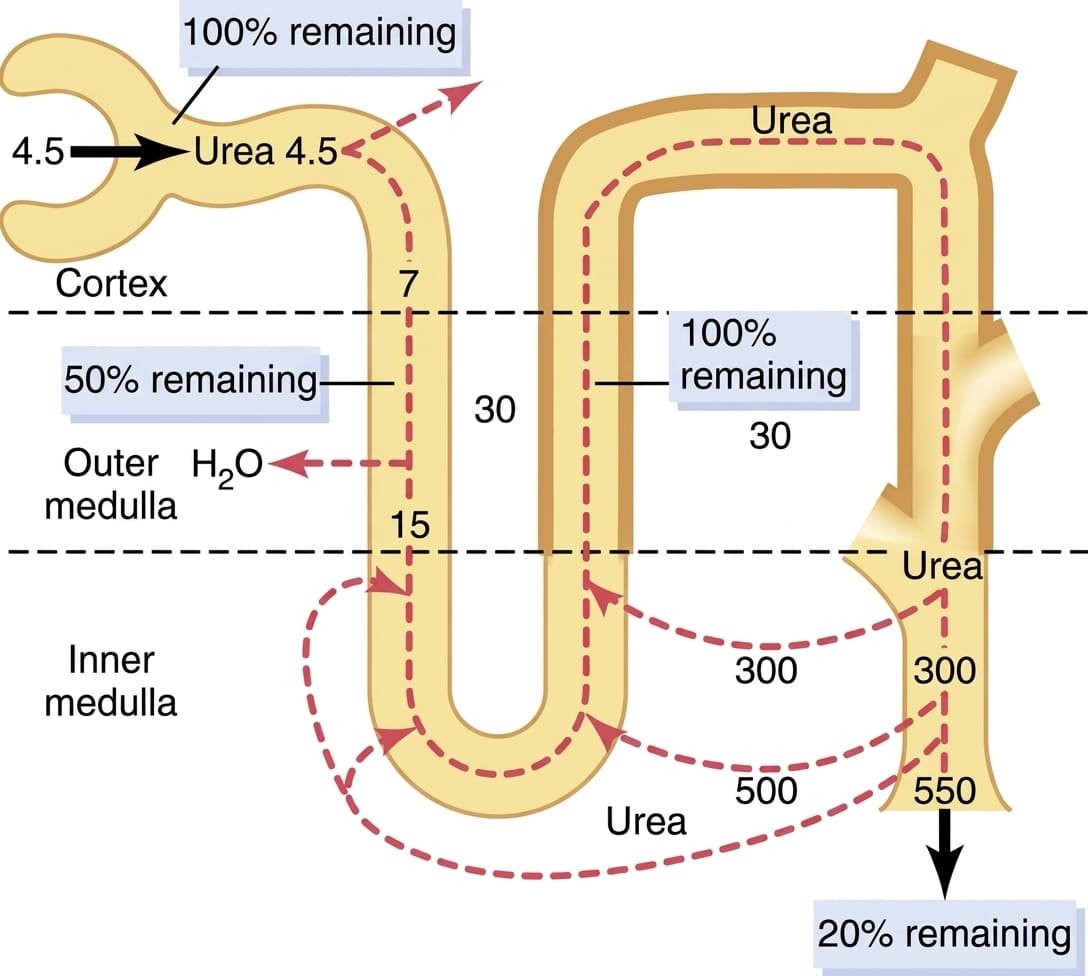
- Urea Permeability: Unlike earlier segments, the inner medullary collecting duct expresses facilitated urea transporters (UT-A1, UT-A3) activated by ADH, allowing concentrated urea to diffuse into the deep medullary interstitium.
- Steep Proton Secretion: Capable of pumping H+ against an electrochemical gradient exceeding 1:1000 via apical H+-ATPases, lowering urine pH down to its physiological minimum of 4.5.
Urine concentration & dilution
The human kidney can vary urine concentration across a wide range—from a dilute 50 mOsm/L (excreting up to 20 L/day of water) to a concentrated 1200 to 1400 mOsm/L (conserving water during dehydration). To excrete the daily obligatory solute load (~600 mOsm/day), the body must maintain a minimal obligatory urine volume of ≈ 0.5 L/day (600 mOsm / 1200 mOsm/L = 0.5 L).
Requirements for Excreting Concentrated Urine
- Elevated Circulating ADH (Vasopressin): Renders the late distal tubules and collecting ducts permeable to water.
- Hyperosmotic Renal Medullary Interstitium: Provides the osmotic driving gradient to draw water out of the collecting ducts into the peritubular space.
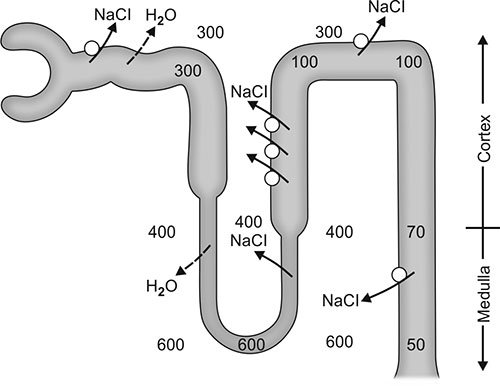
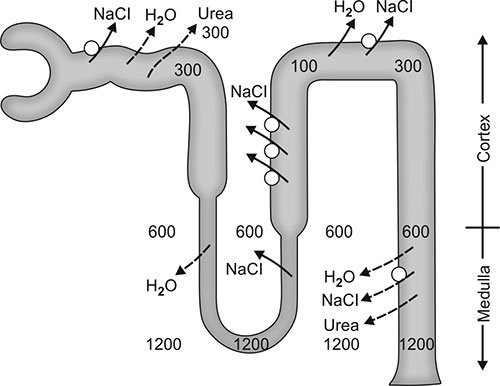
The Countercurrent Multiplier Mechanism
The countercurrent multiplier depends on the anatomical arrangement of the long loops of Henle in juxtamedullary nephrons. It operates via the interaction between active solute transport and countercurrent flow:
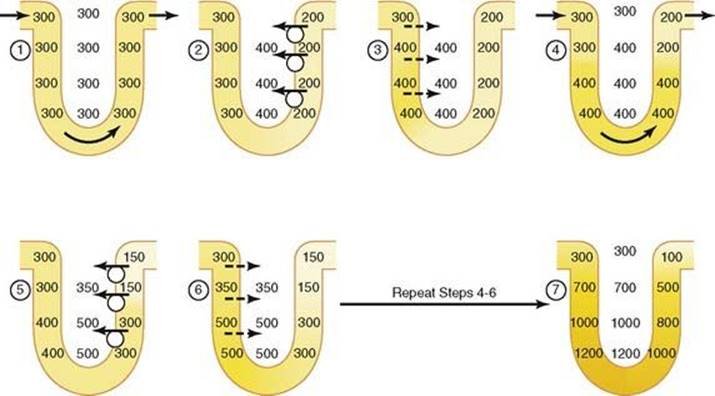
Steps of the Countercurrent Multiplier
- The Single Effect: The thick ascending limb actively pumps Na+, Cl-, and K+ into the interstitium while remaining impermeable to water, establishing a maximum transverse concentration gradient of 200 mOsm/L between the tubular fluid and surrounding interstitial fluid.
- Osmotic Equilibration: As isosmotic fluid (300 mOsm/L) enters the descending limb, water diffuses out into the 400 mOsm/L interstitium until the descending tubular fluid equilibrates at 400 mOsm/L.
- Axial Fluid Flow: New isosmotic fluid enters from the proximal tubule, pushing the hyperosmotic fluid from the descending limb around the hairpin bend into the thick ascending limb.
- Multiplication of the Gradient: The TAL pumps ions out of this already concentrated fluid, establishing another 200 mOsm/L gradient. With repetitive cycles, this process multiplies the 200 mOsm/L horizontal gradient into a vertical cortico-medullary gradient reaching 1200 to 1400 mOsm/L in the inner medulla.
Role of Urea Recycling in Medullary Hyperosmolarity
Passive urea reabsorption from the inner medullary collecting ducts contributes approximately 40% to 50% of the total medullary interstitial osmolarity (~500 to 600 mOsm/L of the 1200 mOsm/L total) when forming maximally concentrated urine.
The Countercurrent Exchanger: Role of the Vasa Recta
The vasa recta are specialized peritubular capillary loops that supply metabolic nutrients to the medulla without dissipating the hyperosmotic medullary gradient. They function as passive countercurrent exchangers:
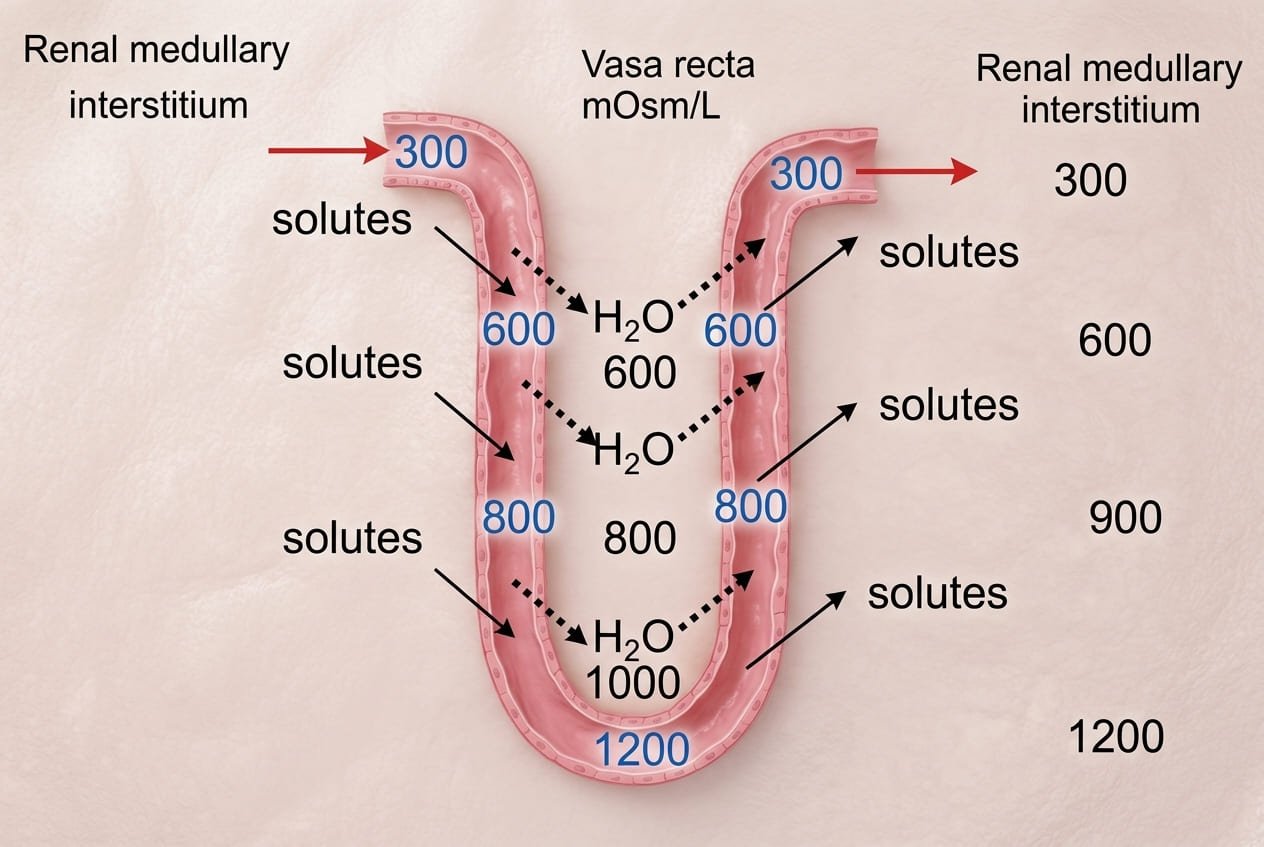
Vasa Recta Preservative Features
- Hairpin Geometry: The U-shaped architecture prevents blood from entering the medulla at one end and exiting at the other, minimizing solute wash-out.
- Sluggish Flow: Medullary blood flow represents only 1% to 2% of total RBF, ensuring that solute removal is slow and matched to the active transport capacity of the thick ascending limb.
Potassium homeostasis
Extracellular fluid potassium concentration is tightly regulated at 4.2 ± 0.3 mEq/L. Because only ≈ 2% of total body potassium resides in the ECF (~59 mEq), with 98% stored intracellularly (~3,920 mEq), minor shifts between compartments or alterations in renal elimination can trigger life-threatening cardiac arrhythmias.
Renal Potassium Handling
- Fractional Reabsorption: Approximately 65% of filtered K+ is reabsorbed in the PCT (primarily paracellularly with water), and 25% to 30% is reabsorbed in the thick ascending limb via the NKCC2 cotransporter.
- Regulatory Site: Dietary variations in potassium intake (ranging from 50 to 200 mEq/day) are managed by adjusting K+ secretion in the late distal tubule and cortical collecting tubule. Under high-potassium intake, principal cells increase K+ secretion; under severe potassium depletion, intercalated cells cease secretion and actively reabsorb K+ via apical H+/K+-ATPase pumps.
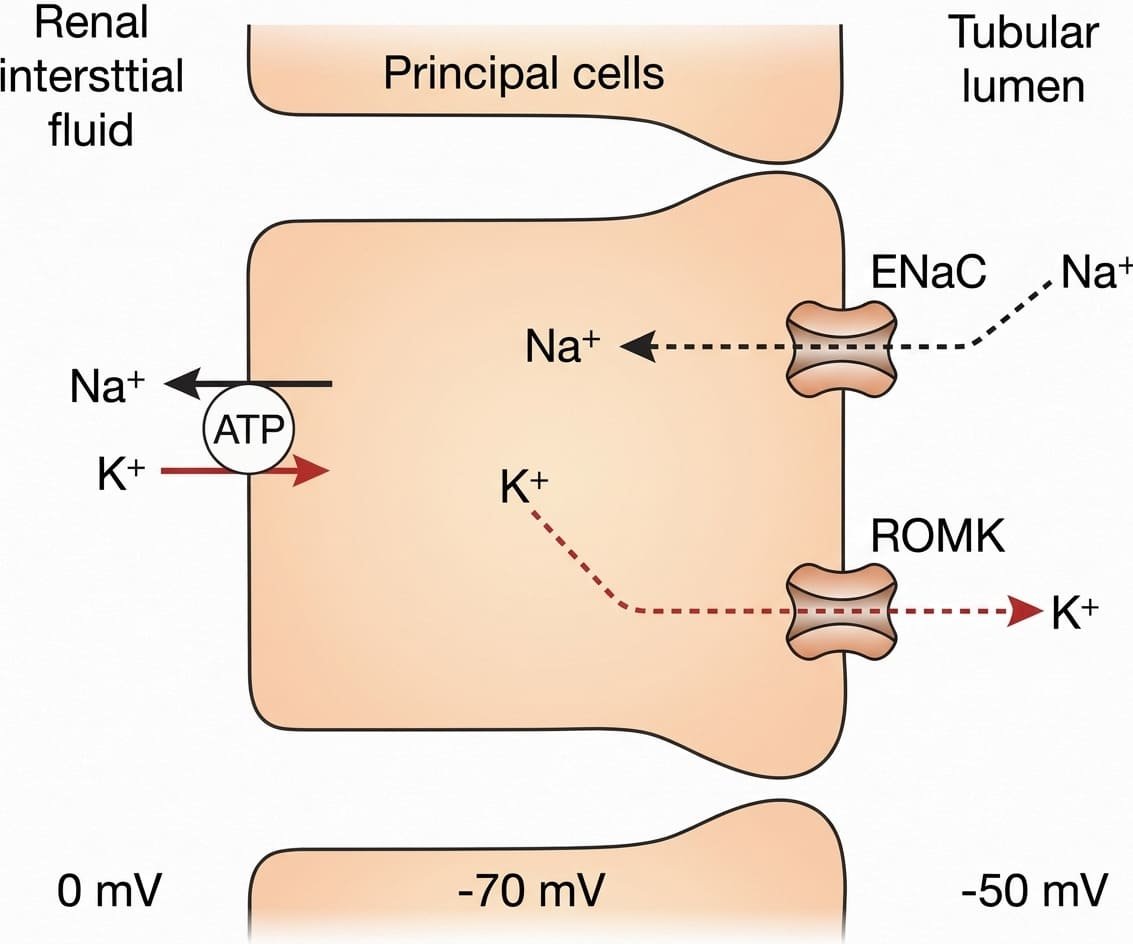
Factors Regulating Potassium Secretion by Principal Cells
| Regulatory Factor | Direction of Potassium Secretion | Underlying Cellular Mechanism |
|---|---|---|
| Increased Extracellular [K+] (>4.1 mEq/L) | Increased Secretion (↑) | Directly stimulates basolateral Na+/K+-ATPase activity, elevates intracellular [K+], increases electrochemical gradient across the luminal membrane, reduces basolateral back-leak, and directly triggers adrenal aldosterone secretion. |
| Elevated Aldosterone | Increased Secretion (↑) | Upregulates basolateral Na+/K+-ATPase pumps, increases apical ENaC channel density (deepening lumen negativity), and increases apical membrane permeability to K+. |
| Increased Tubular Flow Rate | Increased Secretion (↑) | High flow (e.g., volume expansion, high-salt intake, loop/thiazide diuretics) flushes secreted K+ downstream, maintaining a steep lumen-to-cell concentration gradient; bending of primary cilia opens high-conductance calcium-activated BK channels. |
| Acute Acidosis (↑ [H+], ↓ pH) | Decreased Secretion (↓) | Intracellular H+ accumulation inhibits the basolateral Na+/K+-ATPase pump and closes apical ROMK channels, reducing potassium entry and secretion into the tubular lumen. |
| Chronic Acidosis | Increased Secretion (↑) | Prolonged acidosis inhibits proximal tubular NaCl and water reabsorption, increasing distal tubular fluid flow rate and overriding the local inhibitory effects of H+ on the Na+/K+-ATPase pump. |
Chemical buffer systems & H-H equation
Extracellular [H+] is maintained at approximately 40 nEq/L (0.00004 mEq/L), corresponding to a physiological arterial pH of 7.40 (normal range: 7.35 to 7.45). The compatible limits of human life over several hours span a blood pH of 6.80 to 8.00. Defense against changes in body fluid [H+] relies on three systems operating over different timescales:
- Chemical Buffer Systems: Combine with acids or bases in seconds to minimize immediate pH shifts.
- Respiratory Center: Modulates alveolar ventilation within 3 to 12 minutes to adjust the rate of volatile CO2 excretion.
- Renal Mechanisms: The slowest but most powerful regulatory system (taking hours to days), capable of completely restoring pH balance by reabsorbing filtered HCO3-, excreting titratable acids, and synthesizing new HCO3- via ammoniagenesis.
Primary Chemical Buffer Systems
- Bicarbonate Buffer System: The primary buffer of extracellular fluid. Consists of a weak acid (H2CO3, carbonic acid) and a conjugate base salt (NaHCO3, sodium bicarbonate). When a strong acid (HCl) is added, it reacts with NaHCO3 to form weak carbonic acid and NaCl, mitigating the fall in pH. When a strong base (NaOH) is added, it reacts with H2CO3 to form NaHCO3 and water.
- Phosphate Buffer System: Composed of dihydrogen phosphate (H2PO4-, weak acid) and monohydrogen phosphate (HPO42-, conjugate base). Operates with a pK of 6.80. Its low extracellular concentration (~8% of bicarbonate) limits its buffering power in ECF, but it is a major buffer in intracellular fluid (ICF) and in renal tubular fluid, where phosphate is concentrated by water reabsorption and tubular pH approaches 6.8.
- Protein Buffer System: Responsible for 60% to 70% of total chemical buffering in the body, primarily intracellularly. Hemoglobin in erythrocytes (HHb / Hb-) buffers H+ generated from metabolic CO2. Histidine imidazole residues on albumin and intracellular proteins have pKs close to 7.4.
- The Isohydric Principle: All chemical buffer pairs in a common solution are in equilibrium with the same shared hydrogen ion concentration:
[H+] = K1 × [HA1] / [A1-] = K2 × [HA2] / [A2-] = K3 × [HA3] / [A3-].
The Henderson-Hasselbalch Equation
The equilibrium of the carbonic acid-bicarbonate buffer system is governed by the law of mass action:
Mathematical Derivation
CO2 + H2O ↔ H2CO3 ↔ H+ + HCO3-
Because dissolved CO2 is in equilibrium with H2CO3, dissolved CO2 is calculated as the product of its solubility coefficient (α = 0.0306 mmol/L/mmHg) and arterial carbon dioxide tension (PCO2):
[H+] = K × (0.03 × PCO2) / [HCO3-]
Taking the negative logarithm on both sides yields the Henderson-Hasselbalch equation:
pH = pK + log ([HCO3-] / [0.03 × PCO2])
Substituting the pK of the system (6.1), normal plasma [HCO3-] (24 mEq/L), and normal PCO2 (40 mmHg):
pH = 6.1 + log (24 / [0.03 × 40]) = 6.1 + log (24 / 1.2) = 6.1 + log (20) = 6.1 + 1.30 = 7.40
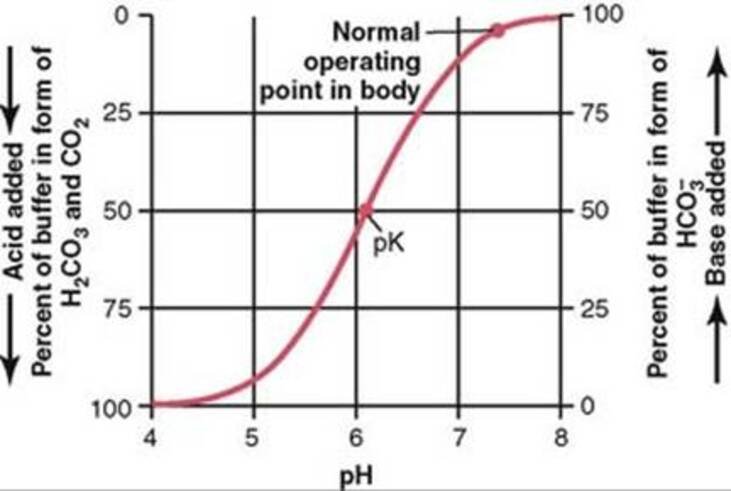
Respiratory Regulation of Acid-Base Balance
Metabolic processes generate approximately 1.2 mol/L of dissolved CO2 in ECF daily. Increases in alveolar ventilation blow off CO2, lowering arterial PCO2, which shifts the equilibrium to the left (↓ H+, ↑ pH). Conversely, hypoventilation retains CO2, increasing H+ concentration. The respiratory system acts as a rapid negative feedback controller of [H+] with an efficiency of 50% to 75%, providing 1 to 2 times the total buffering power of all chemical buffers in ECF combined.
Renal acid-base regulation
The kidneys regulate extracellular [H+] through three coordinated mechanisms: secretion of H+, reabsorption of filtered HCO3-, and generation of new HCO3-.
The Quantitative Challenge
- Filtered Bicarbonate Load: GFR (180 L/day) × Plasma [HCO3-] (24 mEq/L) = 4,320 mEq of HCO3- filtered per day. Under normal conditions, virtually all of this filtered load must be reabsorbed to prevent urinary base loss.
- Fixed Metabolic Acid Load: The body produces approximately 80 mEq of non-volatile (fixed) acids daily (mainly sulfuric and phosphoric acids derived from dietary protein catabolism).
- Total Daily H+ Secretion: To reabsorb 4,320 mEq of filtered HCO3- and excrete 80 mEq of fixed acid, the renal tubules must secrete a total of 4,400 mEq of H+ per day (4,320 + 80 = 4,400 mEq/day).
1. Bicarbonate Reabsorption Across the Nephron
- Proximal Convoluted Tubule: Reabsorbs ≈ 85% of filtered HCO3- (~3,670 mEq/day).
- Thick Ascending Limb of Henle: Reabsorbs ≈ 10% of filtered HCO3-.
- Distal Tubule & Collecting Duct: Reabsorbs remaining ≈ 5% of filtered HCO3-.
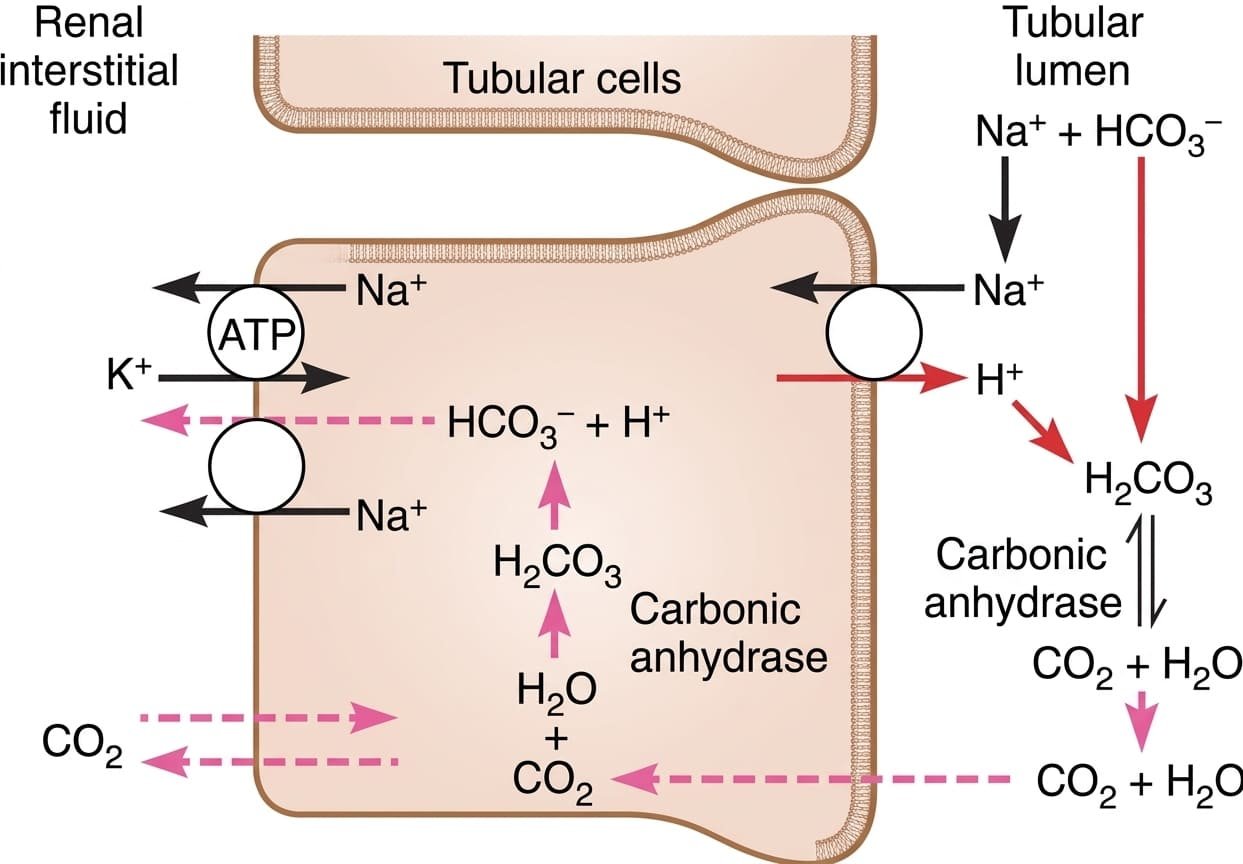
2. The Concept of Reciprocal Titration
Because filtered HCO3- cannot cross the luminal apical membrane directly, it must combine with secreted H+ to be converted to CO2. Thus, HCO3- and H+ titrate each other in the tubular lumen. For every H+ secreted, one HCO3- is reabsorbed into the peritubular capillary blood. In systemic alkalosis, filtered HCO3- exceeds secreted H+; excess HCO3- escapes reabsorption and is excreted in urine, restoring ECF pH. In systemic acidosis, secreted H+ exceeds filtered HCO3-; all filtered HCO3- is reabsorbed, and excess H+ must be buffered by non-bicarbonate urinary buffers.
Factors Regulating Tubular H+ Secretion
- Stimulators of H+ Secretion:
- Increased arterial PCO2 (respiratory acidosis).
- Increased extracellular [H+] / decreased blood pH (metabolic acidosis).
- Increased aldosterone: Directly stimulates apical H+-ATPase pumps in Type A intercalated cells and increases lumen negativity via ENaC in principal cells. (Hyperaldosteronism causes metabolic alkalosis).
- Hypokalemia (drives cellular H+ shift into tubular cells, accelerating H+ secretion).
- Inhibitors of H+ Secretion: Decreased PCO2, decreased extracellular [H+] (alkalosis), and hyperkalemia.
Titratable acid & ammonium buffering
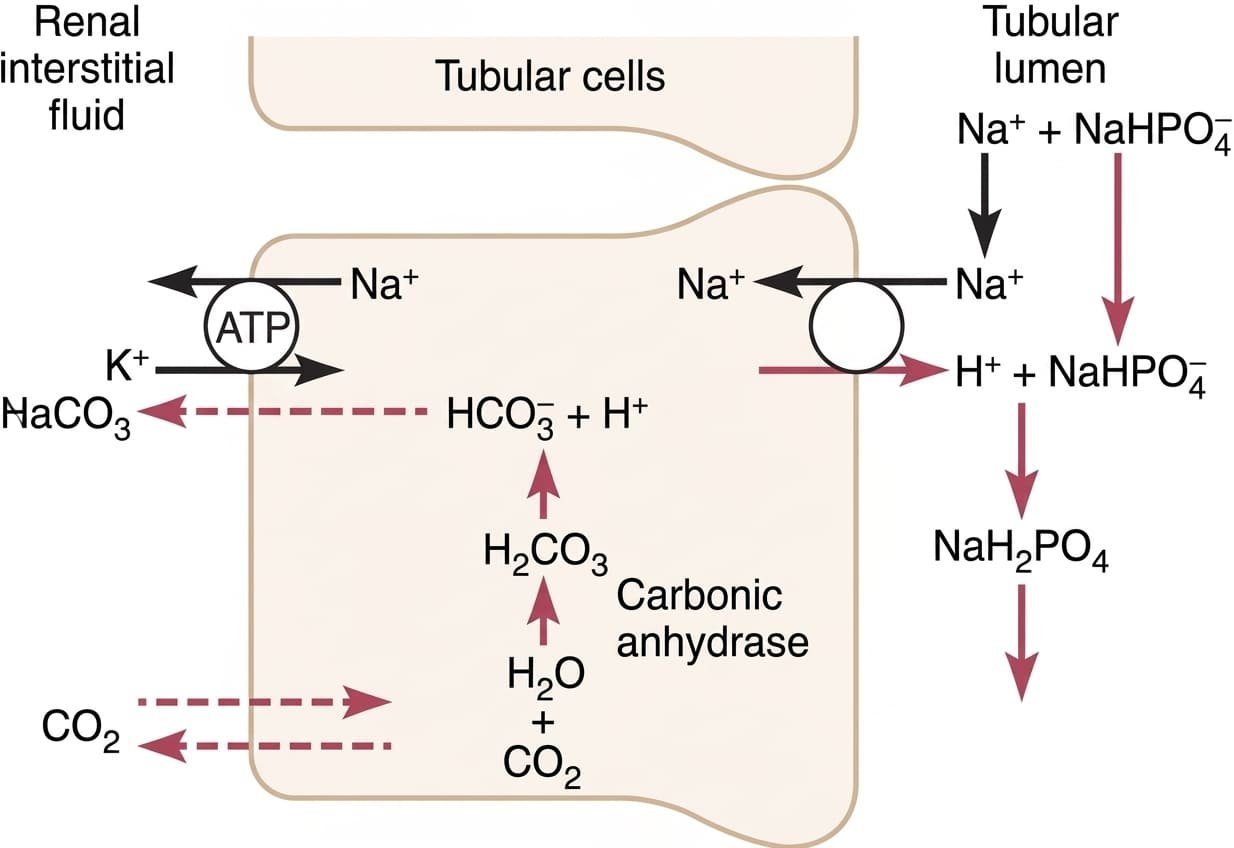
The minimal urine pH achievable by apical proton pumps is 4.5, which corresponds to a free [H+] of only 0.03 mEq/L. If the daily non-volatile acid load of 80 mEq were excreted as unbuffered free H+ in urine, it would require over 2,667 liters of urine per day (80 mEq / 0.03 mEq/L ≈ 2,667 L). To excrete this acid load in a normal 1.5 L daily urine volume, excess H+ must combine with non-bicarbonate buffers: the phosphate buffer (titratable acid) and the ammonia buffer system. In doing so, the kidneys generate new bicarbonate that is added to the blood.
1. The Phosphate Buffer System (Titratable Acid)
Filtered monohydrogen phosphate (HPO42-) is concentrated in the tubular lumen by upstream water reabsorption. As urine pH drops along the tubule, HPO42- accepts a secreted H+ to form dihydrogen phosphate (H2PO4-), which is excreted in the urine as a sodium salt (NaH2PO4).
2. The Ammonia-Ammonium Buffer System
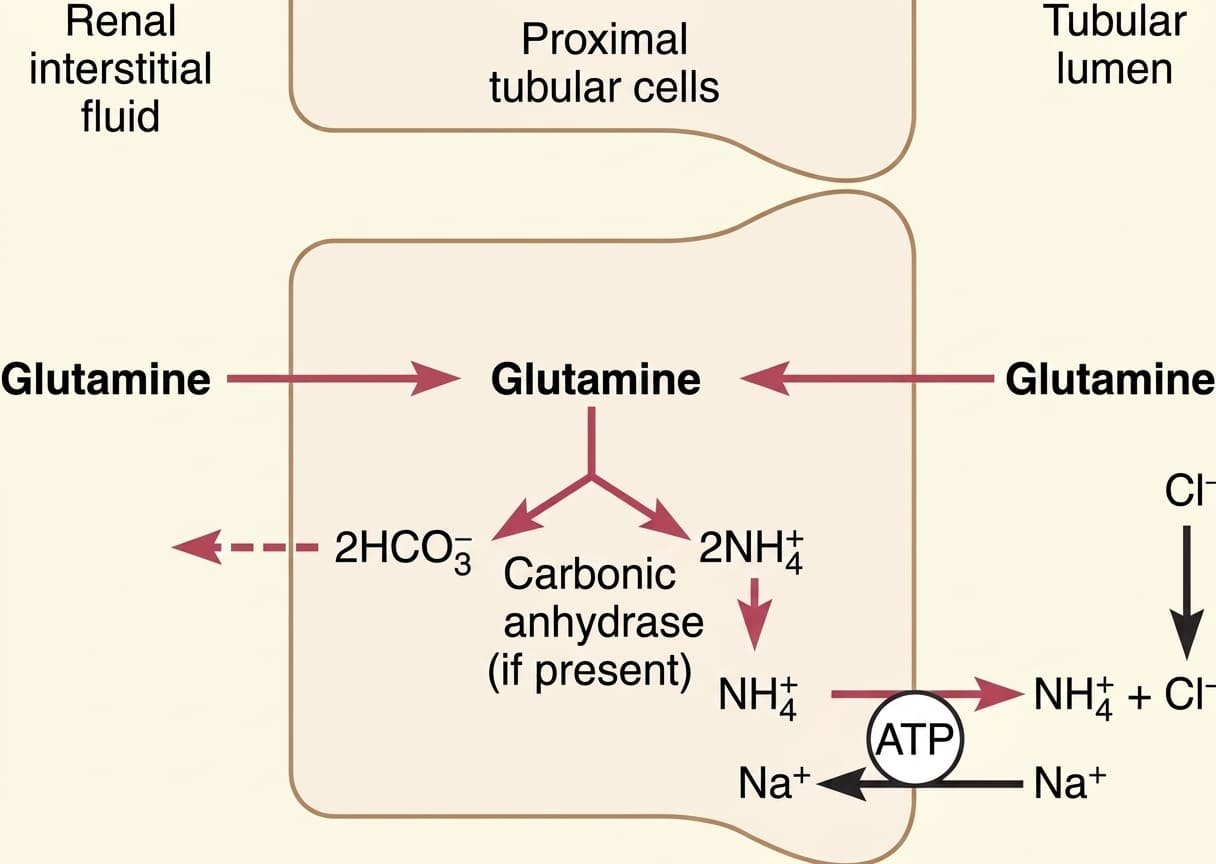
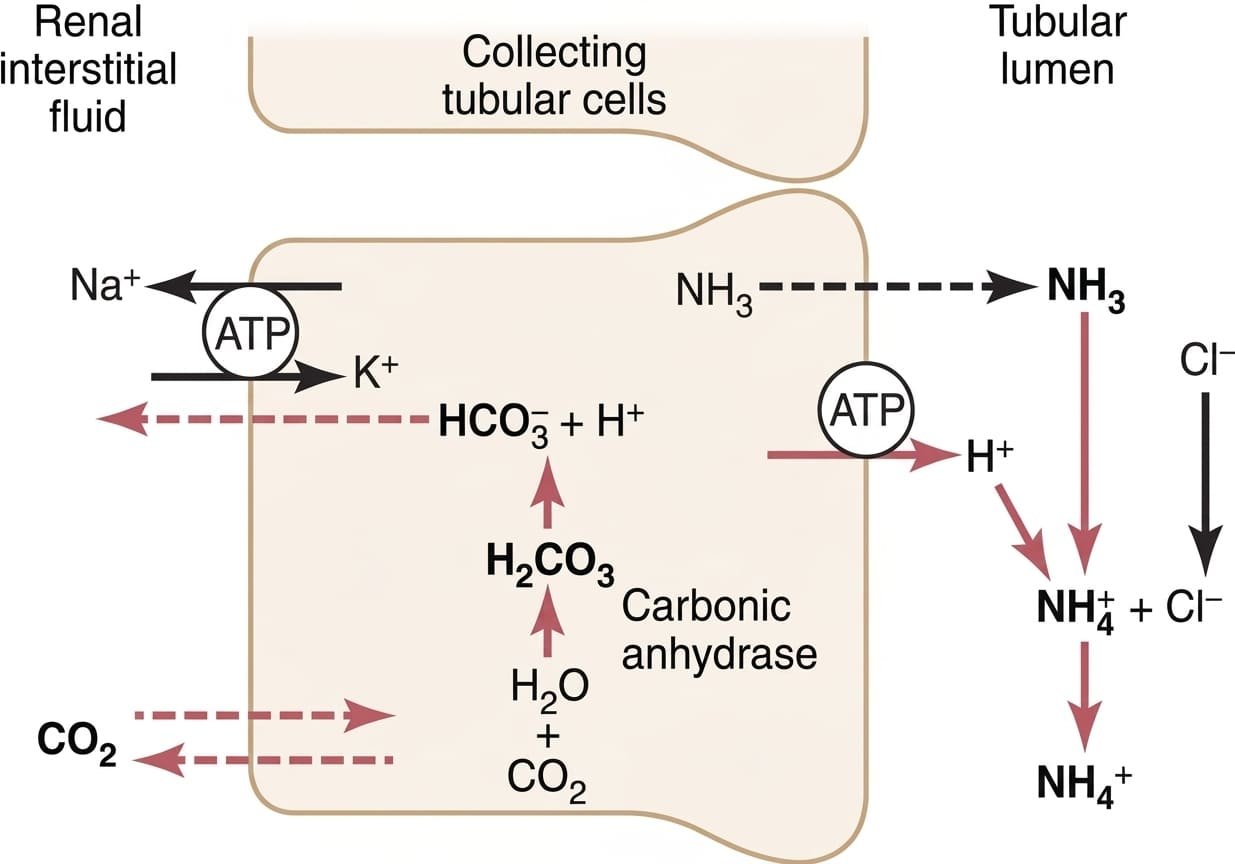
The ammonia buffer system is the primary physiological mechanism by which the kidneys eliminate fixed acid and synthesize new bicarbonate during chronic acidosis. It is composed of ammonia (NH3, gas/lipid soluble) and ammonium ion (NH4+, polar cation).
Adaptability in Chronic Acidosis
Under normal basal conditions, ammonium excretion accounts for ~40 to 50 mEq/day of acid excretion (~50% of fixed acid load). However, chronic acidosis transcriptionally induces renal glutaminase and glutamate dehydrogenase enzymes. Over several days, ammonium excretion can increase up to 500 mEq/day, representing the kidney's primary reserve defense against chronic metabolic acid challenges (e.g., diabetic ketoacidosis, chronic renal failure).
Primary acid-base disorders
Primary acid-base disturbances are classified as either metabolic (disturbances where the primary abnormality alters extracellular [HCO3-]) or respiratory (disturbances where the primary abnormality alters arterial PCO2). The body mounts compensatory responses via the opposite regulatory system to return the [HCO3-]/PCO2 ratio toward normal.
| Disturbance | pH / [H+] | Primary Disturbance | Compensatory Response | Common Clinical Causes |
|---|---|---|---|---|
| Respiratory Acidosis | pH ↓ (<7.35) [H+] ↑ (>45 nEq/L) |
PCO2 ↑↑ (>45 mmHg) (Alveolar hypoventilation) |
Renal: [HCO3-] ↑ ↑ Tubular H+ secretion, ↑ NH4+ excretion, ↑ new HCO3- generation |
COPD, severe asthma, opioid overdose, respiratory center depression, Guillain-Barré syndrome, flail chest |
| Metabolic Acidosis | pH ↓ (<7.35) [H+] ↑ (>45 nEq/L) |
[HCO3-] ↓↓ (<22 mEq/L) (Loss of base or acid accumulation) |
Respiratory: PCO2 ↓ Hyperventilation (Kussmaul breathing) blowing off volatile CO2 within minutes |
Diabetic ketoacidosis (DKA), lactic acidosis, severe diarrhea (loss of HCO3-), advanced chronic kidney disease, salicylate toxicity |
| Respiratory Alkalosis | pH ↑ (>7.45) [H+] ↓ (<35 nEq/L) |
PCO2 ↓↓ (<35 mmHg) (Alveolar hyperventilation) |
Renal: [HCO3-] ↓ ↓ Tubular H+ secretion, incomplete HCO3- reabsorption with urinary excretion of HCO3- |
High altitude (hypoxia-driven hyperventilation), psychogenic anxiety, pulmonary embolism, early sepsis, salicylate toxicity (central stimulation) |
| Metabolic Alkalosis | pH ↑ (>7.45) [H+] ↓ (<35 nEq/L) |
[HCO3-] ↑↑ (>26 mEq/L) (Loss of acid or base retention) |
Respiratory: PCO2 ↑ Hypoventilation to retain CO2 (limited by arterial hypoxemia); ↑ renal HCO3- excretion |
Severe vomiting / nasogastric suction (loss of HCl), loop/thiazide diuretic abuse, primary hyperaldosteronism (Conn’s syndrome), excessive antacid ingestion |
Renal clearance: GFR & RBF
Renal clearance (Cx) of a substance is the virtual volume of plasma that is completely freed (cleared) of that substance by the kidneys per unit time (expressed in mL/min). It is calculated using the urine flow rate (V), urinary concentration (Ux), and arterial plasma concentration (Px):
The Renal Clearance Equation
Excretion Rate = Ux × V
Cx = (Ux × V) / Px
- Ux: Concentration of substance X in urine (mg/mL).
- V: Urine flow rate (mL/min).
- Px: Concentration of substance X in systemic plasma (mg/mL).
Measurement of Glomerular Filtration Rate (GFR)
A substance can be used to measure GFR if it meets the following physiological criteria: it must be freely filtered across the glomerular barrier; must be neither reabsorbed nor secreted by the renal tubules; must not be synthesized, metabolized, or stored by the kidneys; and must be physiologically non-toxic and biologically inert.
- Inulin Clearance (Gold Standard): Inulin is an uncharged exogenous fructose polysaccharide (MW ≈ 5,200 Da) that meets all the criteria of an ideal filtration marker. The amount filtered per unit time (Pin × GFR) equals the amount excreted per unit time (Uin × V):
GFR = (Uin × V) / Pin = Cinulin ≈ 125 mL/min.
Because inulin requires a continuous intravenous infusion and serial blood sampling, its use is largely restricted to research settings. - Endogenous Creatinine Clearance: Creatinine is an endogenous by-product of skeletal muscle creatine metabolism produced at a relatively constant rate. It is freely filtered at the glomerulus, is not reabsorbed, but undergoes a small degree of active tubular secretion in the proximal tubule (~10% to 20%). Consequently, creatinine clearance slightly overestimates true GFR:
Ccreatinine = (Ucr × V) / Pcr ≈ 95 to 140 mL/min.
Despite this, serum creatinine concentration ([Pcr]) serves as a routine clinical surrogate for GFR: because production is relatively steady, if GFR drops by 50%, serum creatinine doubles.
Measurement of Effective Renal Plasma Flow (ERPF) & RBF
- Para-Aminohippuric Acid (PAH) Clearance: PAH is an organic anion that is both freely filtered (~20%) and actively secreted by proximal tubule OAT transporters (~80%). At low plasma concentrations, virtually all PAH entering the renal circulation is cleared in a single trans-renal passage (extraction ratio, EPAH ≈ 0.90). Therefore, the clearance of PAH provides an accurate measurement of effective renal plasma flow (ERPF):
ERPF = CPAH = (UPAH × V) / PPAH ≈ 585 to 650 mL/min.
True Total Renal Plasma Flow (RPF) = CPAH / EPAH = 585 / 0.90 ≈ 650 mL/min. - Calculating Total Renal Blood Flow (RBF): Utilizing RPF and the patient’s systemic hematocrit (Hct):
RBF = RPF / (1 − Hematocrit).
Assuming a hematocrit of 0.45: RBF = 650 / (1 − 0.45) = 650 / 0.55 ≈ 1180 to 1200 mL/min.
Endocrine & metabolic actions
The kidneys function as primary endocrine organs, producing hormones that regulate systemic erythropoiesis, blood pressure, and bone mineral balance.
1. Erythropoietin (EPO) Secretion
- Site of Synthesis: Approximately 90% of all erythropoietin is produced by specialized peritubular interstitial capillary endothelial and fibroblast-like cells within the deep renal cortex and outer medulla. The remaining 10% is synthesized by hepatocytes in the liver.
- Stimulus for Secretion: Decreased tissue oxygen tension (hypoxia caused by anemia, high altitude, hypoxemia, or renal artery stenosis). Hypoxia stabilizes hypoxia-inducible factors (HIF-1α, HIF-2α), driving transcription of the EPO gene.
- Biological Mechanism: EPO circulates to the red bone marrow, binding surface EPO receptors on committed erythroid progenitors (CFU-E). It rescues proerythroblasts from programmed apoptosis, accelerating erythroblastic differentiation into mature circulating red blood cells.
- Clinical Correlate: In advanced Chronic Kidney Disease (CKD), parenchymal fibrosis destroys peritubular interstitial cells, causing severe normocytic normochromic anemia due to EPO deficiency (treated clinically with recombinant human erythropoietin / darbepoetin alfa).
2. Activation of Vitamin D (Calcitriol Synthesis)
The kidneys execute the final, rate-limiting enzymatic activation step in the systemic synthesis of the active steroid hormone vitamin D:
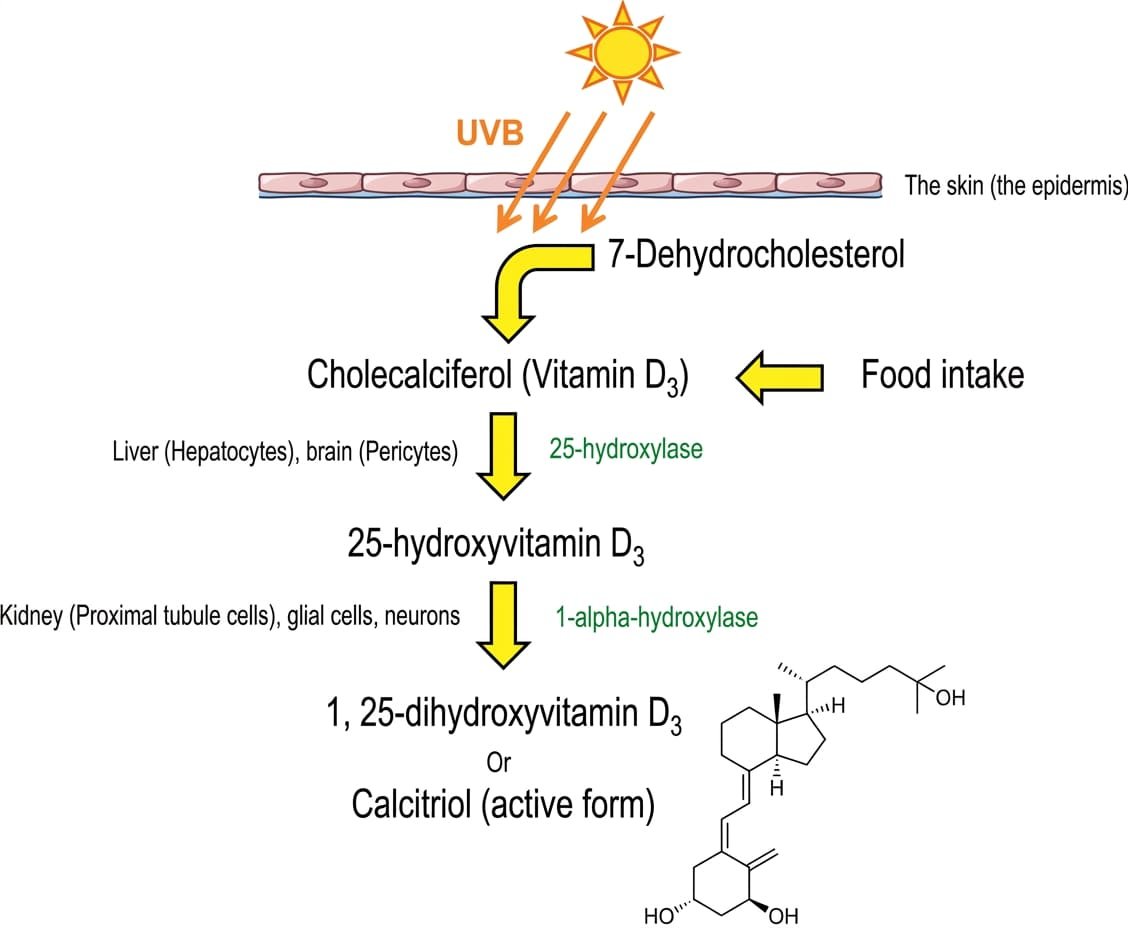
Calcitriol Regulation & Target Organ Effects
- Enzymatic Regulation: Renal mitochondrial 1α-hydroxylase (CYP27B1) is transcriptionally stimulated by parathyroid hormone (PTH) and hypophosphatemia, and feedback-inhibited by high calcium, high calcitriol, and fibroblast growth factor 23 (FGF-23).
- Intestinal Calcium & Phosphate Uptake: Calcitriol enters intestinal enterocytes, binding nuclear vitamin D receptors (VDR) to induce synthesis of apical TRPV6 calcium channels, intracellular calbindin-D9k, and basolateral PMCA calcium extrusion pumps, increasing intestinal Ca2+ and PO43- absorption.
- Renal Tubular Effects: Promotes renal tubular Ca2+ reabsorption in distal tubules, and modulates proximal tubular phosphate handling.
- Clinical Correlate: In CKD, loss of functional proximal tubular mass impairs 1α-hydroxylase activity, leading to calcitriol deficiency, hypocalcemia, hyperphosphatemia, and secondary hyperparathyroidism (renal osteodystrophy).
Quick recap
References
The following authoritative medical physiology reference texts support this curriculum study note:
- Guyton and Hall: Hall, J.E. and Hall, M.E. (2021) Guyton and Hall Textbook of Medical Physiology. 14th edn. Philadelphia: Elsevier. [Chapter 26: Renal Functional Anatomy; Chapter 27: Glomerular Filtration; Chapter 28: Tubular Processing; Chapter 29: Urine Concentration and Dilution; Chapter 30: Regulation of Potassium and Acid-Base Balance].
- Ganong’s Review of Medical Physiology: Barrett, K.E., Barman, S.M., Brooks, V.L. and Yuan, J.X.J. (2019) Ganong’s Review of Medical Physiology. 26th edn. New York: McGraw-Hill Education. [Section VII: Renal Physiology; Chapters 37–39].
- Koeppen & Stanton’s Renal Physiology: Koeppen, B.M. and Stanton, B.A. (2018) Renal Physiology. 6th edn. Philadelphia: Elsevier Mosby. [Chapters 1–8: Physiology of Body Fluids, Glomerular Filtration, Tubular Transport, and Acid-Base Balance].
- Vander’s Renal Physiology: Eaton, D.C. and Pooler, J.P. (2018) Vander’s Renal Physiology. 9th edn. New York: McGraw-Hill Education. [Chapters 1–10: Elements of Renal Function, Clearance, and Regulation of Water and Electrolytes].