
Comprehensive Immunology: Host Defense, Cellular Communication, Phagocytosis, and Adaptive Immunity
On this page 18 sections
Foundations of Immunology
1. The Dual Architecture of Host Defense: Innate versus Adaptive Immunity
The human immune system organizes its protective responses across two cooperative functional arms: the immediate, non-tailored innate immune system and the highly specialized, delayed adaptive immune system.
| Feature | Innate Immunity (First Line) | Adaptive Immunity (Specialized Line) |
|---|---|---|
| Speed of Response | Rapid; operates within minutes to hours after exposure. | Delayed; requires several days to develop and mature during primary exposure. |
| Target Specificity | Non-specific; responds against common microbial signatures identically across different invaders. | Highly specific; precision-tailored to unique individual antigens. |
| Immunological Memory | Absent; repeat challenge generates the exact same baseline response intensity. | Present; creates long-lasting memory cells producing faster and stronger secondary responses. |
| Primary Elements | Physical barriers (skin, mucosa), chemical shields (gastric acid, lysozymes), phagocytes (macrophages, neutrophils), natural killer cells, complement cascade, and cytokines. | B lymphocytes (humoral immunity via antibodies) and T lymphocytes (cell-mediated immunity via CD4+ helper and CD8+ cytotoxic T cells). |
2. Hematopoiesis, Stem Cells, and Leukocyte Classification
Immune cells constantly travel throughout the body using blood and lymphatic vessels. While these cells reside in normal circulating blood, their absolute counts rise rapidly during infection.
The primary reservoir and birthplace for these cells is the bone marrow. All mature blood elements arise from immature precursors known as hematopoietic stem cells (HSCs) through the regulated process of hematopoiesis.
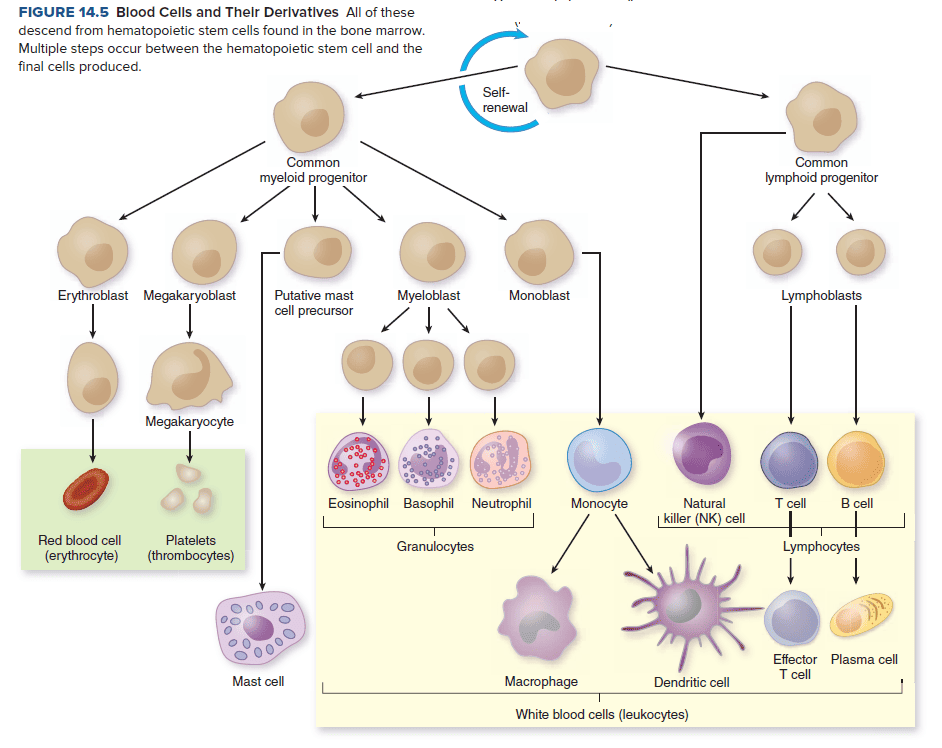
| Cell Class | Cell Type (% Circulating Leukocytes) | Primary Tissue Location | Core Functional Role |
|---|---|---|---|
| Granulocytes (Contain fluid-filled, chemically active cytoplasmic granules) |
Neutrophils (55% to 65%) Also termed PMNs, polymorphonuclear leukocytes, or polys |
Mainly circulating in blood; sparse in healthy tissues, but migrate quickly in large numbers during inflammation. Bone marrow holds large reserve pools. | Professional phagocytes functioning as the body's rapid response team. They arrive first at tissue damage sites, exhibit very high killing capacity, and have a short functional lifespan of 1 to 2 days. |
| Eosinophils (2% to 4%) | Low numbers in circulation; most enter mucosal tissues and reside near local secretions. | Involved in allergic reactions and defense against parasitic worms. Granules contain antimicrobial compounds and the enzyme histaminase (which breaks down histamine). | |
| Basophils (0% to 1%) & Mast Cells | Basophils circulate in blood; mast cells reside within peripheral connective tissues near vessels and mucosal boundaries. | Key players in allergic reactions and acute inflammation. Their granules release vasoactive mediators like histamine to boost capillary permeability. (Note: while they share similar appearance and functions, they represent distinct cell lineages). | |
| Mononuclear Phagocyte System (MPS) | Monocytes (3% to 8%) | Circulate within blood vessels following release from bone marrow. | Precursor cells that travel through blood and enter injured or infected tissues, where they differentiate into active tissue macrophages or dendritic cells. |
| Macrophages | Present in almost all tissues (abundant in spleen, lungs, liver, lymph nodes, and peritoneal cavity). Named according to their home tissue. | Professional tissue sentinels and scavengers. They clear daily cell debris, phagocytose pathogens, produce cytokines, regenerate their lysosomes to sustain killing, and live for weeks to months. | |
| Dendritic Cells | Originate in tissues, then travel to secondary lymphoid organs (lymph nodes, spleen, appendix, tonsils). | Highly motile, phagocytic cells during early life. They capture antigens in peripheral tissues and migrate to lymphoid organs to present them to lymphocytes. | |
| Lymphocytes | B Cells, T Cells, and Natural Killer (NK) Cells (25% to 35%) | Abundant in secondary lymphoid organs (lymph nodes, spleen, mucosal-associated lymphoid tissue) and constantly recirculate through blood and lymph. | Primary mediators of adaptive immunity. B cells differentiate into antibody-producing plasma cells; T cells direct responses and destroy infected host cells; NK cells eliminate virus-infected and malignant cells. |
3. Primary and Secondary Lymphoid Organs
| Organ Category | Anatomical Sites Included | Physiological Role |
|---|---|---|
| Primary (Central) Lymphoid Organs |
|
Sites where lymphocytes are generated from stem cells and mature into immunocompetent cells without prior foreign antigen stimulation. |
| Secondary (Peripheral) Lymphoid Organs |
|
Sites where mature lymphocytes encounter trapped antigens and antigen-presenting cells to launch active adaptive immune responses. |
4. Cellular Communication: Receptors, Cytokines, and Adhesion Molecules
Leukocytes must communicate clearly with one another and with local endothelial tissues to coordinate defense responses. They exchange information using three main tools:
| Cytokine Class | Representative Factor | Cellular Source | Physiological & Immune Action |
|---|---|---|---|
| Chemokines | Chemokines (chemotactic cytokines) | Various tissue and immune cells | Guide directional movement (chemotaxis) of leukocytes toward sites of infection or tissue damage. |
| Colony-Stimulating Factors (CSFs) | CSFs | Various immune and stromal cells | Promote bone marrow stem cells to grow and differentiate into mature leukocytes. |
| Interferons (IFNs) | Interferon alpha (IFN-α) | Leukocytes | Blocks viral replication in neighboring cells (antiviral defense). |
| Interferon beta (IFN-β) | Fibroblasts | Provides antiviral protection in non-immune connective tissues. | |
| Interferon gamma (IFN-γ) | T lymphocytes and Natural Killer (NK) cells | Strongly activates macrophages and directs adaptive immune pathways. | |
| Interleukins (ILs) | IL-1 | Macrophages and epithelial cells | Stimulates T cells and macrophages; triggers inflammatory responses and fever. |
| IL-2 | T cells | Drives T-cell growth and clonal expansion. | |
| IL-4 | T cells and mast cells | Encourages B-cell antibody production and class switching. | |
| IL-6 | T lymphocytes and macrophages | Promotes T- and B-cell growth; drives acute inflammation and systemic fever. | |
| Tumor Necrosis Factor (TNF) | TNF-α | Macrophages, T cells, and Natural Killer cells | Drives local inflammation, kills certain tumor cells, triggers liver acute-phase proteins, and coordinates immune responses. |
5. Pattern Recognition: Toll-Like Receptors (TLRs)
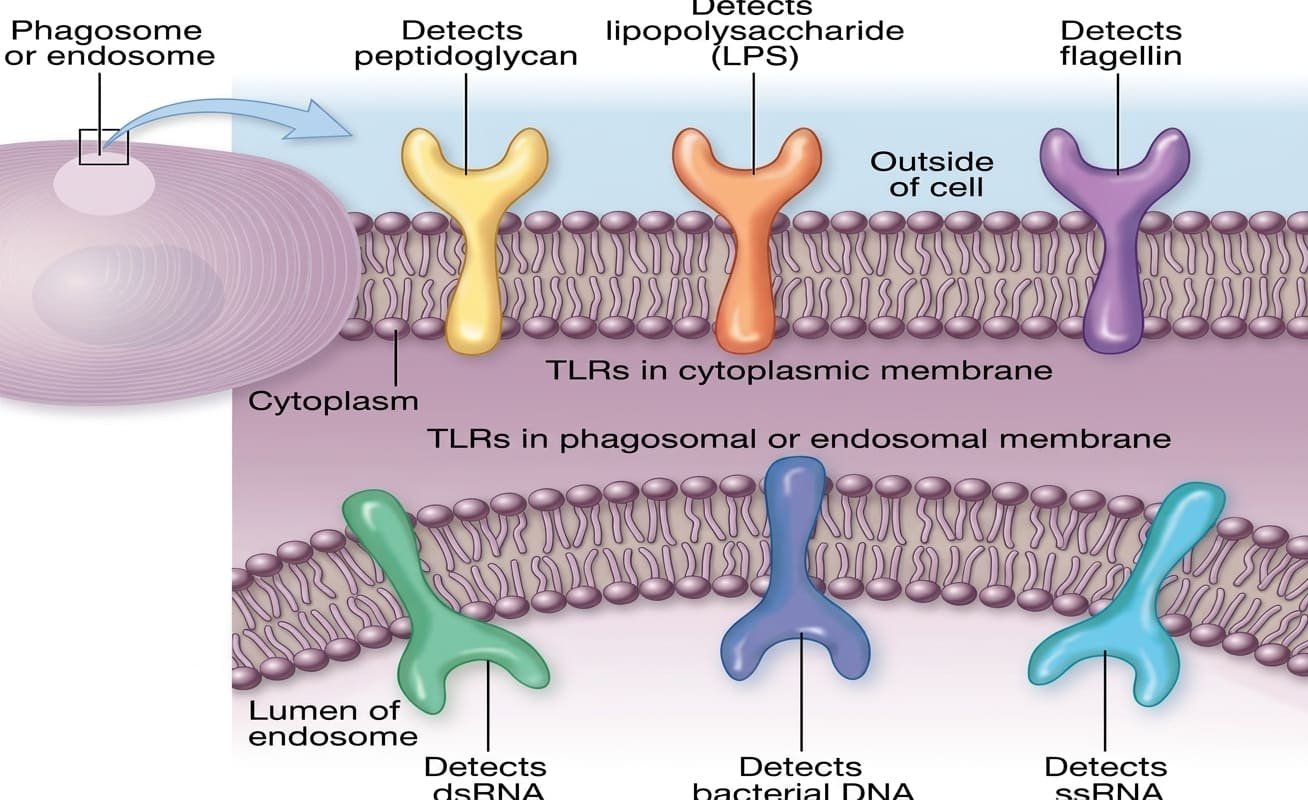
Sentinels must spot microbial invaders early. They rely on Toll-like receptors (TLRs), a family of more than 10 distinct pattern-recognition receptors. Each TLR detects a specific microbial molecule or shared pathogen pattern.
6. The Complement Cascade: Triggers, Pathways, and Biological Outcomes
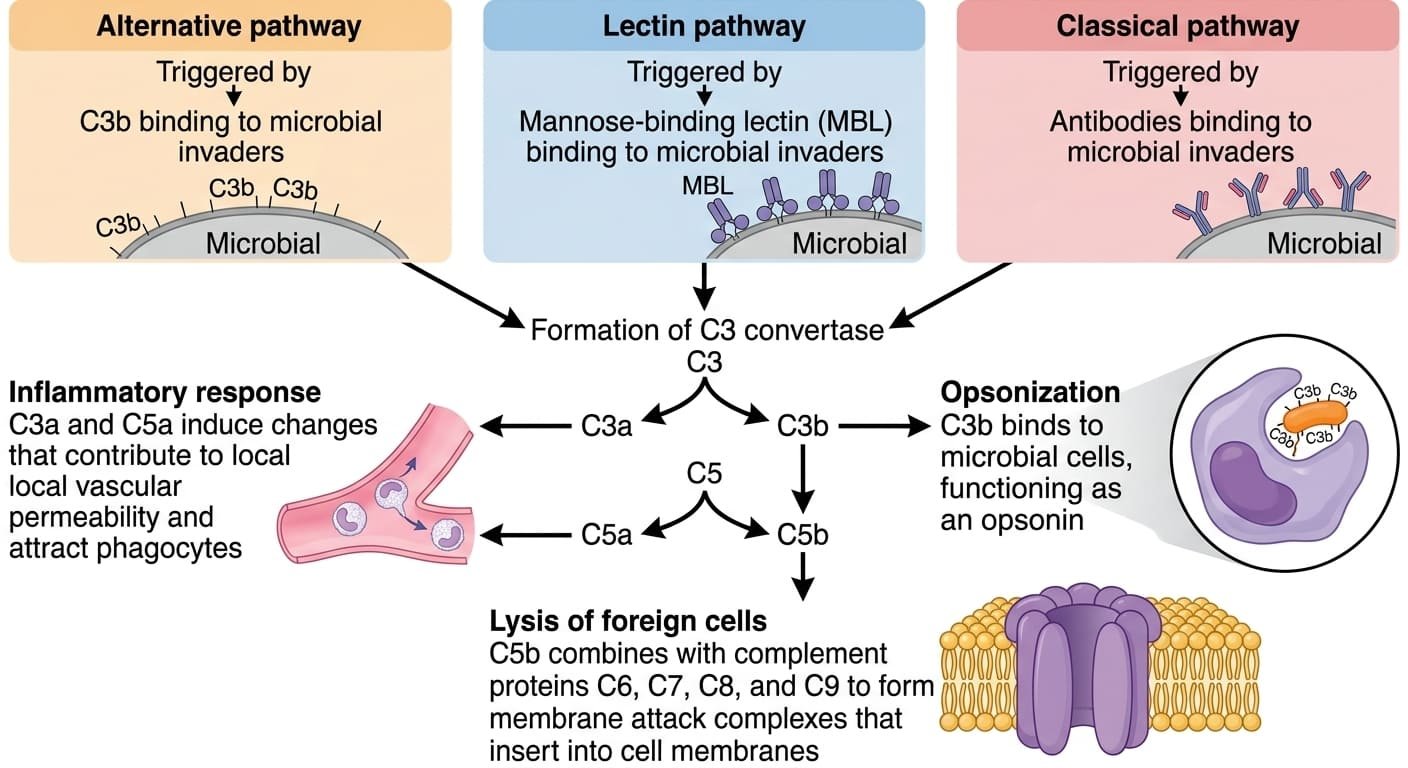
The complement system consists of nine major circulating proteins, designated C1 through C9. These proteins circulate in an inactive form within blood and tissue fluids. When triggered by foreign substances, they activate in a rapid, sequential enzymatic cascade.
| Complement Pathway | Triggering Stimulus | Initial Biochemical Assembly |
|---|---|---|
| Alternative Pathway | Spontaneous activation; complement fragment C3b binds directly to foreign microbial surfaces. | C3b deposits directly on the foreign cell wall without needing antibodies. |
| Lectin Pathway | Soluble host pattern-recognition protein called mannose-binding lectin (MBL) binds mannose sugars on microbial invaders. | MBL attaches to repeating carbohydrates on bacterial or fungal surfaces. |
| Classical Pathway | Specific antibodies bind to foreign antigens, forming immune complexes. | Antibody stems expose binding sites that recruit and activate the C1 complex. |
| Biological Outcome | Key Complement Mediators | Detailed Physiological Mechanism |
|---|---|---|
| 1. Induction of Inflammation | C3a and C5a (Often termed anaphylatoxins) |
These fragments bind receptors on blood vessel endothelial cells and mast cells, increasing vascular permeability. C5a also serves as a potent chemoattractant that draws flowing phagocytes toward the activation site. C3a and C5a also stimulate phagocyte metabolism and increase their surface C3b receptors. |
| 2. Opsonization | C3b | C3b coats foreign microbial surfaces, acting as a molecular tag (opsonin). Phagocytes carry specific surface C3b receptors that let them easily grip and ingest the coated microbe. |
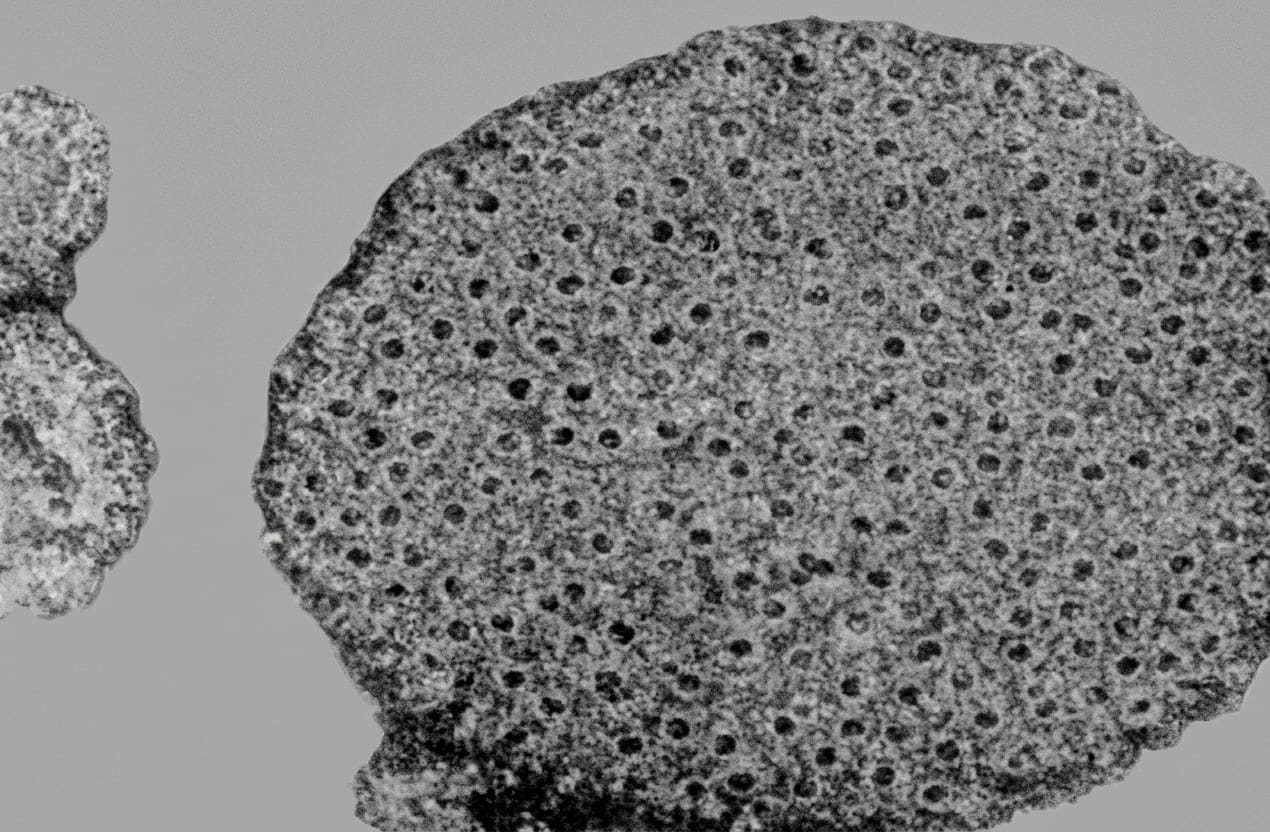
| 3. Cell Lysis via MAC | C5b, C6, C7, C8, and multiple C9 molecules | Fragment C5b binds the target membrane and recruits C6, C7, and C8. This complex drives the assembly of multiple C9 units into a doughnut-shaped pore called the Membrane Attack Complex (MAC). These pores disrupt membrane integrity, leading to cell lysis. |
7. The Inflammatory Response: Mechanisms, Vascular Changes, and Phagocyte Recruitment
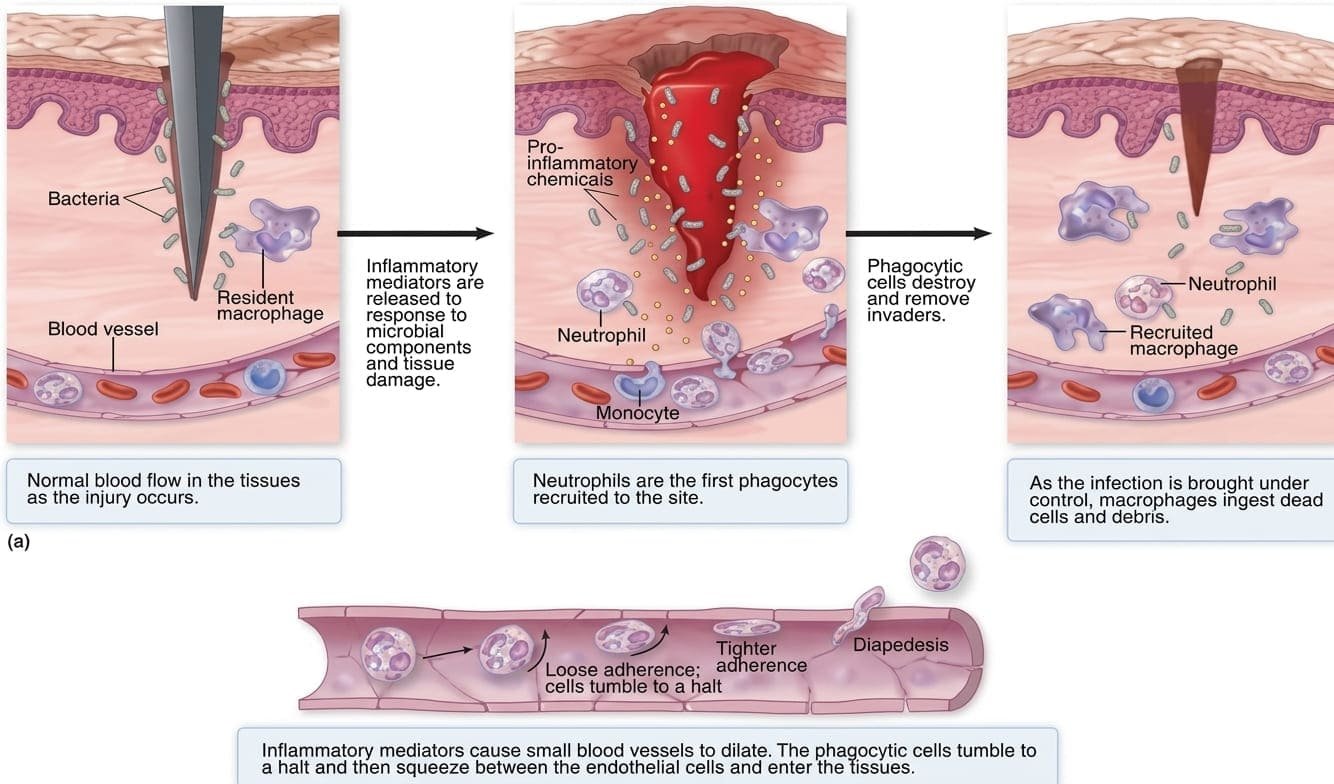
Inflammation is a coordinated response to tissue damage or microbial invasion. Injuries caused by penetrating objects or microbial toxins trigger local defenses designed to isolate the injury, eliminate invaders, and restore tissue function.
| Initiating Event | Molecular Mediators Involved | Downstream Inflammatory Effect |
|---|---|---|
| 1. Microbial Molecular Products | Microbial flagellin, LPS, and bacterial DNA binding macrophage TLRs | Macrophages release pro-inflammatory cytokines such as TNF-α. TNF-α stimulates hepatocytes in the liver to synthesize acute-phase proteins, which enhance complement activation and phagocytosis. |
| 2. Microbial Surface Activation of Complement | Generation of complement split products C3a and C5a | Directly trigger mast cell degranulation, releasing histamine and pro-inflammatory cytokines that increase vascular permeability. |
| 3. Physical Tissue Injury | Activation of enzymatic cascades:
|
Prevents blood loss, blocks microbial spread through the body, and triggers localized pain and vascular widening. |
8. The Multistep Leukocyte Extravasation Cascade
Phagocytes travel quickly through normal blood vessels. To reach infected tissues, they complete a coordinated sequence of recruitment steps:
9. Resolution, Chronic Inflammation, and Systemic Complications
| Stage / Outcome | Dominant Cells & Structures | Pathological Process & Clinical Features |
|---|---|---|
| Acute Inflammation & Pus Formation | Neutrophils (PMNs), fibrin clots, and tissue debris | Short-term, localized response starting right after injury. Clotting factors seal the wound and trap pathogens. As short-lived neutrophils die in large numbers, their remains mix with cellular debris to form pus. A localized collection of pus forms a boil or abscess. During normal healing, new capillaries grow into the site, damaged tissue is replaced, and a scar forms. |
| Chronic Inflammation & Granulomas | Macrophages, Multinucleated Giant Cells, T-helper cells | Develops when acute inflammation fails to clear an infection. This response can persist for months or years. If activated macrophages cannot digest the pathogen, many macrophages fuse together to form multinucleated giant cells. Macrophages, giant cells, and helper T cells then form tight clusters called granulomas. Granulomas wall off pathogens to keep them from spreading. This illustrates cooperation between innate and adaptive defenses, and is a hallmark of diseases like tuberculosis and histoplasmosis. |
| Host Tissue Damage | Degranulating phagocytes releasing reactive chemicals | Activated phagocytes can release toxic oxygen radicals and digestive enzymes into surrounding tissues. This response can become life-threatening in enclosed, delicate spaces like the meninges of the brain and spinal cord. |
| Septic Shock | Systemic monocytes, macrophages, and endothelial cells | Occurs when Gram-negative bacteria enter the bloodstream and release massive amounts of endotoxin (lipopolysaccharide / LPS). This triggers widespread cytokine release, leading to profound systemic vasodilation, a precipitous drop in blood pressure, widespread capillary microclotting, hypoperfusion, and extensive tissue necrosis. |
10. Cellular Specialization: Macrophages versus Neutrophils
| Comparative Parameter | Tissue Macrophage | Circulating Neutrophil (PMN) |
|---|---|---|
| Normal Physiological Role | Tissue sentinel and scavenger; phagocytoses debris and dead cells; monitors for danger; calls for reinforcements. | Circulating rapid responder; sparse in healthy tissues; rapidly recruited to damage sites. |
| Arrival Timeline | Already resident within tissues; additional cells recruited after the initial neutrophil wave. | First leukocyte recruited from the blood to arrive at damaged or infected tissue. |
| Lifespan & Lysosome Renewal | Long-lived (weeks to months); continuously regenerates lysosomes to maintain killing activity. | Short-lived (1 to 2 days); dies after degranulating and phagocytosing targets. |
| Intrinsic Killing Power | Moderate at baseline; killing capacity increases significantly when activated. | Naturally high baseline killing power, exceeding that of resting and activated macrophages. |
| Activation & Tissue Toxicity | Stimulated by T-helper cell signals (like IFN-γ) to become activated macrophages. They produce large amounts of oxygen radicals and nitric oxide. Because these chemicals damage host tissues, macrophages cannot safely remain activated indefinitely. | Releases enzymes from cytoplasmic granules and uses reactive oxygen bursts to rapidly destroy microbes. |
11. The Six Sequential Steps of Phagocytosis
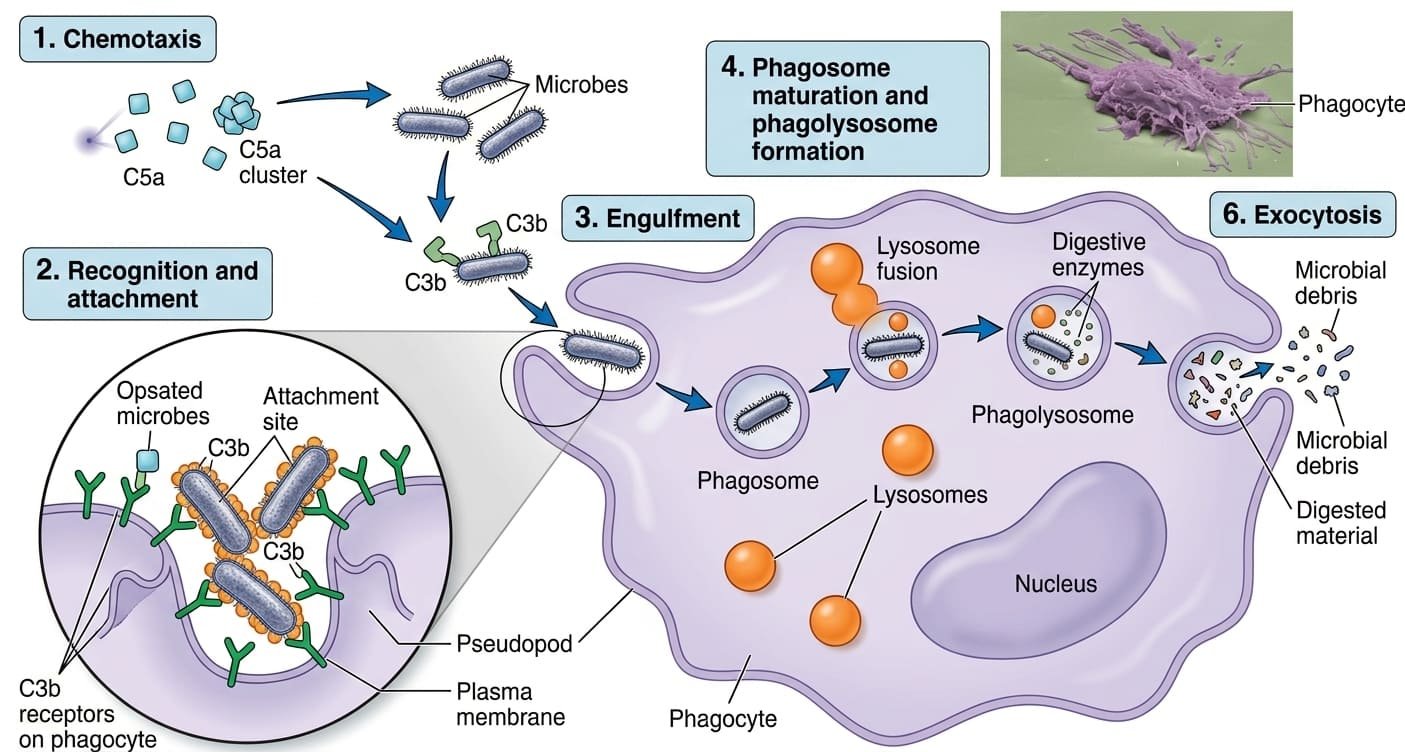
Phagocytosis is the process by which specialized cells engulf, kill, and digest foreign microorganisms and cellular debris. Understanding each step is clinically important because many pathogens have developed ways to block specific stages of this pathway.
12. Adaptive Immunity: Humoral Defense and B Lymphocytes
Humoral immunity is carried out by B lymphocytes (B cells), which develop and mature in the bone marrow. This arm protects mainly against extracellular pathogens, such as bacteria and toxins in the blood and lymph.
13. Antibody Structure and Functional Protection Mechanisms
Antibodies (immunoglobulins) are Y-shaped proteins that bind specific foreign antigens.
| Structural Component | Molecular Characteristics | Functional Activity |
|---|---|---|
| Two Identical Arms (Fab Regions) | Formed by variable amino acid sequences that differ widely among antibody clones. | Provide high antigen-binding specificity. The unique tip shapes let each antibody bind exclusively to its matching target antigen. |
| Stem Region (Fc Region) | Constant amino acid sequence shared within each immunoglobulin class. | Acts as a "red flag" tag. When the arms bind an antigen, the stem recruits and activates other immune components (such as complement proteins and phagocyte Fc receptors) to destroy the target. |
14. Adaptive Immunity: Cell-Mediated Defense and T Lymphocytes
Cell-mediated immunity is driven by T lymphocytes (T cells), which develop in the bone marrow and mature within the thymus. This arm targets intracellular pathogens (such as viruses and intracellular bacteria) as well as aberrant host cancer cells. (Note: T cells do not secrete antibodies).
| T-Cell Subpopulation | Core Functional Role | Effector Mechanisms and Actions |
|---|---|---|
| Helper T Cells (CD4+) | Often called the "Generals" of the immune system. | Coordinate broad immune responses by releasing cytokines. They do not directly kill infected cells. Instead, their cytokines activate B cells, stimulate cytotoxic T cells, and activate macrophages to enhance their killing capacity. |
| Cytotoxic T Cells (CD8+) | Often called the "Assassins" of the immune system. | Directly bind and destroy host cells that harbor intracellular viruses, intracellular bacteria, or cancerous mutations. |
15. Intracellular Surveillance, Apoptosis, and Autoimmunity
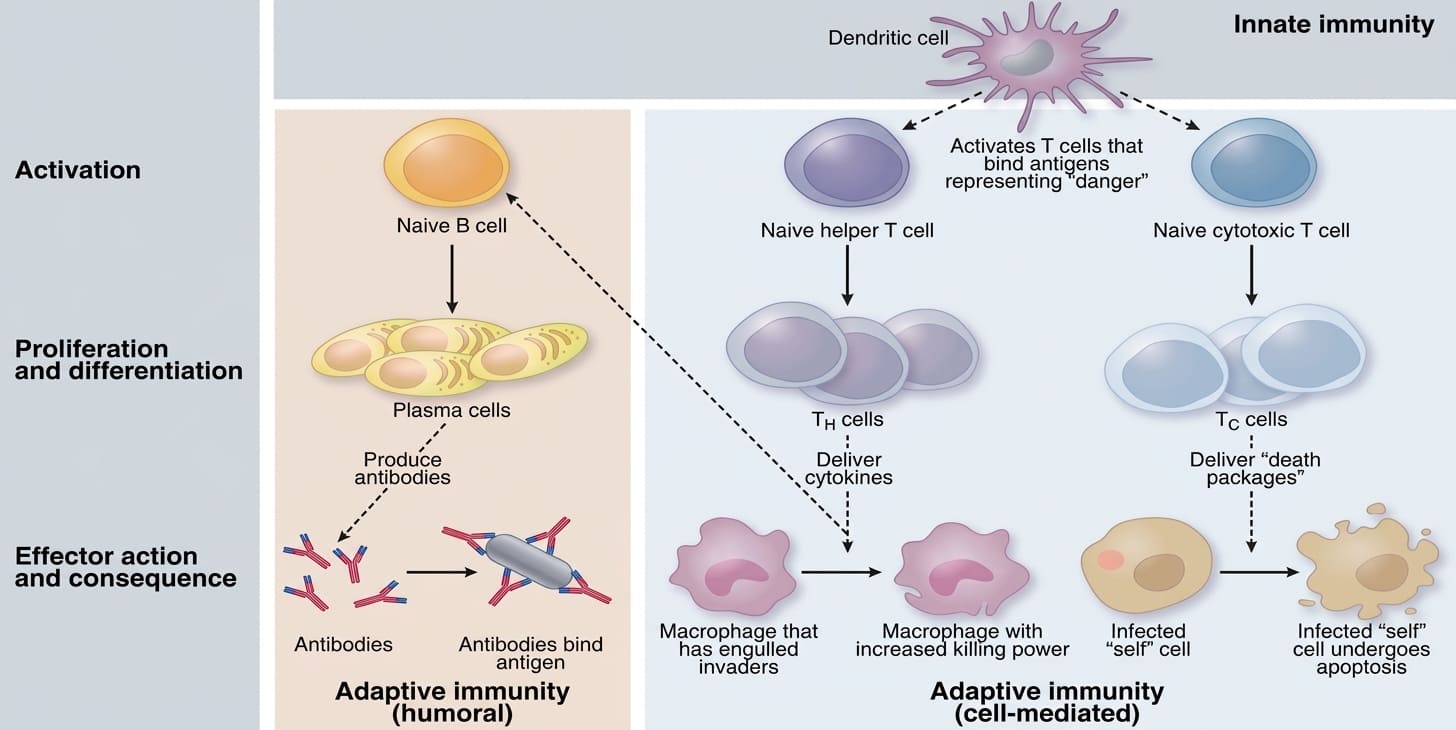
Because cytotoxic T cells kill host cells, the body uses strict quality control mechanisms to target only infected or abnormal cells while sparing healthy tissue.
16. Clinical Applications and Pathological Correlations
| Clinical Discipline | Representative Conditions / Therapies | Core Immunological Connection |
|---|---|---|
| Vaccinology | Preventive and therapeutic vaccines | Introduces harmless antigens to stimulate primary adaptive immunity, generating protective memory B and T cells without causing full disease. |
| Allergy & Asthma | Hypersensitivity reactions, allergic asthma, anaphylaxis | Occurs when the immune system mounts inappropriate, exaggerated responses against harmless environmental antigens, driven by IgE, basophils, eosinophils, and mast cells. |
| Autoimmunity | Type 1 Diabetes Mellitus, Rheumatoid Arthritis, Multiple Sclerosis (MS) | Develops when self-tolerance fails and adaptive lymphocytes attack healthy host tissues. |
| Immunodeficiency | Acquired: HIV/AIDS; Congenital: Severe Combined Immunodeficiency (SCID) | Weakened immune components leave the patient vulnerable to frequent, severe opportunistic infections. |
| Cancer Immunotherapy | CAR-T cell therapy, immune checkpoint inhibitors | Harnesses and reprograms the patient's own cytotoxic T cells to overcome tumor suppression and destroy cancer cells. |
| Transplantation Medicine | Solid organ and bone marrow grafting | Uses targeted immunosuppression to prevent recipient T cells and antibodies from recognizing donor tissue antigens and rejecting the graft. |
Further Reading
These resources provide reliable background reading on immune-system structure, innate and adaptive immunity, inflammation, phagocytosis, and clinical immunology.