
Gram-Negative Bacteria: Neisseria, Enterobacterales, Vibrio, Campylobacter and Helicobacter
On this page
Overview
The gram-negative wall — and why it matters clinically
- Outer membrane: LPS (endotoxin) in the outer leaflet — fever, shock, DIC when released in sepsis; porin proteins control nutrient entry and exclude antibiotics.
- Periplasmic space: β-lactamases (including extended-spectrum ESBLs and carbapenemases) sit here and destroy penicillins/cephalosporins before they reach their targets — a major resistance engine in Uganda's referral hospitals.
- Clinical consequences: gram-negative bacteraemia with shock is a medical emergency (early fluids, antibiotics within the first hour); drug choice often needs broader agents (third-generation cephalosporins, carbapenems, aminoglycosides — per culture and local policy).
Neisseria (diplococci)
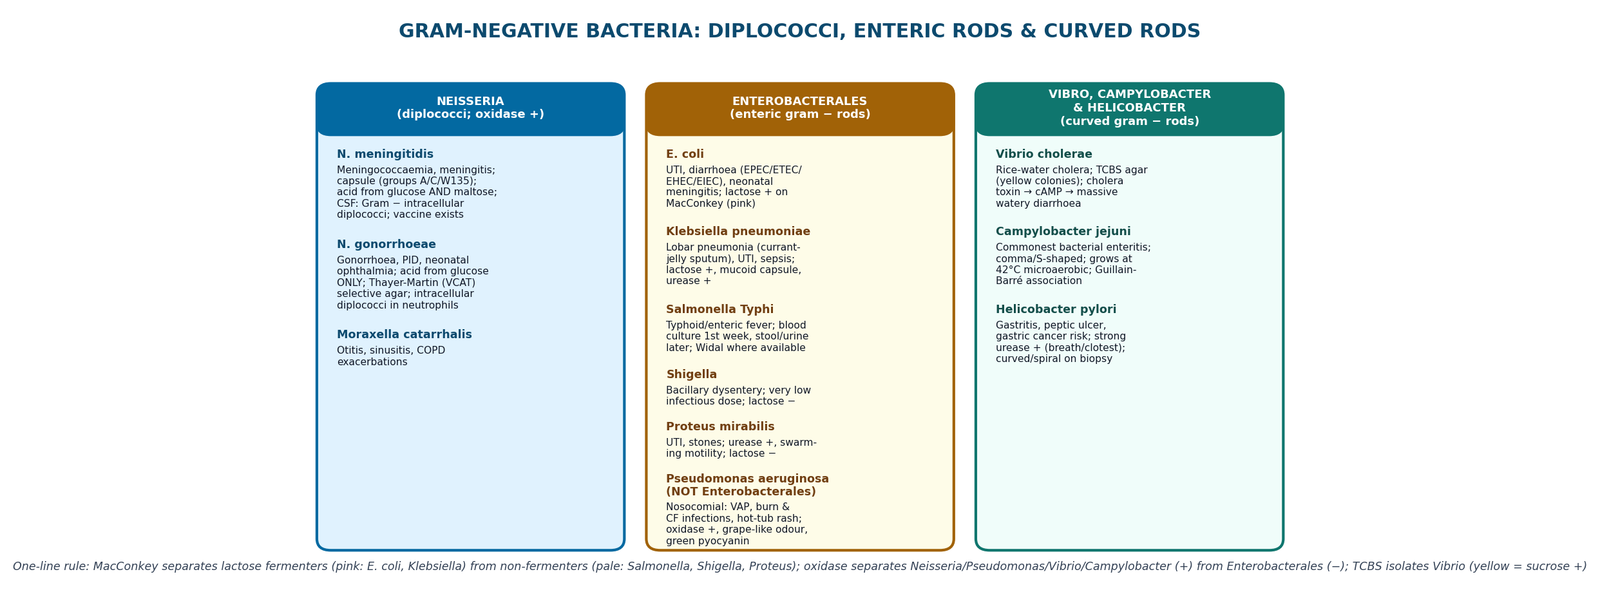
Kidney-shaped (coffee-bean) gram-negative diplococci, oxidase positive, fastidious — they need chocolate agar (lysed RBCs release factor V/X nutrients) and 5–10% CO₂. The selective medium is Thayer-Martin (chocolate agar + vancomycin, colistin, amphotericin B/ nystatin, trimethoprim — the "VCAT" antibiotics suppress normal flora from genital specimens).
Scroll the table sideways on a smaller screen.
| Feature | N. meningitidis (meningococcus) | N. gonorrhoeae (gonococcus) |
|---|---|---|
| Disease | Meningitis, meningococcaemia (non-blanching petechiae/purpura, shock, Waterhouse–Friderichsen adrenal haemorrhage); epidemic in crowded settings ("meningitis belt" of Africa) | Gonorrhoea (urethral/cervical discharge, epididymitis, PID, tubal infertility); neonatal conjunctival ophthalmia; disseminated gonococcaemia (arthritis–dermatitis) |
| Virulence factors | Polysaccharide capsule (groups A, C, W135, Y — vaccine targets), LPS (endotoxin → purpura/shock), IgA protease, pili | Pili (antigenic variation → repeat infection), Opa proteins, IgA protease, LPS |
| Specimen & microscopy | CSF: gram-negative intracellular diplococci within neutrophils; skin aspirate in fulminant disease; blood cultures | Urethral smear: intracellular gram-negative diplococci (diagnostic in symptomatic men); culture or NAAT for women and extra-urethral sites |
| Sugar fermentation | Acid from glucose AND maltose | Acid from glucose ONLY (not maltose) |
| Prevention | Conjugate vaccines (A, C, W, Y) — routine childhood/reactive campaigns in Uganda; chemoprophylaxis for close contacts (ciprofloxacin/rifampicin per protocol) | Safe sex, condoms, treating partners; neonatal eye prophylaxis (silver nitrate/erythromycin) where practised; syndromic treatment per national STI guidelines |
Moraxella catarrhalis (also oxidase-positive gram-negative diplococcus) is the third member to know: otitis media, sinusitis and acute exacerbations of COPD — reliably β-lactamase positive.
Enterobacterales: the enteric rods
Facultative anaerobic gram-negative rods of the gut. The workhorse medium is MacConkey agar: it selects gram-negatives (bile salts + crystal violet inhibit gram-positives) and differentiates by lactose fermentation — lactose fermenters = pink colonies (E. coli, Klebsiella); non-fermenters = pale (Salmonella, Shigella, Proteus).
Scroll the table sideways on a smaller screen.
| Organism | MacConkey / key tests | Signature diseases | Exam points |
|---|---|---|---|
| Escherichia coli | Lactose + (pink), indole +, oxidase − | UTI (commonest cause), neonatal sepsis/meningitis, intra-abdominal sepsis; diarrhoeagenic pathotypes: ETEC (traveller's diarrhoea, heat-labile/stable toxins), EPEC (infant diarrhoea), EHEC O157 (bloody diarrhoea, HUS — antibiotics may worsen), EIEC (dysentery-like) | The laboratory's "workhorse" organism; uropathogenic strains have fimbrial adhesins; K1 capsule in neonatal meningitis strains |
| Klebsiella pneumoniae | Lactose +, mucoid colonies, urease +, non-motile, citrate + | Lobar pneumonia in alcoholism/diabetes ("currant-jelly" sputum), UTI, hospital sepsis | Thick polysaccharide capsule → mucoid growth and phagocytosis resistance; a classic ESBL/carbapenemase carrier in hospitals |
| Salmonella enterica (Typhi & non-typhoidal) | Non-lactose (pale), H₂S + (black on XLD/SS agar), motile | Typhoid/enteric fever (stepwise fever, relative bradycardia, rose spots, leucopenia, constipation then diarrhoea); NTS: gastroenteritis, invasive disease (HIV, sickle cell, malnourished children) | Culture by week: blood 1st week → stool/urine later (bone marrow most sensitive); chronic gallbladder carriage; Widal test where culture unavailable (limited accuracy) |
| Shigella (S. dysenteriae, flexneri…) | Non-lactose, non-motile, no H₂S | Bacillary dysentery (fever, cramp, small-volume bloody mucoid stools, tenesmus) | Extremely low infectious dose (10–200 organisms) → person-to-person and food-borne spread; S. dysenteriae type 1 produces Shiga toxin (HUS risk) |
| Proteus mirabilis | Non-lactose, urease strongly +, "swarming" motility on blood agar, phenylalanine deaminase + | UTI (especially with stones/struvite), wound infection | Urease splits urea → ammonia → alkaline urine → struvite stones |
| Enterobacter, Citrobacter, Serratia | Variable lactose | Nosocomial sepsis, ventilator pneumonia | "SPICE" group — inducible AmpC β-lactamase resistance (may report cephalosporin-sensitive yet become resistant on therapy) |
Curved and spiral rods: Vibrio, Campylobacter, Helicobacter
Scroll the table sideways on a smaller screen.
| Organism | Disease & mechanism | Diagnosis |
|---|---|---|
| Vibrio cholerae | Cholera: cholera toxin (CT) permanently activates adenylyl cyclase → cAMP → massive Cl⁻ and water secretion → "rice-water" stools, litres of fluid loss/hour, hypovolaemic death within hours if untreated; treatment is rehydration (ORS/IV), doxycycline or azithromycin shortens illness | TCBS agar: bright yellow colonies (sucrose fermenter; high pH and bile salts select against others); oxidase +; comma-shaped on stain; RDTs for outbreak screening |
| Campylobacter jejuni | The commonest bacterial enteritis worldwide: inflammatory diarrhoea ± blood, fever, cramps; usually self-limiting; macrolides for severe disease; post-infection Guillain–Barré syndrome (molecular mimicry of gangliosides) and reactive arthritis | Grows at 42°C, microaerobic, on selective (Skirrow/CCDA) media; S-shaped/"seagull" rods on Gram stain; oxidase +, catalase + |
| Helicobacter pylori | Chronic gastritis → peptic ulcer disease → gastric adenocarcinoma and MALT lymphoma risk; urease neutralises gastric acid; corkscrew motility burrows through mucus | Urease is the diagnostic handle: rapid urease (CLO) test on gastric biopsy, urea breath test, stool antigen; spiral/curved rods on special stain; treat with PPI + clarithromycin + amoxicillin (or metronidazole) combinations per guideline |
Pseudomonas and friends (oxidase-positive non-fermenters)
Pseudomonas aeruginosa is not an Enterobacterale — it is an oxidase-positive, non-lactose-fermenting rod that produces a grape-like odour and diffusible pigments (pyocyanin — blue-green). It barely grows at 37°C-unless... — it grows almost anywhere (including disinfectant solutions) and infects the vulnerable: burn wounds, ventilator-associated pneumonia, catheter sepsis, malignant otitis externa in diabetics, hot-tub folliculitis, chronic lung colonisation in cystic fibrosis. It is naturally resistant to many antibiotics (porin exclusion + efflux) — treat with antipseudomonal β-lactams (piperacillin-tazobactam, ceftazidime, cefepime, carbapenems) ± aminoglycoside per susceptibility. Acinetobacter baumannii ("Iraqibacter") and Stenotrophomonas complete the picture of difficult hospital gram-negatives.
Laboratory identification summary
Clinical scenarios
Scenario 1 — Purpura and shock in a boarding student
A 17-year-old in a crowded school dormitory develops fever, headache and a non-blanching petechial rash spreading to purpura, with cold peripheries and a dropping blood pressure. You recognise meningococcaemia with septic shock — a minutes-to-hours emergency: immediate IV ceftriaxone (do not wait for the LP if the patient is unstable), aggressive fluid resuscitation, check for adrenal haemorrhage (Waterhouse–Friderichsen), and notify public health for contact chemoprophylaxis (ciprofloxacin or rifampicin per protocol) and vaccination campaign assessment — meningococcus exploits exactly this crowding.
Scenario 2 — The dysentery differential on the ward
A 4-year-old has fever, cramping and frequent small bloody mucoid stools with tenesmus. Your stool microscopy shows pus cells and RBCs but no amoebae; the differential is Shigella vs amoebic vs EHEC dysentery. You send stool culture (MacConkey/XLD) and RDTs; because shigellosis needs almost no organisms to spread, you isolate the child's stool hygiene at home and treat per national dysentery guidance (e.g. ciprofloxacin or azithromycin per current susceptibility data) while reviewing daily. You note the danger of casual quinolone use driving resistance — culture first when the child is stable enough.
Scenario 3 — Rice-water stools at the cholera treatment centre
During a lakeshore outbreak, a previously well adult passes litres of clear watery stool with flecks of mucus ("rice-water"), without fever or cramps. You start ORS immediately — rehydration is the treatment that saves lives; antibiotics are secondary — and give a single dose of doxycycline (azithromycin in pregnancy/children) to shorten shedding. A stool RDT is positive for cholera; the lab confirms yellow colonies on TCBS. You report to the district, reinforce water chlorination and handwashing, and remember: cholera is a water-and-sanitation disease with a toxin as its weapon.
Key points
References
- Medical Microbiology (Baron, ed.), NCBI Bookshelf — Neisseria and Enterobacteriaceae chapters (Library reference.)
- WHO Manual for Laboratory Identification and AST of Bacterial Pathogens of Public Health Importance in the Developing World (Library reference.)
- Jawetz, Melnick & Adelberg's Medical Microbiology (Library reference.)
- Uganda Clinical Guidelines 2023 — meningitis, dysentery, cholera and STI chapters (Library reference.)
- CDC resources: meningococcal disease, gonorrhoea, cholera, Campylobacter (Library reference.)
Further reading
For deeper study, compare this lesson with current guidance and standard references from recognised medical and scientific organisations.
- WHO laboratory manual for bacterial pathogens of public-health importance
- CDC — infectious disease resources
- Uganda MoH Knowledge Management Portal (UCG 2023)
- Clinical Medicine Year 1, Semester 2 curriculum
For education only. Syndromic and definitive treatment follow the Uganda Clinical Guidelines and current national antimicrobial policy; suspected outbreaks require immediate notification.