Attitude formation and change (Persuasion theory, Cognitive dissonance)
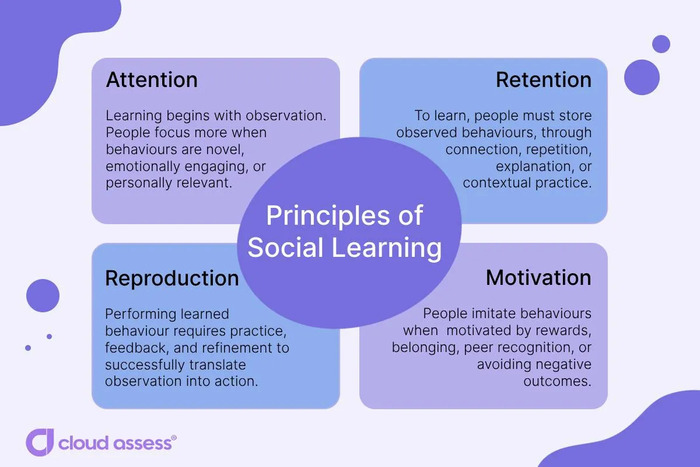
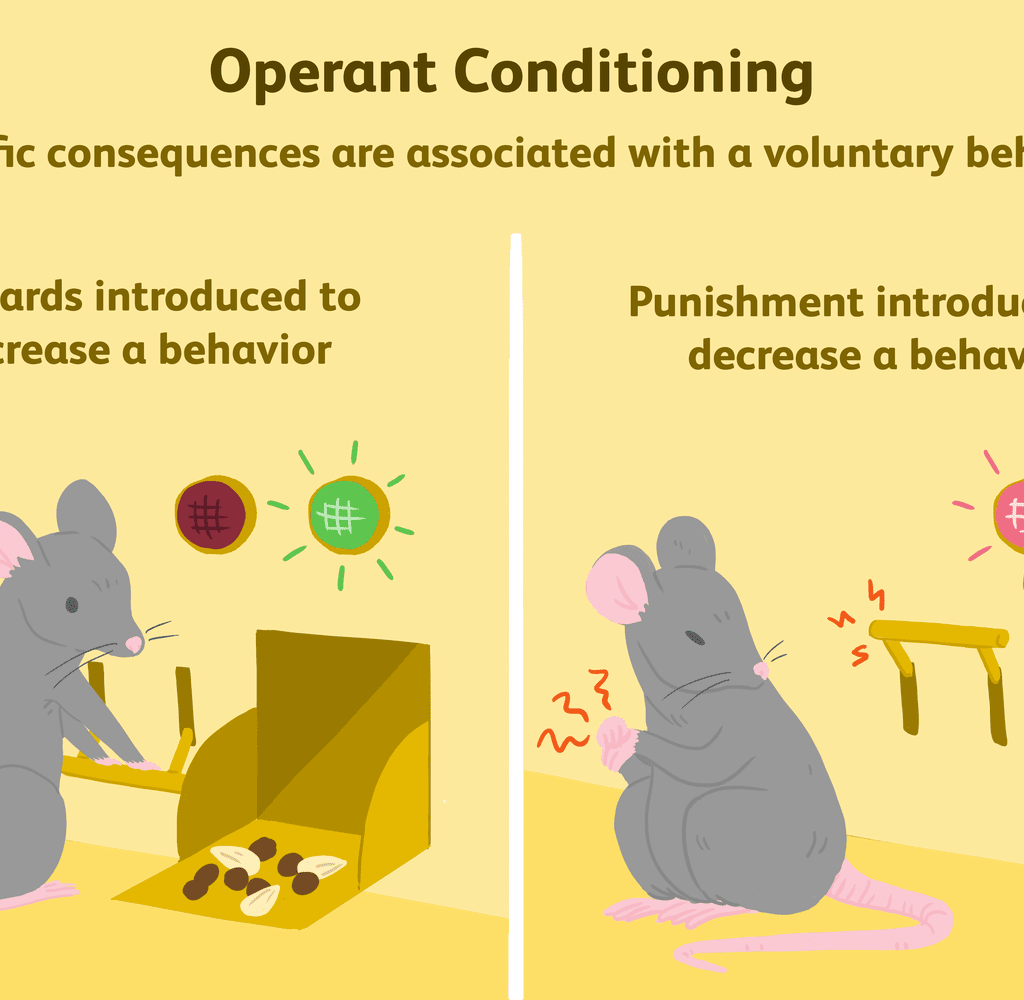
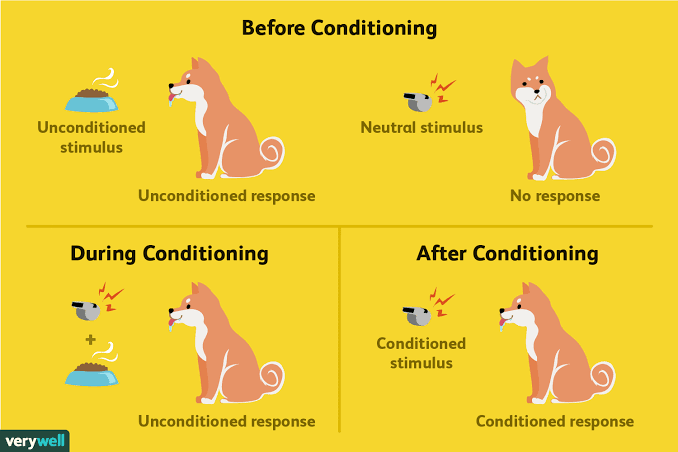
Attitude Formation and Change: Persuasion Theory and Cognitive Dissonance A comprehensive study of how attitudes are acquired, the mechanisms of persuasion via the Yale approach and Elaboration Likelihood Model, and the psychological impact of cognitive dissonance on behavior change in healthcare. 1. How Attitudes Are Formed Attitudes are learned; none is inborn. They are acquired gradually through the interaction of the individual with the environment and are continuously shaped, strengthened, or modified by experience. Sources of Attitudes Family and early socialisation: The first and most powerful source; parents transmit attitudes toward food, health, authority, religion, and other groups. Early attitudes tend to be enduring (law of primacy). Peers and reference groups: Friends, classmates, and workmates strongly shape attitudes, especially in adolescence, through conformity and group norms. Culture, religion, and community: Shared values of the cultural group define which attitudes are acceptable; stigma and prejudice are often culturally transmitted. Mass media and social media: Television, radio, films, and the internet model behaviours and present repeated evaluations of issues, celebrities, products, and health practices. Personal experience: Direct experience with an object forms strong attitudes — e.g., a bad hospital experience creates a lasting negative attitude toward hospitals. Learning processes: Classical conditioning: Pairing objects with pleasant/unpleasant events. Operant conditioning: Attitudes reinforced by approval or reward. Observational learning: Imitating models, especially admired ones. Mere exposure effect: Repeated presentation of a neutral object, even without reward, tends to make it more liked — familiarity breeds acceptance. Biological factors: Temperament and genetic variation modestly influence attitude formation through personality, but the content of attitudes is overwhelmingly learned. Key Point Strong attitudes are formed by direct personal experience, early learning, and association with important values; weak attitudes are formed by hearsay and media alone. 2. Persuasion Theory Persuasion is a deliberate attempt to change an attitude (and thereby behaviour) through the transmission of a message. The Yale Approach (Hovland et al., 1950s) This model analyses persuasion as “who says what to whom with what effect.” Four groups of factors determine whether a message changes an attitude: Factor What makes persuasion more effective What weakens persuasion Source (Who communicates) High credibility (expertise, trustworthiness); attractiveness and likability; similarity to the receiver. Low credibility; perceived bias, vested interest, or ulterior motive. Message (What is communicated) Clear, logical, well-organised; moderate two-sided arguments; strong but not extreme fear appeal with a recommended action. Confusing or exaggerated messages; extreme positions; fear without a solution. Channel (How it is communicated) Face-to-face for emotional/personal issues; mass media for wide reach; multiple channels together. Single, inappropriate channel (e.g., complex statistics on radio). Receiver (To whom) Receivers with low initial involvement, moderate self-esteem, younger age; messages matched to beliefs. High prior knowledge; strong opposing attitudes; strong counter-arguing. 2.1 The Elaboration Likelihood Model (ELM) Petty and Cacioppo (1986) explained persuasion through two routes, depending on how motivated and able the receiver is to think about the message: Central route: The receiver carefully processes the arguments (high motivation and ability). Result: attitudes are strong, durable, and predictive of behaviour. Used when the issue is personally relevant. Peripheral route: The receiver relies on superficial cues — the speaker’s attractiveness or status, slogans, emotions, crowd behaviour — without thinking deeply (low motivation or ability). Result: attitudes are weak, temporary, and easily changed again. Key Point For lasting health-behaviour change, aim for central-route persuasion: make the issue personally relevant, give clear evidence, and help the receiver think through the arguments — peripheral cues (posters, slogans) alone rarely change durable behaviour. 2.2 Fear Appeals Fear-arousing messages (e.g., graphic warnings about smoking, HIV, or road accidents) can change attitudes, but only under specific conditions: the message must arouse moderate fear, provide a specific, achievable recommended action, and convince the receiver that the action will avert the threat (response efficacy) and that they can perform it (self-efficacy). Extreme terror without a workable solution is usually dismissed (“fear control”) rather than acted on (“danger control”). 2.3 Resistance to Persuasion Forewarning: Advance notice of a persuasive attempt allows counter-argument preparation and reduces its effect. Inoculation (McGuire): Prior exposure to weak, refutable versions of opposing arguments — like vaccination — builds resistance to later, stronger persuasion; used in anti-smoking and anti-misinformation programs. Reactance: Messages perceived as threatening freedom provoke the opposite attitude — e.g., a coercive “you must” campaign can harden resistance. 3. Cognitive Dissonance Theory Leon Festinger (1957) proposed that people strive for consistency among their cognitions (thoughts, beliefs, knowledge, attitudes) and between cognition and behaviour. When two cognitions conflict, or behaviour contradicts an attitude, an uncomfortable state of tension called cognitive dissonance arises, which motivates the person to reduce it. A cognition is any piece of knowledge — a belief, opinion, or fact about oneself, behaviour, or the environment. Consonant cognitions are consistent with one another; dissonant cognitions are inconsistent and produce psychological discomfort (anxiety, guilt, unease). Example: A person who smokes (behaviour) and who believes smoking causes cancer (cognition) experiences dissonance. 3.1 Magnitude of Dissonance Dissonance is stronger when the cognitions involved are important to the self, when the dissonant cognition is highly valued, and when there are few consonant cognitions resisting change. Dissonance always increases immediately after a decision (post-decision dissonance — doubts about the rejected option) and after insufficient justification, forced compliance, or effortful actions that produce weak rewards. 3.2 Ways of Reducing Dissonance Strategy Mechanism Example (smoking) Change the behaviour Act in line with the cognition Stop smoking Change the attitude/cognition Reinterpret or deny the conflicting belief “The evidence on smoking is not conclusive.” Add consonant cognitions Introduce new beliefs that support the behaviour “Smoking relaxes me; stress kills too.” Reduce the importance of the dissonant cognition Minimise its significance “Everything causes cancer nowadays.” Reduce perceived choice Convince oneself the behaviour was unavoidable “I smoke because of my stressful job.” 3.3 Classic Supporting Evidence Festinger and Carlsmith (1959): Participants who performed a boring task and then told the next person it was interesting for only $1 (insufficient justification) later rated the task as more enjoyable than those paid $20 — the