
Anti-Amoebic and Other Antiprotozoal Agents: Metronidazole, Diloxanide and the Luminal Partners
On this page
Overview
Core concept: tissue vs lumen infection
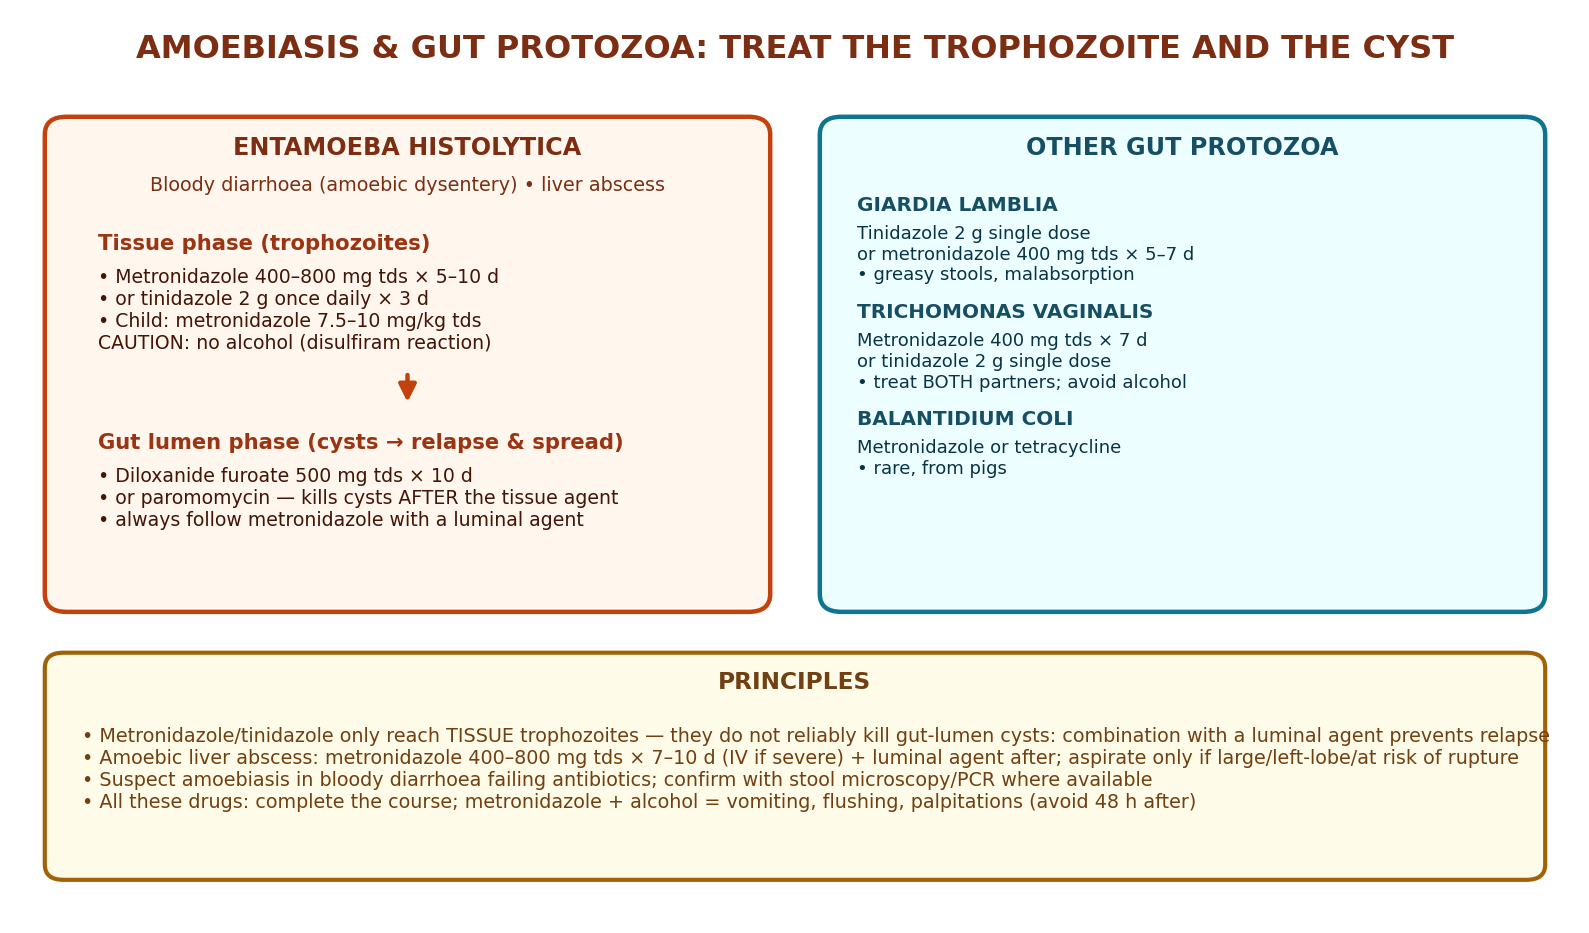
E. histolytica exists in two forms: trophozoites (the active, tissue-invading form that causes dysentery and liver abscess) and cysts (the environmentally resistant form passed in stool that spreads infection and seeds relapse). Two consequences follow:
- Metronidazole and tinidazole are prodrugs activated by reduction in anaerobic organisms — they reach blood and tissue trophozoites but penetrate the gut lumen poorly and do not reliably kill cysts.
- Cysts left behind germinate into new trophozoites → relapse weeks later and ongoing transmission. Hence every tissue-phase treatment is followed by a luminal agent (diloxanide furoate 500 mg tds × 10 days, or paromomycin).
The amoebicides in detail
Scroll the table sideways on a smaller screen.
| Drug | Dose (adult / child) | Indications | Adverse effects | Contraindications, interactions, counselling |
|---|---|---|---|---|
| Metronidazole (Flagyl®) | Amoebic dysentery: 400–800 mg tds × 5–10 days; liver abscess: 400–800 mg tds × 7–10 days (IV 500 mg tds if severe); giardiasis: 400 mg tds × 5–7 days; trichomoniasis: 400 mg tds × 7 days. Child: 7.5–10 mg/kg tds | First-line for amoebiasis, giardiasis, trichomoniasis, plus anaerobic bacterial infections (intra-abdominal sepsis, dental, C. difficile first episode, bacterial vaginosis) | Metallic taste, nausea/GI upset, headache, disulfiram reaction with alcohol (flushing, vomiting, palpitations), dark urine (harmless), peripheral neuropathy with prolonged courses | Avoid alcohol during and 48 h after; warfarin effect enhanced (monitor INR); reduces phenytoin clearance; avoid in 1st-trimester pregnancy where alternatives exist; caution Cockcroft renal dosing in severe impairment |
| Tinidazole | Amoebiasis: 2 g once daily × 3 days; giardiasis and trichomoniasis: 2 g single dose. Child (>3 y): 50–60 mg/kg single daily dose | Same indications as metronidazole where shorter courses improve adherence | As metronidazole; generally better tolerated, metallic taste still common | Same alcohol prohibition; long half-life → single-dose convenience; avoid in pregnancy; same interaction profile |
| Diloxanide furoate (luminal agent) | 500 mg tds × 10 days after the tissue-phase course; child 20 mg/kg/day in 3 doses | Asymptomatic cyst passage; mandatory follow-on after metronidazole/tinidazole for invasive amoebiasis | Mild: flatulence, nausea, pruritus; very safe (poorly absorbed) | Effectively non-toxic — the limiting factor is availability; paromomycin 25–35 mg/kg/day in 3 doses × 7 days is the alternative luminal agent |
| Paromomycin (luminal aminoglycoside) | 25–35 mg/kg/day orally in 3 divided doses × 7 days | Luminal amoebiasis; also used off-label for cryptosporidiosis in some protocols | GI upset; minimal systemic absorption (safe in pregnancy relative to systemic drugs, still specialist-guided) | Not absorbed — ineffective for tissue disease; give after the tissue agent |
Giardia, Trichomonas and Balantidium
Scroll the table sideways on a smaller screen.
| Organism / disease | Presentation | Treatment | Exam-worthy points |
|---|---|---|---|
| Giardia lamblia (giardiasis, "beaver fever") | Non-bloody, greasy, foul-smelling diarrhoea, bloating, weight loss, malabsorption (fat-soluble vitamin deficiency); chronic infection in children → growth faltering; stool shows cysts/trophozoites or antigen | Tinidazole 2 g single dose or metronidazole 400 mg tds × 5–7 days; albendazole/mebendazole are alternatives | No luminal follow-on needed (no tissue phase); treat household contacts with symptoms; check water source — ponds and unboiled water are the classic source |
| Trichomonas vaginalis (trichomoniasis) | Frothy yellow-green vaginal discharge, itching, dysuria; often asymptomatic in men but they carry and transmit it | Metronidazole 400 mg tds × 7 days or tinidazole 2 g stat; treat both sexual partners simultaneously | Part of STI syndromic management; a flagellated organism on wet-mount; untreated infection is linked to adverse pregnancy outcomes and increased HIV acquisition |
| Balantidium coli | Dysentery resembling amoebiasis; the only ciliate parasite of humans, contracted from pigs | Metronidazole or tetracycline | Rare in Uganda — a differential, not a daily diagnosis |
| Cryptosporidium (note) | Profuse watery diarrhoea, severe and prolonged in advanced HIV | Supportive; ART immune recovery is the treatment; nitazoxanide 500 mg bd × 3 days in immunocompetent patients (limited evidence in AIDS) | Chlorine-resistant oocysts — safe water (boiling/filtering) matters |
Amoebic liver abscess
Amoebae travel via the portal vein and digest hepatocytes — a right-lobe subdiaphragmatic "anchovy paste" (chocolate) abscess. The classic picture: subacute fever, right upper quadrant or pleuritic shoulder pain, hepatomegaly with point tenderness, raised right hemidiaphragm on chest X-ray, and a positive serology (amoebic antibody/ antigen) — stool microscopy is often negative here because the bowel has healed.
- Drug treatment first: metronidazole 400–800 mg tds × 7–10 days (IV 500 mg tds if the patient cannot take oral) + a luminal agent afterwards — imaging resolves slowly over months and is not the measure of cure.
- Aspiration is the exception, not the rule: indicated for very large abscess (typically >10 cm or at risk of rupture), left-lobe abscess (pericardial rupture risk), failure to respond to 48–72 h of therapy, or diagnostic uncertainty (rule out pyogenic abscess/malignancy). Send aspirate for microscopy — trophozoites at the wall are diagnostic.
- Complications: rupture into peritoneum, pleura or pericardium — the last is life-threatening and classically follows left-lobe disease.
Safety, interactions and counselling
- The alcohol rule: metronidazole and tinidazole inhibit aldehyde dehydrogenase → acetaldehyde accumulation (disulfiram-like reaction: flushing, vomiting, palpitations, hypotension). No alcohol during treatment and for 48–72 h after the last dose — including beer, waragi and traditional brews; counsel explicitly because "medicine plus alcohol" misunderstandings cause avoidable harm.
- Interactions: warfarin (INR rises — monitor), phenytoin (toxicity), lithium, ciclosporin; disulfiram and alcohol-containing syrups should be avoided concurrently.
- Pregnancy: avoid nitroimidazoles in the first trimester where alternatives exist; invasive amoebiasis in later pregnancy is treated because untreated disease is worse for the fetus — luminal agents like paromomycin (non-absorbed) are preferred when the disease is luminal-only.
- Complete the course: partial treatment of giardia or trichomonas breeds recurrence; trichomoniasis requires partner treatment to prevent ping-pong reinfection.
Clinical scenarios
Scenario 1 — Bloody diarrhoea that failed antibiotics
A 29-year-old trader has 2 weeks of bloody mucoid diarrhoea. He was given ciprofloxacin at a clinic without improvement. You suspect amoebic dysentery (antibacterial antibiotics do not touch Entamoeba; chronicity and blood distinguish it from bacillary dysentery — always consider shigella too and test for both). You treat with metronidazole 800 mg tds × 7 days, warn him strictly against alcohol (including waragi) during and 2 days after treatment, and on day 8 start diloxanide furoate 500 mg tds × 10 days to clear the luminal cysts. Skipping the luminal phase is the classic reason for relapse a month later.
Scenario 2 — The child failing to thrive with greasy stools
A 4-year-old in a rural parish has 2 months of intermittent greasy, foul-smelling, non-bloody stools, a distended abdomen and weight faltering. Giardia antigen is positive on stool testing. You prescribe tinidazole 50 mg/kg single dose (syrup or crushed tablet) — a single observed dose beats a week of metronidazole when adherence is uncertain — counsel the mother to boil drinking water, and review growth at the next visit. The household's other symptomatic children are treated too.
Scenario 3 — Fever and pleuritic shoulder pain
A 35-year-old man has had 3 weeks of fever, night sweats, and pain in the right shoulder worse on breathing. Examination finds a tender liver edge 4 cm below the costal margin. Ultrasound shows a 9 cm right-lobe fluid collection. Amoebic serology is positive. You start IV metronidazole 500 mg tds because he is vomiting, schedule a luminal agent to follow, and monitor closely — the abscess is large but he is stable and responding, so you do not aspirate initially; left-lobe location, failure to defervesce by 72 h, or threatened rupture would change that decision. He improves by day 3 and completes oral therapy; the ultrasound abnormality will persist for months — you tell him this so a later scan doesn't trigger unnecessary interventions.
Key points
References
- Uganda Clinical Guidelines 2023 — diarrhoeal diseases and STI management chapters (Library reference.)
- Katzung's Basic & Clinical Pharmacology — chemotherapy of protozoal infections chapter (Library reference.)
- Goodman & Gilman's The Pharmacological Basis of Therapeutics (Library reference.)
- WHO Model List of Essential Medicines: antiprotozoal agents (Library reference.)
- CDC DPDx — Laboratory identification of parasites of public health concern: Entamoeba histolytica, Giardia (Library reference.)
Further reading
For deeper study, compare this lesson with current guidance and standard references from recognised medical and pharmaceutical organisations.
- WHO Model List of Essential Medicines 2023
- Uganda MoH Knowledge Management Portal (UCG 2023)
- CDC DPDx parasite identification library
- MSF Clinical Guidelines
- DCM Year One Semester Two curriculum
For education only. Always confirm the diagnosis and follow the current Uganda Clinical Guidelines and syndromic STI protocols in practice.