Doctors Revision

Medicine-Infectious Diseases

Medicine-Infectious Diseases

Amoebiasis: comprehensive intestinal colitis, liver abscess, diagnosis and management

Amoebiasis: intestinal colitis, dysentery and liver abscess Amoebiasis is infection with the pathogenic protozoan Entamoeba histolytica. It may be asymptomatic, produce colitis and dysentery, or spread through the portal circulation to the liver and occasionally the pleura, lung, peritoneum, brain or skin. E. dispar and E. moshkovskii are morphologically similar but usually non-invasive; therefore the phrase “amoeba cysts seen” is not enough to prove invasive disease. Core treatment rule: invasive disease needs a tissue-active drug followed by a luminal cyst-eradicating agent. Learning outcomes Describe cyst and trophozoite morphology and the faecal–oral life cycle. Explain adherence, flask-shaped ulcers, portal spread and liver abscess formation. Differentiate asymptomatic carriage, amoebic colitis, fulminant colitis and extraintestinal disease. Interpret stool microscopy, antigen/PCR, serology and liver imaging. Manage dysentery, liver abscess, complications and treatment failure safely. Prevent transmission through sanitation, water safety and sexual-health counselling. Organism and life cycle Form Features Role in disease Mature cyst Resistant wall, multiple nuclei; survives outside the host Infectious form swallowed in contaminated food/water or transferred by hands. Trophozoite Motile, rapidly degenerates outside the colon Replicates in lumen, may adhere to and destroy epithelium, and can invade blood vessels. After cyst ingestion, excystation occurs in the small bowel. Trophozoites migrate to the caecum and colon, multiply and either remain luminal or invade. Encystation occurs during distal transit and cysts are passed in formed stool. Transmission and risk factors Faecally contaminated water, food, hands and household surfaces. Inadequate sanitation, crowded institutions and unsafe sewage disposal. Oral–anal sexual exposure and household contact. Travel/residence in endemic tropical settings. Malnutrition, pregnancy, immunosuppression and corticosteroid exposure, which can worsen invasive disease. Cysts are the major environmental and transmission form. Trophozoites in fresh diarrhoeal stool die quickly but may transmit directly during sexual contact. Pathogenesis E. histolytica uses lectin-mediated adherence to colonic mucin and epithelial cells, then releases proteases and cytotoxic molecules that damage cells and extracellular matrix. Initial mucosal lesions enlarge into characteristic flask-shaped ulcers with a narrow mucosal neck and broad submucosal base. Trophozoites can enter venules and travel through the portal system to the liver. The liver lesion contains necrotic material and inflammatory cells; it may be sterile initially but can become secondarily infected with bacteria. Clinical spectrum Asymptomatic intestinal infection Many infected people pass cysts without symptoms. Confirmed E. histolytica carriage matters because transmission and future invasion are possible. A luminal eradication regimen is generally required, but a non-specific microscopy report should be clarified before labelling every Entamoeba as pathogenic. Amoebic colitis Gradual abdominal pain, tenesmus and frequent loose stools. Mucus and blood ranging from mild dysentery to severe colitis. Weight loss, anorexia, fatigue and low-grade fever. Right iliac fossa tenderness or an amoeboma-like inflammatory mass. Fulminant necrotising colitis Extensive ulceration may cause severe pain, high fever, ileus, peritonism, toxic megacolon, perforation, massive haemorrhage, shock and death. Corticosteroids given for presumed inflammatory bowel disease can accelerate fulminant amoebiasis. Amoebic liver abscess Fever, right-upper-quadrant pain and tender hepatomegaly. Referred right shoulder pain, pleuritic pain or cough from diaphragmatic irritation. Often solitary and right-lobe dominant, but multiple lesions occur. Jaundice, respiratory distress, pleural effusion or peritonism suggest obstruction or rupture. Rupture may occur into the pleura, lung, pericardium, peritoneum or skin. Brain abscess is rare and rapidly life-threatening. History and examination Ask about water and sanitation, travel, household diarrhoea, oral–anal exposure, previous dysentery, recent antibiotics, steroid use, HIV/immunosuppression, weight loss and duration. For suspected liver abscess ask about RUQ/shoulder pain, cough, alcohol, biliary disease and prior treatment. Assess hydration, pulse, blood pressure, fever, pallor, abdominal tenderness, guarding, distension, bowel sounds, hepatomegaly, jaundice, pleural signs, skin lesions and mental status. Toxic appearance, peritonism, shock, severe anaemia or altered consciousness requires admission and urgent specialist review. Diagnosis and interpretation Intestinal disease Specific stool antigen or PCR: preferred where available because it distinguishes E. histolytica from look-alikes. Fresh microscopy: may show trophozoites or cysts; rapid examination is important. Multiple specimens increase yield. Haematophagous trophozoites: a classic clue, but erythrophagocytosis is not perfectly specific and should not replace antigen/PCR. Endoscopy/biopsy: reserved for uncertainty, severe colitis or suspected inflammatory bowel disease/amoeboma; biopsy risks must be considered. Extraintestinal disease Ultrasound: accessible first-line imaging for liver abscess. CT/MRI: defines size, number, rupture, pleural/peritoneal extension and alternative pathology. Serology: often positive in liver abscess but may remain positive after previous infection; interpret with imaging. Aspirate: may contain thick brown “anchovy-sauce” material; send for bacterial culture and amebic antigen/PCR where possible. Investigation What it adds Important limitation FBC Leukocytosis, anaemia, thrombocytosis Non-specific and may be normal early. LFTs Alkaline phosphatase/transaminase changes, bilirubin Cannot distinguish amoebic from pyogenic abscess alone. Stool culture/PCR for bacteria Detects co-infection Negative culture does not exclude amoebiasis. Blood cultures Important in toxic abscess/colitis May be negative in uncomplicated disease. Do not overinterpret microscopy: “Entamoeba cysts” without species confirmation may represent non-pathogenic species. Conversely, a negative stool test does not exclude liver abscess. Differential diagnosis For dysentery consider shigellosis, campylobacteriosis, salmonellosis, Yersinia, inflammatory bowel disease, intestinal tuberculosis, schistosomiasis, colorectal cancer and ischemic colitis. For liver lesions consider pyogenic abscess, hydatid disease, malignancy, tuberculosis, fungal abscess and infected biliary cysts. Amoebic and bacterial abscess may coexist. Management of intestinal infection Invasive colitis Use a tissue-active nitroimidazole such as metronidazole or tinidazole according to current UCG age/weight regimen. Rehydrate, maintain nutrition and monitor for perforation, toxic megacolon, haemorrhage and sepsis. Mandatory luminal course After the tissue-active course give paromomycin, diloxanide furoate, iodoquinol or another UCG-approved luminal agent. This clears residual cysts and reduces relapse and transmission. Asymptomatic confirmed E. histolytica Use a luminal agent even without symptoms. Clarify species when possible before treating a non-pathogenic Entamoeba report. Use oral or IV fluids according to dehydration and ability to drink. Avoid loperamide and other antimotility drugs in severe bloody diarrhoea or suspected invasive colitis. Do not give corticosteroids for presumed IBD until amoebic colitis is excluded; if steroids were started, involve specialists urgently. Review pregnancy, breastfeeding, liver disease, drug interactions and alcohol use before nitroimidazole therapy. Amoebic liver abscess Obtain ultrasound and baseline FBC/LFTs; take blood cultures if febrile/toxic. Start a tissue-active

Medicine-Infectious Diseases

Malaria: comprehensive life cycle, pathophysiology, diagnosis, severe disease and management

Malaria: a complete clinical chapter for student doctors Malaria is an infection caused by protozoa of the genus Plasmodium and transmitted predominantly by the bite of an infected female Anopheles mosquito. It is one of the most important causes of fever, anaemia, hospital admission and preventable death in Uganda. The clinician’s task is not simply to recognise a positive test: it is to identify the species and parasite burden, recognise severe disease early, treat correctly, and continue searching for another diagnosis when the course does not fit malaria. Clinical anchor: every febrile patient may have malaria, but every positive malaria test does not explain every clinical problem. Learning outcomes Describe the vector, human and mosquito phases of the parasite life cycle. Explain why P. falciparum causes sequestration, cerebral malaria, acidosis, anaemia, hypoglycaemia and renal injury. Differentiate uncomplicated malaria, severe malaria, treatment failure and non-malarial fever. Interpret thick and thin films, rapid diagnostic tests, parasite density and repeat tests. Manage malaria safely in children, pregnancy, HIV, malnutrition, sickle-cell disease and renal dysfunction. Explain prevention, surveillance, counselling and follow-up. Definition and species Malaria is confirmed when a compatible clinical illness is accompanied by asexual Plasmodium parasites in blood or a validated parasite antigen test. Five species infect humans: Species Biology Clinical importance Microscopy clues P. falciparum Multiple parasites per red cell; mature forms sequester Most severe disease; cerebral malaria, acidosis, renal failure, severe anaemia, shock and death Delicate multiple rings, appliqué forms, crescent gametocytes; mature trophozoites often absent from peripheral film P. vivax Invades reticulocytes; dormant hypnozoites Relapse, splenic complications and occasional severe disease Enlarged red cells, Schüffner dots, amoeboid trophozoites P. ovale Hypnozoites; usually low parasitaemia Relapsing illness; can be misidentified as vivax Oval/fimbriated erythrocytes, Schüffner-type dots P. malariae Low-level long persistence Quartan pattern and chronic immune-complex nephropathy Band forms and rosette schizonts P. knowlesi Twenty-four-hour asexual cycle; macaque reservoir Rapidly progressive severe disease in Southeast Asia May resemble falciparum early and malariae later; travel history is essential Uganda epidemiology and determinants of risk Transmission intensity varies between regions and seasons. Rainfall and temperature affect breeding sites; altitude changes vector survival; housing, drainage, bed-net access and indoor residual spraying affect exposure. Repeated childhood infection can create partial immunity, but no endemic adult is completely protected. Severe disease is more likely in young children, pregnant women, non-immune visitors, people with HIV or malnutrition, and patients with sickle-cell disease or delayed access to treatment. Ask about residence, recent travel, season, occupation near water or forest, bed-net use, indoor spraying, previous malaria, recent antimalarial use and whether medicine was purchased from an informal source. An epidemiological risk does not replace parasitological testing; a low-risk patient can still have imported or transfusion-associated malaria. Transmission and life cycle Inoculation: the mosquito injects sporozoites with saliva. Hepatic invasion: sporozoites rapidly enter hepatocytes. Asexual multiplication forms liver schizonts, which rupture and release merozoites. This phase is clinically silent. Hypnozoites: P. vivax and P. ovale may remain dormant in hepatocytes and reactivate, producing relapses without a new mosquito bite. Erythrocytic cycle: merozoites invade red cells, develop through ring, trophozoite and schizont stages, and rupture the cell. The cycle is approximately 48 hours for falciparum/vivax/ovale and 72 hours for malariae. Gametocytogenesis: a proportion differentiates into male and female gametocytes, which are the forms infectious to mosquitoes. Mosquito development: gametocytes fuse in the gut, form an ookinete and oocyst, and generate sporozoites that migrate to the salivary glands. Radical cure is different from blood-stage cure: an ACT clears circulating parasites but does not reliably eradicate vivax/ovale hypnozoites. Follow current UCG guidance and assess G6PD risk before a relapse-prevention drug. Pathophysiology in detail Fever Rupture of schizont-infected erythrocytes releases parasite products such as glycosylphosphatidylinositol and haemozoin. Innate immune cells produce IL-1, IL-6, TNF and other mediators, causing rigors, fever, sweating and malaise. Antipyretics improve comfort but do not treat the parasite. Sequestration and microvascular disease Falciparum-infected erythrocytes express PfEMP1 and related adhesins. They bind endothelial receptors, form rosettes with uninfected cells and avoid splenic clearance. In the brain, placenta, kidneys and lungs this reduces perfusion and oxygen delivery. Sequestration explains why peripheral parasite density may underestimate total biomass. Anaemia Both infected and uninfected erythrocytes are removed by the spleen. Inflammation, dyserythropoiesis, bleeding, nutritional deficiency and repeated infection worsen anaemia. Severe anaemia reduces oxygen delivery and can itself cause heart failure, acidosis and death. Cerebral malaria Microvascular obstruction, endothelial activation, blood-brain barrier dysfunction, hypoxia and inflammatory injury produce impaired consciousness, seizures and coma. Cerebral malaria is a clinical diagnosis in a patient with falciparum parasitaemia after alternative causes of coma have been assessed; a positive malaria test must not stop evaluation for meningitis, hypoglycaemia, sepsis, intoxication or head injury. Acidosis and respiratory distress Lactate accumulates because of tissue hypoxia, anaerobic metabolism, severe anaemia, seizures, shock and impaired hepatic/renal clearance. Deep breathing is often compensatory Kussmaul breathing, not primary pneumonia. Pulmonary oedema may follow capillary leak or excessive fluid administration. Hypoglycaemia Glucose is consumed by parasites and sick patients often have poor intake. Hepatic dysfunction, quinine-related hyperinsulinaemia and pregnancy further increase risk. Neurological signs of hypoglycaemia can mimic cerebral malaria. Renal and hepatic injury Hypoperfusion, haemoglobinuria, inflammatory injury and parasite pigment can cause acute kidney injury. Jaundice may result from haemolysis, hepatocellular injury or cholestasis; marked jaundice with encephalopathy should trigger consideration of severe malaria plus hepatic failure or another diagnosis. Clinical presentation Uncomplicated malaria The typical patient has fever or a history of fever, chills, rigors, headache, weakness, myalgia, arthralgia, anorexia, nausea or vomiting. Abdominal pain and diarrhoea are common in children. The spleen may be palpable. Fever periodicity is often absent, especially early or after partial treatment. Severe malaria danger signs Impaired consciousness, coma, abnormal behaviour or repeated convulsions. Prostration: inability to sit, stand, drink or breastfeed. Respiratory distress, acidotic breathing, hypoxaemia or pulmonary oedema. Shock, cold extremities, weak pulse or delayed capillary refill. Severe pallor, haemoglobinuria, jaundice with organ dysfunction or abnormal bleeding. Hypoglycaemia, oliguria, acute kidney injury or severe electrolyte disturbance. Persistent vomiting, very high parasite density or rapid

Swine Flu
Medicine-Infectious Diseases

Swine Flu (Influenza A H1N1): Clinical Features, Diagnosis, Treatment and Prevention

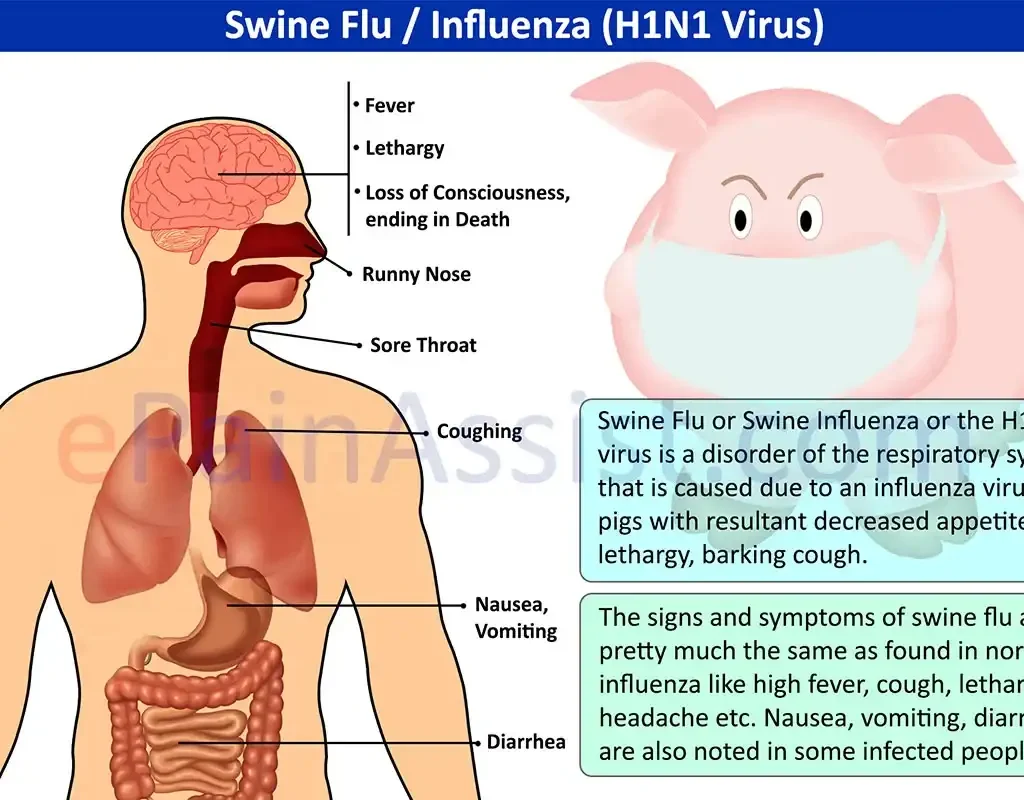
Swine Flu (Influenza A H1N1): Clinical Features, Diagnosis, Treatment and Prevention Clinical Medicine Year 3 • pandemic H1N1, current seasonal H1N1pdm09 illness and severity-based clinical care Clinical safety note: “Swine flu” usually refers to the 2009 pandemic influenza A(H1N1) strain, now circulating as seasonal A(H1N1)pdm09. Follow current influenza guidance and local protocols. Do not delay antiviral treatment in severe disease, pregnancy or high-risk patients while waiting for laboratory confirmation. What “swine flu” means today Swine flu is the popular name used during the 2009 influenza A(H1N1) pandemic. That virus was a reassortant containing gene segments from human, avian and swine lineages. After the pandemic, A(H1N1)pdm09 became part of seasonal human influenza circulation. Separate swine-influenza viruses can infect people after direct occupational exposure to pigs and require public-health subtyping. H1N1 illness may be mild, but it can also cause viral pneumonia, ARDS, myocarditis, encephalitis, secondary bacterial pneumonia, sepsis and death. The key clinical questions are severity, host risk and whether the illness could represent a novel animal-origin influenza infection. Learning outcomes Explain influenza A structure, H1N1 nomenclature, antigenic drift and reassortment. Describe transmission, incubation, infectious period and high-risk groups. Recognise uncomplicated influenza, pneumonia, sepsis, ARDS and neurologic complications. Select molecular testing and understand the limits of rapid tests. Use oseltamivir, supportive care, isolation, vaccination and outbreak-control principles safely. Virology and epidemiology Influenza A is an enveloped, segmented, negative-sense RNA virus in the Orthomyxoviridae family. H1N1 identifies haemagglutinin 1 and neuraminidase 1. Haemagglutinin binds respiratory epithelial receptors and neuraminidase helps release progeny virions. Antigenic drift causes gradual seasonal change; reassortment can create a novel virus with limited population immunity. The 2009 pandemic spread globally because many people had little pre-existing immunity. H1N1pdm09 is now included in seasonal influenza surveillance and vaccine composition, but severe illness remains possible when care is delayed or the patient has reduced cardiopulmonary/immune reserve. Transmission, incubation and communicability Respiratory droplets and aerosols from coughing, sneezing, talking and clinical procedures. Contaminated hands and surfaces followed by touching the eyes, nose or mouth. Close household, school, workplace and healthcare contact. Rare occupational infection with swine influenza after direct pig exposure; unusual cases require notification and subtype testing. Incubation is commonly 1–4 days, often about 2 days. Infectiousness may begin about one day before symptoms and last 5–7 days after onset, longer in young children, immunocompromised people and severe illness. Fever may be absent in older or immunosuppressed patients. Pathophysiology Virus enters airway epithelial cells and replicates. Damage to ciliated epithelium impairs mucociliary clearance. Innate immune activation causes fever, malaise, myalgia and headache. Lower-airway infection can produce diffuse alveolar inflammation, hypoxaemia and ARDS. Damaged epithelium predisposes to pneumococcal or staphylococcal superinfection. Inflammation or direct viral invasion can affect the heart, brain, muscles and kidneys. Clinical features Uncomplicated influenza Fever, chills, malaise, headache and profound fatigue. Dry cough, sore throat, hoarseness and rhinorrhoea. Myalgia, arthralgia, backache, eye discomfort and photophobia. Nausea, vomiting or diarrhoea, particularly in children. Complicated influenza Primary viral pneumonia with breathlessness, hypoxaemia and diffuse infiltrates. Secondary bacterial pneumonia with recurrent fever, purulent sputum, focal consolidation or sepsis. ARDS, shock, acute kidney injury, rhabdomyolysis and myocarditis. Encephalitis, encephalopathy, seizures or Guillain–Barré syndrome. Exacerbation of asthma, COPD, heart failure, diabetes or other chronic disease. High-risk groups Group Reason for increased risk Pregnant/recently postpartum women Respiratory and immune physiologic changes Young children and older adults Immature or reduced immune and cardiopulmonary reserve Chronic lung/heart disease Reduced reserve and decompensation risk Diabetes, renal/liver/neurologic disease or obesity Higher risk of organ complications HIV, cancer, transplant or long-term steroids Impaired immune control and prolonged shedding Red flags requiring urgent admission Shortness of breath, tachypnoea, chest pain, cyanosis or low oxygen saturation. Haemoptysis, persistent high fever, hypotension or sepsis. Confusion, drowsiness, seizures or inability to wake. Inability to drink, persistent vomiting, dehydration or markedly reduced urine. Recurrent fever or worsening cough after initial improvement. High-risk patient with rapidly progressive symptoms. In children: poor feeding, grunting, chest indrawing, convulsions or lethargy. History and examination Domain What to assess Time course Day of illness, sudden onset, improvement followed by deterioration Exposure Household outbreak, school/workplace, healthcare, travel and pig contact Risk status Pregnancy, age, chronic disease, HIV, immunosuppression and obesity Respiratory status Respiratory rate, work of breathing, SpO2, chest signs and ability to feed/speak Systemic severity Pulse, BP, capillary refill, hydration, mental state, glucose and urine Complications Focal chest signs, cardiac symptoms, muscle weakness, seizures or neurologic change Investigations RT-PCR/molecular respiratory panel: preferred for severe, admitted, unusual or outbreak-associated cases and for subtype information. Rapid antigen tests are less sensitive; a negative result does not exclude influenza in severe illness. Chest radiograph or ultrasound for pneumonia, oedema, effusion or ARDS. Full blood count, electrolytes, renal/liver tests, glucose, CRP and lactate as indicated. Blood/sputum cultures when bacterial superinfection or sepsis is suspected. ECG/troponin for myocarditis, CK for rhabdomyolysis and blood gas for respiratory failure. Test for malaria and other local causes of fever where appropriate; coinfection is possible. Differential diagnosis Condition Key issue Seasonal influenza A/B Often clinically indistinguishable; molecular testing identifies the virus. COVID-19/other respiratory viruses Overlap in symptoms and pneumonia; use local testing. Bacterial pneumonia Focal consolidation, purulent sputum, recurrent fever or sepsis. Malaria Fever, headache, anaemia, thrombocytopenia or altered mental state. Typhoid, dengue and other tropical infections Consider exposure, rash, GI disease and laboratory patterns. Management Antiviral treatment Oseltamivir A common adult treatment dose with normal renal function is 75 mg orally twice daily for 5 days. Start promptly in severe disease, hospitalisation, pregnancy and high-risk patients; adjust for renal function, age and local guidance. Timing Benefit is greatest within 48 hours, but treatment can benefit severe, progressive, hospitalised or high-risk patients even when started later. Do not wait for PCR when treatment is clinically indicated. Novel exposure Unusual illness after pig exposure requires public-health notification, subtype testing and specialist advice about resistance and duration. Outpatient care Rest, oral fluids, nutrition and safe-dose paracetamol. Stay home, improve ventilation and wear a mask around others while infectious. Give clear return precautions for breathlessness, chest pain, confusion, dehydration,

Avian Influenza
Medicine-Infectious Diseases

Avian Influenza (Bird Flu, Including H5N1): Clinical Features, Diagnosis and Management

Avian Influenza (Bird Flu, Including H5N1): Clinical Features, Diagnosis and Management Clinical Medicine Year 3 • zoonotic influenza at the human–animal interface and its pandemic potential Clinical safety note: Suspected human infection with avian influenza A—especially H5N1—requires immediate notification to public health authorities and expert laboratory coordination. Ask about sick/dead birds, poultry farms, live markets, dairy cattle, raw milk and contaminated environments. Begin infection-control precautions and discuss antiviral treatment promptly; do not wait for a routine influenza test to rule it out. Why bird flu matters Avian influenza is caused by influenza A viruses that normally circulate among birds. Most avian strains do not infect humans efficiently, but some—particularly highly pathogenic H5 viruses—can cause severe human disease after direct or environmental exposure. Human illness ranges from conjunctivitis or mild upper-respiratory symptoms to severe viral pneumonia, acute respiratory distress syndrome (ARDS), gastrointestinal disease, encephalitis, multiorgan failure and death. The immediate clinical task is to separate ordinary seasonal influenza from a possible novel zoonotic influenza infection. The difference is made by exposure history, specimen choice, public-health testing and rapid treatment—not by the appearance of fever alone. Learning outcomes Explain influenza A subtypes, haemagglutinin/neuraminidase nomenclature and avian influenza ecology. Recognise the exposure history and clinical spectrum of human H5N1/H7N9 infection. Plan testing, isolation, antiviral treatment and monitoring of contacts. Identify respiratory, ocular, gastrointestinal and neurologic complications. Explain how reassortment, mutation and poultry control influence pandemic risk. Influenza virology Influenza A viruses are enveloped, segmented, negative-sense RNA viruses in the family Orthomyxoviridae. Their surface proteins are haemagglutinin (H) and neuraminidase (N), which define subtypes such as H5N1, H7N9 and H1N1. The segmented genome allows reassortment when two influenza viruses infect the same cell. Gradual mutation is called antigenic drift; abrupt reassortment can produce a virus to which humans have little immunity. “Highly pathogenic” and “low pathogenic” refer primarily to disease severity in poultry, not automatically to severity in humans. A low-pathogenic avian virus in birds may still cause serious human illness. Animal reservoirs and human exposure Wild aquatic birds are important reservoirs. Poultry, wild birds and some mammals can become infected. Human infections are uncommon and usually follow close exposure to infected animals or contaminated environments rather than efficient human-to-human spread. Handling sick or dead poultry, wild birds, cats or other infected animals. Slaughtering, defeathering, butchering, cleaning cages or handling droppings and secretions. Working on farms, in live-bird markets, veterinary services or culling teams. Contact with infected dairy cattle or raw milk in settings where H5 viruses are circulating in mammals. Unprotected contact with contaminated surfaces, equipment or aerosols. Human infection is not acquired by eating properly cooked poultry or pasteurised milk. The primary concern is exposure during handling, slaughter, milking or preparation of infected animals and contaminated materials. Pathogenesis and pandemic risk Virus enters through the eye, nose, mouth or lower respiratory tract. Avian influenza viruses preferentially bind receptors in the respiratory tract, but some strains can infect conjunctival, gastrointestinal or neurologic tissues. Viral replication and an exaggerated inflammatory response can damage alveoli, causing diffuse pneumonitis and ARDS. Gastrointestinal and neurologic involvement may occur in severe or unusual presentations. Pandemic risk would rise if a novel avian virus acquired sustained, efficient human-to-human transmission through mutation or reassortment. That is a surveillance concern—not evidence that every human case spreads readily. Clinical presentations 1. Conjunctivitis Red, watery, painful or gritty eyes may be the first or only symptom after ocular exposure. Conjunctivitis in a person who handled infected birds, cattle or contaminated equipment should prompt avian-influenza testing and public-health notification. 2. Upper-respiratory and systemic illness Fever, chills, headache, myalgia, malaise and anorexia. Sore throat, cough, rhinorrhoea and shortness of breath. Diarrhoea, nausea, vomiting or abdominal pain—particularly described with H5N1. 3. Severe lower-respiratory disease Viral pneumonia can progress rapidly to hypoxaemic respiratory failure, ARDS, shock, secondary bacterial infection, acute kidney injury and multiorgan failure. Findings include tachypnoea, hypoxaemia, crackles, cyanosis, confusion, chest pain and increasing work of breathing. 4. Neurologic complications Encephalitis, encephalopathy, seizures, ataxia and altered consciousness have been reported. Consider neurologic disease particularly when respiratory findings do not fully explain the level of altered mental status. History and examination Ask/examine Examples Clinical importance Animal exposure Sick/dead birds, poultry, wild birds, dairy cattle, cats, live markets Determines whether a novel influenza pathway is needed Type of contact Slaughter, defeathering, milking, culling, cage cleaning, droppings Estimates intensity and route of exposure Eye symptoms Redness, tearing, pain, photophobia, blurred vision May be the dominant presentation Respiratory status Respiratory rate, SpO2, work of breathing, chest signs Detects pneumonia/ARDS early Neurologic/GI status Confusion, seizures, vomiting, diarrhoea Identifies severe or atypical disease Contacts Household and occupational contacts with symptoms Supports monitoring and outbreak investigation Investigations Specific virologic testing Collect respiratory specimens in consultation with the reference laboratory: nasopharyngeal/oropharyngeal swabs for upper-respiratory illness and lower-respiratory specimens when severe pneumonia is present. Collect conjunctival swabs when conjunctivitis is present. Use real-time RT-PCR with assays that detect influenza A and differentiate avian subtypes. Routine seasonal influenza rapid tests may be negative or cannot subtype the virus. Do not delay public-health notification while waiting for a result. Use appropriate PPE and specimen packaging; laboratory workers require trained procedures for potentially high-consequence pathogens. Severity assessment Pulse oximetry, arterial/venous blood gas, chest radiograph or CT when indicated. Full blood count, electrolytes, renal/liver tests, glucose, CRP and lactate. Blood cultures and tests for bacterial coinfection when pneumonia or sepsis is suspected. ECG/troponin and neurologic imaging/CSF only when clinically indicated and safe. Differential diagnosis Condition Clues Seasonal influenza A/B Community circulation without unusual animal exposure; confirm by routine testing. COVID-19 and other respiratory viruses Respiratory syndrome; test according to local protocol. Avian influenza Conjunctivitis, severe pneumonia or GI disease plus bird/mammal exposure. Bacterial pneumonia/sepsis Focal consolidation, purulent sputum, shock or positive cultures; coinfection can occur. Malaria and other tropical febrile diseases Fever after travel/exposure; test in parallel when appropriate. Management Start treatment and infection-control planning early. Current guidance supports prompt antiviral treatment for suspected novel avian-influenza infection, particularly severe disease, while confirmatory testing is arranged. Antiviral therapy

marburg virus
Medicine-Infectious Diseases

Marburg Virus Disease: Clinical Features, Diagnosis, Management and Prevention

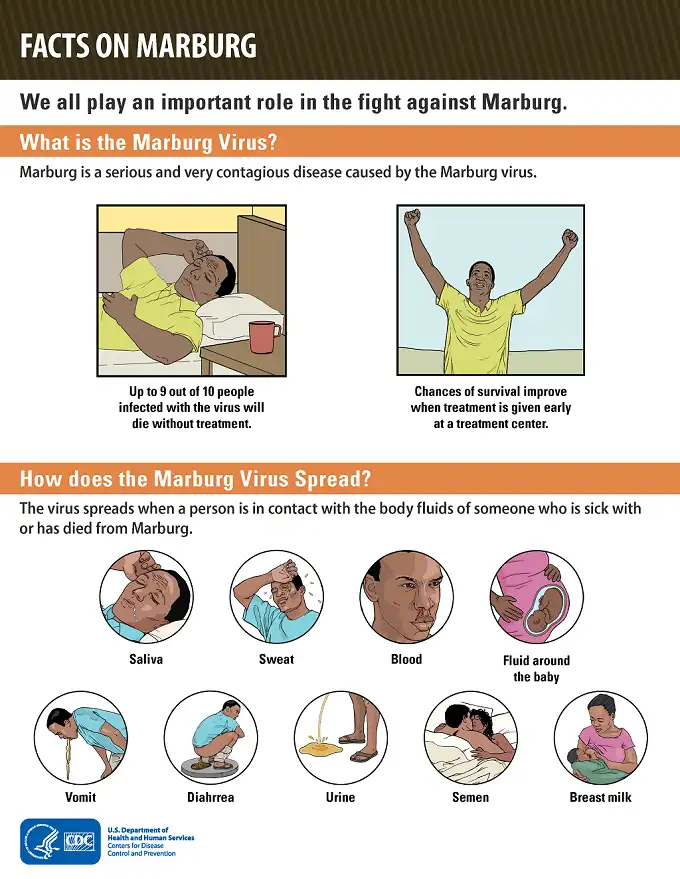
Marburg Virus Disease: Clinical Features, Diagnosis, Management and Prevention Clinical Medicine Year 3 • a severe filovirus infection linked to bats, caves, body fluids and high-consequence outbreaks Clinical safety note: Suspected Marburg virus disease (MVD) is a public-health emergency. Isolate immediately, notify the designated authorities, use trained staff and appropriate PPE, and coordinate all specimen collection, transfer, burial and laboratory work through the national viral-haemorrhagic-fever pathway. Do not assume that absence of bleeding makes the patient safe or that an ordinary fever ward can manage suspected MVD. Why Marburg matters Marburg virus disease is a rare but highly severe viral haemorrhagic fever caused by Marburgvirus or Ravn virus. It begins abruptly with fever, severe headache, malaise and muscle pain, then may progress to watery diarrhoea, vomiting, abdominal pain, rash, shock, organ failure, encephalopathy and bleeding. The presentation overlaps heavily with malaria, typhoid, Ebola, dengue and bacterial sepsis, so exposure history and immediate infection prevention are as important as laboratory confirmation. Marburg and Ebola are both filoviruses and share many clinical and control principles, but they are different viruses. There are currently no approved Marburg vaccine or antiviral treatment; early intensive supportive care is the intervention most likely to improve survival. Learning outcomes Describe Marburg virus classification, morphology, reservoir and routes of transmission. Explain the incubation period, phases of illness and mechanisms of shock and coagulopathy. Recognise early, gastrointestinal, haemorrhagic, neurologic, ocular and genital complications. Plan safe diagnostic testing and differential diagnosis. Describe supportive care, infection prevention, contact monitoring and survivor counselling. Definition and virology Marburg virus and Ravn virus are enveloped, filamentous, non-segmented, negative-sense RNA viruses in the family Filoviridae and genus Marburgvirus (often called Orthomarburgvirus in current taxonomy). The virion contains nucleoprotein and polymerase-associated proteins surrounded by a lipid envelope with glycoprotein spikes. The virus replicates in macrophages, dendritic cells, endothelial cells, hepatocytes and other tissues. Marburg disease was first recognised in 1967 after laboratory-associated outbreaks in Marburg and Frankfurt and Belgrade linked to imported African green monkeys from Uganda. Later outbreaks in Africa have been associated with cave or mine exposure and human-to-human transmission. Reservoir and transmission The Egyptian fruit bat, Rousettus aegyptiacus, is the principal natural reservoir identified for Marburg virus. People may become infected while entering caves/mines or handling bats, then transmit virus to others through body fluids after symptoms begin. Blood, vomit, stool, urine, saliva, sweat, breast milk, semen and other body fluids. Direct contact with a symptomatic patient’s mucous membranes or broken skin. Unsafe injections, contaminated instruments or blood products. Contact with a body during funeral preparation or burial. Sexual exposure to survivors because virus may persist in semen. Patients are not generally infectious before symptoms. Casual contact without body-fluid exposure is not the usual route, but every suspected patient should be assessed conservatively until testing and an exposure history are clear. Incubation and infectious period The incubation period is usually 2–21 days. Early illness may resemble malaria or influenza. Infectivity increases as viral load rises and as vomiting, diarrhoea, bleeding and other wet symptoms develop. In fatal cases, deterioration commonly occurs during the second week, but course and fatality vary by outbreak, viral strain, timing of care and access to intensive support. Pathophysiology Virus enters through mucosa, broken skin, injection or contaminated body-fluid exposure. It replicates in antigen-presenting cells and macrophages and spreads through lymphatics and blood. Immune dysregulation causes high cytokine activity while adaptive immune responses are delayed or ineffective. Endothelial injury and inflammatory mediators increase vascular permeability and promote capillary leak. Hepatocellular injury reduces clotting-factor synthesis; platelet and coagulation abnormalities amplify bleeding. Vomiting and diarrhoea cause severe volume and electrolyte loss, while shock leads to kidney, liver, brain and cardiac dysfunction. Important: A patient with Marburg may die from dehydration, shock, acidosis, kidney failure or multiorgan dysfunction without dramatic external bleeding. Early fluid, electrolyte, glucose and organ support are therefore essential. Clinical presentation 1. Early dry phase Abrupt high fever and severe frontal or temporal headache. Severe malaise, profound weakness, chills and myalgia/arthralgia. Photophobia, conjunctival injection, sore throat and anorexia. Nausea and early abdominal discomfort. 2. Gastrointestinal/wet phase From approximately day 3–5, many patients develop watery diarrhoea, repeated vomiting, abdominal pain, chest pain, cough, hiccups, dehydration and rapid weight loss. The combination of high stool/vomit volume and capillary leak can produce shock even before bleeding appears. 3. Rash and bleeding A non-itchy maculopapular rash may appear around days 5–7. Severe disease may cause petechiae, ecchymoses, bleeding from gums and nose, haematemesis, melaena, haematuria, vaginal bleeding or oozing from venepuncture sites. Bleeding is a late and serious sign, but is neither necessary nor sufficient to diagnose MVD. 4. Neurologic, ocular and genital complications Confusion, agitation, drowsiness, seizures, encephalitis or coma. Eye pain, photophobia, uveitis, visual loss or other post-acute ocular disease. Orchitis, testicular pain and possible viral persistence in semen. Pregnancy complications, fetal loss and infection of placental/reproductive tissues. History and examination Risk domain Questions Clinical significance Cave/mine exposure Entering caves, mines or bat habitats; bat contact Strongly supports a possible index exposure Outbreak contact Household, healthcare, funeral or caregiving contact Identifies high-risk contacts requiring monitoring Body-fluid exposure Blood, vomit, diarrhoea, sexual exposure, needlestick Determines urgent occupational/public-health follow-up Symptoms Fever, headache, diarrhoea, vomiting, abdominal pain, rash, bleeding Guides isolation and severity assessment Organ function Urine, glucose, mental state, breathing, visual and testicular symptoms Identifies complications needing specialist care Investigations Safety first Before collecting blood or swabs, notify the reference laboratory and infection-prevention team. Use trained personnel, appropriate PPE, leak-proof triple packaging and approved transport. Never send a suspected high-risk specimen through an ordinary uncoordinated route. Specific tests RT-PCR: detects viral RNA during acute disease and is the principal confirmatory method. Antigen detection: can support early diagnosis in approved reference or field systems. IgM/IgG serology: helps distinguish recent infection or later immune response but may be negative early. Virus isolation/electron microscopy: specialised high-containment methods; electron microscopy identifies filovirus morphology but does not reliably distinguish Marburg from Ebola. Severity assessment Full blood count, platelets, glucose, electrolytes, urea, creatinine and bicarbonate. AST/ALT, bilirubin, albumin,

ebola
Medicine-Infectious Diseases

Ebola Virus Disease: Clinical Features, Diagnosis, Treatment and Outbreak Control

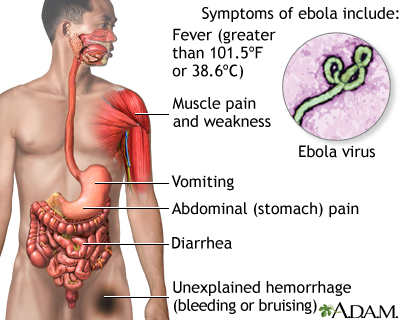
Ebola Virus Disease: Clinical Features, Diagnosis, Treatment and Outbreak Control Clinical Medicine Year 3 • a high-consequence viral haemorrhagic fever requiring early isolation, testing and supportive care Clinical safety note: A patient with fever or unexplained illness plus a compatible travel, outbreak, funeral, healthcare or animal-exposure history must be managed through the national viral-haemorrhagic-fever pathway. Call infection-prevention and public-health teams before collecting specimens or moving the patient. Do not perform unsafe injections, venepuncture or invasive procedures without appropriate PPE, trained staff and a plan for contaminated waste. Why Ebola matters Ebola virus disease (EVD) is a severe zoonotic infection caused by viruses in the genus Orthoebolavirus. It can begin as a nonspecific febrile illness and progress to profuse vomiting and diarrhoea, dehydration, shock, organ failure, coagulopathy, encephalopathy and death. The most important clinical intervention is not waiting for bleeding: early recognition, safe isolation, rapid testing, aggressive supportive care and contact tracing save lives. Ebola is not spread by casual contact before symptoms. Once symptoms begin, however, blood, vomit, stool, urine, breast milk, semen, vaginal fluids, saliva and other body fluids can transmit virus. Patients, caregivers, healthcare workers and people involved in funerals are at greatest risk when body fluids are handled without protection. Learning outcomes Describe Ebola virus structure, species, reservoirs and transmission. Explain the incubation period and the pathophysiology of endothelial, immune and hepatic injury. Recognise early, gastrointestinal, haemorrhagic and neurologic stages. Construct a safe diagnostic approach and distinguish EVD from malaria, typhoid, dengue, yellow fever and other VHF. Plan isolation, supportive care, approved species-specific therapeutics, survivor care and outbreak control. Definition and virology Ebola viruses are enveloped, filamentous, non-segmented, negative-sense single-stranded RNA viruses in the family Filoviridae. Important species include Zaire ebolavirus, Sudan ebolavirus, Bundibugyo ebolavirus, Taï Forest ebolavirus and Reston ebolavirus. Zaire ebolavirus is the species associated with many of the largest human outbreaks; Sudan and Bundibugyo viruses require separate clinical and vaccine considerations. The virion contains nucleoprotein, polymerase-associated proteins, matrix proteins and a surface glycoprotein. The glycoprotein enables attachment and entry into host cells and contributes to endothelial dysfunction and immune evasion. Mononuclear phagocytes, dendritic cells, endothelial cells, hepatocytes and adrenal cells become infected, leading to viraemia and multiorgan injury. Reservoir and transmission The exact natural reservoir is not fully established, but fruit bats are an important suspected reservoir. Human index cases may arise after exposure to infected wildlife or carcasses, followed by human-to-human transmission. Direct contact with blood or body fluids of a symptomatic patient. Contact with a deceased patient during preparation or burial. Unsafe injections, blood transfusion or contaminated instruments. Sexual exposure to survivors because Ebola virus can persist in semen for months. Breast milk and other secretions in selected clinical contexts. Animal exposure, including hunting, butchering or handling sick/dead wildlife. Incubation and communicability The incubation period is approximately 2–21 days, most often about one week. People are generally not infectious before symptoms begin. Infectivity rises with illness severity and is highest when the patient has vomiting, diarrhoea, bleeding or large amounts of virus-containing body fluid. Survivors require structured follow-up because viral persistence in semen, breast milk, ocular fluid or other immune-privileged sites can affect counselling and transmission prevention. Pathophysiology Virus enters through mucosa, broken skin, injection or inhalation of contaminated droplets/aerosols during high-risk procedures. It replicates in macrophages and dendritic cells and spreads through lymphatic tissue and blood. Innate immune signalling is disrupted; infected cells release inflammatory mediators while antigen presentation is impaired. Endothelial injury, cytokines and loss of vascular integrity cause capillary leak, hypotension and tissue oedema. Liver injury reduces clotting-factor synthesis; platelet and coagulation abnormalities produce coagulopathy. Vomiting, diarrhoea, fever and capillary leak cause profound dehydration, electrolyte disturbance, acidosis, kidney injury and shock. Clinical reasoning: Haemorrhage is dramatic but not required for diagnosis. A patient can be in life-threatening Ebola shock because of diarrhoeal fluid loss, capillary leak, acidosis and organ failure before visible bleeding appears. Clinical presentation 1. Early dry phase Early features are nonspecific: sudden fever, severe headache, fatigue, weakness, myalgia, arthralgia, backache, sore throat, conjunctival injection and anorexia. Malaria, typhoid, COVID-19 and other febrile infections may look identical at this stage. 2. Gastrointestinal/wet phase Nausea, repeated vomiting and watery diarrhoea. Abdominal pain, dysphagia, hiccups and profound weakness. Dehydration, postural dizziness, oliguria and electrolyte disturbance. Rash, red eyes and worsening transaminases. Confusion, agitation or reduced consciousness from shock, encephalitis or metabolic abnormalities. 3. Haemorrhagic and multiorgan disease Bleeding may include petechiae, ecchymoses, bleeding from venepuncture sites, gums, nose, gastrointestinal tract, vagina or urinary tract. Severe cases can develop shock, acute kidney injury, hepatitis, hypoglycaemia, respiratory distress, encephalopathy, seizures and multiorgan failure. The amount of external bleeding does not reliably predict severity. 4. Pregnancy and newborn considerations Pregnancy is associated with high maternal and fetal risk. Virus can be present in placenta, amniotic fluid, breast milk and other tissues. Pregnant patients require obstetric, infectious-disease and public-health coordination. Avoid unsafe obstetric procedures; use dedicated protocols for delivery, miscarriage, stillbirth and disposal of contaminated material. Case definition and exposure assessment Ask about Examples Why it changes risk Geography/time Residence or travel in an outbreak area within 21 days Links symptoms to an active transmission chain Contact Care for a suspected case, funeral attendance, blood/body-fluid contact Identifies high-risk exposure and contacts Healthcare Needlestick, unsafe injection, unprotected procedure May require urgent occupational-risk management Animal exposure Hunting, butchering or handling wildlife/primates/bats Possible index-case exposure Symptoms Fever, headache, vomiting, diarrhoea, rash, bleeding, weakness Determines triage and isolation urgency Investigations Routine severity assessment in a safe setting Capillary glucose, pulse oximetry, temperature, respiratory rate, blood pressure and mental state. Full blood count and platelets; leukopenia or thrombocytopenia may occur. Electrolytes, urea, creatinine, bicarbonate, liver tests, bilirubin and albumin. PT/INR, aPTT, fibrinogen and lactate where available. Malaria testing, blood cultures and other differential tests only through safe procedures and approved pathways. Specific Ebola tests RT-PCR: the main acute diagnostic test in blood, usually positive after viraemia develops. Antigen-detection tests: useful in approved field or reference-laboratory settings. Serology: IgM may support recent infection; IgG supports previous exposure or

rift valley fever
Medicine-Infectious Diseases

Rift Valley Fever: Zoonotic Transmission, Clinical Features, Diagnosis and Control

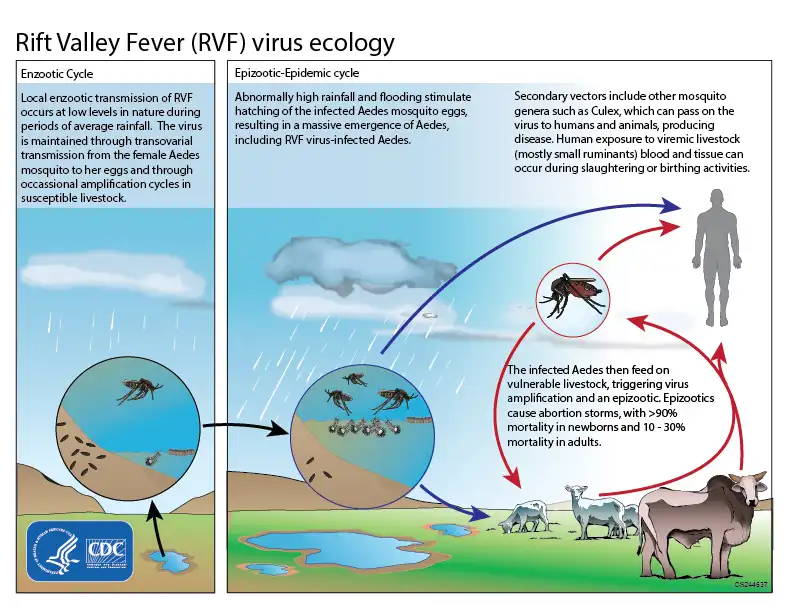
Rift Valley Fever: Zoonotic Transmission, Clinical Features, Diagnosis and Control Clinical Medicine Year 3 • a One Health viral zoonosis affecting people, livestock, mosquitoes and food systems Clinical safety note: Suspected Rift Valley fever (RVF) requires urgent notification, public-health coordination and safe specimen handling. Do not handle blood, aborted tissues, placentas, raw meat or animal carcasses without appropriate PPE and veterinary/public-health guidance. Human treatment is mainly supportive; specialist and reference-laboratory input is essential. Why Rift Valley fever matters Rift Valley fever is a mosquito-borne viral zoonosis that mainly affects livestock but can infect humans. It is clinically important for two reasons: it can cause explosive abortion and neonatal death in sheep, goats and cattle, and it can produce human disease ranging from a short febrile illness to retinitis, meningoencephalitis, haemorrhagic fever, liver failure and death. In Uganda and other African settings, a cluster of livestock abortions, sudden animal deaths and human fever after animal contact should trigger a One Health investigation. The “animal story” is often the clue that distinguishes RVF from malaria, dengue or ordinary viral hepatitis. Learning outcomes Explain RVF virology, vector ecology, animal reservoirs and human exposure routes. Recognise the clinical spectrum from uncomplicated fever to ocular, neurologic and haemorrhagic disease. Construct a safe diagnostic and differential-diagnosis plan. Describe supportive treatment, infection prevention and outbreak control. Apply the One Health relationship between animal vaccination, mosquito control and human protection. Definition and virology RVF virus is an enveloped, segmented, negative-sense RNA virus in the genus Phlebovirus. Modern taxonomy places it in the family Phenuiviridae; older teaching materials may describe it under the former family Bunyaviridae. Its segmented genome allows reassortment, and its ecology is closely linked to mosquitoes, rainfall and livestock amplification. The disease was first recognised in Kenya’s Rift Valley in 1931. It is established in sub-Saharan Africa and has also caused outbreaks in Egypt, the Arabian Peninsula and other regions. The virus primarily circulates between mosquitoes and animals, with humans infected as incidental hosts. Animal hosts and transmission cycle Source/vector How infection occurs Clinical implication Floodwater Aedes mosquitoes Eggs can survive dry periods and hatch after heavy rain/flooding Explains sudden outbreaks after unusual rainfall Other mosquitoes Anopheles, Culex, Mansonia and other genera can amplify and spread virus Outbreak control cannot rely on one mosquito species only Infected livestock Sheep, goats, cattle and camels develop viraemia; pregnant animals may abort Handling blood, placenta, foetus, meat or milk is a major occupational risk Humans Usually a dead-end host; infection follows mosquito bites or animal exposure Human cases can signal an ongoing animal outbreak Routes of human infection Contact with blood, tissues, organs, placenta, aborted foetuses or vaginal secretions of infected animals. Inoculation through cuts, abrasions or contaminated needles. Aerosol exposure during slaughtering, necropsy, butchering or laboratory manipulation. Consumption of raw or inadequately pasteurised milk and possibly undercooked animal products. Bites from infected mosquitoes. There is no evidence of sustained ordinary person-to-person transmission. Nevertheless, blood and tissues from a viraemic patient may expose healthcare workers, laboratory staff and caregivers, so standard precautions and outbreak-specific PPE are essential. Incubation and pathogenesis The human incubation period is commonly about 2–6 days. Virus first replicates at the entry site and lymphoid tissue, followed by viraemia. The liver is a major target, and hepatic necrosis, thrombocytopenia, endothelial injury and inflammatory responses explain fever, jaundice, bleeding and organ failure. In some patients the virus or immune response affects the retina or central nervous system. Exposure through mosquito or infected animal material. Viraemia and systemic inflammatory response. Most patients develop a self-limited influenza-like illness. A small minority develop localised ocular disease, meningoencephalitis or haemorrhagic/hepatic disease. Clinical presentation in humans 1. Uncomplicated febrile illness Many infections are asymptomatic or mild. Symptomatic patients may develop abrupt fever, severe headache, malaise, weakness, myalgia, arthralgia, backache, nausea, vomiting, photophobia and dizziness. Conjunctival injection and mild hepatitis can occur. 2. Ocular disease Retinal vasculitis, macular lesions or retinitis may appear after the systemic illness. Blurred vision, scotomata, photophobia, floaters and reduced visual acuity require urgent ophthalmologic assessment. Visual loss may be permanent even when the fever resolves. 3. Meningoencephalitis Neurologic disease may develop later, with severe headache, neck stiffness, photophobia, confusion, drowsiness, seizures, focal deficits, weakness or coma. Consider RVF in a patient with encephalitis and a compatible livestock/mosquito exposure, while urgently excluding bacterial meningitis, malaria, HSV, TB and other viral infections. 4. Haemorrhagic and hepatic disease Jaundice, hepatomegaly and marked transaminase elevation. Bleeding from gums, nose, gastrointestinal tract or injection sites. Easy bruising, petechiae, haematuria and disseminated intravascular coagulation. Shock, renal failure, hypoglycaemia, encephalopathy and multiorgan failure. Severe-disease alert Persistent vomiting, jaundice, altered mental state, visual symptoms, seizures, active bleeding, hypotension, oliguria, severe thrombocytopenia or rapidly worsening liver tests require admission and specialist escalation. Animal clues that support human RVF During an outbreak, veterinarians may observe sudden large numbers of abortions, high neonatal mortality, fever, weakness, diarrhoea and hepatic necrosis in young livestock. Pregnant ewes and goats can abort at very high rates. These findings are epidemiologically important even if human patients have only mild fever. History and examination History/exam focus Questions and findings Why it matters Animal contact Slaughtering, butchering, assisting births, handling abortions, veterinary work, farming Direct tissue exposure is a major route Animal outbreak Abortion storms, neonatal deaths, livestock illness or unexplained animal deaths Strongly raises suspicion and guides public-health response Mosquito/rainfall exposure Flooding, heavy rains, outdoor work, mosquito abundance Supports vector-borne acquisition Eyes Visual loss, floaters, scotoma, photophobia May indicate retinal disease Neurologic state Headache, neck stiffness, seizures, weakness, confusion Identifies meningoencephalitis Bleeding/liver/kidney Jaundice, bleeding, abdominal pain, urine output, bruising Identifies severe haemorrhagic/hepatic disease Investigations and specimen safety Routine assessment Full blood count and platelets. AST, ALT, bilirubin, albumin, glucose, urea, creatinine and electrolytes. PT/INR, aPTT, fibrinogen and lactate where available. Malaria test, blood cultures and other febrile-illness investigations. CSF studies and brain imaging only when safe and when meningitis/encephalitis is suspected. Ophthalmologic examination for any visual complaint. Specific diagnosis RT-PCR: detects viral RNA early in blood or tissue and is particularly useful during

Dengue Fever
Medicine-Infectious Diseases

Dengue Fever: Clinical Features, Warning Signs, Diagnosis and Management

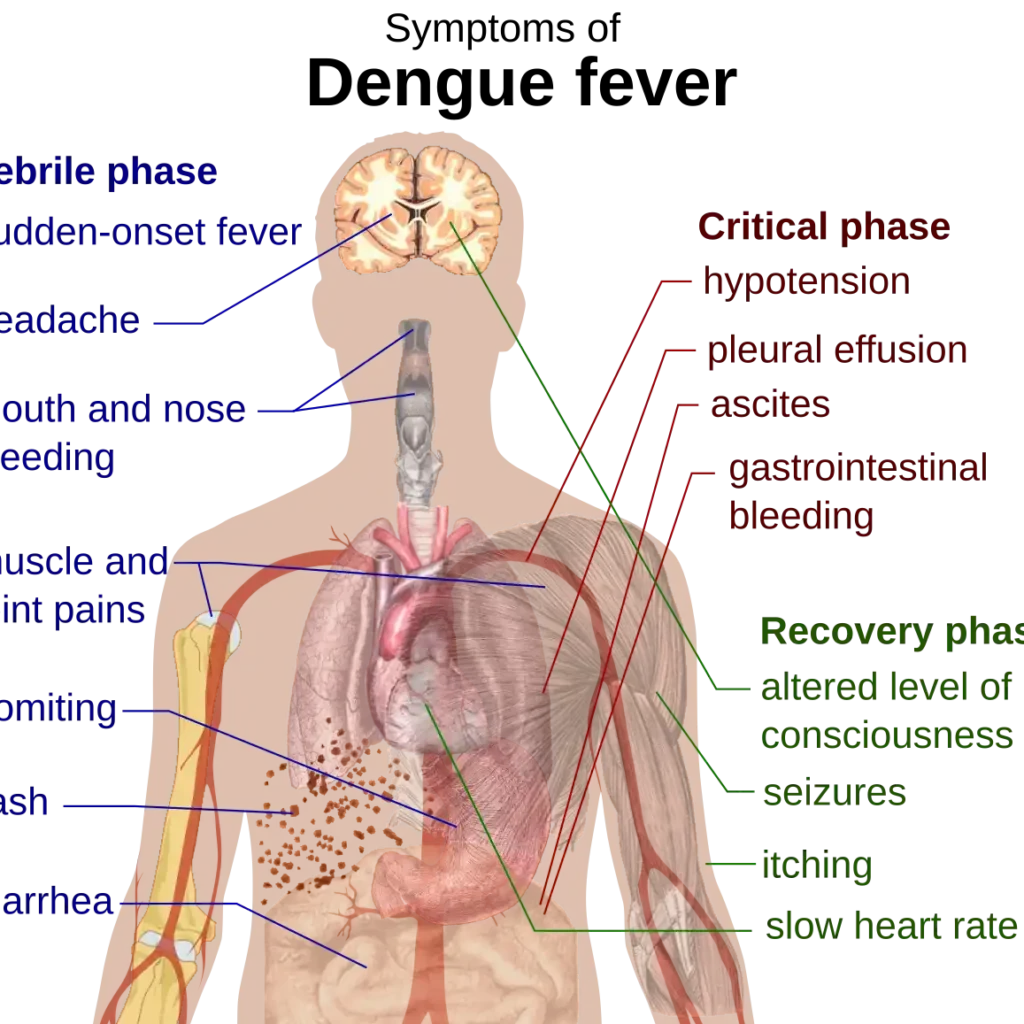
Dengue Fever: Clinical Features, Warning Signs, Diagnosis and Management Clinical Medicine Year 3 • dengue illness, dengue with warning signs, severe dengue and dengue shock Clinical safety note: Dengue can deteriorate rapidly when fever settles and the critical phase begins. Treatment is mainly careful fluid management and monitoring. Avoid aspirin, ibuprofen, diclofenac and intramuscular injections until significant bleeding risk has been excluded. Use current national/WHO/CDC guidance for fluid volumes, admission and paediatric care. Why dengue matters Dengue is an acute infection caused by one of four closely related dengue virus serotypes (DENV-1, DENV-2, DENV-3 and DENV-4). It is transmitted mainly by infected female Aedes aegypti mosquitoes. Most illness is self-limited, but plasma leakage, shock, severe bleeding, liver failure, myocarditis and encephalopathy can develop—often around the time the fever improves. The key bedside skill is to classify the patient repeatedly. A patient who looks stable during the febrile phase may become critically ill during the 24–48-hour critical phase. Serial examination, haematocrit, urine output, pulse pressure and mental state are more useful than a single platelet count. Learning outcomes Explain dengue serotypes, transmission, pathogenesis and the risk of secondary infection. Distinguish undifferentiated dengue, dengue with warning signs and severe dengue. Recognise the febrile, critical and recovery phases. Interpret CBC, haematocrit, liver tests, NS1/PCR and dengue serology. Manage hydration, shock, bleeding, organ dysfunction and safe discharge. Definition, virology and epidemiology Dengue virus is an enveloped, positive-sense single-stranded RNA flavivirus. Infection with one serotype usually gives long-lasting immunity to that serotype but only temporary and incomplete protection against the others. A later infection with a different serotype can be more severe in some patients because pre-existing non-neutralising antibodies may facilitate viral entry into Fc-receptor-bearing cells—an immunologic process called antibody-dependent enhancement. Dengue is endemic in many tropical and subtropical regions. Risk increases with urban crowding, water storage, climate conditions that support mosquito breeding, population movement and low community immunity. Transmission and incubation An infected female Aedes mosquito acquires virus while feeding on a viraemic person. After an extrinsic incubation period in the mosquito, it can transmit dengue during later bites. Mosquitoes commonly bite during daylight, especially in the early morning and late afternoon. Human incubation is usually about 4–10 days. Rare non-vector transmission can occur through blood products, organ transplantation or vertical transmission. Pathophysiology: why severe dengue causes shock Virus replicates in dendritic cells, monocytes and macrophages and triggers innate immune responses. Cytokines, complement and endothelial mediators alter vascular permeability. In severe disease, plasma leaks from the intravascular space into the pleural and abdominal cavities while red cells remain intravascular. Intravascular volume falls even though the patient may appear oedematous. Haematocrit rises because plasma is lost but red cells are concentrated. If leakage is untreated, tissue perfusion fails, causing metabolic acidosis, organ injury and shock. Platelet destruction, marrow suppression and coagulopathy contribute to mucosal or gastrointestinal bleeding. Interpretation principle: In a patient with warning signs, a rising haematocrit with a falling platelet count suggests ongoing plasma leakage. A falling haematocrit in a shocked patient may instead indicate bleeding or haemodilution after fluids. Clinical phases Phase Typical timing What to look for Febrile Usually 2–7 days High fever, headache, retro-orbital pain, myalgia, arthralgia, nausea, vomiting, rash, mild bleeding and leukopenia Critical Often around defervescence; about 24–48 hours Capillary leakage, rising haematocrit, narrow pulse pressure, shock, fluid accumulation, severe bleeding or organ dysfunction Recovery After leakage stops Reabsorption of fluid, improved appetite/urine, slowing pulse, convalescent rash and sometimes transient bradycardia Clinical manifestations Uncomplicated dengue Sudden high fever, chills and severe headache. Retro-orbital pain, photophobia and marked muscle, bone or joint pains (“breakbone fever”). Nausea, vomiting, anorexia and abdominal discomfort. Macular or maculopapular rash, facial flushing and pruritus during recovery. Mild gum or nose bleeding, petechiae or a positive tourniquet test may occur. Leukopenia and thrombocytopenia are common; not every low platelet count means severe disease. Warning signs Severe abdominal pain or abdominal tenderness. Persistent vomiting or inability to maintain oral fluids. Clinical fluid accumulation: ascites, pleural effusion or pericardial effusion. Mucosal bleeding, haematemesis, melaena, haematuria or heavy vaginal bleeding. Lethargy, restlessness, irritability, confusion or reduced Glasgow Coma Scale. Enlarged tender liver. Progressively rising haematocrit, especially with rapidly falling platelets. Reduced urine output, cold extremities, tachycardia or narrowing pulse pressure. Severe dengue Severe dengue is diagnosed when there is one or more of: Severe plasma leakage causing shock or respiratory distress from fluid accumulation. Severe bleeding judged clinically important, especially with haemodynamic compromise. Severe organ involvement: AST/ALT often very high, encephalitis/encephalopathy, myocarditis, arrhythmia, acute kidney injury or other organ failure. History and examination Assess Questions/examination Clinical decision Timing Day of illness, day fever settled, prior dengue and travel/outbreak exposure Predicts the transition into the critical phase Hydration Oral intake, vomiting, thirst, mucosa, capillary refill, urine volume Determines oral versus IV fluids Circulation Pulse, systolic/diastolic BP, pulse pressure, extremity temperature, mental state Detects compensated shock before hypotension Leakage/bleeding Abdominal tenderness, ascites, pleural signs, gums, stool, urine, menstrual loss Guides admission and blood-product decisions Organ function Glucose, liver size, jaundice, neurologic state, chest findings, ECG Identifies severe dengue and ICU needs Special groups Pregnancy, infancy, elderly age, obesity, renal/cardiac disease Requires lower threshold for observation and careful fluid titration Investigations Baseline and serial tests Full blood count: leukopenia, thrombocytopenia and serial haematocrit. Haematocrit should be interpreted with the fluid history and bleeding assessment. Urea, creatinine, electrolytes, glucose, AST/ALT, bilirubin and albumin. Coagulation profile when bleeding, liver failure or severe illness is suspected. Chest radiograph or ultrasound for pleural effusion, ascites and pulmonary oedema. ECG/troponin/echocardiography when myocarditis or arrhythmia is suspected. Malaria testing and cultures when clinically indicated; dengue and malaria can coexist. Specific dengue tests RT-PCR: detects viral RNA early in illness and can identify serotype. NS1 antigen: useful in the early febrile period, although sensitivity varies by serotype and whether infection is primary or secondary. IgM: usually becomes detectable after approximately day 4–5 and remains detectable for weeks to months. IgG: a single positive result often indicates previous flavivirus exposure; paired sera or a fourfold rise is more

yellow fever
Medicine-Infectious Diseases

Yellow Fever: Clinical Features, Diagnosis, Management and Prevention

Yellow Fever: Clinical Features, Diagnosis, Management and Prevention Clinical Medicine Year 3 • an African arboviral disease with hepatic, renal and haemorrhagic complications Clinical safety note: Suspected yellow fever is a notifiable public-health emergency. Isolate the patient from mosquitoes, notify the health authorities, obtain expert laboratory advice and manage in hospital. There is no routine specific antiviral cure; survival depends on early recognition, careful supportive care and prevention of complications. Why yellow fever matters Yellow fever is an acute mosquito-borne viral haemorrhagic disease caused by yellow fever virus, a flavivirus. It ranges from an asymptomatic or mild febrile illness to a toxic phase with jaundice, coagulopathy, shock, renal failure, encephalopathy and death. Because early yellow fever can look like malaria, viral hepatitis, dengue or sepsis, the diagnosis is often missed unless the clinician asks about mosquito exposure, travel, vaccination and outbreaks. The word “yellow” refers to jaundice from hepatic injury. The disease is not spread by ordinary casual contact, but a patient with circulating virus can infect a mosquito that later bites another person. Early mosquito precautions therefore protect both the patient and the community. Learning outcomes Describe the virus, vectors, reservoirs and jungle, intermediate and urban transmission cycles. Explain the clinical phases from incubation through acute and toxic disease. Recognise jaundice, bleeding, shock, renal failure and encephalopathy as danger signs. Choose appropriate laboratory tests and distinguish yellow fever from malaria, hepatitis, dengue and other severe febrile diseases. Provide safe supportive management and explain vaccination, mosquito control and outbreak response. Definition and virology Yellow fever virus is an enveloped, positive-sense single-stranded RNA virus in the genus Flavivirus. It is an arbovirus because it is transmitted by arthropods. The virus has a strong tropism for hepatocytes, reticuloendothelial cells and other tissues. Viral replication, apoptosis and inflammatory injury can produce midzonal hepatic necrosis, cholestasis, coagulopathy and multiorgan dysfunction. Epidemiology and transmission cycles Yellow fever remains endemic in tropical parts of Africa and South America. Uganda is within the African risk zone, so a febrile jaundiced patient with mosquito exposure or an outbreak connection requires serious consideration of yellow fever alongside malaria and viral hepatitis. Cycle Reservoir and vector Clinical/public-health meaning Sylvatic (jungle) Non-human primates and forest mosquitoes; humans enter the cycle when they work or travel in forest Occupational and travel-related cases; primate deaths may precede human cases Intermediate (savannah) Forest-edge mosquitoes infect monkeys and humans in rural or semi-rural areas Can cause rural outbreaks and bridge infection toward towns Urban Infected humans and peridomestic Aedes mosquitoes, especially Aedes aegypti Rapid explosive outbreaks where population immunity is low An infected mosquito becomes capable of transmission after an extrinsic incubation period. Humans are most infectious to mosquitoes around the early viraemic days of illness. A person does not normally infect another person directly by touch, coughing or sharing food. Risk factors Living in or visiting a yellow-fever-endemic area without vaccination. Forest work, farming, hunting, logging, fishing or outdoor night/day exposure depending on the vector. Low community vaccine coverage, urban crowding and abundant breeding sites. Immunosuppression or advanced age, which may increase the risk of severe vaccine adverse effects or severe natural disease. Pregnancy and young infancy require careful vaccine-risk decisions in a travel or outbreak context. Pathophysiology After a mosquito bite, virus replicates locally and enters lymphatic tissue. Viraemia disseminates virus to the liver, spleen, lymph nodes, kidney and bone marrow. Hepatocyte injury causes jaundice, raised aminotransferases, impaired clotting-factor synthesis and hypoglycaemia. Systemic endothelial injury, cytokines and coagulation abnormalities produce bleeding, capillary leak and shock. Acute kidney injury results from shock, direct injury and pigment/volume effects; encephalopathy may reflect hepatic failure, shock or metabolic derangement. Teaching link: In yellow fever, jaundice is not simply a liver-test abnormality. It is a visible marker of a disease process that can simultaneously disturb clotting, glucose control, kidney perfusion and brain function. Clinical course 1. Incubation phase Symptoms commonly begin about 3–6 days after an infective mosquito bite. The patient is usually well during incubation. 2. Acute febrile phase This phase usually lasts several days and may include sudden fever, chills, severe headache, backache, myalgia, arthralgia, nausea, vomiting, photophobia, weakness and facial flushing. Conjunctival injection and relative bradycardia may be present. Laboratory findings can include leukopenia, thrombocytopenia, raised transaminases and mild proteinuria. 3. Remission phase Many patients improve after the initial fever. A short remission does not always mean cure; clinicians must warn patients to return if jaundice, bleeding, severe abdominal pain, reduced urine, confusion or recurrent fever appears. 4. Toxic phase A minority progress to severe disease, often after apparent improvement. Findings include: Jaundice, dark urine, pale stool and tender hepatomegaly. Persistent vomiting, epigastric or right-upper-quadrant pain. Bleeding from gums, nose, gastrointestinal tract, injection sites or uterus; petechiae and ecchymoses. Hypotension, narrow pulse pressure, cold extremities, oliguria and metabolic acidosis. Acute kidney injury, haematuria and reduced urine output. Hypoglycaemia, agitation, drowsiness, seizures or hepatic encephalopathy. Myocarditis, arrhythmias, respiratory failure, disseminated intravascular coagulation and multiorgan failure. Bedside danger signs Jaundice plus bleeding, persistent hypotension, altered mental state, oliguria, hypoglycaemia, severe abdominal pain, rapidly rising INR, severe thrombocytopenia or worsening creatinine should be treated as toxic yellow fever until proven otherwise. History and examination Ask or examine Why it matters Onset, travel and residence Links illness to endemic area or a known outbreak and estimates incubation. Vaccination card and prior yellow fever A documented vaccine or past infection greatly changes probability, but does not replace testing in a compatible outbreak. Mosquito and forest exposure Identifies sylvatic or urban risk. Malaria tests and treatment Failure to improve after appropriate antimalarial therapy should prompt a wider differential. Bleeding and urine output Detects coagulopathy and kidney injury early. Neurologic state and glucose Encephalopathy and hypoglycaemia are potentially reversible emergencies. Jaundice, hydration, shock, hepatosplenomegaly Assesses severity and need for admission/critical care. Investigations Initial severity assessment Full blood count with platelet count and haematocrit. Urea, creatinine, electrolytes, glucose and urinalysis. AST, ALT, bilirubin, albumin and alkaline phosphatase. PT/INR, aPTT, fibrinogen and lactate where available. Blood group and cross-match if bleeding or severe

Cytomegalovirus
Medicine-Infectious Diseases

Cytomegalovirus (CMV) Infection: Clinical Features, Diagnosis and Management

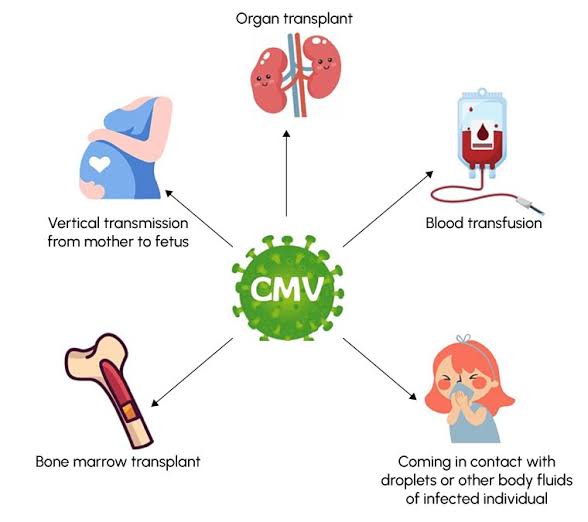
Cytomegalovirus (CMV) Infection: Clinical Features, Diagnosis and Management Clinical Medicine Year 3 • CMV in immunocompetent people, pregnancy, newborns, HIV and transplant patients Clinical safety note: CMV treatment is specialist-directed. Doses, duration, renal adjustment, pregnancy decisions and newborn treatment must follow the current Uganda Clinical Guidelines, local laboratory capability and infectious-disease/paediatric advice. Ganciclovir, valganciclovir, foscarnet and cidofovir can cause serious marrow, renal and reproductive toxicity. Why CMV matters Cytomegalovirus is a ubiquitous human herpesvirus that usually produces silent or mild infection in an immunocompetent host but can cause destructive disease when cellular immunity is immature or impaired. The same virus therefore has very different meanings in a healthy adult, a pregnant woman, a newborn, a person with advanced HIV, and a transplant recipient. The important clinical question is not simply “Is CMV present?” Many healthy adults remain CMV-IgG positive for life. The clinically useful question is: Is there evidence of recent infection, viral replication, tissue-invasive disease, or congenital infection in a vulnerable patient? Learning outcomes Explain CMV classification, latency, reactivation and the major routes of transmission. Distinguish primary infection, reinfection, reactivation, congenital infection and perinatal infection. Recognise CMV mononucleosis, congenital CMV, retinitis, pneumonitis, gastroenteritis, encephalitis and disseminated disease. Select and interpret PCR, serology, antigen testing, histology, ophthalmology and newborn tests. Plan supportive care, antiviral induction/maintenance, monitoring, prevention and follow-up. Definition and virology CMV, also called human herpesvirus type 5 (HHV-5), is an enveloped double-stranded DNA virus in the Herpesviridae family and Betaherpesvirinae subfamily. It has a large genome and replicates slowly. Infected cells enlarge and may show basophilic intranuclear inclusions surrounded by a clear halo—the classic “owl-eye” appearance—although immunohistochemistry and molecular tests are now more sensitive in many settings. Like other herpesviruses, CMV persists after the first infection. Latent virus remains mainly in cells of the monocyte/macrophage lineage and other tissues. Immunosuppression, inflammation, transplantation, HIV immune failure or severe illness can allow reactivation and renewed viral replication. Epidemiology and risk groups CMV infection is common worldwide, with seroprevalence varying by age, crowding, breastfeeding, sexual exposure and socioeconomic conditions. A positive CMV-IgG result is therefore common and does not by itself prove active disease. Patient group Why disease may be severe Typical clinical concern Immunocompetent adult Usually effective T-cell control Asymptomatic infection or heterophile-negative mononucleosis Pregnant woman and fetus Placental transmission can injure the developing brain, ear, eye and growth pathways Congenital CMV, fetal growth restriction, sensorineural hearing loss Newborn, especially preterm Immature cellular and humoral immunity Sepsis-like illness, pneumonitis, hepatitis, thrombocytopenia Advanced HIV Low CD4-mediated immunity permits tissue invasion Retinitis, colitis, oesophagitis, encephalitis and disseminated disease Solid-organ or stem-cell transplant recipient Immunosuppressive drugs and donor/recipient mismatch Viral syndrome, pneumonitis, graft dysfunction and opportunistic coinfection Transmission CMV is present in saliva, urine, blood, semen, vaginal secretions, cervical secretions, breast milk and transplanted tissues. Transmission normally requires close or repeated contact rather than casual contact across a room. Congenital: transplacental infection during pregnancy after maternal primary infection, reinfection or reactivation. Primary infection generally carries the greater fetal risk, but reactivation can still transmit. Perinatal: exposure to genital secretions during delivery and breast milk. In a term infant this is often asymptomatic; very premature infants can develop clinically important disease. Child-to-child: saliva and urine from toddlers are important sources. Sharing utensils, kissing on the mouth and contact with nappies can transmit virus. Sexual: semen and cervical/vaginal secretions. Blood and organs: transfusion of infected cellular products and transplantation from a CMV-positive donor. Pathogenesis: how latent virus becomes disease CMV enters mucosal or damaged tissue cells and spreads locally and through blood leukocytes. The immune system usually suppresses replication but does not eradicate the virus. Latency is maintained in monocytes and progenitor cells; inflammation or immunosuppression activates viral gene expression. New virions infect endothelial, epithelial, stromal and neural tissues. The resulting tissue injury may be direct viral cytopathy plus immune-mediated inflammation. In pregnancy, placental infection can impair fetal growth and neurodevelopment. In advanced HIV, inadequate T-cell control permits high viral load and destructive retinitis, colitis or encephalitis. Clinical reasoning: CMV disease is most likely when a compatible organ syndrome occurs in a patient with impaired cellular immunity and there is evidence of viral replication or tissue invasion. Detecting CMV DNA in blood alone does not prove that CMV caused a particular symptom. Clinical presentations 1. Asymptomatic infection Most infections in children and healthy adults are silent. The patient may have no illness but can intermittently shed CMV in saliva or urine for months or years. A positive IgG often represents remote infection rather than current disease. 2. CMV mononucleosis in an immunocompetent host After an incubation period commonly measured in weeks, some adolescents and adults develop prolonged fever, profound fatigue, malaise, myalgia, headache, sore throat, cervical or generalised lymphadenopathy and mild hepatitis. Atypical lymphocytosis and raised transaminases are common. Unlike Epstein–Barr virus mononucleosis, prominent exudative tonsillitis and heterophile antibody positivity are less typical. Usually self-limited over several weeks. Possible complications include hepatitis, haemolysis, thrombocytopenia, myocarditis, pneumonitis, meningoencephalitis and Guillain–Barré syndrome, but these are uncommon in healthy people. 3. Congenital CMV Congenital CMV means infection acquired before birth. Some infants are normal at birth but later develop hearing loss or developmental difficulty. Symptomatic disease may include: Intrauterine growth restriction, prematurity and poor feeding. Microcephaly, seizures, hypotonia or abnormal neurologic examination. Periventricular calcifications, ventriculomegaly, white-matter abnormalities or cortical malformations. Petechiae and purpura (“blueberry muffin” appearance), thrombocytopenia and anaemia. Jaundice, hepatosplenomegaly, hepatitis and cholestasis. Chorioretinitis, optic abnormalities and sensorineural hearing loss. Congenital versus perinatal infection Testing after the first few weeks becomes difficult because urine or saliva PCR may reflect postnatal acquisition. To confirm congenital infection, test saliva or urine by PCR as soon as possible and ideally within the first 21 days of life. A positive test beyond this window cannot reliably distinguish congenital from perinatal infection without stored newborn samples or additional evidence. 4. CMV disease in advanced HIV CMV disease is classically associated with severe immune suppression, particularly a very low CD4 count, although effective ART has reduced its frequency. Presentations include: Retinitis: painless

Scroll to Top