
The pharyngeal apparatus: arches, pouches, clefts & congenital anomalies
On this page
Overview & germ layers
The pharyngeal apparatus (historically termed the branchial apparatus due to its evolutionary homology with the gill machinery of aquatic vertebrates) constitutes the primary embryological foundation for the development of the face, oral cavity, neck, pharynx, larynx, and associated endocrine and lymphoid glands.
During the fourth and fifth weeks of human intrauterine development, tissues on the ventrolateral aspect of the embryonic head and neck undergo dramatic morphological folding. The pharyngeal apparatus forms as a bilateral series of rounded mesodermal ridges that emerge sequentially in a craniocaudal gradient on either side of the primitive foregut, extending from the level of the future ear down toward the epicardial ridge.

Tri-Germ Layer Organization
The pharyngeal apparatus represents a unique developmental convergence where all three primary germ layers, augmented by specialized cranial neural crest cells (ectomesenchyme), interact through tightly coordinated epithelial-mesenchymal signaling cascades:
- Outer Surface Ectoderm: Covers the external lateral surface of the embryo, forming the epithelial lining of the pharyngeal clefts and the future cutaneous epithelium of the face and neck.
- Inner Foregut Endoderm: Lines the pharynx internally, forming the lateral outpocketings known as pharyngeal pouches, which give rise to the epithelial lining of the middle ear cavity, palatine tonsillar crypts, parathyroid glands, thymus, and thyroid follicular and parafollicular cells.
- Intermediate Mesenchyme: Sandwiched between the outer ectoderm and inner endoderm, composed of a mixture of:
- Mesoderm: Derived from paraxial mesoderm (occipital and pre-otic somites) and lateral plate mesoderm, forming all voluntary striated branchiomeric musculature and cardiovascular endothelial channels.
- Cranial Neural Crest Cells (Ectomesenchyme): Migrate from the margins of the fusing neural tube (mesencephalon and rhombencephalon) into the arches, differentiating into the facial viscerocranium, cartilages, middle ear ossicles, tendons, dermis, and vascular smooth muscle.
The four apparatus components
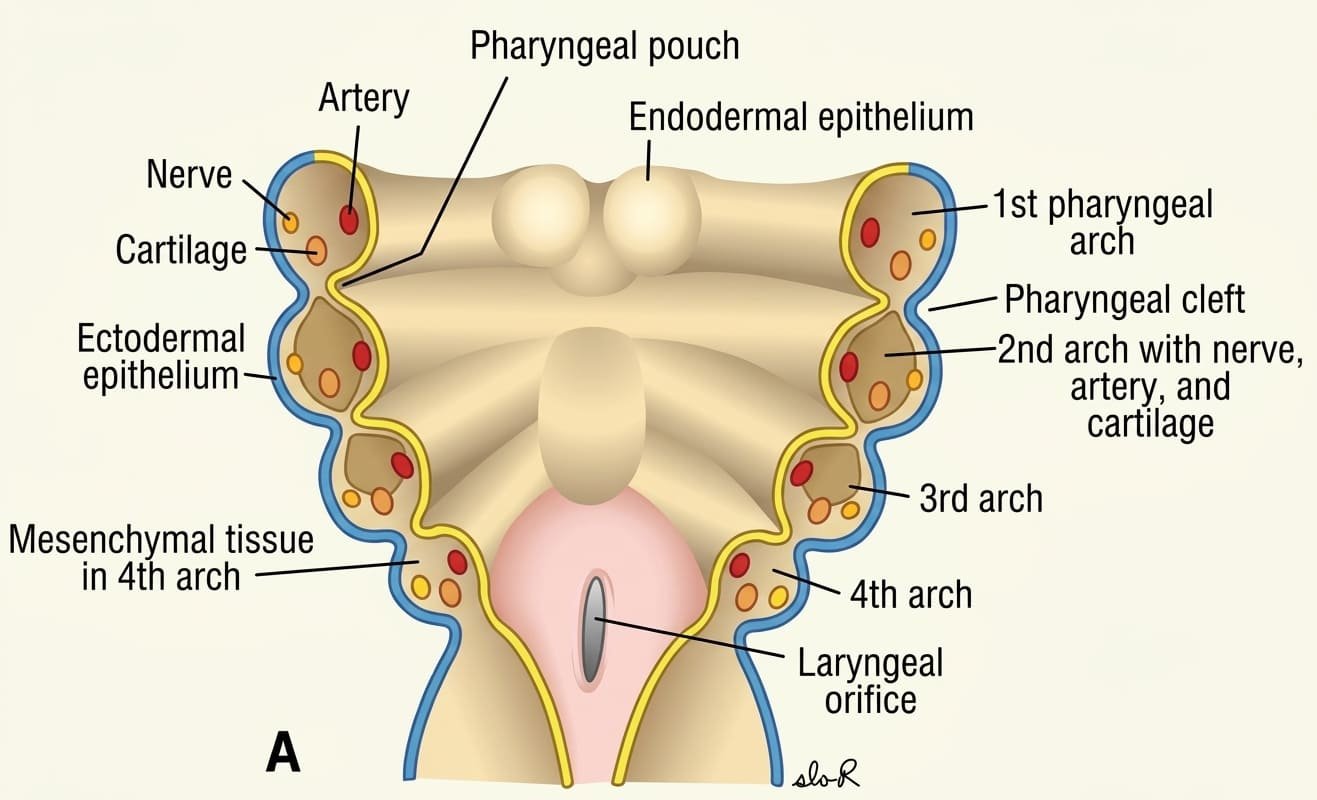
The pharyngeal apparatus consists of four distinct architectural elements arranged symmetrically along the embryonic foregut wall:
- Pharyngeal Arches: Transverse paired bars or cylindrical masses of mesenchyme bounded externally by ectoderm and internally by endoderm. Six pairs of arches form in human embryos, numbered craniocaudally 1 to 6 (the fifth arch is rudimentary and regresses rapidly, leaving arches 1, 2, 3, 4, and 6 to develop).
- Pharyngeal Pouches: Lateral, balloon-like outpocketings of endodermal epithelium arising from the lateral walls of the primitive foregut (pharynx), protruding between adjacent internal arches. There are four pairs of well-defined pouches (with a rudimentary fifth pouch usually joining the fourth).
- Pharyngeal Clefts (Grooves): Invaginating external indentations of surface ectoderm separating adjacent external arches. There are four pairs of pharyngeal clefts.
- Pharyngeal Membranes: Delicate, bilaminar septa formed at the bottom of the grooves where external ectoderm comes into direct contact with internal endoderm due to the transient migration of intervening mesoderm. Four pairs form initially.
Facial prominences & stomodeum
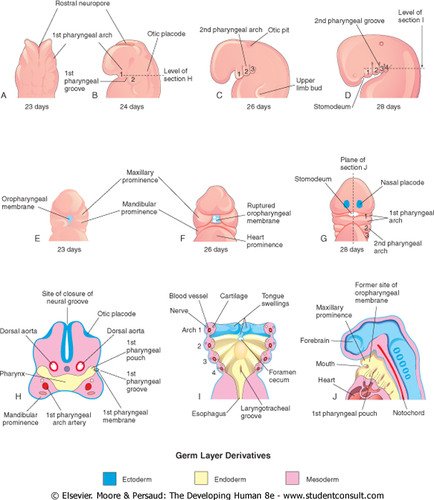
The pharyngeal arches contribute not only to cervical structures, but directly build the human face. At the end of the fourth week, the center of the developing embryonic face is dominated by a central depression called the stomodeum (the primitive mouth cavity). The stomodeum is initially separated from the blind-ended cranial foregut by the bilaminar oropharyngeal (buccopharyngeal) membrane, which ruptures around embryonic day 26 to establish continuity between the amniotic cavity and the primitive gut.

The Five Primary Mesenchymal Prominences (Day 42)
Surrounding the stomodeum are five distinct mesenchymal facial buds formed by active neural crest proliferation:
- 1. Frontonasal Prominence (Unpaired): Forms the cranial boundary of the stomodeum. Originates from mesenchyme ventral to the developing forebrain; later develops nasal placodes, giving rise to the forehead, nasal bridge, and nasal septum.
- 2 & 3. Maxillary Prominences (Paired): Form the lateral boundaries of the stomodeum. Derived from the dorsal portion of the first pharyngeal arch; gives rise to the upper cheeks, secondary palate, and the majority of the upper lip.
- 4 & 5. Mandibular Prominences (Paired): Form the caudal boundary of the stomodeum. Derived from the ventral portion of the first pharyngeal arch; fuses across the midline to form the lower jaw (mandible), chin, and lower lip.
Facial development is completed during the fifth to eighth weeks by the formation and fusion of the medial and lateral nasal prominences around the invaginating nasal pits.
Arch architecture & nerves
Every individual pharyngeal arch possesses an identical structural blueprint, containing four primary internal functional elements within its core of mesenchyme and ectomesenchyme:
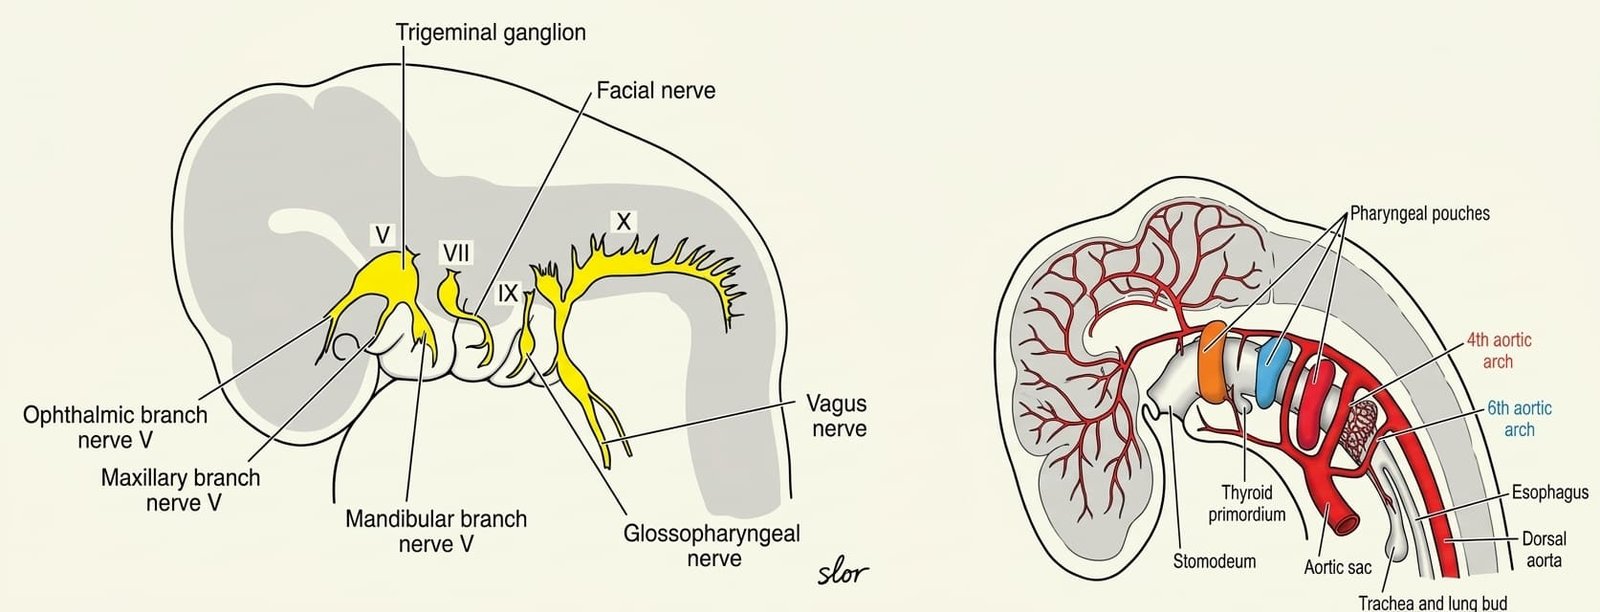
- Aortic Arch Artery: An arterial vessel arising ventrally from the aortic sac that traverses the arch to terminate dorsally in the paired dorsal aortae.
- Cartilaginous Rod: A skeletal core derived from cranial neural crest cells that provides physical scaffolding and later undergoes endochondral or membranous ossification.
- Muscular Component: A myogenic cluster derived from paraxial/lateral plate mesoderm that differentiates into striated branchiomeric skeletal muscles.
- Cranial Nerve (Branchiomeric Nerve): A specific cranial nerve that grows into the arch from the brainstem to supply sensory and motor innervation to all tissues derived from that specific arch. When muscle tissue migrates away from its arch of origin during subsequent fetal development, it carries its ancestral cranial nerve supply with it.

First pharyngeal arch (mandibular arch)
The first pharyngeal arch (mandibular arch) is the most cranial and largest arch, dividing early into a smaller dorsal maxillary process and a larger ventral mandibular process.
1. Skeletal Derivatives & Meckel’s Cartilage
- Maxillary Process (Dorsal Portion): Extends forward beneath the developing optic cup. Through intramembranous ossification of neural-crest-derived mesenchyme, it forms the maxilla, premaxilla, zygomatic bone, and the squamous part of the temporal bone.
- Mandibular Process (Ventral Portion): Contains the cartilaginous bar of the first arch, known as Meckel’s cartilage.
- The vast majority of Meckel’s cartilage regresses and disappears as the surrounding mesenchyme undergoes intramembranous ossification to form the bony mandible.
- The dorsal extremity of Meckel’s cartilage detaches and undergoes endochondral ossification to form two middle ear auditory ossicles: the malleus and the incus.
- The fibrous perichondrium of Meckel’s cartilage persists as two adult fibrous bands: the anterior ligament of the malleus and the sphenomandibular ligament.
2. Muscular Derivatives
The mesodermal core of the first arch differentiates into:
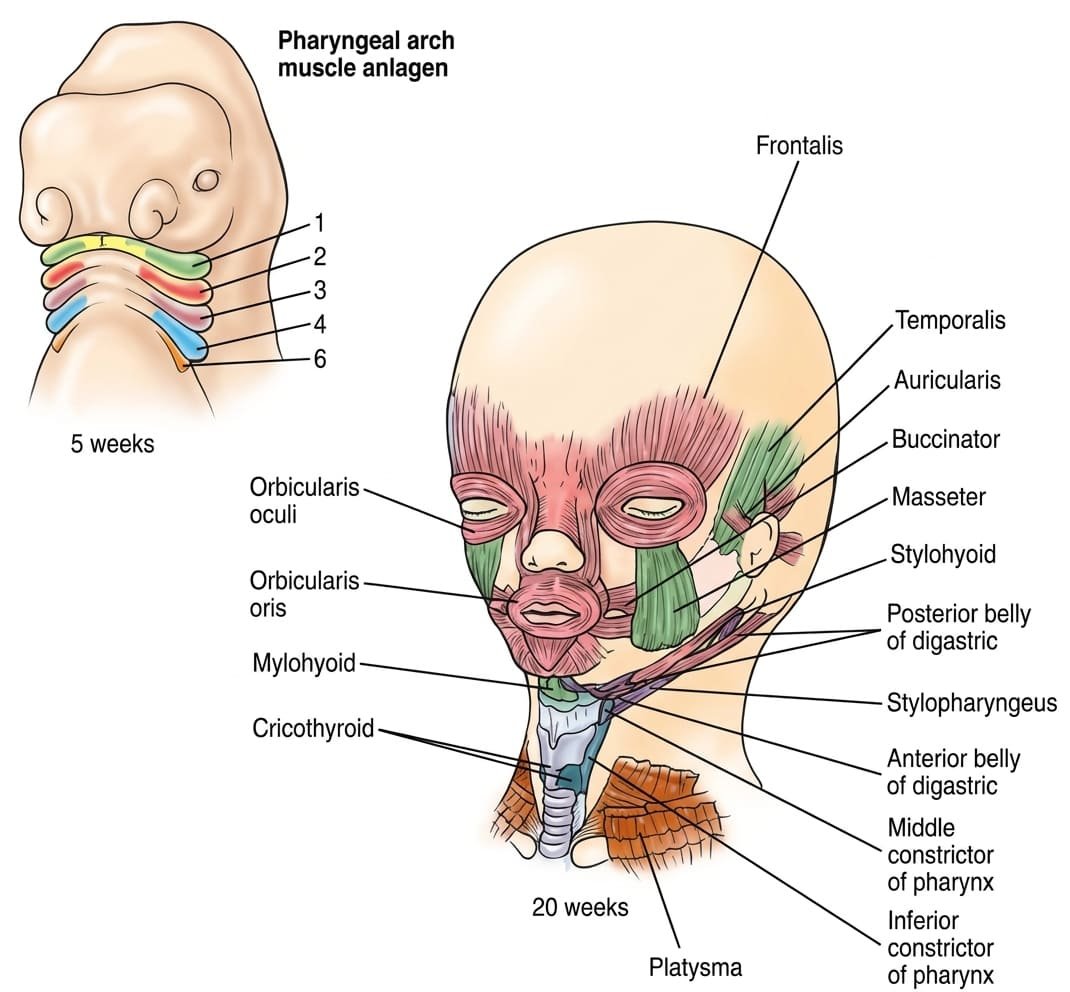
- The four primary muscles of mastication: temporalis, masseter, medial pterygoid, and lateral pterygoid.
- Mylohyoid and the anterior belly of the digastric (suprahyoid floor of mouth).
- Tensor tympani (middle ear muscle that dampens sound from chewing by pulling the malleus medially).
- Tensor veli palatini (tenses the soft palate and dilates the Eustachian tube).
3. Innervation & Vascular Supply
- Nerve of the First Arch: The trigeminal nerve (CN V).
- Motor supply to all first arch muscles is provided exclusively by the mandibular division (CN V3).
- Sensory supply to the overlying facial skin and oral mucosa is provided by all three branches: ophthalmic (V1), maxillary (V2), and mandibular (V3). The mandibular nerve also supplies general somatic sensation to the anterior two-thirds of the tongue via the lingual nerve.
- Vascular Supply: The first aortic arch artery largely regresses, with its remnants persisting as the maxillary artery and contributing to the external carotid artery.
Second pharyngeal arch (hyoid arch)
The second pharyngeal arch (hyoid arch) plays a major role in the development of the facial muscles, middle ear, and hyoid bone.
1. Skeletal Derivatives & Reichert’s Cartilage
The cartilaginous rod of the second arch is Reichert’s cartilage. It undergoes endochondral ossification to yield:
- The stapes (the innermost middle ear auditory ossicle).
- The styloid process of the temporal bone.
- The fibrous stylohyoid ligament (formed by the ossified sheath/perichondrium of the middle segment of Reichert’s cartilage).
- Ventrally: the lesser horn (cornu) and the upper part of the body of the hyoid bone.
2. Muscular Derivatives
Second arch mesoderm expands and migrates widely beneath the facial skin, differentiating into:
- All muscles of facial expression (including orbicularis oculi, orbicularis oris, buccinator, platysma, frontalis, occipitalis, and zygomaticus).
- The stapedius muscle (middle ear muscle that dampens sound oscillations of the stapes footplate).
- The stylohyoid muscle.
- The posterior belly of the digastric muscle.
- The auricular muscles of the external ear.
3. Innervation & Vascular Supply
- Nerve of the Second Arch: The facial nerve (CN VII). Supplies motor control to all muscles of facial expression and conveys special visceral afferent (taste) fibers from the anterior two-thirds of the tongue via the chorda tympani.
- Vascular Supply: The second aortic arch artery regresses in adults; its remnant forms the transient embryonic stapedial artery (which degenerates, leaving the caroticotympanic artery).
Third pharyngeal arch
The third pharyngeal arch contributes selectively to the deeper visceral anatomy of the pharynx and hyoid apparatus.
1. Skeletal Derivatives
The cartilage of the third arch undergoes endochondral ossification to form:
- The greater horn (cornu) of the hyoid bone.
- The lower part of the body of the hyoid bone (fusing with the upper body derived from the second arch).
2. Muscular Derivatives
Muscular differentiation of the third arch is restricted to a single skeletal muscle: the stylopharyngeus muscle, which elevates the pharynx and larynx during deglutition.
3. Innervation & Vascular Supply
- Nerve of the Third Arch: The glossopharyngeal nerve (CN IX). Provides motor innervation to the stylopharyngeus muscle and general somatic/special visceral afferent (taste) sensation to the posterior one-third of the tongue.
- Vascular Supply: The third aortic arch artery gives origin to the common carotid artery and the proximal segment of the internal carotid artery (the remainder of the internal carotid being formed by the cranial extension of the dorsal aorta).
Fourth & sixth pharyngeal arches
The fourth and sixth pharyngeal arches develop in close anatomical association around the laryngotracheal diverticulum. The fifth arch is fleeting and forms no permanent adult structures.
1. Skeletal Derivatives
The cartilages of the fourth and sixth arches fuse together to establish the cartilaginous framework of the larynx:
- Thyroid cartilage (including the superior and inferior cornu).
- Cricoid cartilage.
- Arytenoid cartilages.
- Corniculate cartilages.
- Cuneiform cartilages.
Embryological Note: The epiglottis does not arise from the arch cartilages; it differentiates from the hypopharyngeal eminence (derived from third and fourth arch endodermal mesenchyme).
2. Muscular Derivatives & Vagal Innervation
Both arches are innervated by distinct branches of the vagus nerve (CN X):
- Fourth Arch Musculature: Differentiates into the cricothyroid muscle (the only intrinsic laryngeal muscle that tenses the vocal folds), the levator veli palatini, and the pharyngeal constrictor muscles (superior, middle, and inferior constrictors).
→ Nerve Supply: The superior laryngeal nerve (specifically the external laryngeal nerve branch of CN X). - Sixth Arch Musculature: Differentiates into all the remaining intrinsic muscles of the larynx (posterior cricoarytenoid, lateral cricoarytenoid, transverse/oblique arytenoids, and thyroarytenoid/vocalis) and the striated muscle of the upper esophagus.
→ Nerve Supply: The recurrent (inferior) laryngeal nerve of CN X.
3. Vascular Remodeling of the 4th & 6th Aortic Arches
Asymmetrical Arterial Transformations
- Fourth Aortic Arch Arteries:
- Left Fourth Arch: Persists as a major segment of the definitive arch of the aorta (connecting the aortic sac to the left dorsal aorta).
- Right Fourth Arch: Persists as the proximal segment of the right subclavian artery (distal segments deriving from the right seventh intersegmental artery and dorsal aorta).
- Sixth Aortic Arch Arteries (Pulmonary Arches):
- Left Sixth Arch: Proximal portion forms the proximal left pulmonary artery; distal portion persists throughout fetal life as the ductus arteriosus (shunting deoxygenated blood from the pulmonary trunk to the aorta), which closes postnatally to become the fibrous ligamentum arteriosum.
- Right Sixth Arch: Proximal portion forms the proximal right pulmonary artery; distal portion degenerates completely.


Pharyngeal pouches & descent
The human embryo develops five pairs of internal endodermal outpocketings: the pharyngeal pouches. The fifth pouch is typically considered a subordinate, caudal divergence of the fourth pouch.

1. First Pharyngeal Pouch
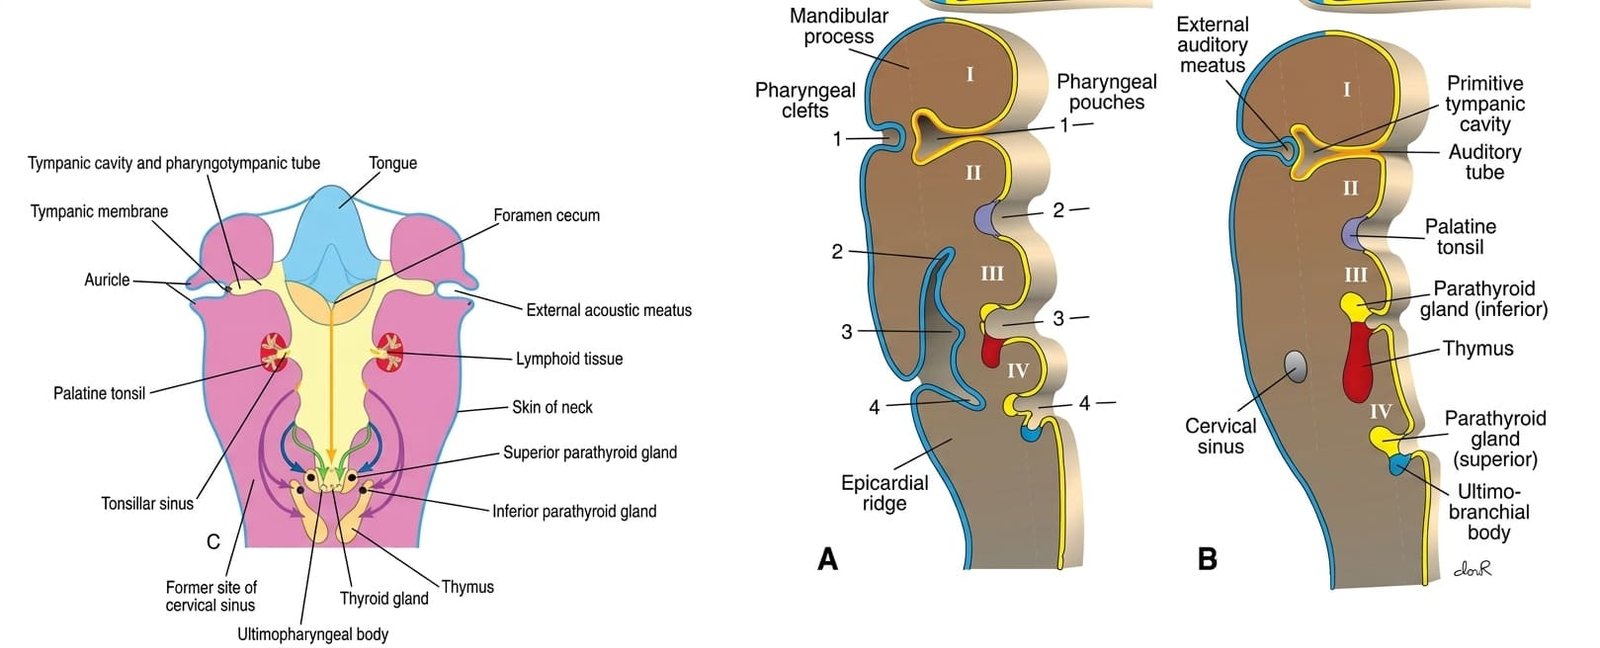
Invaginates laterally toward the first ectodermal cleft, forming the elongated tubotympanic recess:
- Distal Portion: Expands into the primitive tympanic (middle ear) cavity and mastoid antrum, enveloping the middle ear ossicles.
- Proximal Portion: Remains narrow, differentiating into the pharyngotympanic (auditory or Eustachian) tube, maintaining an open connection between the nasopharynx and middle ear.
2. Second Pharyngeal Pouch
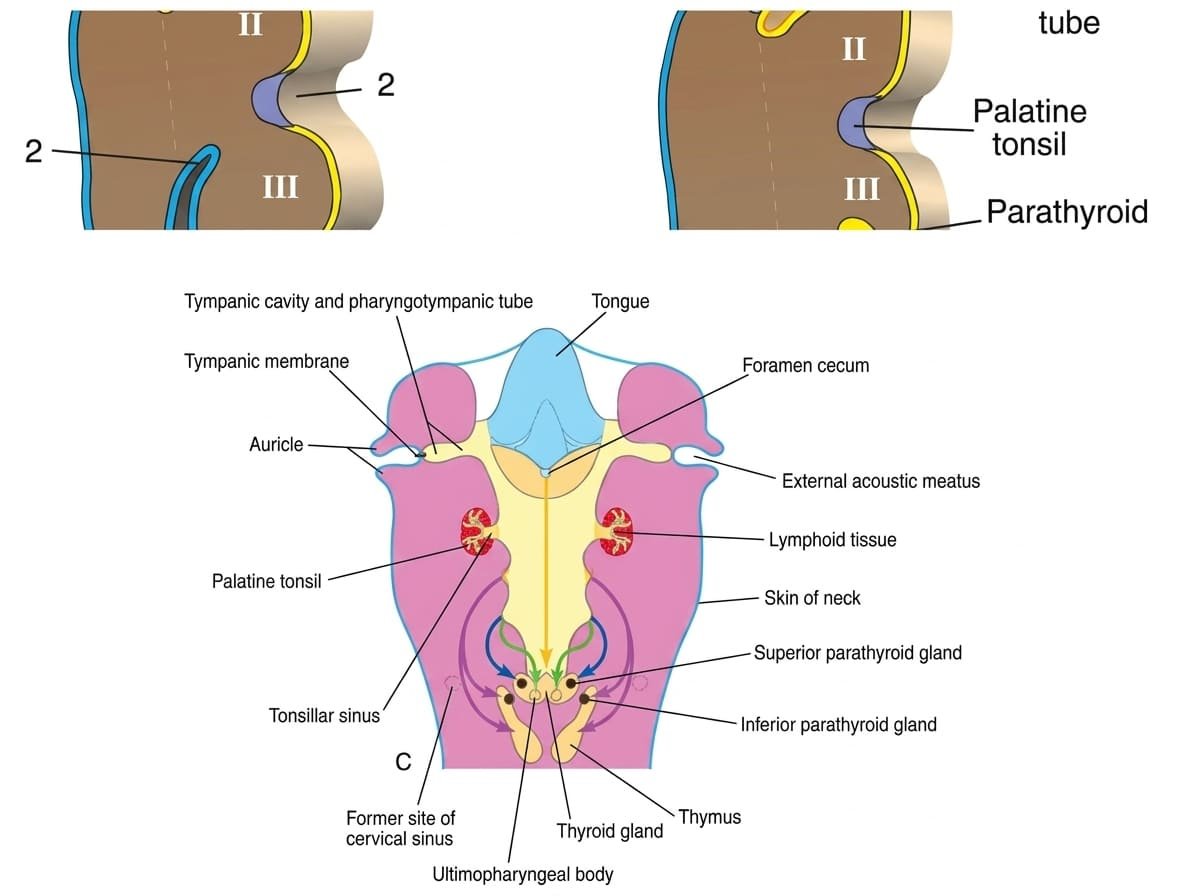
The endodermal lining proliferates rapidly to form solid epithelial buds that penetrate the surrounding mesenchyme. During the second month, these buds are invaded by second arch mesoderm, forming the primordium of the palatine tonsil:
- During the third to fifth months, lymphatic tissue infiltrates the primordium to establish definitive tonsillar lymph nodules.
- The remaining lumen of the pouch persists into adult anatomy as the tonsillar fossa (tonsillar sinus).
3. Third Pharyngeal Pouch
Characterized by a bifurcation into a dorsal wing and a ventral wing at its distal extremity:
- Dorsal Wing: Epithelial cells differentiate during the fifth week into the inferior parathyroid gland (parathyroid III).
- Ventral Wing: Proliferates and fuses across the midline with its contralateral partner to form the bilobed primordium of the thymus.
- Caudal Migration: Both gland primordia lose their connections to the pharyngeal wall. The migrating thymus descends caudomedially through the neck into the superior and anterior mediastinum. Because the inferior parathyroid gland is physically anchored to the descending thymic stalk, it is dragged caudally, settling at the lower pole of the thyroid gland.

4. Fourth & Fifth Pharyngeal Pouches
- Fourth Pouch (Dorsal Wing): Epithelium differentiates into the superior parathyroid gland (parathyroid IV). Because it does not associate with the long-descending thymus, it detaches from the pharyngeal wall and attaches directly to the posterior surface of the migrating thyroid gland at its upper pole.
- Fourth Pouch (Ventral Wing) / Fifth Pouch: Differentiates into the ultimobranchial body (also termed the caudal pharyngeal complex).
→ The ultimobranchial body is incorporated into the posterior lobes of the thyroid gland. Its cells, populated by migrating cranial neural crest cells, differentiate into the parafollicular cells (C cells) of the thyroid gland, which synthesize and secrete calcitonin to lower serum calcium levels.
Clefts, membranes & cervical sinus
In the five-week human embryo, four external ectodermal pharyngeal clefts are present, but only one cleft contributes to definitive adult anatomy.
Fate of the First Pharyngeal Cleft & Membrane
- First Pharyngeal Cleft: The dorsal segment of the first ectodermal cleft deepens, invaginating medially toward the tubotympanic recess to establish the external acoustic (auditory) meatus.
- First Pharyngeal Membrane: Located at the junction of the first cleft and first pouch. Differentiates into the definitive tympanic membrane (eardrum), retaining a unique three-layered embryological architecture:
- External layer: derived from ectoderm of the first cleft.
- Middle fibrous layer (lamina propria): derived from mesenchyme / neural crest.
- Internal mucosal layer: derived from endoderm of the first pouch.

Fate of Clefts 2, 3, & 4 and the Cervical Sinus of His
- Second Arch Overgrowth: The mesenchymal tissue of the second pharyngeal arch undergoes intense mitotic proliferation, rapidly expanding caudally like an operculum to completely overgrow the smaller third and fourth arches.
- Formation of the Cervical Sinus: The free caudal edge of the second arch fuses with the epicardial ridge in the lower neck. This traps the second, third, and fourth pharyngeal clefts within a transient, smooth, ectoderm-lined cavity called the cervical sinus (of His).
- Normal Obliteration: As development proceeds, the epithelial lining of the cervical sinus undergoes apoptosis and degenerates entirely, smoothing the lateral contours of the neck.
- Membranes 2, 3, & 4: Because mesenchyme invades between the inner endoderm and outer ectoderm, the second, third, and fourth pharyngeal membranes disappear, leaving no adult remnants.
Complete derivatives summary
Scroll the table sideways on a smaller screen.
| Arch & Cranial Nerve | Skeletal & Cartilaginous Derivatives | Muscular Derivatives | Aortic Arch Arterial Derivatives |
|---|---|---|---|
| Arch 1 (Mandibular) CN V (Trigeminal: V3 motor; V1, V2, V3 sensory) |
• Maxillary process: Premaxilla, maxilla, zygomatic bone, squamous temporal bone (membranous ossification) • Mandibular process: Mandible (surrounding Meckel’s cartilage) • Meckel’s cartilage dorsal tips: Malleus, incus • Ligaments: Anterior ligament of malleus, sphenomandibular ligament |
• Muscles of mastication (temporalis, masseter, medial & lateral pterygoids) • Mylohyoid • Anterior belly of digastric • Tensor tympani • Tensor veli palatini |
• Maxillary artery • Contribution to external carotid artery |
| Arch 2 (Hyoid) CN VII (Facial) |
• Reichert’s cartilage: Stapes, styloid process of temporal bone • Lesser cornu of hyoid bone • Upper body of hyoid bone • Stylohyoid ligament |
• Muscles of facial expression (orbicularis oris/oculi, buccinator, platysma, frontalis, etc.) • Stapedius • Stylohyoid • Posterior belly of digastric • Auricular muscles |
• Stapedial artery (embryonic remnant; caroticotympanic artery) |
| Arch 3 CN IX (Glossopharyngeal) |
• Greater cornu of hyoid bone • Lower body of hyoid bone |
• Stylopharyngeus muscle |
• Common carotid artery • Proximal internal carotid artery |
| Arch 4 CN X (Vagus: Superior laryngeal nerve) |
• Laryngeal cartilages (Thyroid, cricoid, arytenoid, corniculate, cuneiform – shared with Arch 6) |
• Cricothyroid muscle • Levator veli palatini • Pharyngeal constrictors (superior, middle, inferior) |
• Left: Arch of aorta (segment between left common carotid and left subclavian) • Right: Proximal right subclavian artery |
| Arch 6 CN X (Vagus: Recurrent laryngeal nerve) |
• Laryngeal cartilages (fusion with Arch 4) |
• All intrinsic muscles of the larynx (except cricothyroid) • Striated muscle of upper esophagus |
• Left: Left pulmonary artery (proximal) and ductus arteriosus (ligamentum arteriosum) • Right: Right pulmonary artery (proximal) |
Scroll the table sideways on a smaller screen.
| Number | Pharyngeal Pouch (Endoderm) | Pharyngeal Cleft (Ectoderm) | Pharyngeal Membrane (Bilaminar) |
|---|---|---|---|
| 1 | Tubotympanic recess (tympanic cavity, mastoid antrum, auditory tube) | External acoustic meatus | Tympanic membrane (eardrum) |
| 2 | Palatine tonsillar primordium and tonsillar fossa | Overgrown by Arch 2; contributes to cervical sinus (obliterated) | Obliterated by invading mesenchyme |
| 3 | Dorsal: Inferior parathyroid gland Ventral: Thymus |
Overgrown by Arch 2; contributes to cervical sinus (obliterated) | Obliterated by invading mesenchyme |
| 4 | Dorsal: Superior parathyroid gland Ventral: Ultimobranchial body (Parafollicular C cells) |
Overgrown by Arch 2; contributes to cervical sinus (obliterated) | Obliterated by invading mesenchyme |
Cysts, sinuses & fistulas
Congenital anomalies of the branchial apparatus arise when embryonic clefts or the cervical sinus fail to obliterate normally during the second month.
1. Lateral Cervical (Branchial) Cyst
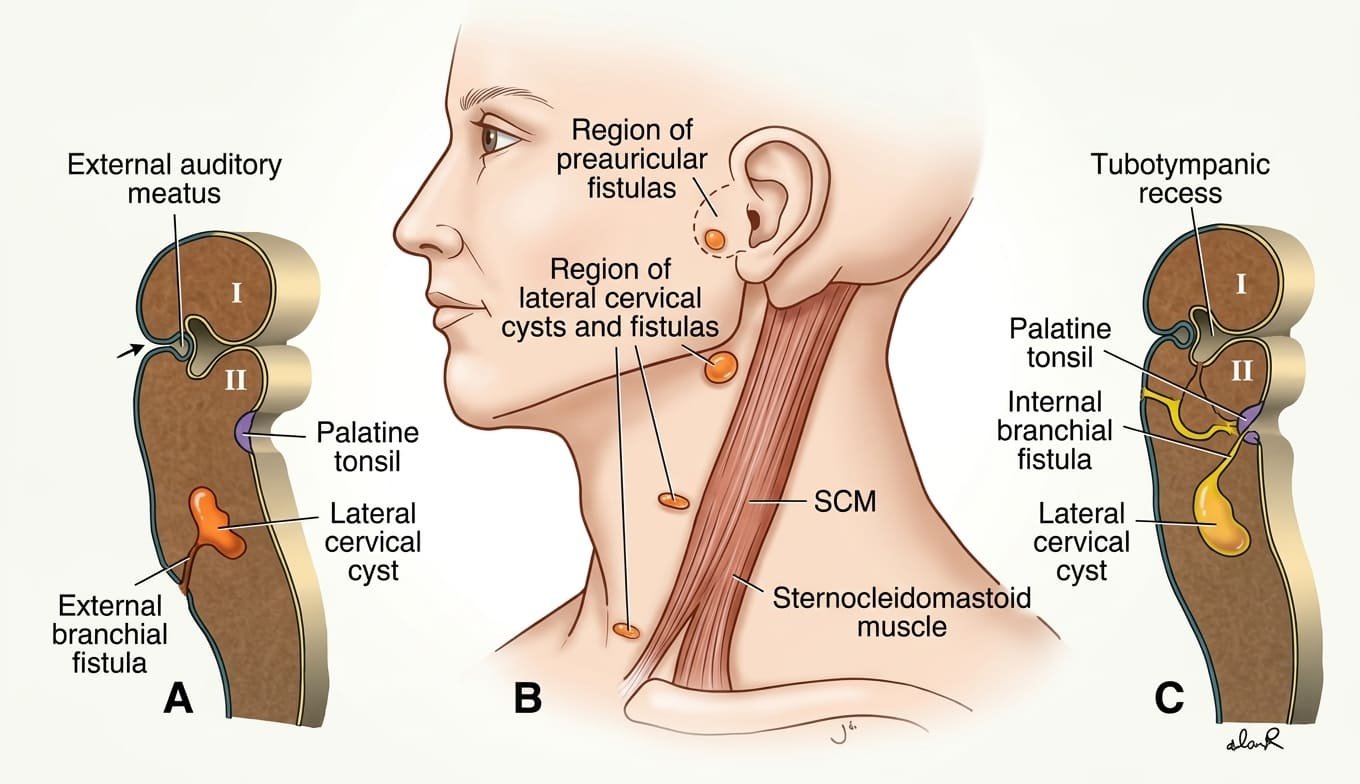
- Etiology: Occurs when a segment of the ectoderm-lined cervical sinus of His fails to obliterate, persisting as an isolated fluid-filled sac. Most commonly represents remnants of the second pharyngeal cleft (95% of cases).
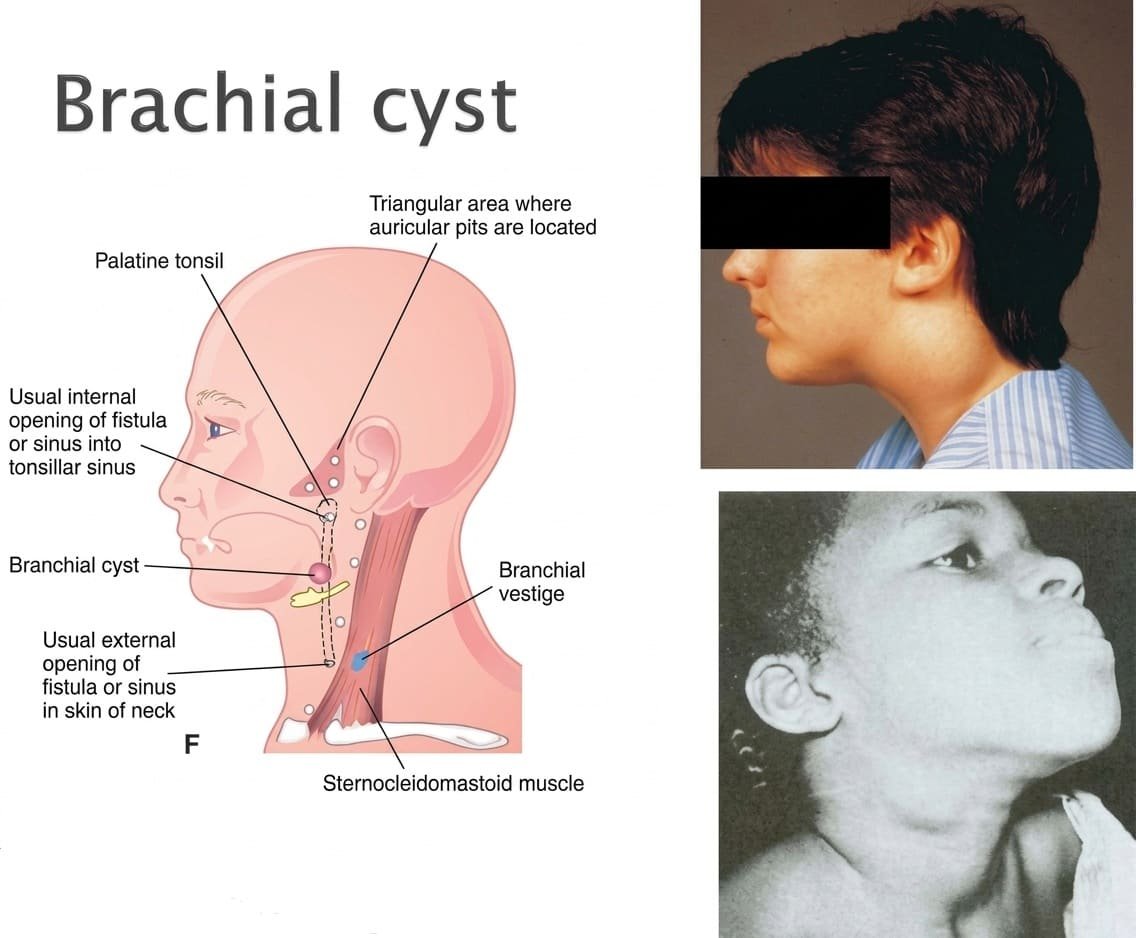
- Clinical Presentation: Typically manifests in older children or young adults as a painless, smooth, fluctuant, non-transilluminating swelling on the lateral aspect of the neck, immediately anterior to the anterior border of the sternocleidomastoid muscle, usually near the angle of the mandible. Frequently enlarges or becomes tender following upper respiratory tract infections.
- Diagnostic Distinction: Must be distinguished from a thyroglossal duct cyst, which is characteristically located in the midline of the neck and moves upward upon tongue protrusion and swallowing.
2. Branchial Sinuses & Fistulas
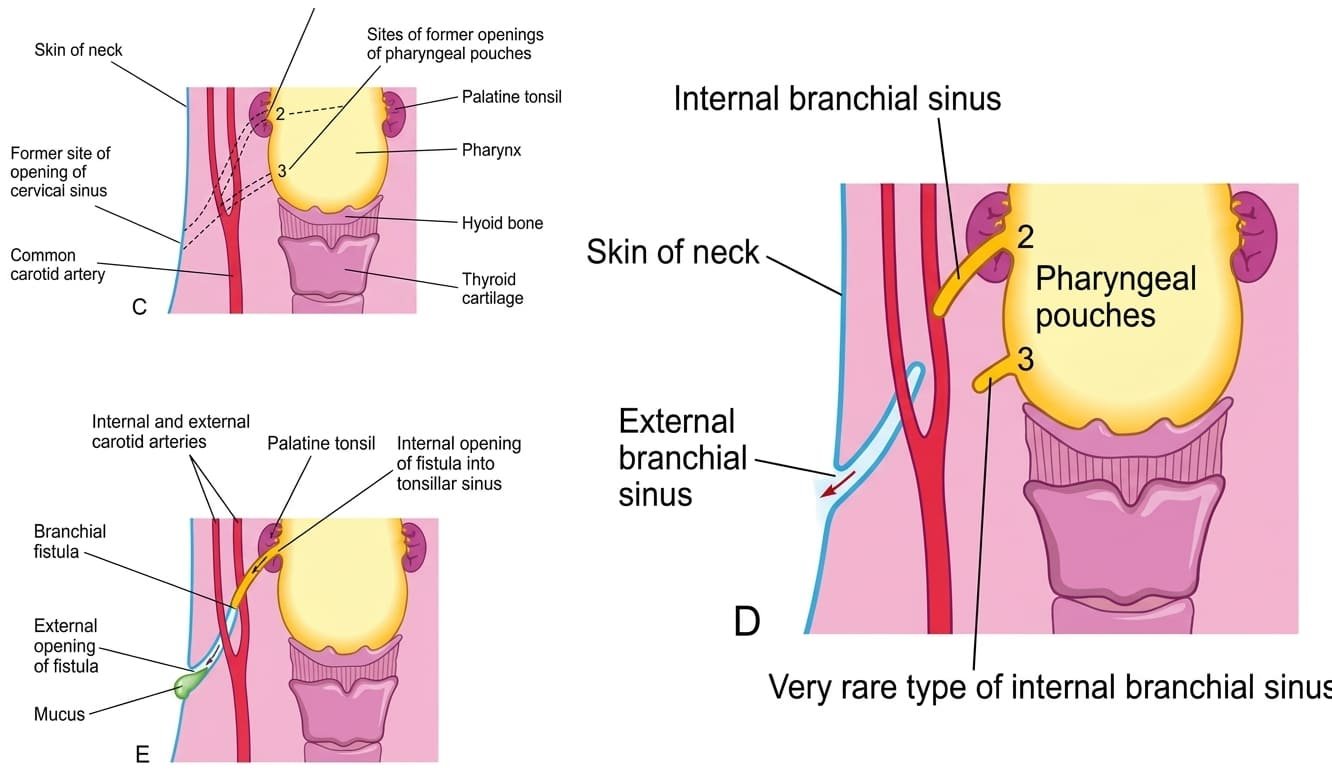
- External Branchial Sinus: A blind pouch opening externally onto the skin along the lower anterior border of the sternocleidomastoid muscle. Results from failure of the second pharyngeal cleft to obliterate completely. Manifests as a small cutaneous opening that periodically discharges clear or purulent mucus.
- Internal Branchial Sinus: A blind pouch opening internally into the pharynx, almost always into the palatine tonsillar fossa. Caused by persistence of the proximal remnant of the second pharyngeal pouch.
- Complete Branchial Fistula: A continuous, patent abnormal tract connecting the lumen of the pharynx directly to the external skin surface of the neck. Results from simultaneous breakdown of the second pharyngeal membrane and persistence of the second cleft and pouch.
→ Anatomical Course: The fistula tract ascends from its cutaneous opening along the lower anterior sternocleidomastoid border, passes deep to the platysma, ascends through the carotid sheath between the internal and external carotid arteries (reflecting the third and second arch boundaries), and opens internally into the palatine tonsillar fossa.
First arch syndromes
First arch syndromes comprise a spectrum of severe congenital craniofacial malformations resulting from insufficient migration or premature apoptosis of cranial neural crest cells into the first pharyngeal arch during the fourth week.
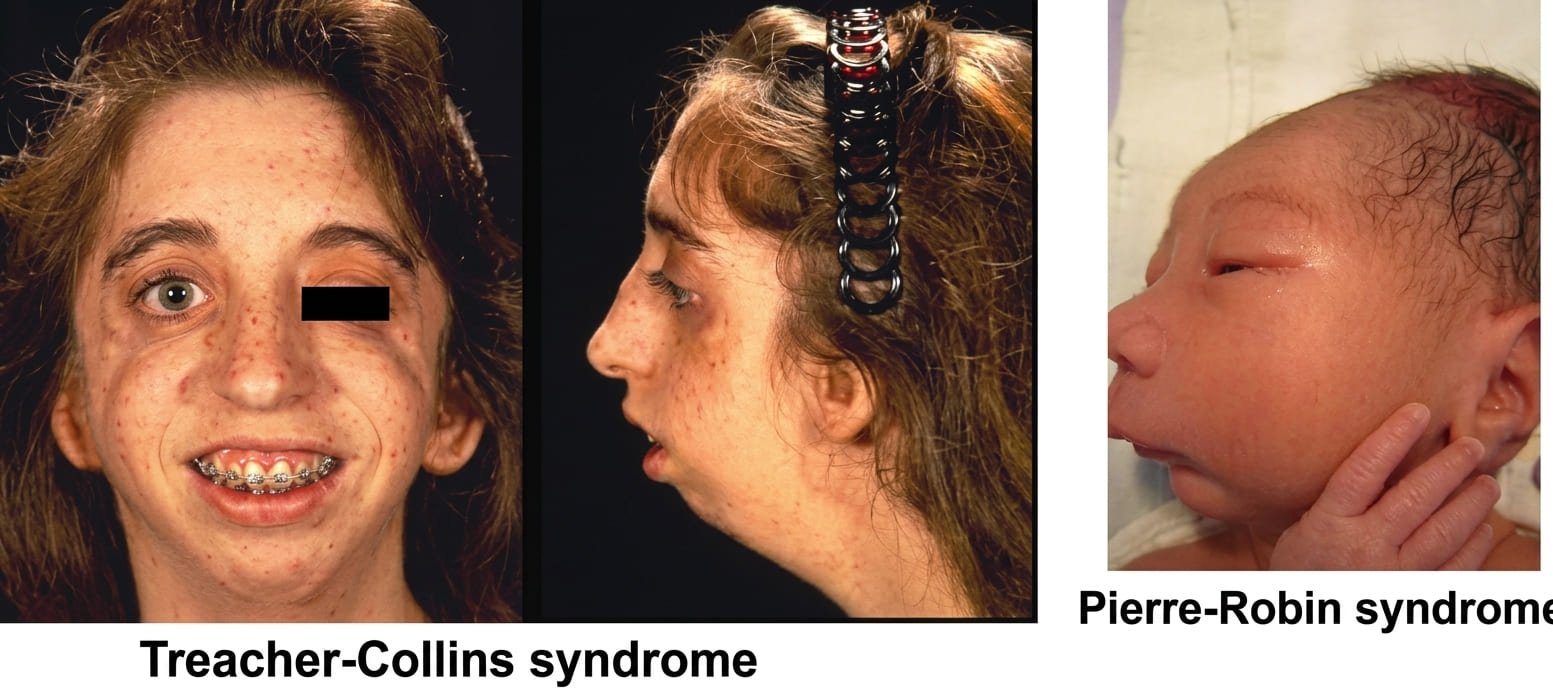
1. Treacher Collins Syndrome (Mandibulofacial Dysostosis)
- Genetics: Autosomal dominant disorder, most frequently caused by mutations in the TCOF1 gene (encoding the nucleolar phosphoprotein treacle, which impairs ribosome biogenesis and triggers extensive neural crest apoptosis) or POLR1C/POLR1D.
- Craniofacial Manifestations:
- Malar (Zygomatic) Hypoplasia: Severe underdevelopment of the cheekbones, resulting in a narrow, depressed midface.
- Mandibular Hypoplasia: Micrognathia (small, receded lower jaw).
- Ocular Defects: Down-slanting palpebral fissures (antimongoloid slant), coloboma of the lateral third of the lower eyelid, and deficiency of lower lashes.
- Auricular & Auditory Deformities: Microtia (rudimentary external ears), absence of the external acoustic meatus, and ossicular malformations (malleus/incus fusion) causing profound bilateral conductive hearing loss.
2. Pierre Robin Sequence
- Pathophysiological Cascade (Sequence): A primary mechanical developmental arrest initiates a domino-like cascade of secondary defects:
- Primary Defect: Severe hypoplasia of the mandibular process (micrognathia).
- Secondary Defect: Because the lower jaw is undersized, the developing tongue is pushed superiorly and posteriorly into the oropharynx (glossoptosis).
- Tertiary Defect: The retracted tongue physically blocks the normal horizontal elevation and fusion of the bilateral palatal shelves across the midline, resulting in a characteristic U-shaped wide cleft secondary palate.
- Neonatal Emergency: Infants present immediately at birth with severe upper airway obstruction and respiratory distress due to the tongue obstructing the posterior pharynx, alongside feeding difficulties and aspiration risk. Requires immediate prone positioning, nasopharyngeal airway stenting, or surgical mandibular distraction osteogenesis.
DiGeorge syndrome & ectopia
DiGeorge Syndrome (22q11.2 Deletion Syndrome)
DiGeorge syndrome (velocardiofacial syndrome) is a severe congenital anomaly caused by failure of differentiation of the third and fourth pharyngeal pouches, secondary to defective cranial neural crest migration into the pharyngeal arches and aortic sac.
- Genetic Basis: Microdeletion on the long arm of chromosome 22 (22q11.2 deletion), typically disrupting the TBX1 transcription factor gene, which regulates pharyngeal endoderm-neural crest signaling.
- Primary Pathological Triad:
- Congenital Thymic Aplasia / Hypoplasia: Failure of ventral pouch 3 development. Leads to complete absence of cell-mediated immunity (profound T-lymphocyte deficiency), predisposing infants to severe, recurrent opportunistic viral, fungal, and bacterial infections.
- Congenital Parathyroid Aplasia / Hypoplasia: Failure of dorsal pouches 3 and 4 development. Absence of parathyroid hormone (PTH) causes neonatal hypocalcemia, manifesting within hours to days of birth as intractable tetany, neuromuscular irritability, carpopedal spasm, and seizures.
- Conotruncal Cardiac Anomalies: Defective neural crest septation of the cardiac outflow tract yields persistent truncus arteriosus, Tetralogy of Fallot, or interrupted aortic arch.
- Craniofacial Dysmorphism: Low-set, notched ears, micrognathia, hypertelorism, short philtrum, and bifid uvula or cleft palate.
Ectopic Parathyroid & Thymic Tissue
Because the thymus and parathyroid glands undergo extensive migration from the pharyngeal wall down into the lower neck and anterior mediastinum, abnormal cell arrests or persistent detached fragments along the migratory route produce ectopic glandular tissue:
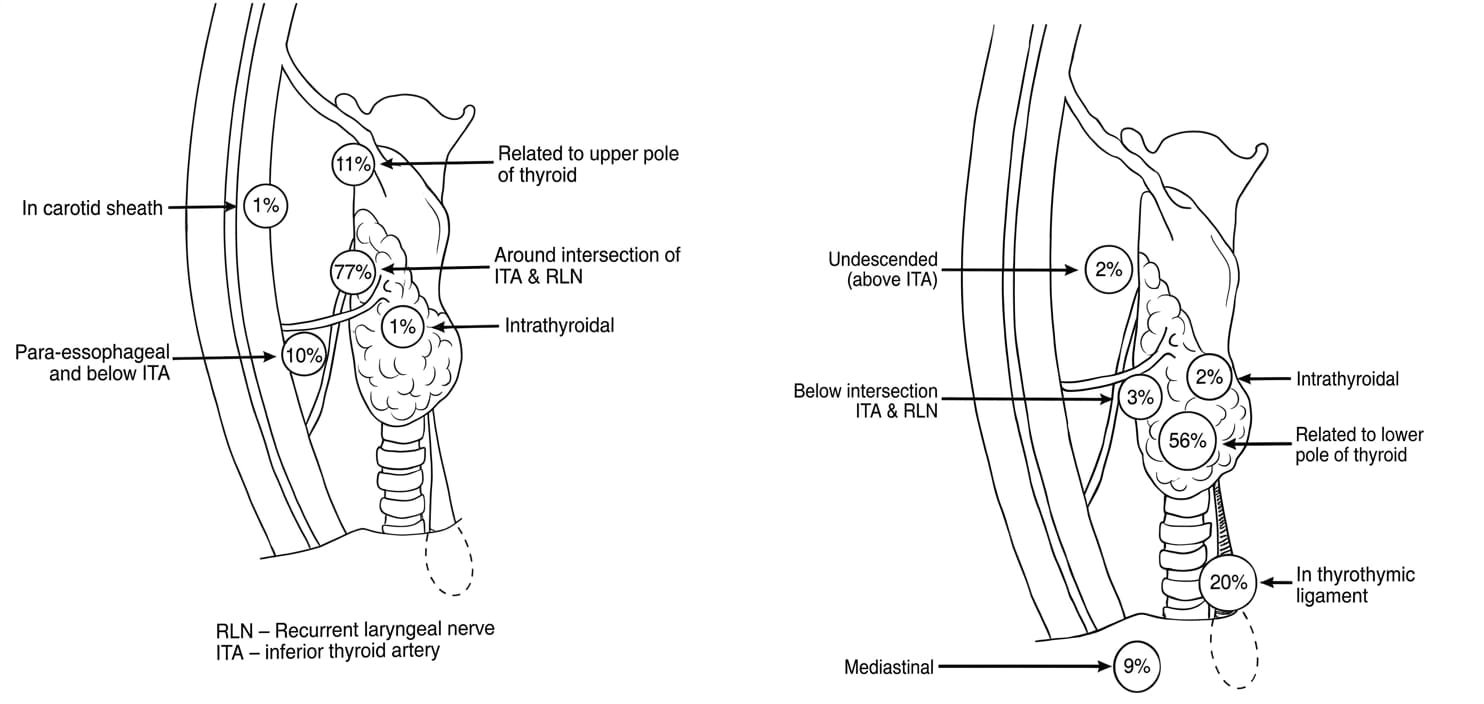
- Ectopic Parathyroid Glands: The inferior parathyroid glands exhibit greater migratory variability than the superior glands. They may arrest anywhere along the pathway from the angle of the mandible down to the superior mediastinum (inside the carotid sheath, embedded in the thyrothymic tract, or within the mediastinal thymus). Occasionally, they become trapped entirely within the parenchyma of the thyroid gland (intrathyroidal parathyroid).
Surgical Relevance: In patients undergoing parathyroidectomy for primary hyperparathyroidism, failure to locate an adenoma at its anatomical position mandates systematic surgical exploration of ectopic sites, particularly the thymus and carotid sheath. - Ectopic Thymic Tissue: Remnants of the thymic stalk may persist as accessory thymic nodules or cysts along the migratory path in the lateral neck or behind the sternocleidomastoid muscle.
Quick recap
References
The following authoritative medical embryology and developmental anatomy reference textbooks support this curriculum study note:
- Langman’s Medical Embryology: Sadler, T.W. (2023) Langman’s Medical Embryology. 15th edn. Philadelphia: Wolters Kluwer. [Chapter 17: Head and Neck – Pharyngeal Arches, Pouches, and Clefts; Congenital Craniofacial Malformations].
- The Developing Human: Moore, K.L., Persaud, T.V.N. and Torchia, M.G. (2020) The Developing Human: Clinically Oriented Embryology. 11th edn. Philadelphia: Elsevier. [Chapter 9: The Pharyngeal Apparatus, Face, and Neck].
- Larsen’s Human Embryology: Schoenwolf, G.C., Bleyl, S.B., Brauer, P.R. and Francis-West, P.H. (2021) Larsen’s Human Embryology. 6th edn. Philadelphia: Elsevier. [Chapter 12: Development of the Head, the Neck, the Eyes, and the Ears].
- Gray’s Anatomy: Standring, S. (2021) Gray’s Anatomy: The Anatomical Basis of Clinical Practice. 42nd edn. London: Elsevier. [Section 4: Head and Neck – Embryology of the Pharynx and Viscerocranium].