
Basal nuclei, limbic system & reticular formation: motor loops, emotional circuits & brainstem integration
On this page
Definitions & nomenclature
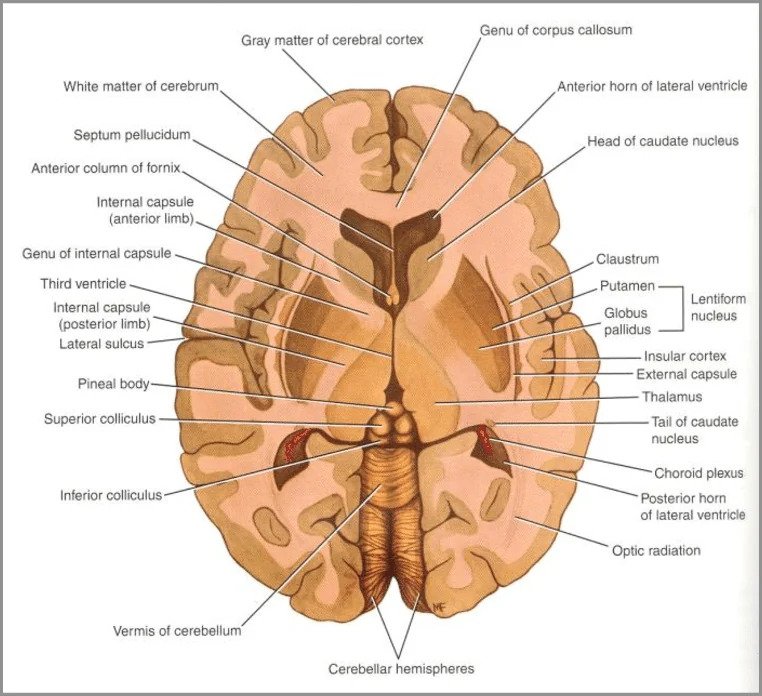
The basal nuclei (historically and clinically termed the basal ganglia) are a collection of subcortical gray matter masses situated within the deep white matter of the cerebral hemispheres, positioned inferior to the lateral ventricles and lateral to the diencephalon (thalamus). While the histological term “ganglion” strictly denotes a peripheral collection of neuronal cell bodies, clinical neurology preserves “basal ganglia” to describe these central motor, cognitive, and affective processing hubs.
Anatomical & Functional Groupings
Subcortical Terminology & Groupings
- Corpus Striatum: Comprises the caudate nucleus, putamen, and globus pallidus. Named for the striped histological appearance produced by bridging myelinated axonal strands (subcapsular gray matter bridges) traversing between the caudate and putamen across the internal capsule.
- Striatum / Dorsal Striatum / Neostriatum: Comprises strictly the caudate nucleus and the putamen. Phylogenetically newest component, serving as the primary receptive portal receiving glutamatergic inputs from the cerebral cortex.
- Pallidum / Paleostriatum: The globus pallidus. Phylogenetically older, containing large GABAergic projection neurons subdivided into an internal segment (GPi) and an external segment (GPe).
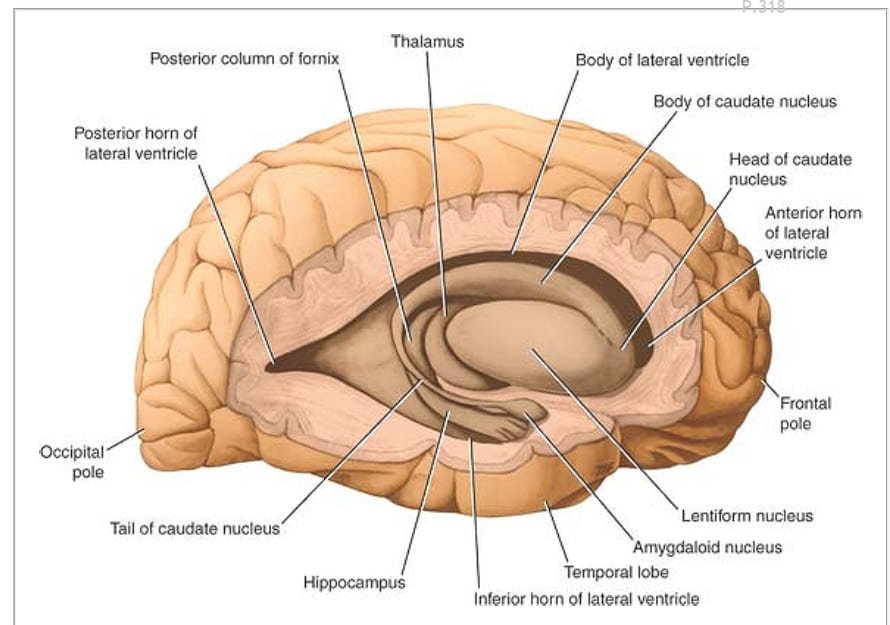
- Lentiform (Lenticular) Nucleus: The lens-shaped anatomical unit formed by the putamen (lateral, darkly pigmented) and the globus pallidus (medial, pale due to heavy myelination). Grouped purely by topographical proximity, though functionally distinct.
- Ventral (Limbic) Striatum: Comprises the ventral extensions of the caudate and putamen, the nucleus accumbens septi, and the striatal portions of the olfactory tubercle. Integrates emotional valence, reward, and motivation with motor execution.
- Extrapyramidal System: Functional motor network integrating the basal ganglia with subcortical and brainstem nuclei: the subthalamic nucleus (STN) of Luys, the midbrain substantia nigra (pars compacta and pars reticulata), the red nucleus, and the reticular formation.
- Additional Deep Nuclei: The claustrum (a thin sheet of gray matter situated between the external capsule and extreme capsule) and the amygdaloid complex (topographically positioned at the tail of the caudate, but functionally belonging to the limbic system).
Basal nuclei architecture
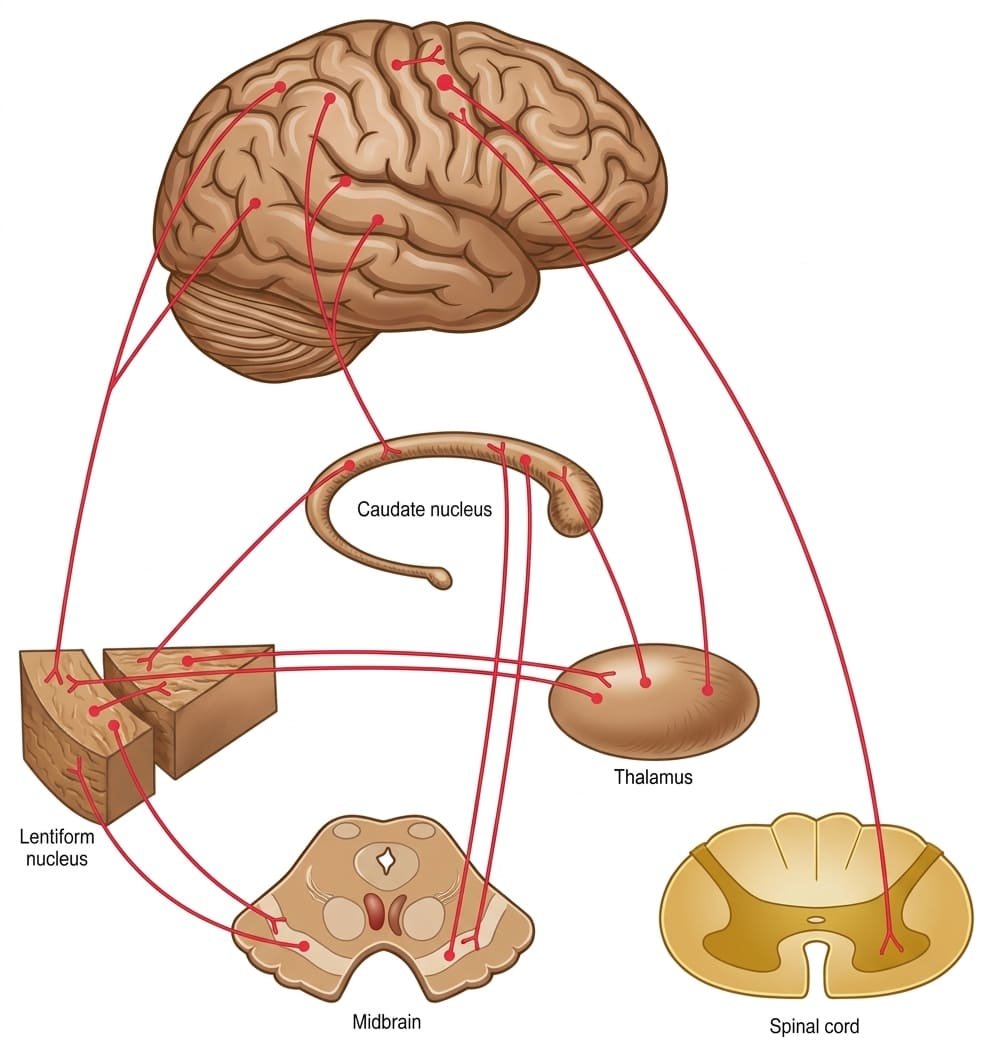
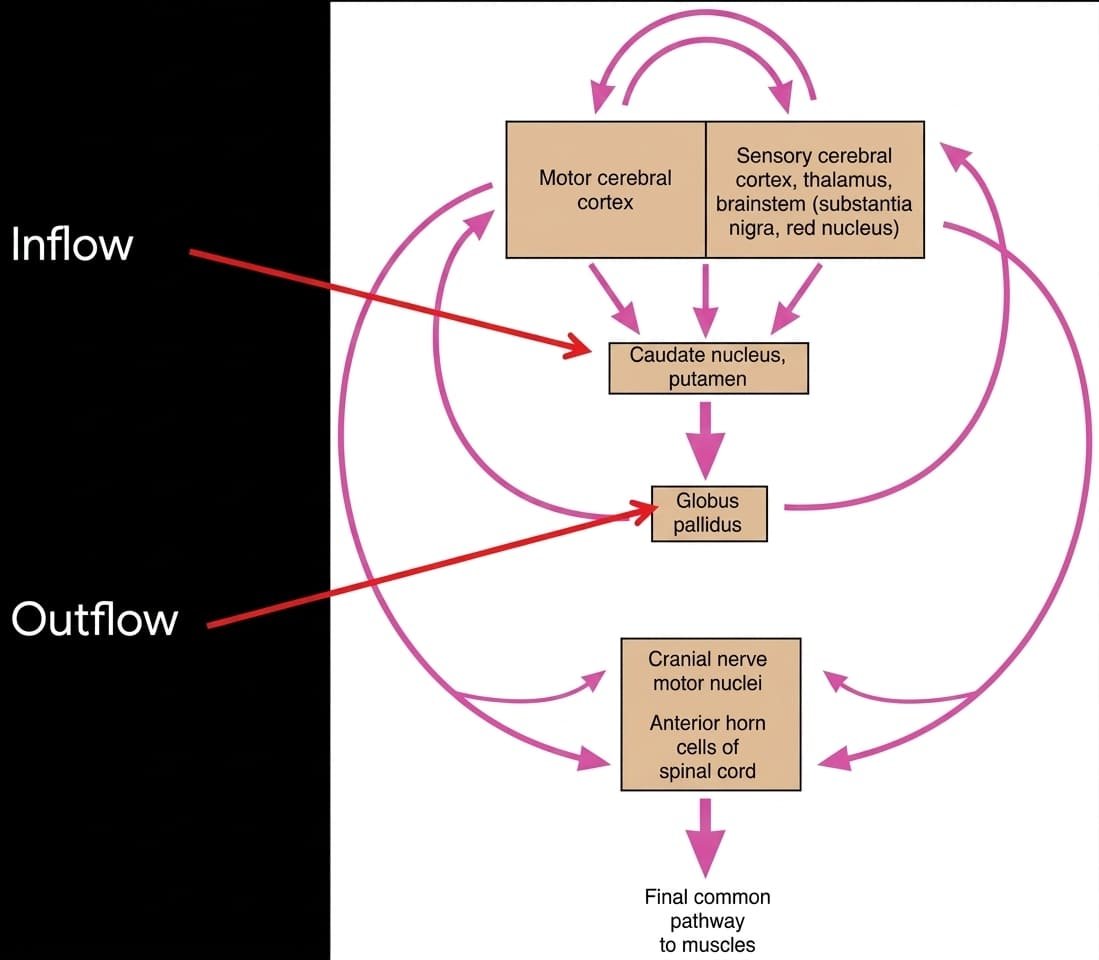
The basal nuclei function as an unmyelinated re-entrant loop: they receive dense excitatory projections from virtually all neocortical areas, process this neural code through internal inhibitory and disinhibitory networks, and funnel refined signals through the thalamus back to cortical motor fields to shape movement initiation and coordination.
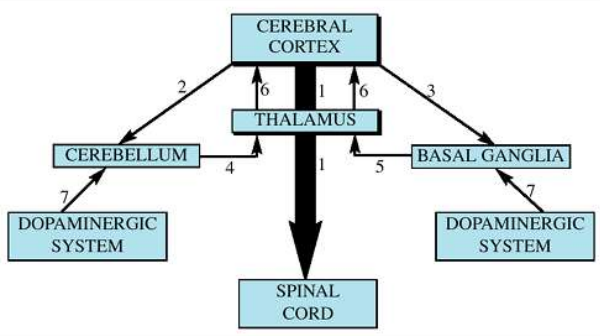
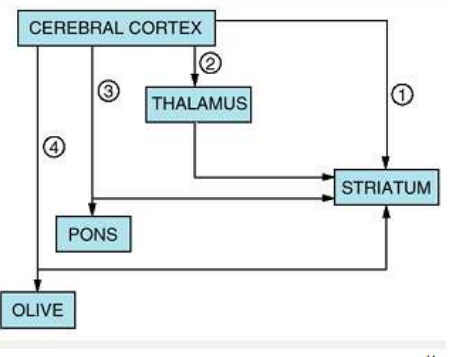
1. The Neostriatum (Caudate & Putamen)
The neostriatum is the primary receiving station of the basal ganglia, composed of >95% GABAergic medium spiny projection neurons (MSNs) studded with dendritic spines, intermingled with cholinergic and GABAergic interneurons.
- Caudate Nucleus: A C-shaped gray mass closely associated with the lateral ventricle. Possesses an expanded head (bulging into the anterior horn), a body (along the ventricular floor), and an attenuated tail (arching into the temporal lobe roof, terminating near the amygdala). Primarily involved in cognitive planning, procedural learning, and saccadic eye movements.
- Putamen: The convex, lateral component of the lentiform nucleus, separated from the globus pallidus by the lateral medullary lamina. Dedicated primarily to somatic motor control across trunk and limb musculature.
- Neostriatal Afferent Connections:
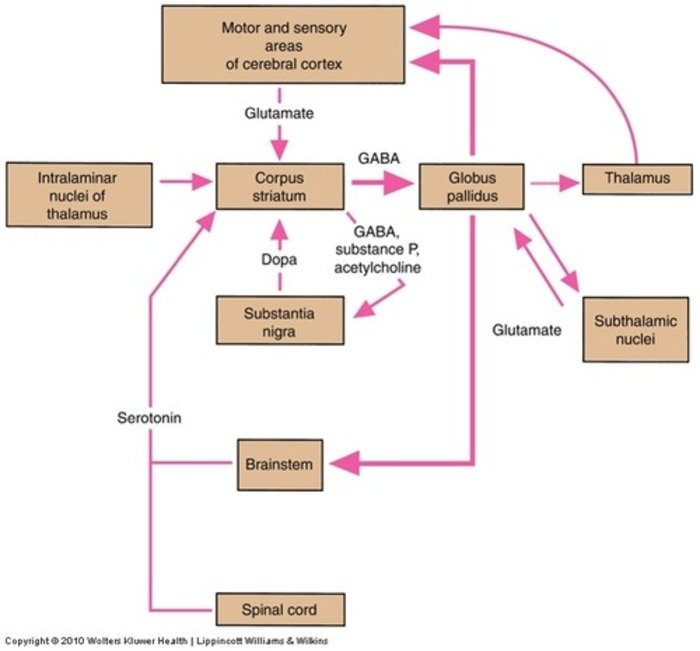
- Corticostriate Fibers: Excitatory glutamatergic projections arising from all areas of the cerebral cortex (motor cortex projects predominantly to the putamen; association and prefrontal cortex project to the caudate).
- Thalamostriate Fibers: Excitatory glutamatergic inputs from the intralaminar thalamic nuclei (centromedian and parafascicular nuclei).
- Nigrostriate Fibers: Modulatory dopaminergic projections arising from the substantia nigra pars compacta (SNc).
- Brainstem Striatal Fibers: Modulatory serotonergic fibers originating from the midbrain and pontine raphe nuclei.
- Neostriatal Efferent Connections:
- Striatopallidal Fibers: Inhibitory GABAergic projections targeting both the external (GPe) and internal (GPi) segments of the globus pallidus.
- Striatonigral Fibers: Inhibitory GABAergic projections (co-transmitting substance P or acetylcholine) targeting the substantia nigra pars reticulata (SNr).
2. The Pallidum (Globus Pallidus) & Substantia Nigra
The globus pallidus and the midbrain substantia nigra pars reticulata (SNr) constitute the major output stations of the basal ganglia:
- Internal Segment (GPi) & SNr: Maintain high spontaneous, tonic inhibitory (GABAergic) firing directed at the ventral anterior (VA) and ventral lateral (VL) nuclei of the thalamus. GPi regulates spinal and limb motor execution; SNr controls head, neck, and oculomotor circuits.
- External Segment (GPe): Acts as an internal relay nucleus within the indirect pathway, projecting inhibitory GABAergic fibers to the subthalamic nucleus.
- Subthalamic Nucleus (STN): An ovoid lens-shaped diencephalic nucleus situated ventral to the thalamus and dorsal to the substantia nigra. The only intrinsically excitatory nucleus within the basal ganglia; utilizes glutamate to drive excitation of the inhibitory GPi/SNr output complex.
The direct, indirect & hyperdirect pathways
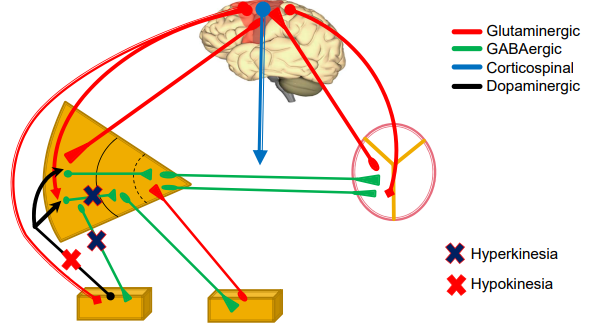
Somatic motor output is governed by the push-pull interaction of two opposing internal basal ganglia loops: the direct pathway (which facilitates movement) and the indirect pathway (which inhibits movement). Both loops receive modulatory input from the hyperdirect pathway and the substantia nigra.
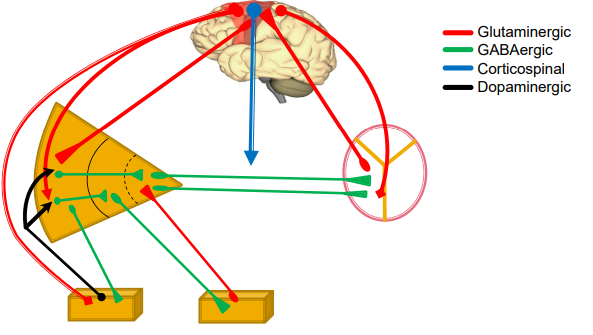
1. The Direct Pathway (“Go” Pathway — Motor Initiation)
The direct pathway provides positive feedback to the cortex, facilitating intended voluntary motor programs:
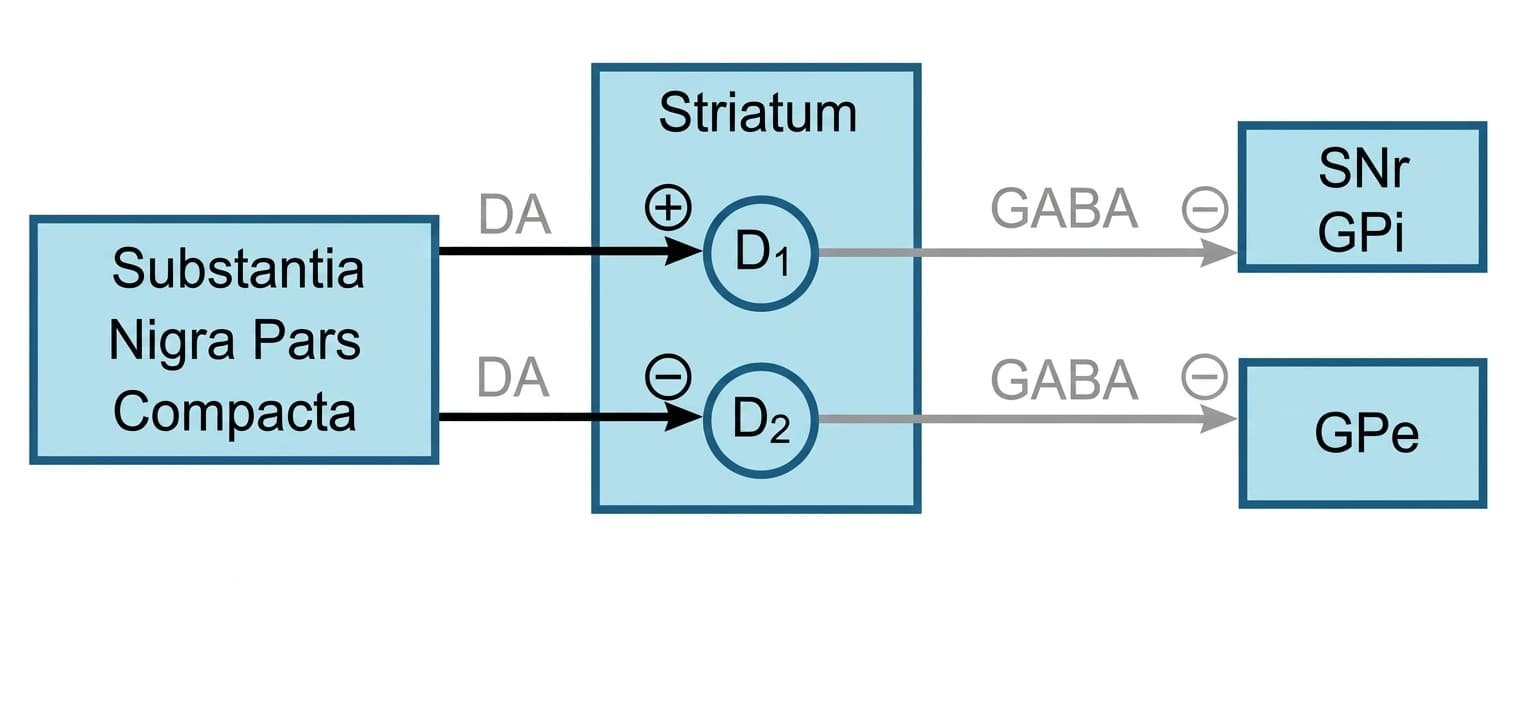
- Cortical Excitation: Pyramidal motor neurons release glutamate onto medium spiny neurons in the striatum expressing D1 dopamine receptors.
- Striatal Inhibition of GPi/SNr: Activated D1-bearing MSNs fire rapidly, releasing GABA (co-transmitting substance P) directly onto the internal segment of the globus pallidus (GPi) and substantia nigra pars reticulata (SNr).
- Disinhibition of Thalamus: Under basal conditions, GPi/SNr neurons fire tonically at 60 to 80 Hz to suppress the thalamus. When inhibited by the striatum, their inhibitory output ceases. This disinhibition releases thalamic neurons (VA/VL) from tonic suppression.
- Thalamocortical Drive: Disinhibited thalamic neurons fire excitatory glutamatergic bursts to the primary motor, premotor, and supplementary motor cortices, initiating movement.
2. The Indirect Pathway (“No-Go” Pathway — Motor Braking)
The indirect pathway provides negative feedback, terminating movements and suppressing competing or involuntary motor programs:
- Cortical Excitation: Pyramidal neurons release glutamate onto striatal MSNs expressing D2 dopamine receptors (co-expressing enkephalin).
- Striatal Inhibition of GPe: Activated MSNs release GABA onto the external segment of the globus pallidus (GPe), transiently shutting down GPe firing.
- Disinhibition of the Subthalamic Nucleus: The GPe tonically inhibits the subthalamic nucleus (STN). When GPe is inhibited, the STN is disinhibited and fires intensely.
- Subthalamic Excitation of GPi/SNr: The STN fires excitatory glutamatergic projections to the GPi and SNr, driving them to fire.
- Enhanced Thalamic Inhibition: Excited GPi/SNr neurons release high levels of GABA onto VA/VL thalamic nuclei. This inhibits thalamocortical drive, shutting down motor execution.
3. The Hyperdirect Pathway
A monosynaptic excitatory pathway running directly from the motor cortex, supplementary motor area, and frontal eye fields to the subthalamic nucleus, bypassing the striatum entirely. Because it has only one synapse, it conducts faster than both the direct and indirect loops. It fires an immediate excitatory signal to the GPi/SNr, initiating a broad “stop” command across the thalamus to suppress competing motor patterns before the direct pathway selectively executes the intended movement.
Pallidofugal tracts & the fields of Forel
Efferent fibers leaving the globus pallidus (GPi) to reach the diencephalon and midbrain are collectively termed pallidofugal fibers. They travel along four distinct trajectories, traversing the subthalamic tegmental fields known as the Fields of Forel.

The Four Pallidofugal Fiber Bundles
- 1. Ansa Lenticularis: Axons arising from the outer portion of the GPi that sweep ventromedially around the anterior margin of the posterior limb of the internal capsule. They loop through the substantia innominata to enter the prerubral field.
- 2. Fasciculus Lenticularis (Forel’s Field H2): Axons from the dorsal GPi that pierce directly through the internal capsule above the subthalamic nucleus, coursing medially as field H2.
- 3. Prerubral Field (Forel’s Field H): The convergence zone situated anterior and rostral to the red nucleus. Here, the ansa lenticularis, lenticular fasciculus, and ascending dentatothalamic fibers (from the contralateral cerebellar dentate nucleus via the superior cerebellar peduncle) intermix.
- 4. Thalamic Fasciculus (Forel’s Field H1): The consolidated fiber bundle that turns dorsolaterally out of Field H, running between the subthalamus and the ventral thalamic surface to terminate in the ventral anterior (VA), ventral lateral (VL), and centromedian (CM) nuclei of the thalamus.
- Pallidosubthalamic & Pallidotegmental Projections: Reciprocal GABAergic fibers passing from the GPe to the subthalamic nucleus, alongside pallidotegmental fibers descending to the pedunculopontine tegmental nucleus (PPN) of the midbrain to regulate locomotor pattern generators.
Physiology & gating functions
While classically considered motor structures, the basal ganglia participate in five parallel, segregated cortico-striato-pallido-thalamo-cortical loops that govern motor, oculomotor, cognitive, and affective processing.
Five Segregated Functional Loops
1. Skeletomotor Loop (Motor Execution)
Originates in the primary motor, premotor, and somatosensory cortices; projects to the putamen; passes via direct/indirect pathways to GPi/SNr; relays via thalamic VA/VL back to the supplementary motor area (SMA). Controls movement amplitude, velocity, initiation, and multijoint coordination.
2. Oculomotor Loop (Saccadic Eye Movements)
Originates in the frontal eye fields (FEF, area 8) and posterior parietal cortex; projects to the body of the caudate; passes via direct/indirect circuits to the SNr. SNr sends GABAergic fibers to disinhibit the superior colliculus, initiating rapid, voluntary saccadic eye movements toward visual targets.
3. Dorsolateral Prefrontal Loop (Cognitive Function)
Originates in the dorsolateral prefrontal cortex (Brodmann areas 9 and 46); projects to the head of the caudate nucleus; relays via mediodorsal (MD) and VA thalamic nuclei back to prefrontal cortex. Governs executive functioning: working memory, rule-based learning, abstract problem solving, and motor sequencing.
4. Lateral Orbitofrontal Loop (Gating & Social Behavior)
Originates in lateral orbitofrontal cortex; projects to the ventromedial caudate; relays via MD/VA thalamus. Governs behavioral gating: suppressing inappropriate social responses, impulse control, shifting behavioral sets, and evaluating risks.
5. Anterior Cingulate / Limbic Loop (Emotion & Motivation)
Originates in anterior cingulate cortex and medial temporal lobe; projects to the ventral striatum (nucleus accumbens); relays via ventral pallidum and MD thalamus. Mediates motivational drive, reward reinforcement, mood regulation, and translation of emotional state into motor action.
Sensory Gating, Spatial Neglect & Cerebellar Complementarity
- Gating Function: The basal ganglia act as an active neurochemical filter, suppressing irrelevant sensory stimuli and subthreshold motor patterns while focusing attention on relevant targets. Disruptions contribute to the involuntary intrusions seen in obsessive-compulsive disorder (OCD) and Tourette syndrome.
- Spatial Neglect: Lesions in the right caudate or putamen can disrupt frontoparietal spatial networks, producing left-sided spatial hemineglect (inattention to contralateral sensory space).
- Complementarity of Basal Ganglia and Cerebellum:
- Basal Ganglia: Operate through inhibitory (GABAergic) gating to determine whether and when a movement occurs (selection, initiation, and motivation of motor programs).
- Cerebellum: Operates through rapid sensory feedback to determine how the movement is executed (real-time error correction, timing, coordination, and equilibrium).
Arterial blood supply to the basal nuclei
The basal nuclei receive their vascularization from deep penetrating branches of the Circle of Willis, making them vulnerable to hypertensive microvascular disease, lacunar infarcts, and Charcot-Bouchard microaneurysm rupture.
Scroll the table sideways on a smaller screen.
| Subcortical Structure | Primary Arterial Supply | Parent Vessel / Branch Origin |
|---|---|---|
| Head of Caudate Nucleus (Rostromedial part) | Medial striate artery (Recurrent artery of Heubner) | Anterior Cerebral Artery (ACA, A1/A2 junction) |
| Body of Caudate & Major Putamen Mass | Lateral striate branches (Lenticulostriate arteries) | Middle Cerebral Artery (MCA, M1 segment) |
| Tail of Caudate & Caudal Putamen | Anterior choroidal artery | Internal Carotid Artery (ICA) |
| Globus Pallidus (Internal Segment - GPi) | Anterior choroidal artery | Internal Carotid Artery (ICA) |
| Globus Pallidus (External/Lateral Segment - GPe) | Lateral striate branches (Lenticulostriate arteries) | Middle Cerebral Artery (MCA, M1 segment) |
| Subthalamic Nucleus & Substantia Nigra | Posterior communicating & paramedian peduncular branches | Posterior Cerebral Artery (PCA) & Basilar bifurcations |
Clinical movement disorders
Basal ganglia pathologies produce movement disorders classified as hyperkinetic (unwanted, excess involuntary movements resulting from loss of indirect pathway inhibition) or hypokinetic (poverty and slowness of voluntary movement resulting from loss of direct pathway facilitation).

1. Hyperkinetic Disorders (Damage to the Indirect Pathway)
- Chorea: Involuntary, rapid, jerky, irregular, non-stereotyped movements that dance haphazardly from one muscle group to another.
- Huntington Disease: Autosomal dominant neurodegenerative disorder caused by an expanded CAG trinucleotide repeat (≥40 repeats) in the HTT gene on chromosome 4p16.3, encoding huntingtin. Pathology begins with selective, early loss of GABAergic/enkephalinergic medium spiny neurons in the caudate nucleus that project to the GPe (indirect pathway). Loss of GPe inhibition leads to subthalamic suppression and hyperkinetic chorea, progressing later to cognitive dementia, depression, and death.
- Sydenham Chorea: Autoimmune chorea (St. Vitus’ dance) occurring weeks to months after group A streptococcal pharyngitis (acute rheumatic fever). Molecular mimicry causes anti-streptococcal antibodies to cross-react with striatal neuronal antigens.
- Wilson Disease (Hepatolenticular Degeneration): Autosomal recessive disorder of biliary copper excretion caused by mutations in the ATP7B gene on chromosome 13. Toxic copper accumulates in the liver and lentiform nucleus (causing bilateral putaminal necrosis and cavitation). Manifests as choreoathetosis, “wing-beating” tremor, parkinsonism, psychiatric disturbances, and pathognomonic corneal Kayser-Fleischer rings.
- Athetosis: Slow, continuous, writhing, involuntary movements, predominantly affecting distal extremities (fingers, hands, face). Reflects fluctuating muscle tone caused by striatal lesions or perinatal kernicterus.
- Hemiballismus: Wild, violent, large-amplitude flinging movements of the contralateral arm and leg. Results from unilateral vascular infarction (lacunar stroke) or hemorrhage in the contralateral subthalamic nucleus (STN). Without excitatory STN drive, GPi/SNr output drops, leaving the thalamus uncontrolled.
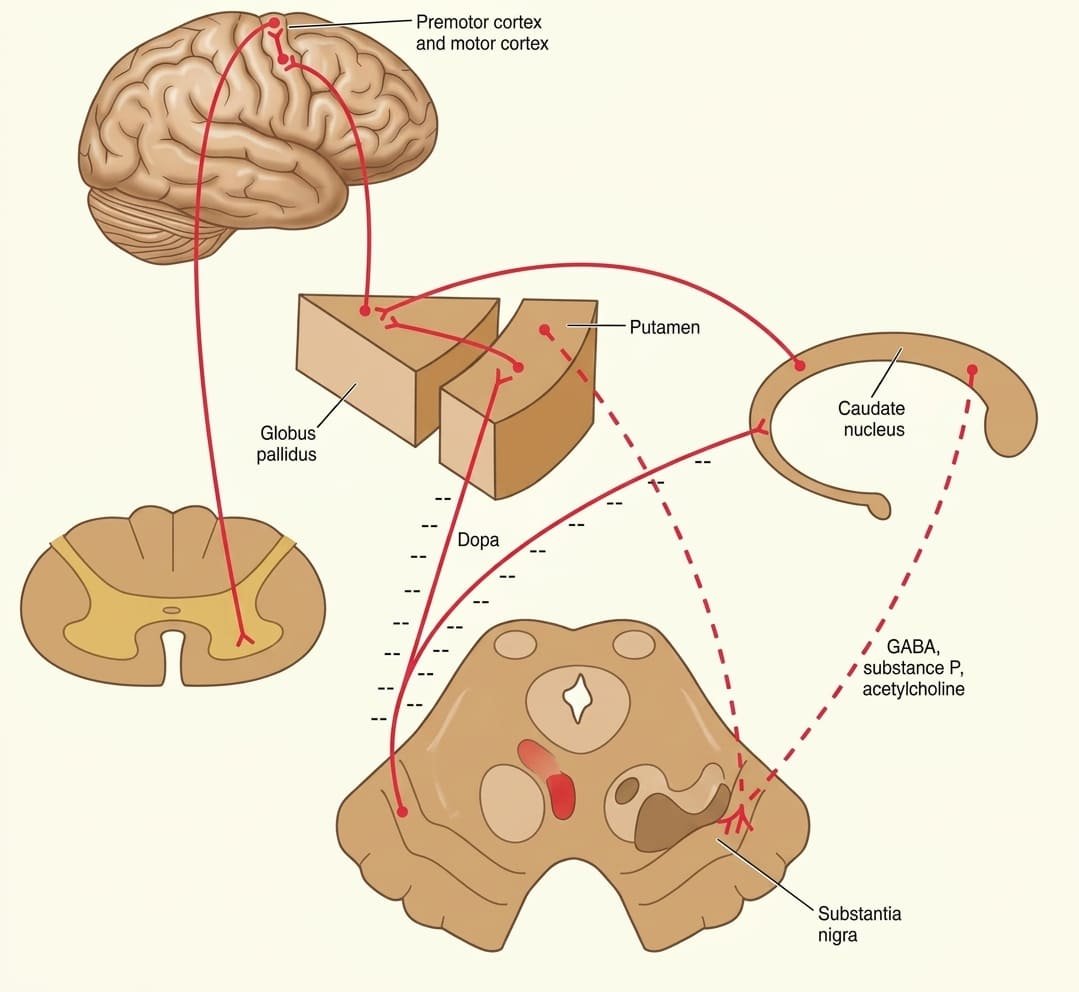
2. Hypokinetic Disorders (Damage to Dopaminergic Systems)
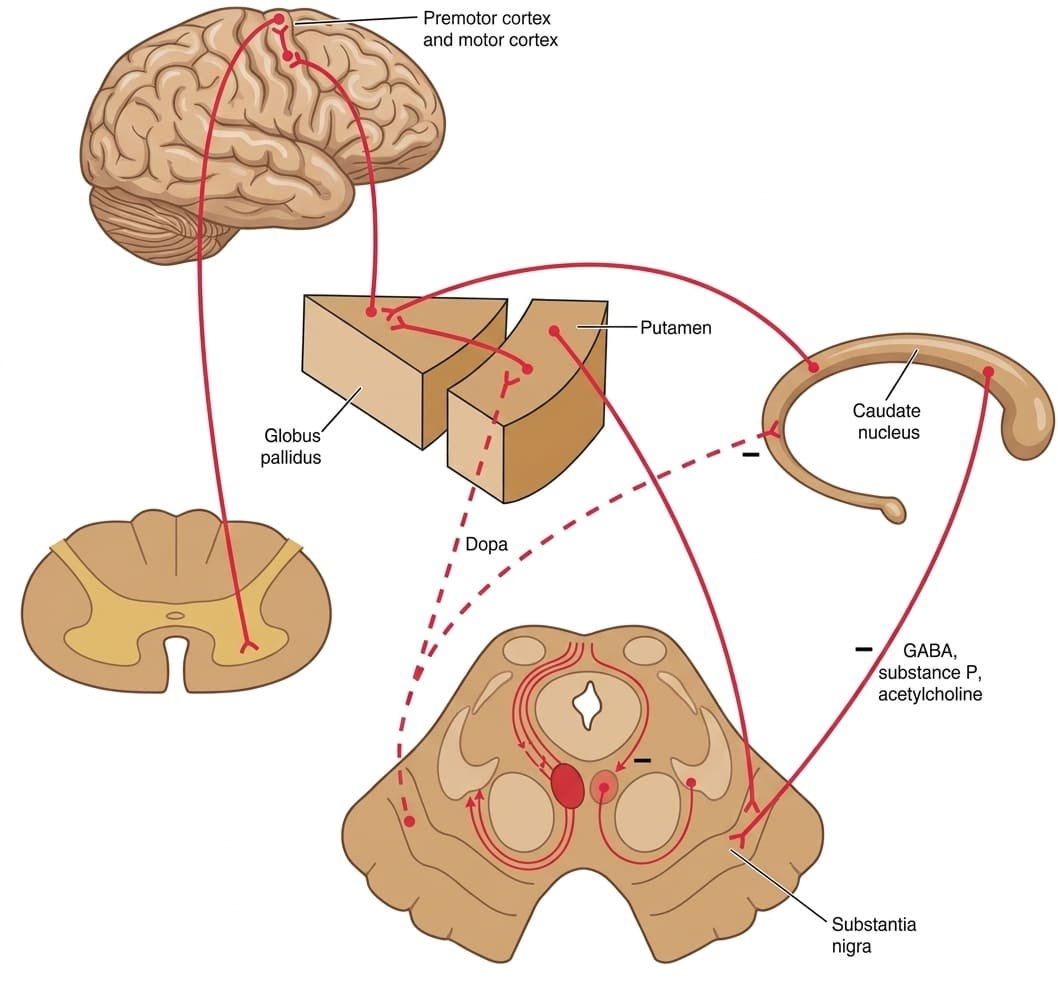
- Parkinson Disease: Chronic neurodegenerative disorder characterized by loss of ≥70% of dopaminergic neurons within the substantia nigra pars compacta (SNc). Histology shows eosinophilic intracytoplasmic inclusions containing α-synuclein (Lewy bodies).
Mechanism: Loss of dopamine depresses the direct pathway (via loss of D1 excitation) and disinhibits the indirect pathway (via loss of D2 inhibition), increasing GPi/SNr activity and suppressing thalamocortical drive.
Clinical Tetrad (TRAP):- Tremor: 4–6 Hz “pill-rolling” resting tremor, typically asymmetric at onset, resolving during voluntary action.
- Rigidity: “Lead-pipe” or “cogwheel” resistance to passive joint movement across flexor and extensor muscle groups.
- Akinesia / Bradykinesia: Poverty, slowness, and progressive fatigue in initiating movements; loss of facial expression (masked facies), decreased spontaneous blink rate, and micrographia.
- Postural Instability: Impaired righting reflexes, flexed stooped posture, and festinating gait with small, shuffling steps.
- Drug-Induced Parkinsonism: Reversible hypokinesia induced by pharmacologic blockade of striatal D2 receptors (first-generation typical antipsychotics like haloperidol, chlorpromazine) or dopamine-depleting agents (reserpine). Managed with centrally acting antimuscarinics (benztropine, trihexyphenidyl) to restore striatal dopamine/ACh balance.
The limbic system & limbic lobe
The term limbic (from Latin limbus, meaning “border”) was introduced by Paul Broca in 1878 (le grand lobe limbique) to describe an arc of phylogenetically ancient cortex encircling the brainstem and corpus callosum along the medial aspect of the cerebral hemisphere.
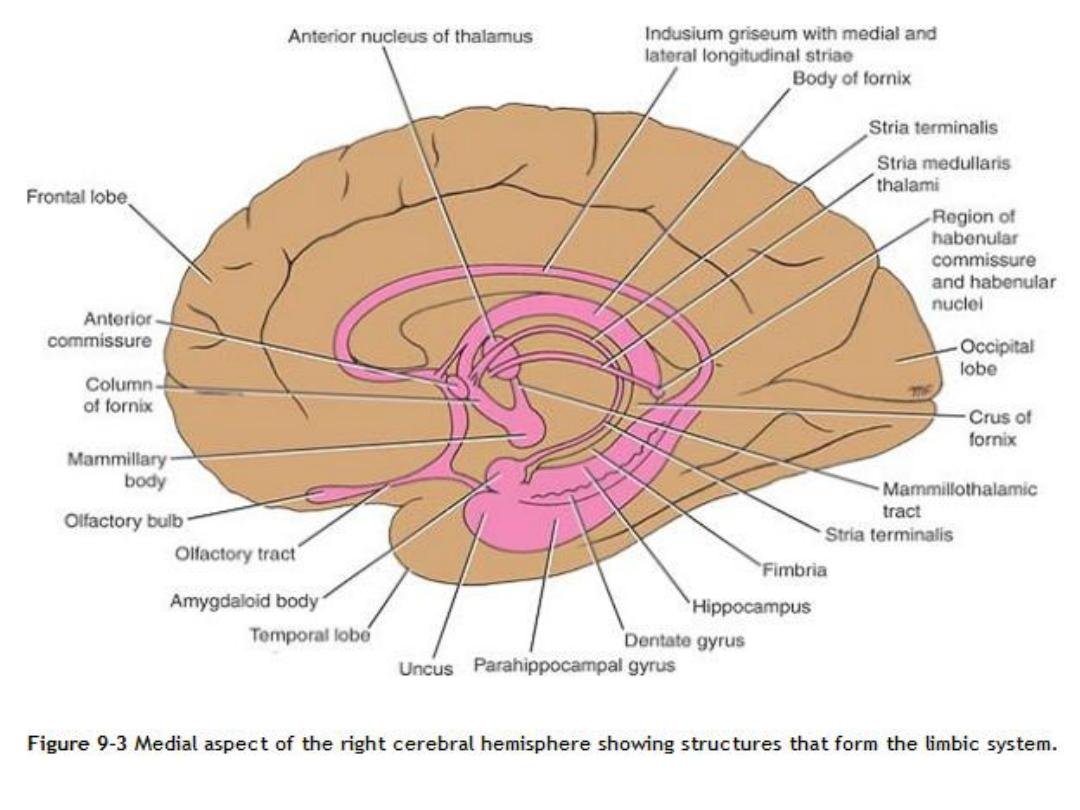
Limbic Lobe versus Limbic System
1. The Limbic Lobe (Anatomical Ring)
A continuous ring of cortex on the medial hemispheric surface, comprising:
- Subcallosal Gyrus (Paraterminal Gyrus): Cortex situated immediately anterior to the lamina terminalis and inferior to the rostrum of the corpus callosum.
- Cingulate Gyrus: Arches superiorly around the body of the corpus callosum within the longitudinal fissure.
- Isthmus of Cingulate Gyrus: Narrow cortical strip connecting the cingulate gyrus to the parahippocampal gyrus posterior to the splenium of the corpus callosum.
- Parahippocampal Gyrus: Cortex along the medial temporal lobe, bounded laterally by the collateral sulcus.
- Uncus: Hook-like anterior prominence of the parahippocampal gyrus overlying the amygdala.
2. The Limbic System (Functional Network)
Incorporates the limbic lobe along with interconnected subcortical gray nuclei, diencephalic structures, and midbrain pathways:
- Telencephalic Structures: Hippocampal formation (hippocampus, dentate gyrus, subiculum), amygdaloid complex, septal area, nucleus accumbens.
- Diencephalic Structures: Anterior thalamic nuclear group, dorsomedial nucleus of the thalamus, mammillary bodies, preoptic and hypothalamic nuclei, habenular nuclei.
- Connecting Fiber Bundles: Alveus, fimbria, fornix, mammillothalamic tract (bundle of Vicq d’Azyr), stria terminalis, stria medullaris thalami, and the medial forebrain bundle.
Rhinencephalon & olfaction
The rhinencephalon (“smell brain”) is the phylogenetically primitive component of the forebrain dedicated to processing olfaction. While olfaction dominates primitive vertebrate limbic systems, human olfaction is closely integrated with emotion and visceral memory.
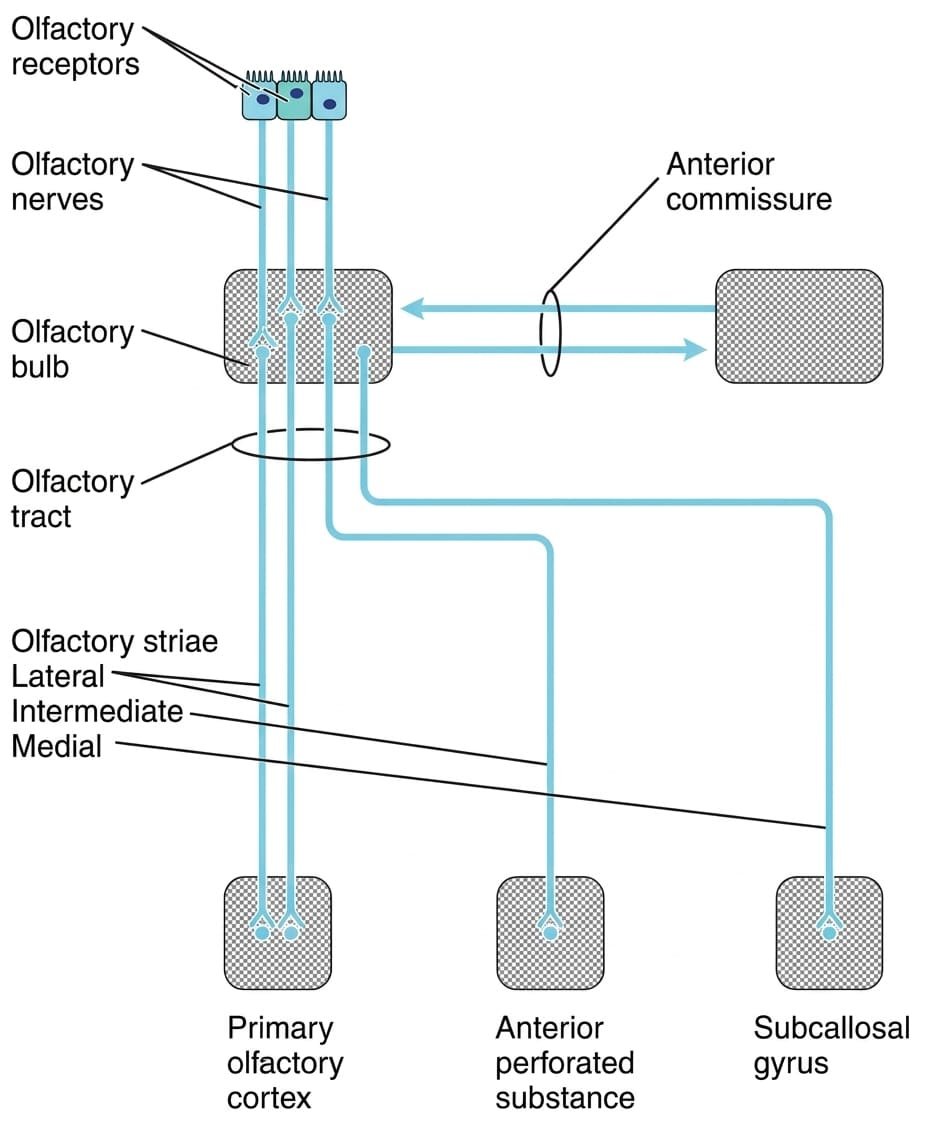
Components of the Olfactory Pathway
- Olfactory Nerve Rootlets (CN I): Unmyelinated central processes of bipolar olfactory receptor neurons located within the olfactory neuroepithelium in the roof of the nasal cavity. They traverse the cribriform plate of the ethmoid bone to enter the olfactory bulb.
- Olfactory Bulb: Laminated subcortical structure lying on the cribriform plate in the olfactory sulcus. Bipolar axons synapse with dendrites of mitral and tufted cells within spherical structures called glomeruli.
- Olfactory Tract: Narrow white-matter band carrying myelinated axons of mitral and tufted cells posteriorly. Expands rostral to the anterior perforated substance into the olfactory trigone.
- Olfactory Striae:
- Lateral Olfactory Stria: The primary functional pathway; projects directly to the primary olfactory cortex (piriform cortex, uncus, entorhinal area, and corticomedial amygdala) without requiring a thalamic relay.
- Medial Olfactory Stria: Projects via the anterior commissure to the contralateral olfactory bulb and the subcallosal (paraterminal) gyrus.
- Intermediate Stria: Terminates within the anterior perforated substance.
Evolutionary cortical layers
The cerebral mantle exhibits distinct cytoarchitectonic layering reflecting its evolutionary development:
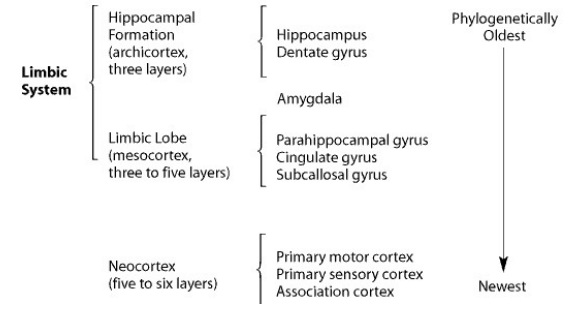
Cytoarchitectonic Subdivisions
- 1. Allocortex (≤3 Layers — Phylogenetically Oldest):
- Archicortex (3 Layers): Comprises the hippocampal formation (dentate gyrus, hippocampus proper [cornu Ammonis], subiculum). The three cellular layers are the molecular layer (superficial), the pyramidal layer (principal projection neurons), and the polymorphic layer (deep intrinsic interneurons). In the dentate gyrus, the pyramidal layer is replaced by a dense granule cell layer.
- Paleocortex (3 to 5 Layers): Includes the olfactory bulb, olfactory tubercle, and the piriform cortex of the anterior parahippocampal gyrus.
- 2. Mesocortex / Juxtallocortex (3 to 5 Layers — Transitional): Transitional cortex providing a boundary between allocortex and neocortex. Comprises the cingulate gyrus, isthmus, and the parahippocampal gyrus.
- 3. Neocortex / Isocortex (6 Layers — Phylogenetically Newest): Over 90% of the human cerebral mantle, composed of six cellular laminae (layers I to VI). Comprises primary motor cortex, primary sensory cortex, and multimodal association cortices.
The Papez circuit
In 1937, American neuroanatomist James Papez proposed a closed anatomical circuit as the biological mechanism of emotion. Contemporary neuroscience recognizes that while this circuit influences emotional expression, it functions primarily as the central pathway for declarative (episodic) memory consolidation.
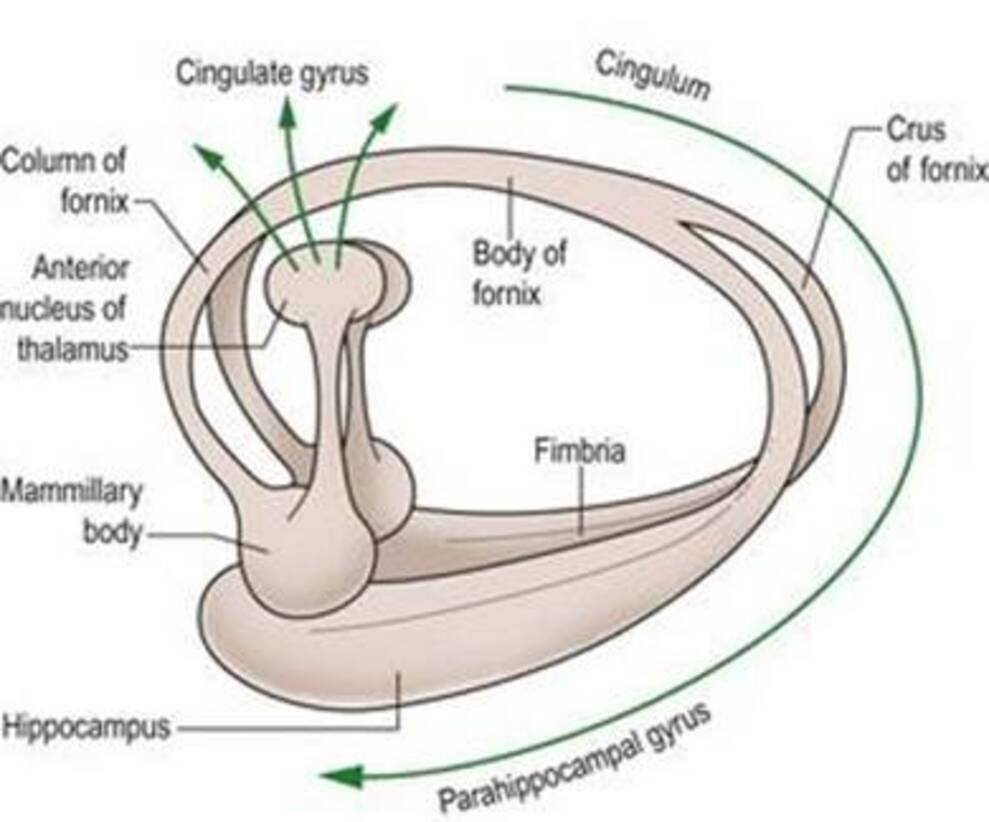
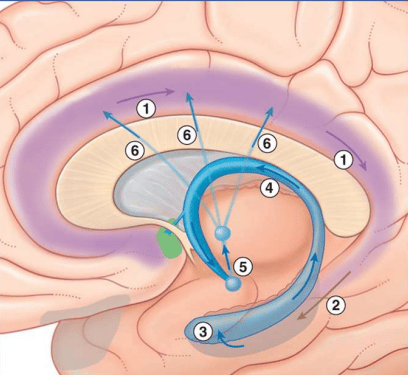
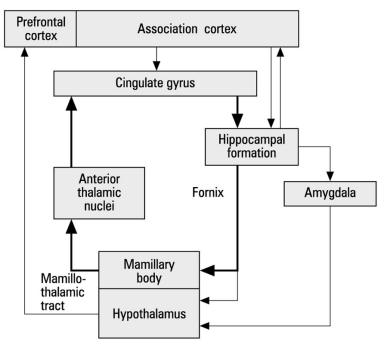
Stepwise Axonal Progression in the Circuit
- Hippocampus Proper & Subiculum: Pyramidal neurons project efferent axons into the alveus and fimbria, consolidating into the fornix.
- Fornix to Mammillary Bodies: The postcommissural fornix descends through the hypothalamus to synapse upon neurons in the medial mammillary nucleus.
- Mammillothalamic Tract (Bundle of Vicq d’Azyr): A compact, myelinated tract projecting from the mammillary bodies to the anterior nuclear group of the thalamus.
- Anterior Thalamic Radiations: Neurons in the anterior thalamic nucleus project through the anterior limb of the internal capsule to terminate in the cingulate gyrus.
- Cingulum: Long association fibers travel within the white matter core of the cingulate gyrus (the cingulum), sweeping posteriorly around the splenium of the corpus callosum into the parahippocampal gyrus.
- Perforant Pathway: Cingulate fibers synapse within the entorhinal cortex (Brodmann area 28), which projects via the perforant path through the subiculum to complete the loop in the dentate gyrus and hippocampus.
Hippocampal formation & trisynaptic loop
The hippocampal formation is an archicortical structure folded into the floor of the inferior (temporal) horn of the lateral ventricle, comprising three distinct regions: the dentate gyrus, the hippocampus proper (cornu Ammonis), and the subiculum.
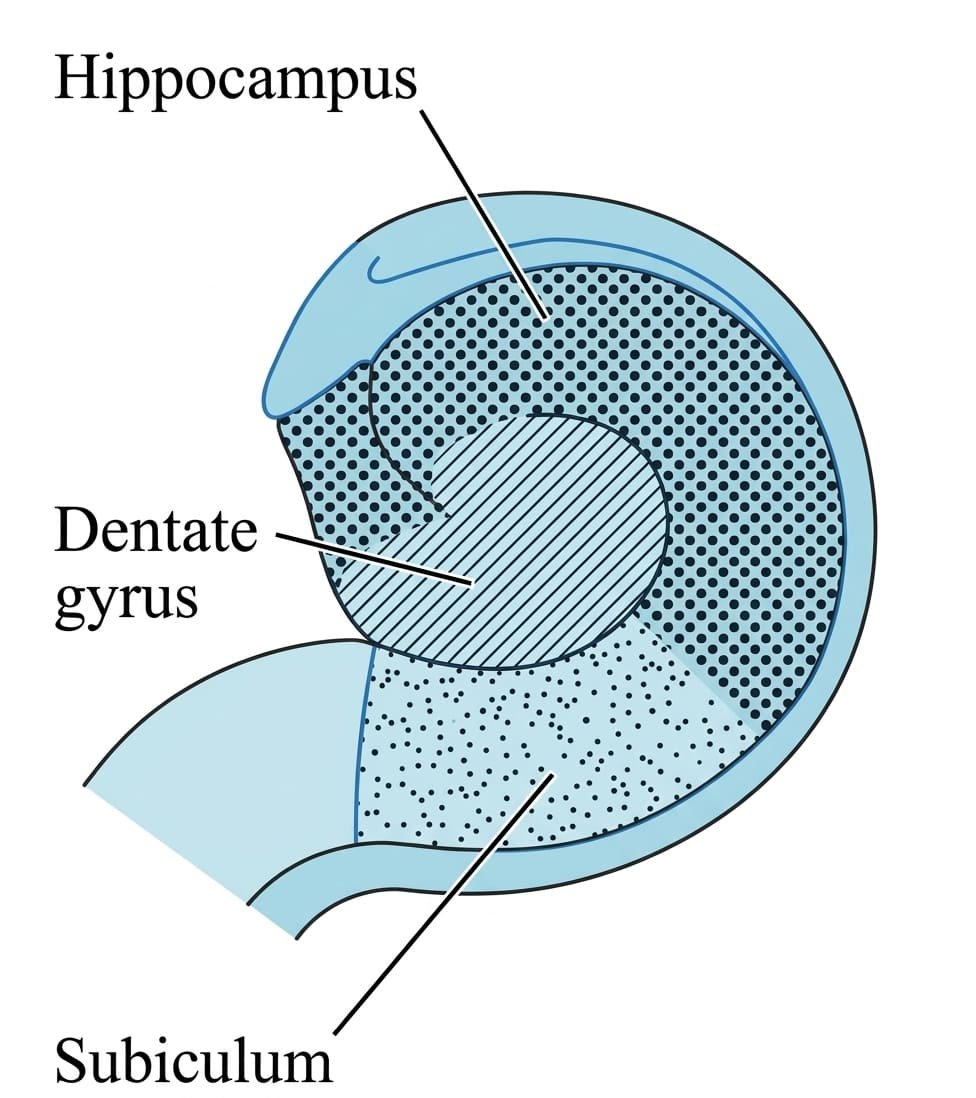
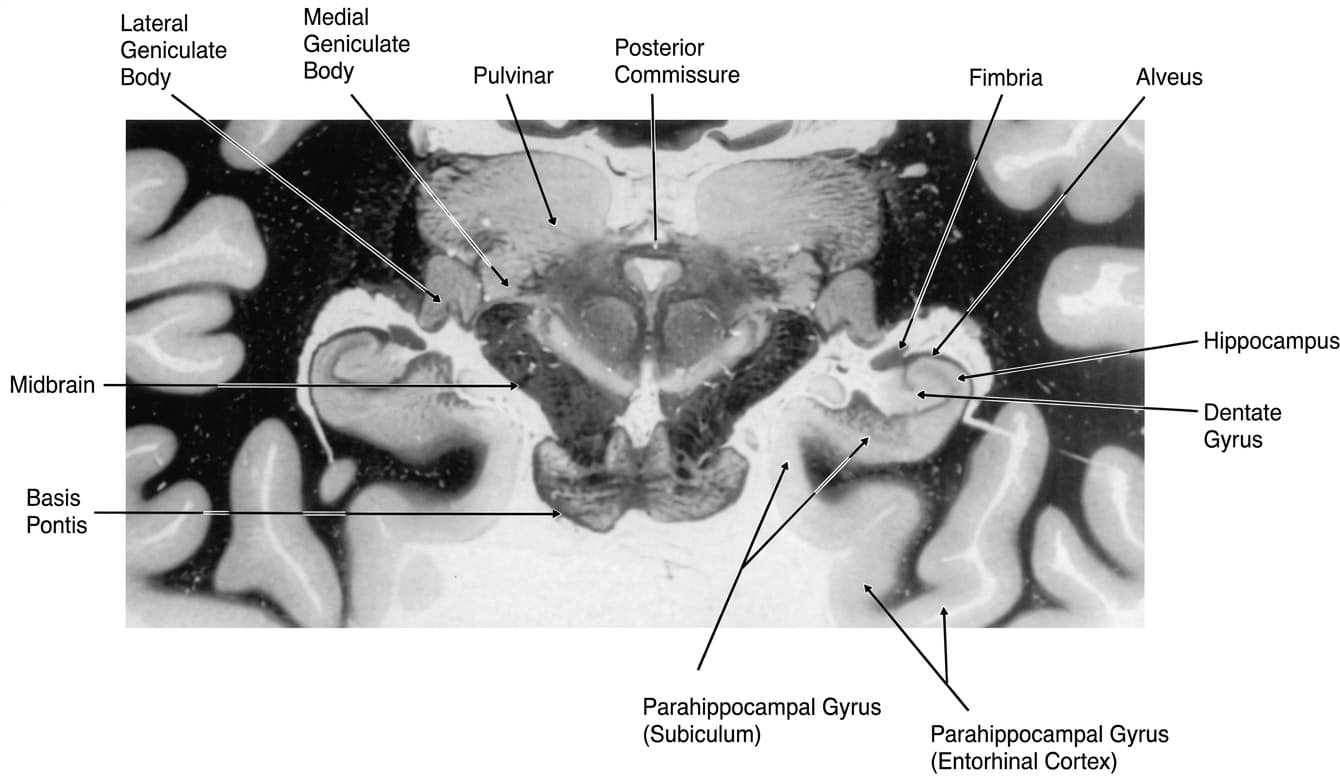
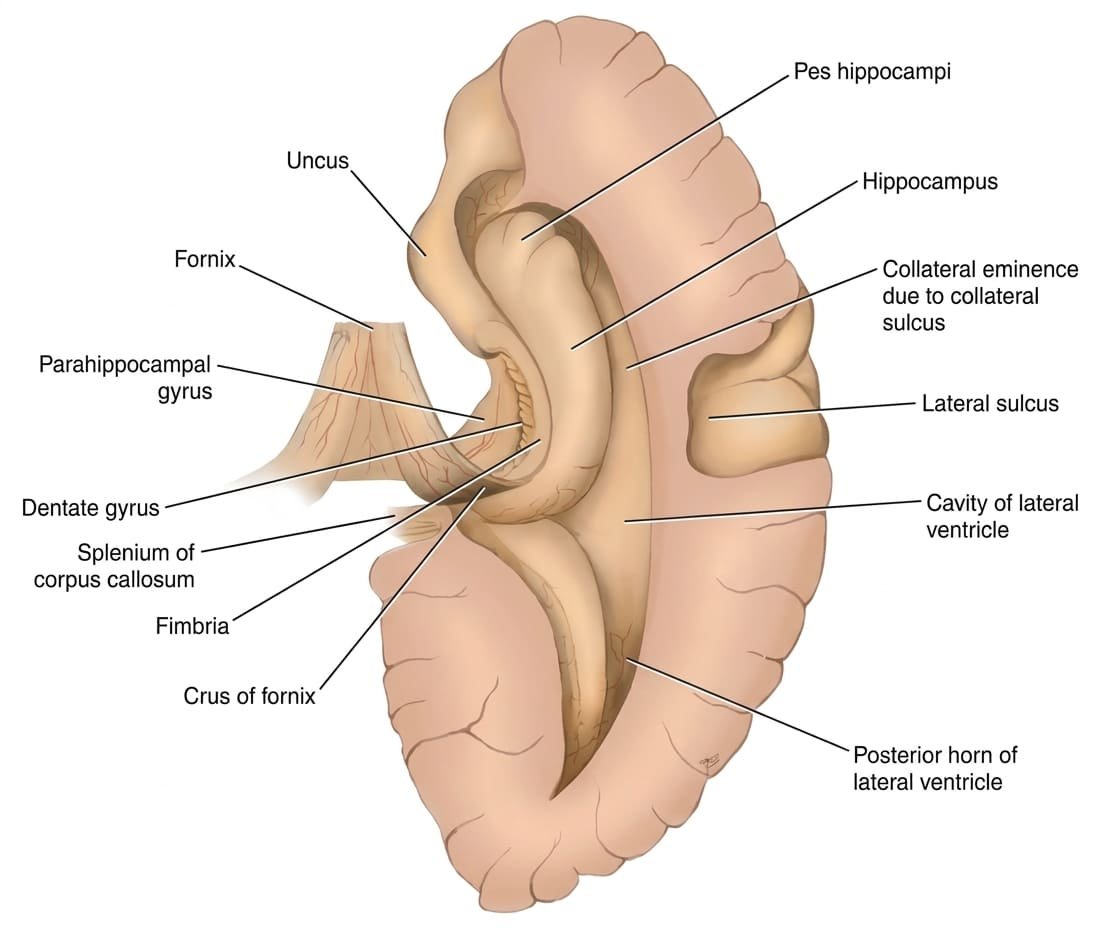
1. Subfields of the Hippocampus Proper (Cornu Ammonis)
Histologically divided into four distinct cytoarchitectonic sectors (CA1 to CA4):
- CA1 (Sommer’s Sector): Contains large pyramidal neurons exceptionally vulnerable to ischemic hypoxia, hypoglycemia, and status epilepticus. First area to undergo cell death in cardiac arrest or severe systemic shock.
- CA2: Narrow zone of densely packed, smaller pyramidal cells relatively resistant to ischemic injury.
- CA3: Large pyramidal cells giving origin to prominent recurrent excitatory axonal collaterals: the Schaffer collaterals.
- CA4: Deep pyramidal zone located within the hilus of the dentate gyrus.
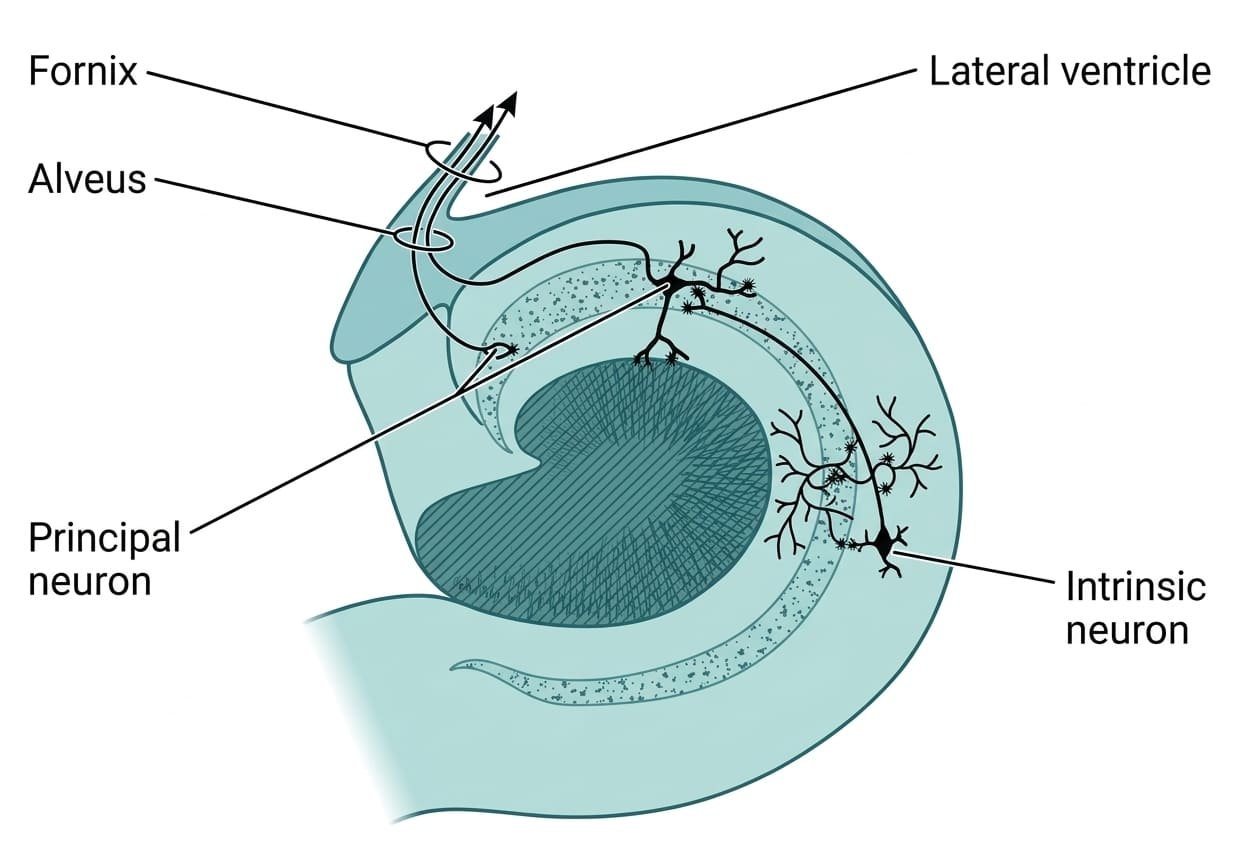
2. The Canonical Trisynaptic Circuit
Information flows through the hippocampal formation along an internal trisynaptic loop that drives long-term potentiation (LTP) and memory encoding:
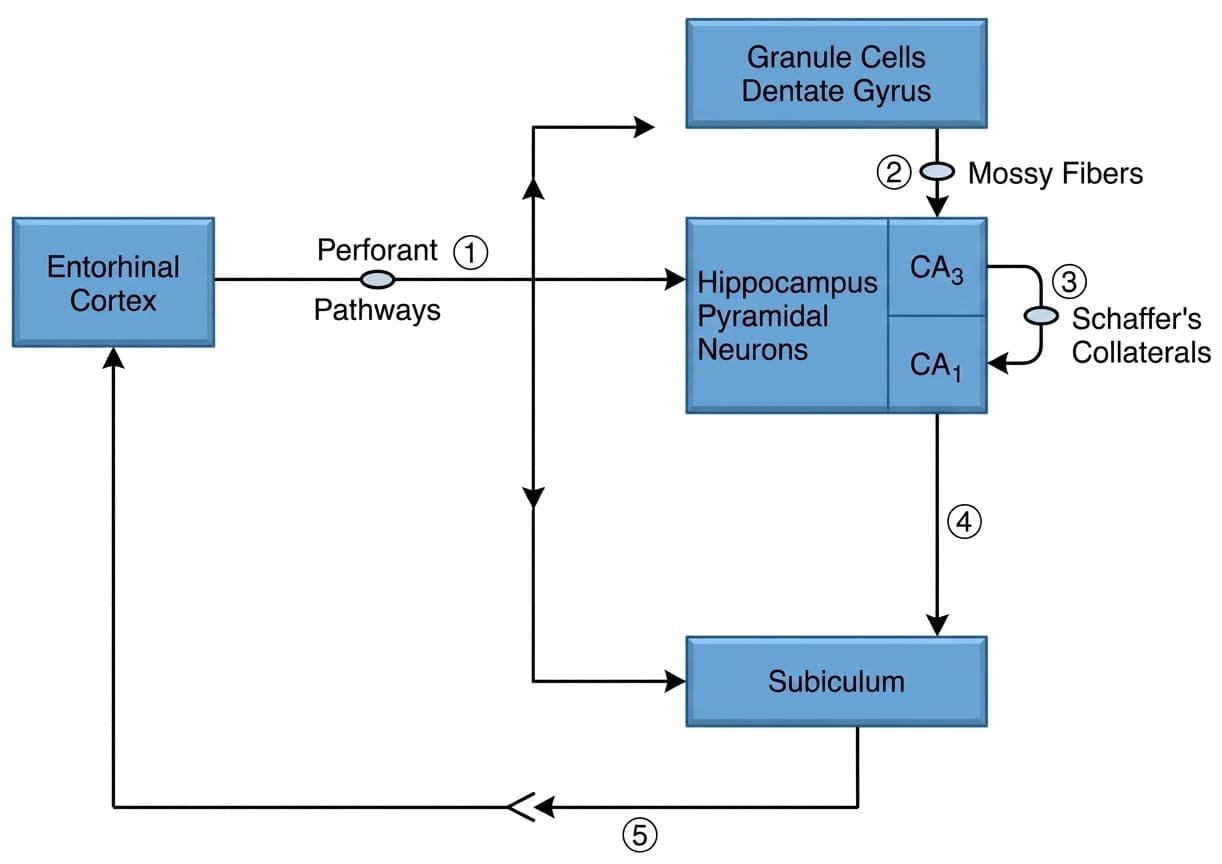
- Perforant Pathway: Axons from layer II/III of the entorhinal cortex pierce (perforate) the subiculum to synapse upon the dendrites of granule cells in the dentate gyrus.
- Mossy Fiber Pathway: Unmyelinated axons of dentate granule cells (mossy fibers) synapse upon the dendrites of pyramidal neurons in the CA3 region of the hippocampus.
- Schaffer Collaterals: CA3 pyramidal neurons send axonal collaterals (Schaffer collaterals) to synapse upon pyramidal neurons in the CA1 region.
- Output Stage: CA1 pyramidal neurons project to the subiculum. The subiculum sends projections back to the deep layers of the entorhinal cortex (closing the loop) and into the fornix.
The fornix & connecting pathways
The fornix (Latin for “arch”) is the primary C-shaped efferent white-matter tract of the hippocampal formation, containing approximately 1.2 million myelinated axons.

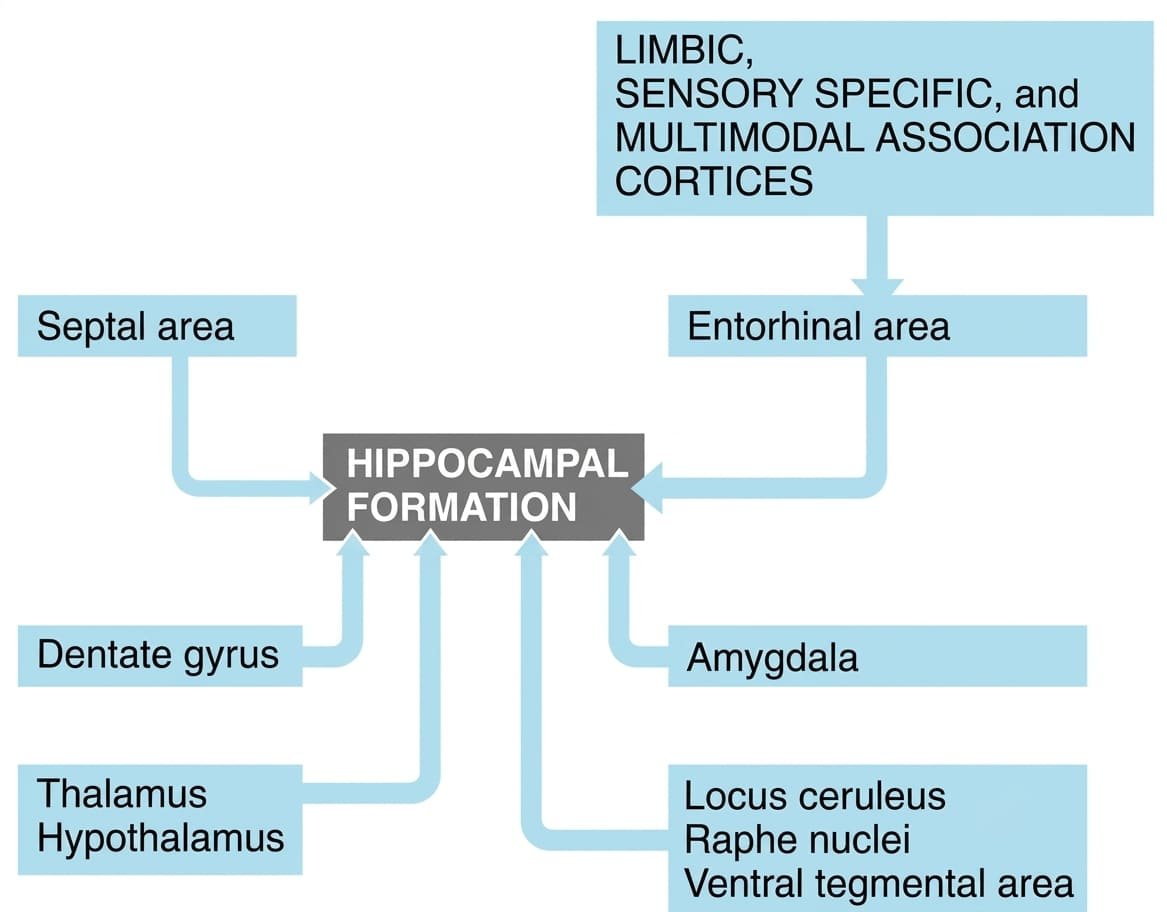
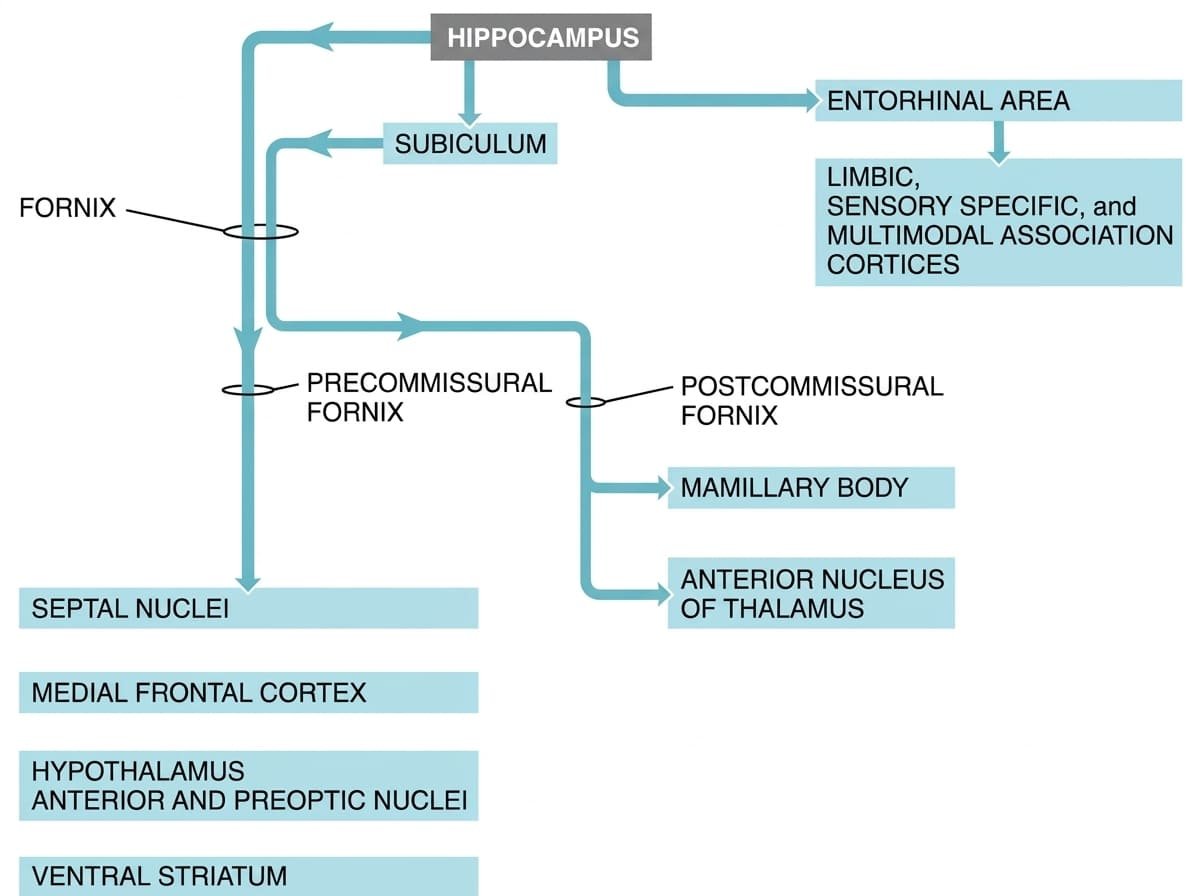
Anatomical Components of the Fornix
- Alveus: Thin layer of white matter covering the ventricular surface of the hippocampus, formed by axons emerging from hippocampal and subicular pyramidal neurons.
- Fimbria: Medial consolidation of the alveus forming a distinct flattened white ribbon along the medial border of the hippocampus.
- Crura of the Fornix: The fimbria arches posterosuperiorly under the splenium of the corpus callosum as the paired crura. Connected across the midline by the commissure of the fornix (psalterium / lyra Davidis), permitting bilateral interhippocampal communication.
- Body of the Fornix: The crura converge beneath the corpus callosum to form the midline body, suspended from the corpus callosum by the septum pellucidum and resting on the roof of the third ventricle.
- Columns of the Fornix & the Anterior Commissure: As the body arches forward over the interventricular foramen (of Monro), it bifurcates around the anterior commissure into:
- Precommissural Fornix: Fibers passing anterior to the anterior commissure, terminating in the septal nuclei, medial frontal cortex, anterior hypothalamus, and the ventral striatum.
- Postcommissural Fornix: Fibers passing posterior to the anterior commissure, traversing the hypothalamus to terminate in the medial nucleus of the mammillary bodies, the anterior thalamic nucleus, and the midbrain tegmentum.
The amygdaloid complex
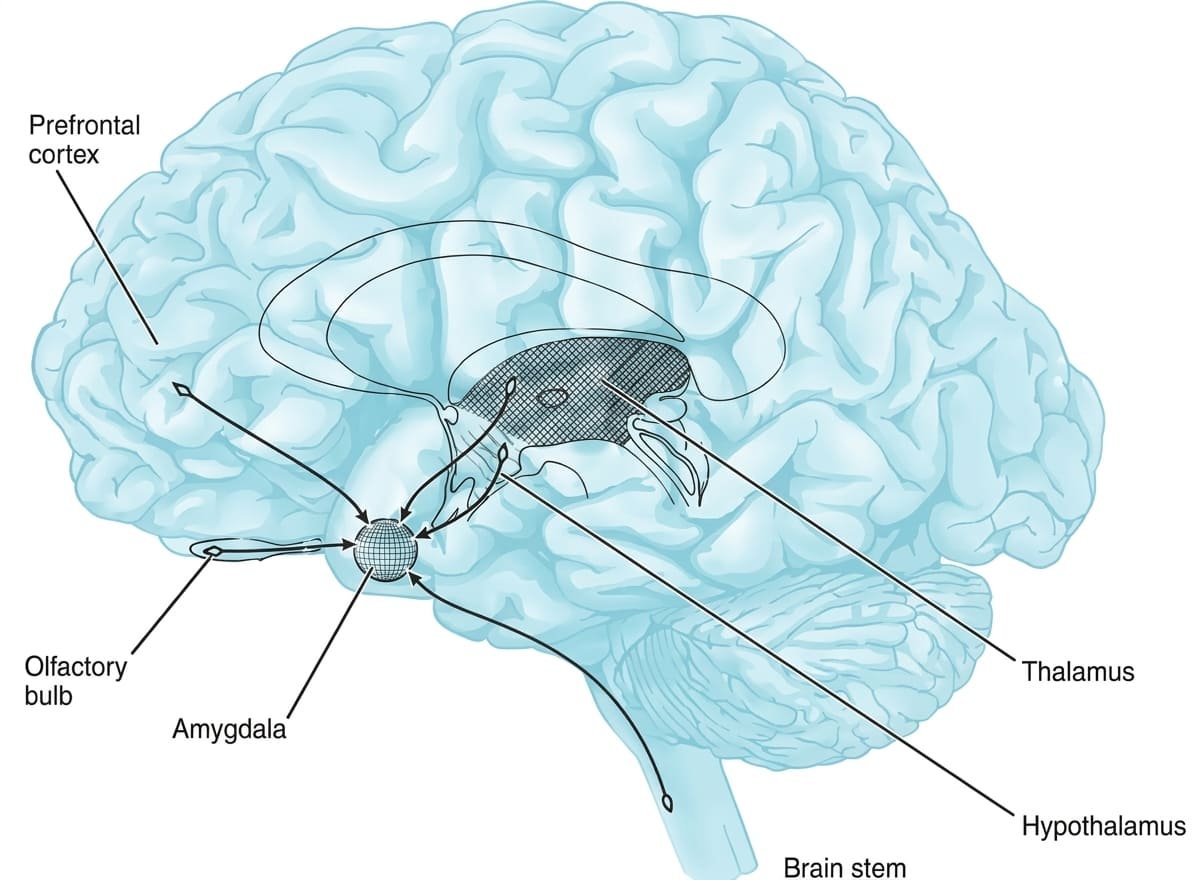
The amygdala (amygdaloid complex) is an ovoid collection of nuclei located deep within the anterior medial temporal lobe, sitting dorsomedial to the tip of the temporal horn of the lateral ventricle, anterior to the hippocampus, and partially underlying the uncus.
1. Nuclear Groups & Connectivity
- Basolateral Group (Largest): Highly developed in humans; receives sensory inputs from visual, auditory, and somatosensory association cortices and the thalamus. Processes emotional significance and valence, projecting to the central nucleus and prefrontal cortex.
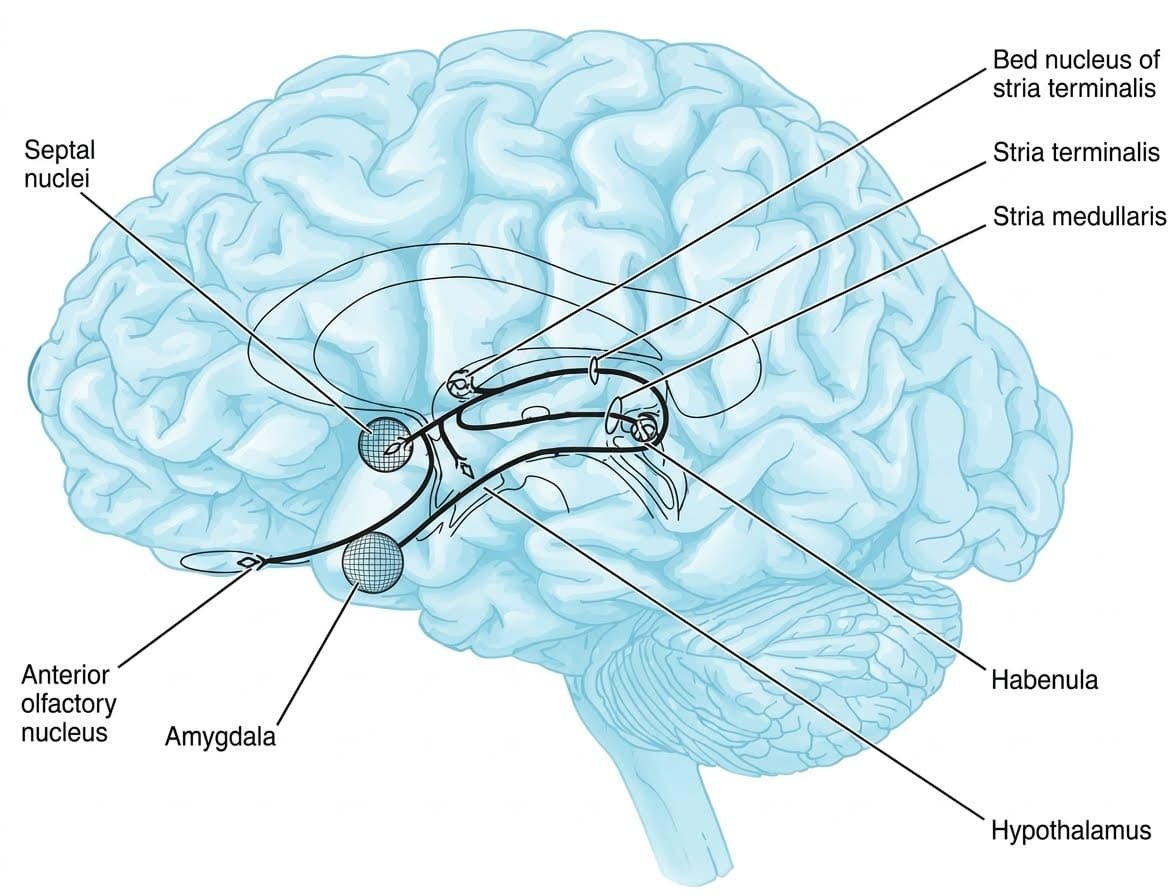
- Central Nucleus: The major efferent output station governing autonomic and motor responses to emotion. Projects to the hypothalamus (autonomic activation) and brainstem nuclei (locus ceruleus, periaqueductal gray, dorsal vagal motor complex).
- Corticomedial (Olfactory) Group: Receives direct olfactory projections from the olfactory bulb; coordinates feeding reflexes and neuroendocrine responses to pheromones and scents.
2. Primary Efferent Pathways
- Stria Terminalis: A C-shaped tract that emerges from the amygdala and arches along the groove between the caudate nucleus and thalamus (sulcus terminalis), accompanied by the thalamostriate vein. Terminates in the bed nucleus of the stria terminalis (BNST), septal nuclei, and anterior hypothalamus.
- Ventral Amygdalofugal Pathway: A direct, non-arched pathway coursing medially through the substantia innominata to terminate in the mediodorsal nucleus of the thalamus, the lateral hypothalamus, and brainstem autonomic centers.
3. Functions of the Amygdala
- Conditioned Fear: Essential for acquiring and storing learned fear responses (fear conditioning). Links neutral conditioned stimuli to aversive unconditioned stimuli.
- Facial Expression Processing: Bilateral amygdala activation is required to detect emotional expressions in others, especially fearful, suspicious, or untrustworthy faces.
- Autonomic & Motor Coordination: Central nucleus activation drives sympathetic arousal: tachycardia, hypertension, pupillary dilation, tachypnea, and behavioral freezing via projections to the periaqueductal gray.
The septal area & reward centers
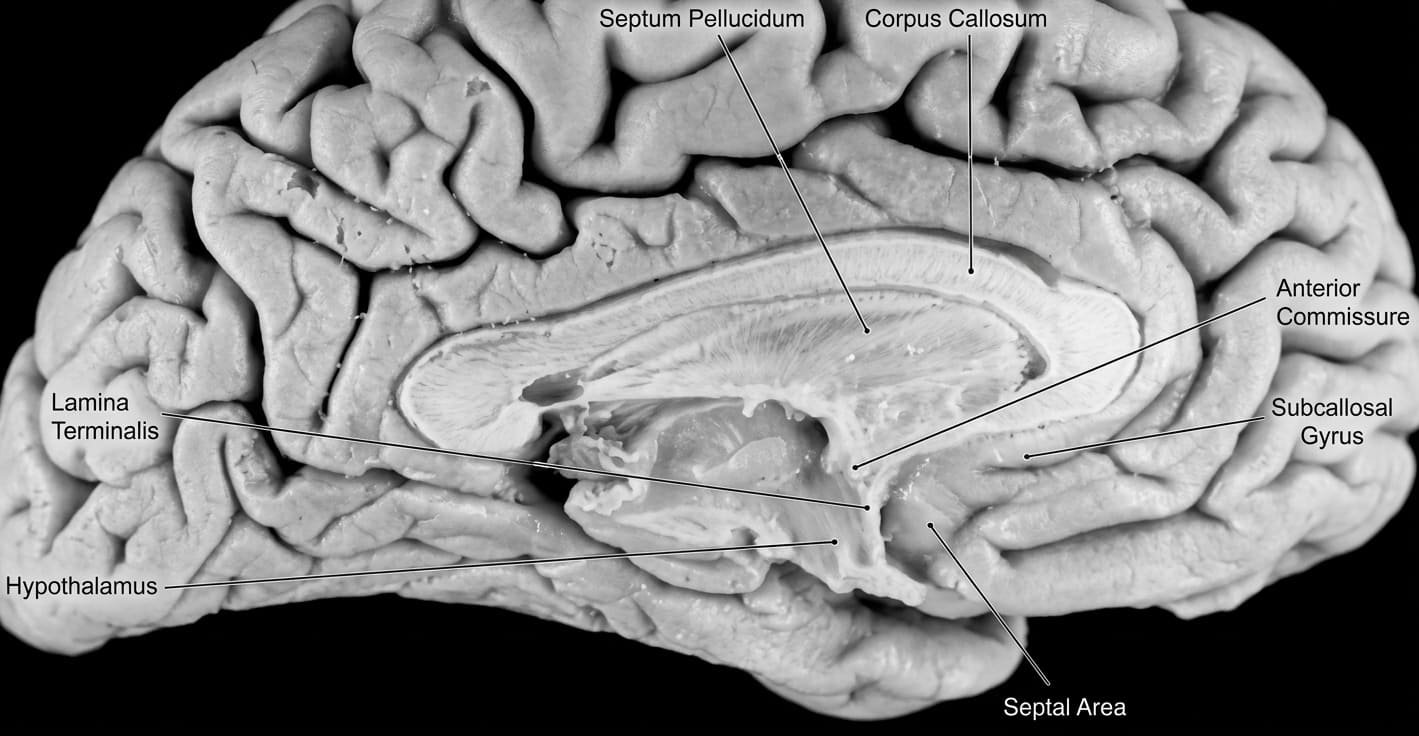
The septal area is a medial telencephalic region positioned anterior to the lamina terminalis and anterior commissure, functioning as a primary limbic relay and reward center.
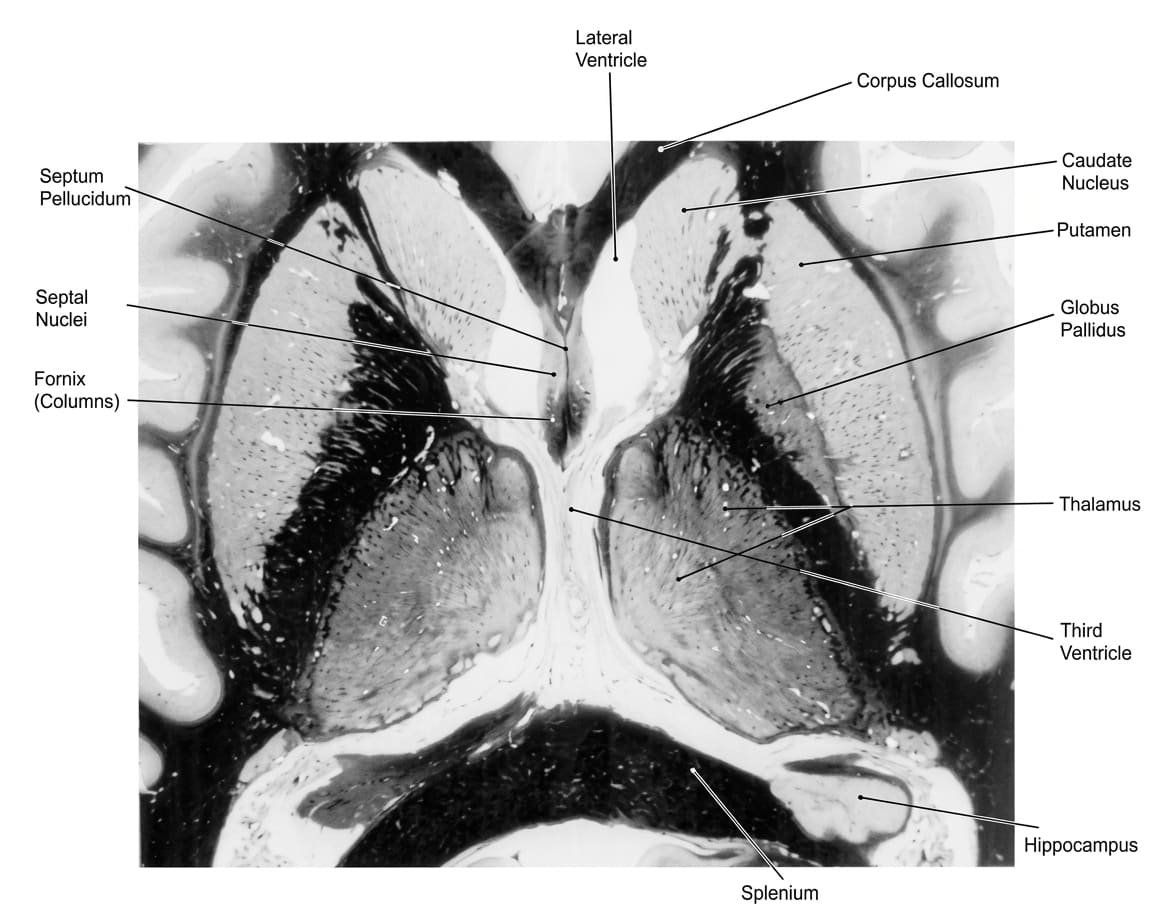
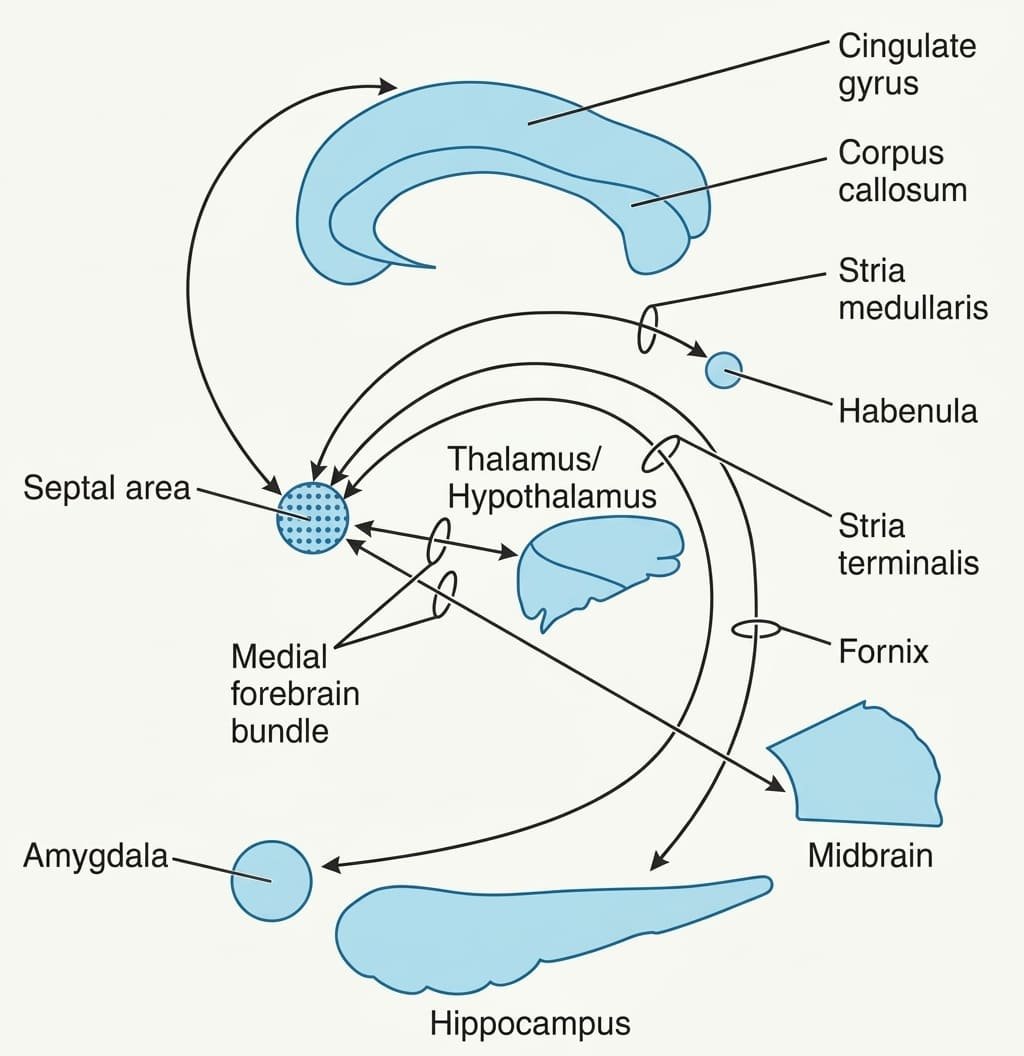
Anatomical Subdivisions
- Septum Pellucidum: A thin, translucent, double-leaf glial membrane separating the anterior horns of the lateral ventricles, extending between the corpus callosum and the fornix. Contains no neurons and is lined by ependyma.
- Septum Verum (True Septum): The subcortical gray structure situated ventral to the septum pellucidum, containing the septal nuclei (medial and lateral septal nuclei). Receives major cholinergic and GABAergic inputs.
Physiological Functions versus Lesion Manifestations
Scroll the table sideways on a smaller screen.
| Physiological Domain | Normal Function / Stimulation Response | Consequence of Bilateral Septal Lesion |
|---|---|---|
| Emotional Tone & Aggression | Moderates affective reactivity; dampens aggression and autonomic panic | “Septal Rage”: Marked hyperirritability, violent aggressive outbursts, and extreme over-reactivity to benign sensory stimuli |
| Reward & Reinforcement | Primary subcortical pleasure/reward center; drives positive behavioral reinforcement | Anhedonia; loss of positive reinforcement drives |
| Fluid Homeostasis | Regulates water intake via hypothalamic osmoreceptor relays | Primary Polydipsia: Compulsive, pathological overdrinking of water |
| Autonomic Regulation | Stimulation inhibits sympathetic output, slows heart rate via vagal activation | Sympathetic hyper-responsiveness; tachycardia |
| Exploratory Locomotion | Maintains sustained, adaptive attention to subtle environmental cues | Transient hyperactivity to novel stimuli that rapidly deteriorates into complete immobility |
The reticular formation
The reticular formation is a continuous, diffuse network of interconnected neurons and interlacing nerve fibers occupying the core of the brainstem, extending from the caudal medulla through the pons and midbrain into the intralaminar nuclei of the thalamus.
Longitudinal Nuclear Columns
- 1. Median (Raphe) Column: Occupies the midline across the brainstem. Composed of serotonergic neurons (nucleus raphe magnus in the medulla, dorsal raphe nucleus in the midbrain). Mediates pain modulation (descending analgesia pathways) and sleep regulation.
- 2. Medial Column (Magnocellular): Contains large neurons that give rise to long ascending and descending projections, including the medial (pontine) and lateral (medullary) reticulospinal tracts regulating extensor and flexor tone in posture and locomotion.
- 3. Lateral Column (Parvocellular): Contains small neurons that receive sensory inputs (somatosensory, auditory, vestibular, visceral) and coordinate autonomic reflexes (cardiovascular center, medullary respiratory centers, vomiting center).
The Ascending Reticular Activating System (ARAS)
The ARAS is an ascending polysynaptic pathway originating from the upper pontine and mesencephalic reticular core. It projects via two routes to modulate cortical alertness:
- Thalamic Route: Projects to the intralaminar and reticular nuclei of the thalamus, which then project diffusely across all cortical layers to drive desynchronized, low-voltage, high-frequency EEG activity characteristic of wakefulness.
- Extrathalamic (Basal Forebrain) Route: Projects through the subthalamus and lateral hypothalamus directly to the basal forebrain (nucleus basalis of Meynert), sending cholinergic inputs to the neocortex.
Clinical neuropsychiatry & limbic syndromes
Klüver-Bucy Syndrome
A neurobehavioral syndrome resulting from bilateral destruction of the anterior temporal lobes, particularly the amygdaloid nuclei (historically demonstrated in rhesus monkeys by Heinrich Klüver and Paul Bucy; seen clinically in herpes simplex encephalitis, severe traumatic brain injury, or bilateral temporal resections):
- Placidity & Docility: Complete loss of normal fear, anger, and defensive aggression; lack of emotional reactivity.
- Visual Agnosia (“Psychic Blindness”): Inability to recognize familiar objects or individuals visually, despite intact visual acuity.
- Hyperorality: Compulsion to explore all environmental objects with the mouth rather than the hands.
- Hypermetamorphosis: Compulsive urge to attend and react to every visual stimulus in the field.
- Hyperphagia (Dietary Changes): Markedly increased appetite; consumption of non-food items (pica).
- Hypersexuality: Markedly increased sexual drive with indiscriminate, inappropriate partner choices.
Wernicke-Korsakoff Syndrome
A nutritional neuropsychiatric emergency caused by severe thiamine (vitamin B1) deficiency, common in chronic alcohol dependency, malnutrition, and hyperemesis gravidarum:
- Wernicke Encephalopathy (Acute & Reversible): Classic clinical triad: (1) Oculomotor dysfunction (bilateral abducens palsies, horizontal nystagmus); (2) Cerebellar ataxia (wide-based gait); and (3) Global confusion. Pathology shows microvascular petechial hemorrhages in the mammillary bodies, periaqueductal gray, and dorsomedial thalamus.
- Korsakoff Psychosis (Chronic & Irreversible): Develops if thiamine is not provided promptly. Characterized by severe anterograde amnesia (inability to form new declarative memories) and retrograde amnesia with confabulation (inventing fabricated memories to fill memory gaps, without intent to deceive). Directly caused by necrosis of the medial mammillary nuclei and anterior/dorsomedial thalamus within the Papez circuit.
Alzheimer Disease & Hippocampal Sclerosis
- Early Hippocampal Atrophy: Neurofibrillary tangles (hyperphosphorylated tau protein) and extracellular amyloid-β plaques appear earliest in the entorhinal cortex and CA1 field of the hippocampus. This selective early damage impairs the perforant pathway and trisynaptic circuit, explaining why short-term memory impairment and anterograde amnesia are the earliest clinical signs of Alzheimer disease.
- Transient Global Amnesia (TGA): Sudden, temporary episode of severe anterograde amnesia lasting ≤24 hours, during which the patient repeatedly asks the same orientation questions. Associated with transient metabolic or ischemic stress in the CA1 sectors of bilateral hippocampi.
Temporal Lobe Epilepsy & Uncinate Fits
- Mesial Temporal Sclerosis: Gliosis and neuronal loss in the hippocampus and amygdala is the most common cause of intractable focal epilepsy.
- Uncinate Fits: Seizure foci localized to the uncus and primary olfactory cortex produce characteristic auras: unpleasant, phantom olfactory or gustatory hallucinations (e.g., burning rubber, rotting fish) accompanied by chewing/lip-smacking automatisms, epigastric rising sensations, and déjà vu.
Quick recap
References
The following authoritative neuroanatomy, neurophysiology, and clinical neurology texts support this curriculum note:
- Snell’s Clinical Neuroanatomy: Splittgerber, R. (2019) Snell’s Clinical Neuroanatomy. 8th edn. Philadelphia: Wolters Kluwer. [Chapter 9: The Basal Nuclei; Chapter 13: The Limbic System; Chapter 6: The Reticular Formation].
- Gray’s Anatomy: Standring, S. (2021) Gray’s Anatomy: The Anatomical Basis of Clinical Practice. 42nd edn. London: Elsevier. [Section 3: Neuroanatomy; Chapter 24: Basal Ganglia; Chapter 25: Limbic System].
- Blumenfeld’s Neuroanatomy: Blumenfeld, H. (2021) Neuroanatomy through Clinical Cases. 3rd edn. Sunderland: Sinauer Associates / Oxford University Press. [Chapter 16: Basal Ganglia; Chapter 18: Limbic System and Memory].
- Principles of Neural Science: Kandel, E.R., Koester, J.D., Mack, S.H. and Siegelbaum, S.A. (2021) Principles of Neural Science. 6th edn. New York: McGraw-Hill Education. [Chapter 38: The Basal Ganglia; Chapter 54: The Hippocampus and Memory].
- Adams and Victor’s Neurology: Ropper, A.H., Samuels, M.A., Klein, J.P. and Prasad, S. (2019) Adams and Victor’s Principles of Neurology. 11th edn. New York: McGraw-Hill Education. [Chapter 4: Disorders of Movement: The Extrapyramidal Motor System; Chapter 26: The Limbic Lobes and the Neurology of Emotion].