Functions of the Skin
A comprehensive study of the integumentary system's roles in protection, thermoregulation, sensation, excretion, and metabolism, including clinical applications and structural mechanisms.
1. Overview
The skin performs a diverse array of functions essential for homeostasis, protection, and interaction with the environment. These functions can be broadly categorized into protective, regulatory, sensory, metabolic, and social functions. Each function is mediated by specific structural components and cellular mechanisms within the skin layers.
2. Protective Functions
The skin serves as the body's first line of defense against external threats. This protective role is multifaceted and involves mechanical, chemical, biological, and ultraviolet barriers.
2.1 Mechanical Barrier
- Stratum corneum: Provides a tough, keratinized surface that resists abrasion, friction, and minor trauma.
- Dermal collagen and elastin: Provide tensile strength and elasticity, allowing the skin to withstand stretching and pressure.
- Hypodermis: Cushions underlying structures against impact and mechanical forces.
2.2 Chemical Barrier
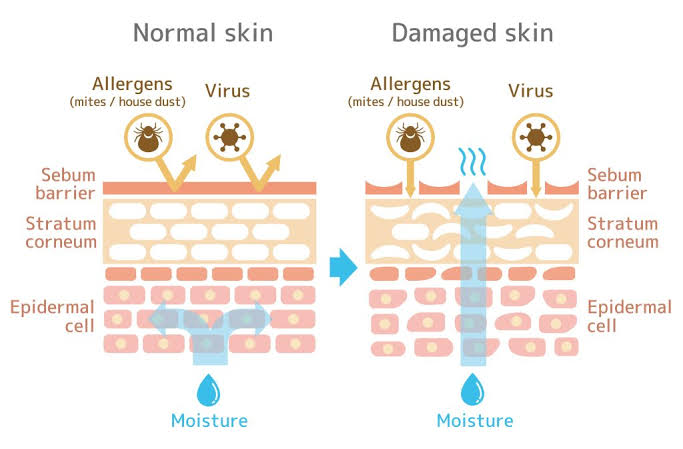
- The acid mantle: A surface film with a pH of 4.5–6.5 that inhibits the growth of pathogenic bacteria and fungi.
- Sebum: Produced by sebaceous glands, containing fatty acids with antimicrobial properties.
- Epidermal lipids: Ceramides, cholesterol, and free fatty acids in the stratum corneum form a waterproof barrier preventing transepidermal water loss (TEWL) and the entry of hydrophilic toxins.
2.3 Biological Barrier
- Langerhans cells: Dendritic cells in the epidermis that capture antigens and present them to T lymphocytes to initiate adaptive immune responses.
- Keratinocytes: Produce antimicrobial peptides such as defensins and cathelicidins that directly kill pathogens.
- Skin microbiome: Commensal bacteria (e.g., Staphylococcus epidermidis) compete with pathogens for resources and produce bacteriocins.
2.4 Ultraviolet (UV) Protection
- Melanin: Produced by melanocytes; absorbs UV radiation (UVA and UVB) to prevent DNA damage in keratinocytes.
- Stratum corneum: Scatters and reflects a portion of incident UV radiation.
- DNA repair: Enzymatic mechanisms in keratinocytes correct UV-induced damage.
Barrier Defects
Defects in the skin barrier (e.g., atopic dermatitis, ichthyosis) lead to increased transepidermal water loss (TEWL), susceptibility to infections, and allergen penetration. Barrier repair therapy with ceramide-containing emollients is a cornerstone of management.
3. Thermoregulation
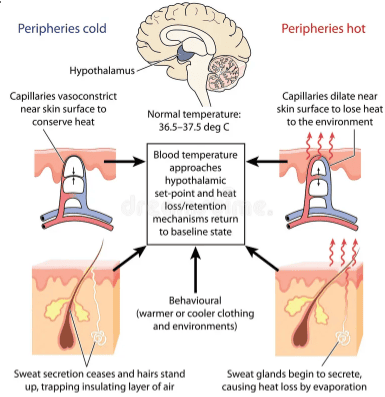
The skin is the primary organ of thermoregulation, maintaining a core body temperature of approximately 37°C through coordinated vascular, neural, and glandular mechanisms.
3.1 Heat Dissipation (In Hot Conditions)
- Vasodilation: Dermal blood vessels dilate, increasing blood flow to the skin surface to facilitate heat loss via radiation, conduction, and convection.
- Eccrine sweating: 2–4 million eccrine glands secrete a hypotonic fluid (99% water, NaCl, urea, lactate). Evaporation of this sweat absorbs latent heat of vaporization (2,430 J/g), effectively cooling the body.
3.2 Heat Conservation (In Cold Conditions)
- Vasoconstriction: Dermal arterioles constrict, shunting blood away from the skin surface to minimize heat loss.
- Piloerection: Arrector pili muscles contract, causing hairs to stand erect ("goosebumps"). In humans, this provides minimal insulation but is significant in furry mammals.
- Subcutaneous fat: Adipose tissue in the hypodermis provides thermal insulation.
Anhidrosis (absence of sweating) in burn patients or those with ectodermal dysplasia severely impairs thermoregulation and can lead to life-threatening hyperthermia. Conversely, hyperhidrosis (excessive sweating) causes significant social and functional impairment.
4. Sensation
The skin contains an extensive network of sensory nerve endings and specialized receptors that detect touch, pressure, temperature, pain, and itch.
4.1 Mechanoreceptors
- Meissner corpuscles: Rapidly adapting; located in dermal papillae. Detect light touch and texture (abundant in glabrous skin).
- Pacinian corpuscles: Rapidly adapting; located in the deep dermis and hypodermis. Detect deep pressure and high-frequency vibration.
- Merkel discs: Slowly adapting; located in the stratum basale. Detect sustained touch and pressure.
- Ruffini endings: Slowly adapting; located in the dermis. Detect skin stretch and torque.
4.2 Thermoreceptors and Nociceptors
- Thermoreceptors: Free nerve endings located at varying depths. Cold receptors are superficial (0.15–0.17 mm); warm receptors are deeper (0.3–0.6 mm).
- Nociceptors: Free nerve endings that respond to tissue-damaging stimuli (mechanical, thermal, chemical) and mediate protective reflexes.
5. Excretion and Secretion
5.1 Excretion
- Sweat: Eliminates small amounts of urea, uric acid, ammonia, and lactic acid, contributing to nitrogenous waste elimination.
- Glandular bypass: In renal failure, the skin can become an important accessory excretory organ for urea, sometimes manifesting as uremic frost.
5.2 Secretion
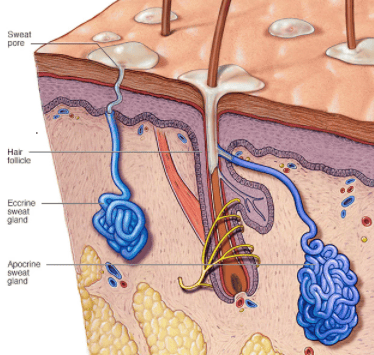
- Sebaceous glands: Secrete sebum (lipids, wax esters, squalene), which lubricates skin/hair and provides antimicrobial fatty acids.
- Apocrine sweat glands: Located in axilla, areola, and anogenital regions. Secrete a protein-rich fluid that is odorless until acted upon by skin bacteria.
- Ceruminous glands: Found in the external auditory canal; secrete cerumen (earwax) to protect the tympanic membrane.
6. Vitamin D Synthesis
The skin is the primary site of Vitamin D synthesis. Exposure to UVB radiation (wavelength 290–315 nm) converts 7-dehydrocholesterol in the epidermis to previtamin D3, which then isomerizes to Vitamin D3 (cholecalciferol).
Activation Pathway:
- Step 1: UV exposure in the skin forms Vitamin D3.
- Step 2: Transported to the liver for hydroxylation.
- Step 3: Final hydroxylation in the kidneys to form calcitriol (1,25-dihydroxyvitamin D3).
Function: Calcitriol regulates calcium and phosphate metabolism, essential for bone mineralization. Deficiency causes rickets in children and osteomalacia in adults.
Dark-skinned individuals require longer sun exposure to synthesize adequate Vitamin D due to higher melanin content. In regions with limited sunlight, dietary supplementation is essential.
7. Social and Psychological Functions
- Non-verbal communication: Mediated by facial muscles and skin (facial expressions).
- Self-esteem: Skin appearance, color, and integrity significantly affect body image and mental health.
- Chronic conditions: Diseases such as acne, psoriasis, and vitiligo can have profound psychosocial impacts beyond their physical manifestations.
8. Summary Table
| Function | Mechanism | Clinical Relevance |
|---|---|---|
| Protection | Mechanical (keratin, collagen), Chemical (acid mantle), Biological (Langerhans cells) | Barrier defects cause infection, dehydration, photosensitivity |
| Thermoregulation | Vasodilation/constriction, eccrine sweating, piloerection, subcutaneous fat | Anhidrosis, hyperhidrosis, heat stroke, hypothermia |
| Sensation | Meissner, Pacinian, Merkel, Ruffini corpuscles; free nerve endings | Neuropathy, chronic pain, anesthesia dolorosa |
| Excretion | Sweat (urea, NaCl), sebum, cerumen | Uremic frost in renal failure, body odor |
| Vitamin D Synthesis | UVB converts 7-dehydrocholesterol to D3 | Rickets, osteomalacia, supplementation needs |
| Social/Psychological | Facial expression, appearance, body image | Psychosocial impact of dermatological disease |
